Resonance, damping and frequency response
This chapter is relevant to Section G6(ii) of the 2023 CICM Primary Syllabus, which asks the exam candidate to "describe the principles of measurement, limitations, and potential sources of
error for pressure transducers, and their calibration". The concepts of resonance and damping fall neatly into the category of limitations and potential sources of error. For a variety of sensible reasons, the college examiners have clearly prioritised this topic, and it appears in multiple past paper questions:
- Question 12 from the first paper of 2020
- Question 17 from the second paper of 2017
- Question 12 from the first paper of 2015
- Question 24 from the second paper of 2012
In spite of how common these questions have been, they are still done very poorly, with a pass rate ranging between 25% and 33%. The topic had also come up once in the Part II exam, in Question 11.2 from the first paper of 2010 where candidates were expected to comment on the "fidelity" of the pressure transducer system which was shown undergoing a fast flush test. The interpretation of fast flush tests and other practical matters related to the "fidelity" of the arterial transducer system are discussed in the section on arterial line dynamic response testing. In many ways, this is a huge self-indulgent redux version of that chapter. From the standpoint of exam preparation, it would be possible to skip this entire chapter and only review the brief square wave test section in the Fellowship Exam required reading chapter on the information derived from arterial line waveforms.
In summary:
- Natural frequency: the frequency with which a system will oscillate after it is disturbed by a nonsustained stimulus
- Resonance: the amplification of signal when is its frequency is close to the natural frequency of a system
- Resonant frequency: the frequency at which the amplitude of the response of the system to a forced vibration is a maximum (in an undamped system, this is the same as the natural frequency)
- Harmonics: sinusoidal waves with a frequency that is a multiple of the fundamental frequency of a periodic signal (in this case the pulse).
- Damping: the reduction in the magnitude of oscillations by the dissipation of energy. In the case of blood pressure transducers, damping is affected by:
- Increasing radius of the tubing (decreases damping)
- Increasing elasticity of the transducer system (increases damping)
- Increasing density of the fluid (decreases damping)
- Increasing length of tubing (increases damping)
- Damping coefficient: a parameter in the equation of motion that defines the rate at which energy is dissipated in a system due to the presence of damping forces
- Critical damping: the smallest value of damping coefficient that yields aperiodic motion (where the system comes to rest without a single oscillation)
- Damping ratio (ζ): the ratio of actual damping coefficient to the critical damping coefficient, where:
- ζ=0 is undamped and oscillates forever
- ζ<1 is underdamped
- ζ=1 is criticall damped
- ζ>1 is overdamped
- Optimum damping ratio: around 0.64-0.7
- Maximises frequency response
- Minimises overshoot of oscillations
- Minimises phase and amplitude distortion
- Corresponds to 2-3 oscillations following an arterial line flush test
- Effect of damping on invasive blood pressure measurement:
- Underdamping: amplified waveforms, widened pulse pressure (higher systolic and lower diastolic)
- Overdamping: narrowed pulse pressure (underestimated systolic, overestimated diastolic), and slurred broad waveforms with loss of dicrotic notch
- MAP remains the same
Of the references used to create this chapter, the most striking feature is that there are multiple articles, all titled "Principles of pressure transducers, resonance, damping and frequency response", all published in Anaesthesia & Intensive Care Medicine over the course of the last twenty years by different authors- Stoker (2004), Wilkinson & Outram (2009), Gilbert (2012), Back & Carroll (2023). There are only two possible outcomes from something like this, each equally baffling: either the authors each found a fresh distinct take on this supposedly fixed and inflexible physics topic which was sufficiently different to the other authors, or the journal printed essentially the same paper under different names every three years. On closer analysis, each article basically presents some of the same information, but not all of it, such that none of them are by themselves sufficient to understand the topic; one needs to skip from Gilbert (2012) to Back & Carroll (2023) or Wilkinson & Outram (2009) to get a clearer explanation of wave harmonics, and then to Stoker for some basic definitions, and back to Gilbert (2012) for a good bibliography of references. The one shared feature is that these papers, as well as practically everyone who publishes on this topic, all seem to refer to Kleinman (1989), an excellent piece which is by far the best explanation of the maths involved. And if rigorous mathematical proof is the really the secret key to the reader's grasp of this material, then we should all be grateful to Ivor Popovich, who contributed this excellent reference from the University of Washington's physics program as well as invaluable corrections that stimulated a renovation of this old page.
But if you're allergic to maths and find calculus as profoundly triggering as the author does, then Moxham (2003) is probably the most useful single reference one can offer for this topic, and will satisfy the majority of readers. In general, one can find the best explanations of these matters in textbooks of anaesthesia, and if the reader is not satisfied with Moxham or Gilbert they can be referred to Miller's Anaesthesia (Chapter 40 in the 7th edition). The reader, unfortunately, cannot be referred to any of the official CICM textbooks for this topic, because neither Davis & Kenny nor Middleton have a satisfactory explanation (instead there is only explicit teaching). If the reader's need for detail is still somehow unsatisfied one can point them towards Jonathan B. Mark's Atlas of Cardiovascular Monitoring. This legendary book is somehow (accidentally?) available for free from the University of Montreal. It is definitive; when you see a pressure waveform in almost any other textbook, most frequently you will find that the images have been borrowed from Mark. Or from Leslie Geddes' Handbook of Blood Pressure Measurement (1991), which is the Iliad of haemodynamic monitoring literature, worth reading for the quality of the writing alone. The author's vocabulary and command of language betray a scientific upbringing from an earlier time, when education and culture could be expected to coexist.
The pressure transducer system as a harmonic oscillator
The fluid between the artery and the transducer can be described as a simple harmonic oscillator, analogous to a pendulum or a mass hanging on a spring. When the pendulum is displaced, it undergoes simple harmonic motion: i.e. it oscillates around the equilibrium point. The mass hanging on a spring will oscillate up and down when disturbed, like a bungee jumper. The literature abounds with analogies (weights on springs, rubber balls dropped from a height, pendulums), but the best one would probably have to be the one from Kleinman (1989), which describes the motion of an object in a circle at a constant speed, projected on a line. The path traced by this object would be easier to visualise if the object was a scribe at the edge of a rotating wheel and it was drawing a waveform on a moving strip of paper, as below:

Because maths, we can express the speed of this rotating object as angular frequency in radians per second, i.e. it is not velocity in the conventional sense but instead the rate of change of the angle per unit time, conventionally expressed using the lower case omega (ω). The use of radians allows us to generalise the period of this rotation: it repeats every 2π radians (because 2π radians is 360º). Thus,
ω = 2π/T
where T is the period, time to complete a full rotation. This means the frequency (f ), of this periodic motion is
f = ω / 2π
which is really just the exact same equation where both sides were divided by 2π to solve for T, or f is the reciprocal of T, a frequency being something over time (1/T). , one will find this explanation uses the term natural frequency (fn), rather than just frequency, which is the frequency with which the system will oscillate when left to its own devices after it is disturbed. Natural frequency would have to be expressed in terms of some kind of time or space (eg. in Hz or cycles per minute), which is not necessarily desirable. Instead, one may wish to use the angular natural frequency, conventionally represented as ω0 or ωn. This is usually represented by the equation
ω0 = √(k/m)
where m is the mass oscillating, and k is a constant that describes the stiffness of the system, otherwise known as Hooke's constant. That means,
fn = ω0 / 2π
or, borrowing the expanded solution of ω0 to incorporate some physical properties of the oscillating object, we can rewrite this as:

And if you are going to incorporate physical properties, you may as well reflect a little on the original purpose of this chapter, and try to reestablish some kind of meaningful clinical focus by representing the stiffness k as the stiffness of the arterial line transducer circuit, and the mass m as the mass of fluid in the tubing. If the circulatory system and transducer tubing were perfectly frictionless, the relationship would simply be:

The importance of the natural frequency
Why does any of this matter, the reader gurgles as they choke on equations. Well: the natural frequency of a system plays a role in how the system responds to repeated and regular externally applied forces, for example the pulse. Consider the system as it sits there after the last impulse, oscillating and slowly coming to rest. If another stimulus occurs (a new wave arrives), it interacts with the existing waveform. If the new waves arrive at the same frequency as the natural frequency of the system, the peaks will coincide and the sum of the amplitudes will be greater (the peaks will be higher). Similarly, the troughs will be lower. This tendency of system to oscillate with greater amplitude at the natural frequency than at other frequencies is resonance, the effect of amplification of vibrations by reinforcement from other vibrations.
The frequency of the pulse, for example, is 1 Hz at a heart rate of 60. If the natural frequency of your pressure transducer is also 1Hz, each peak of the pulse pressure wave can coincide with a peak of the system's own oscillation, increasing the amplitude of the measured peaks (systolic pressure) and decreasing the amplitude of the troughs (diastolic pressure).

From this, it follows that this system will resonate vigorously with the pulse, and give a wildly overestimated pressure. Conversely, if the pulse and the system are perfectly out of sync (troughs of pulse pressure falling on peaks of the natural resonance) the waveform will be perfectly flat. This is obviously not going to be a useful measurement device.
Generally speaking, at the bedside you will find most commercially available arterial line systems have a natural frequency somewhere in the range of 35-40 (Fujiwara et al, 2015), though many studies mentioning this will instead reference Schwid et al (1988) whose ancient dieselpunk art line kits had a natural frequency of 10-25 Hz. Even this might seem like overkill (even the wildest tachycardia will usually not exceed 4Hz), but in fact it is necessary because the arterial pulse waveform is not a sine wave, but a complex wave with multiple peaks and troughs, which can be expressed as the sum of many superimposed waves of different frequencies.
Fourier analysis of physiological pressure waves
Most of the physiologically relevant waveforms are not sine waves but rather complex waves. Fourier demonstrated that any complex waveform can be constructed from a number of simple sinusoidal waveforms, the frequency of which is some multiple of the frequency of the complex wave (which is called the fundamental). The other component of the calculation is a constant, which is a mean value of the waveform over the duration of its cycle (in this case, this is the mean arterial pressure).
Thus, for arterial pressure measurement, the complex arterial pressure waveform is composed of one fundamental waveform (that's the pulse rate) and numerous other higher frequency waveforms (harmonics). At a heart rate of 60, the fundamental frequency is 1Hz, and the harmonic frequencies are 2Hz, 3Hz, 4 Hz, et cetera. The lower frequency harmonics tend to have the higher amplitude.

By adding all these waveforms together, one may approximate the true shape of the pulse waveform, which is recognizable as an arterial pulse waveform. Well, no. That idealised graphic is not what it looks like when you go full nerd and generate sine waves in a spreadsheet.  It looks more like the Google-coloured graph on the left, which is less recognizable as an arterial waveform, but is more scientifically accurate.
In actual fact, whenever you see these superimposed harmonics in a textbook, it is only the first and second, and the source of the image is usually Geddes (1991). It is usually in black and white, and usually has a little rectangular box to illustrate the resemblance between the summed waveform and the shape of the arterial pulse. In this graph, the fundamental waveform is added to 63% of the second harmonic. (i.e. the amplitude of the fundamental is taken as 100%). As far as can be reasonably reconstructed from historical records, Geddes and all subsequent authors who keep re-using this image do so not because it represents a realistic model of the human arterial pressure wave, but because the addition of these sine functions conveniently produces a waveform with a recognisable dicrotic notch.
So, what do the harmonics of the arterial pulse really look like? For this, one needs to look to an earlier, more honest time. The best representation of this comes from a 1949 book by Anders Tybjaerg Hansen, titled "Pressure Measurement in the Human Organism". It is reproduced here, with no permission whatsoever.

Six harmonics with their respective amplitudes are represented here, their summed waveform indeed looking very familiar and arterial-like. The book itself is so old that there is no digital copy anywhere within sight. It was published as a supplement of Acta Physiological Scandinavica. Without this, it is impossible to determine how Hansen came up with these phase shifts and amplitudes, except to guess that in the 1940s he must have laboriously and manually performed a Fourier analysis of recorded waveforms to plot the six harmonics.
How many harmonics does one need to analyse, and why
The answer depends on how much "resolution" is required. Realistically, you could make do with just five harmonics- that would be enough to have an accurate representation of the pulse pressure - but at least eight harmonics need to be analysed and added together in order to reproduce the pulse waveform with enough fidelity to discern such structures as the dicrotic notch. The higher you go in frequency of harmonics, the lower their amplitude, and therefore the smaller their contribution to the summed waveform - so to analyse anything beyond the tenth harmonic is pointless, as it will not add very much to the shape of your pulse waveform.
The natural frequency of the transducer system needs to be much higher than the fundamental frequency of the pulse wave. With a low natural frequency, the fundamental frequency or some of the first few harmonics would end up being amplified by resonance, and because these are already high-amplitude waves the effect on the summed waveform would be quite significant. If the natural resonance of the transducer system is closer to the eighth harmonic, resonance will still amplify that waveform, but because the amplitude of this harmonic is very low, the effect on the summed waveform will be minimal. Ergo, transducer systems need to have a minimum natural frequency at least eight times the expected maximum frequency of the expected fundamental frequency of the measured system. Most commercially available systems analyse eight harmonics; thus to maintain accuracy for pulse rates up to 180 bpm (3 Hz), the natural frequency of the system needs to be at least (3 × 8) = 24 Hz. Generally speaking commercially available systems have a natural frequency well above this value (usually 200Hz) but we interfere with this by adding tubing, stopcocks, cannulae, three-way taps and air bubbles. How much interference this causes can actually be measured - you can assess the natural frequency of the completed arterial line transducer setup by doing a fast flush test.

The pressure bag flush being released is similar to the ball being dropped or a spring being released, in the sense that it sets into motion an oscillation of the arterial transducer set, allowing its natural frequency to be observed. A system which has a low natural frequency will have a longer time interval between the peaks, and will lose a lot of the fine detail from the arterial line waveform. This loss of detail is referred to as "damping", and arises due to the fact that the transducer system has to operate in a non-ideal world, completely unlikely the slippery universe of idealised frictionless objects.
Damping
In a totally ideal frictionless system, after one solid kick the system would just continue to oscillate forever at its natural frequency. Chris Meyer from University of Washington described the "elegant beauty and simplicity" of this periodic motion as "to a certain extent boring" in his excellent set of lecture materials from 2008, presumably because he prefers the nailbiting excitement of a decaying function. In the real world we have conflict and drama, and anything that oscillates will squander its energy on having to bully neighbouring atoms out of the way as it moves.

This is damping, which has several similarly worded definitions, of which the least verbose is probably:
"the reduction in the magnitude of oscillations by the dissipation of energy"
That energy can be dissipated in a whole range of predictable ways. For example in the arterial pressure transducer, the energy is lost by the interactions of the fluid with itself and with the walls of the tubing. These factors are familiar Poiseuillean variables, which plug into the equation as follows:

where
- the r in πr2 is the radius of the tubing
- E is the volume elasticity of the system, i.e. the change in pressure exerted by the transducer membrane and the walls of the circuit on the fluid per change in volume of the fluid.
- ρ is the density of the fluid
- L is the length of the tubing
This is the fn being altered, i.e. damping is decreasing the natural frequency of the system by making it oscillate more slowly. That should make intuitive sense (friction makes things slower, the rotating object moving through the molasses of neighbouring matter if you prefer to return to that circular motion analogy). Energy is lost, and so it also feels logical and intuitive that damping should decrease the amplitude of waves (a pendulum under water will be drawing smaller and smaller arcs, compared to one in air).
Which component is most important? Generally, the diameter of the tubing has the greatest effect on damping; damping increases by the third power of any decrease in the diameter of the tubing. In other words, narrower tubing increases damping by a disproportionally large degree. Which is to say, narrow tubing results in lower amplitude waveforms. One can model this. Say, the tubing decreases in diameter by 33%. The damping will increase by 135% (and the frequency will shift by a relatively small value). In short, you want a short fat tube.

Damping is therefore a major influence on the performance characteristics of a device that measures a harmonically oscillating subject, and seems like something we should be able to characterise more precisely than to simply say that Poiseuille equation things make the waveform more lazy. The need to be more scientific about this is reflected in the CICM exams, where optimal damping, damping ratio and damping coefficient are sometimes asked about (eg. in Question 17 from the second paper of 2017). The concise definitions for these terms are already in the grey box at the beginning of the chapter, but assuming the reader has made it this far, they are likely looking for a longform explanation. Therefore:
Damping coefficient, damping ratio and critical damping
The reader trying to understand the physics of damping is constantly bedevilled by the Babylonian language crisis of damping terminology, which is muddled constantly even by respected professionals. The conventional notation for damping (lowercase zeta, ζ) is used by many resources (Wikipedia) to refer to the damping ratio, whereas Gilbert (2012) and Kleinman (1989) use it to signify "damping coefficient" while they actually mean damping ratio, and Wilkinson & Outram (2009) for some reason use β (the stiffness coefficient of the Rayleigh damping model) instead, call it damping coefficient, while they actually mean damping ratio, and don't explain how α and β differ from c or ζ except to say that "the mathematical formula is complex and can be confusing". To remove ambiguity from the reader's mind, let us be extremely clear: these are all different things.
Referring to something widely considered definitive (Encyclopedia of Vibration, 2001),
Damping coefficient (c) is "a parameter that defines the rate at which energy is dissipated in a system due to the presence of damping forces"
which plugs into the equation of motion
mẍ(t) + cẋ(t) + kx(t) = 0
where ẍ(t) is acceleration, ẋ(t) is velocity, m is mass, k is stiffness and c is the damping coefficient. It is expressed in in Newton second per meter or kilograms per second. Whereas:
Damping ratio (ζ) is"a dimensionless parameter for describing the amount of damping in a system"
and it i defined by the equation
ζ = c/ccr
where c is the actual damping coefficient and ccr is the damping coefficient of critical damping. Thus, ζ represents a ratio (sometimes a percentage) of critical damping, describing the amount of damping in the system. Which means we need to now define critical damping:
Critical damping (ccr) is "the numerical value used to nondimensionalize damping parameters to produce a damping ratio"
or
"that value of damping that separates oscillation from nonoscillation of the free response"
or
"the minimum amount of damping that a spring-mass damper system can have and not vibrate"
and it is defined by the equation
ccr = 2mω0 = 2√(mk)
where oscillating mass m comes to rest because of stiffness coefficient k, at its natural frequency ω0.
Another good way to phrase this concept would be to say that "a critically damped system represents a system with the smallest value of damping coefficient that yields aperiodic motion", which is a fancy way of saying that at ccr it does not boing. Following from this, it would make intuitive sense that any undamped system (i.e. where the damping coefficient is zero) would boing forever, and any damping coefficient higher than the critical damping value would produce a system which returns to its baseline state non-instantaneously, and the higher coefficient the slower it goes.
Optimum damping ratio
Following from the discussion of the optimum range of frequencies (was it 24 Hz?), one would have to conclude that some damping is good, as one does not wish to have an extremely resonant system. And from that statement it follows that, if some damping is good, then there must be some level of damping which is "best", for any given system. It is often said that for arterial transducer systems the damping ratio of around 0.64-0.7 is ideal, this is a mathematically derived value at which the system has a minimal ITAE (integral of time-weighted absolute error) value, a tuning criterion for controller performance. ITAE is designed to measure the relationship between the error of the reported result, and the time it takes to acquire the result, penalising a larger later error.
Consider: if the arterial line transducer is critically damped, it will never overshoot or undershoot by resonating with its natural frequency against the input frequency. The measurement will not oscillate, it will be true and accurate, but it will take time to get to the true reading, approaching it asymptotically. For an extreme example, if an arterial line transducer gradually arrived at within 0.000001% of the true value over the course of six minutes, nobody would find this increase in accuracy to be a satisfactory compromise with speed. Therefore we tolerate error to get a faster reading. On the other hand it would not serve our purposes to have a system that instantly blurts out a wildly exaggerated take whenever it is asked for its opinion. Ergo, some balance between these variables must exist. That balance is represented by the ITAE which assigns a decaying value to both speed and error.
However, to get into a discussion of ITAE would risk of losing the momentum of one explanation by having to introduce new variables and start another. Fortunately, this balance can be represented graphically without resorting to such things. The reason to bring this up is because most resources at this point will typically throw the reader into a diagram that plots amplitude ratio versus frequency ratio for systems with different damping ratio values to demonstrate exactly how 0.64-0.7 is the ideal ζ value. The diagram is invariably some modification of this excellent original from Fry (1960), and it would be a shame to miss an opportunity to butcher a classic:


To go through this systematically: the x-axis is the frequency ratio, f/fn - the ratio of the driving input frequency (f), eg. the cardiac pulse, and the natural frequency of the transducer (fn). Where f = fn, i.e at the x-axis value of 1.0, the maximum amount of resonance is to be expected (as the natural frequency and the input frequency are the same and their peaks and troughs should have the maximum effect on amplifying or cancelling each other). At this point in the x-axis, for a completely undamped system, the effect on the amplitude should be maximal.
That brings us to the amplitude ratio, which is the ratio of the output amplitude to baseline amplitude (which is whatever the amplitude would be if the frequency was stable). Output amplitude increases as the input frequency approaches the natural frequency and the peaks and troughs of the input line up with the peaks and troughs of the baseline. The ratio of the output amplitude divided by the baseline amplitude will therefore be highest there. Where the output amplitude and baseline amplitude are the same, i.e. where the ratio on the y axis is 1.0, there is no amplification whatsoever: waveforms going into this transducer are left completely unchanged, as there is no resonance. That seems like a desirable characteristic for a measurement device, as we generally depend on these to report the data faithfully without embellishing it with their exaggerations.
From this, it follows that the optimum damping ratio would be one which remains reasonably flat and closest to an amplitude ratio 1.0 over the range of frequencies which we consider desirable, in this case 0-24 Hz (say, up to 30 HZ, to capture ten harmonics). As the commonly available arterial line transducers mostly have a natural frequency in the 35-40 Hz range, it would make sense to focus on the 0.0-0.7 range of frequency ratios, and wish for a damping ratio that is flattest in that range. As you can see, the best candidates for this are ζ values around 0.64 t0 0.707.

So. the wave amplitude is the least inaccurate within that range. Additionally, some resources mention that "phase shift" or "phase lag" is minimised. One finds this in Brandis and in Thomas Alured Faunce's excellent Annotated Syllabus, of which all of Deranged Physiology is basically a gushing fanfic. The phase distortion these sources are referring to is the tendency of pressure waves with different frequencies to propagate with different velocities. Obviously having your fundamental harmonic arrive completely out of sync with the others would affect the summed waveform perceived by the transducer, and the accuracy of the measurement would suffer. Now, it is fair to say that this cannot be completely avoided (all transmission media are imperfect in this way, and the longer the tubing the worse it gets), but one may minimise it if the phase distortion is at least proportional to the frequency ratio (in which case the least laggy frequencies are also those closest to the fundamental). This is also something observed at the 0.64-0.707 range of damping coefficients, as demonstrated by another diagram from Fry:

Though it is also fair to say that the difference in phase distortion between damping ratios of 0.5 and 1.0 is fairly minor.
So which is it, 0.64 or 0.707? The choice appears to be something of a judgment call. The damping ratio ζ = 0.707 is special because it never overshoots, which means the fundamental harmonic and other high-amplitude waves that contribute the most to the summed arterial pressure waveform will be faithfully reported. On the other hand, the drop in amplitude ratio for the higher frequencies would cause a loss of the finer detail from the arterial trace, which may or may not be meaningful depending on your application. The 0.64 value for ζ has a slight resonant frequency peak at a middle range of frequencies and would produce trivially exaggerated amplitudes for the middle range of frequencies which some might consider acceptable as a tradeoff for a nicer-looking waveform.
Does any of this really matter to the brutal daily realities of the coalface intensivist? The reasonable person would agree that in the smoky trenches of critical care basically nobody would ever be hanging their professional reputation on decisions that are made on the basis of observing the subtle shapes hidden in the arterial pulse. Still, there are situations when one might need to have confidence in the faithful representation of the dicrotic notch; for example when one is assessing the timing of the IABP balloon inflation. But if there is a scientific answer to this question, the easily googleable literature does not present it to the casual reader. None of the papers mentioned in the recommendations at the beginning of this chapter, nor any of the official CICM textbooks, list even a single reference to explain their choices, which are:
| Literature reference | Optimum damping ratio |
| Kleinman (1989 | 0.64 |
| Moxham (2003) | "Around 0.7" |
| Stoker (2004) | "up to two-thirds of the natural frequency of the system", i.e 0.6666666 |
| Wilkinson & Outram (2009) | 0.64 |
| Gilbert (2012) | "between 0.6 and 0.7" |
| Back & Carroll (2023) | 0.64 |
| Physics in Anaesthesia, Middleton (2021) | no mention whatsoever |
| The Physiology Viva, Brandis | 0.64 |
| The Annotated Syllabus, Faunce | 0.64 |
| Basic Physics and Measurement in Anaesthesia (Davis & Kenny, 1995) | no mention whatsoever |
In short, we want slightly underdamped systems. But damping is not all bad:
Frequency response
The frequency response of a system is the relationship between the frequency of the measured waves and the amount of amplitude amplification which might occur as the result of resonance. It can be represented on an amplitude/frequency graph:
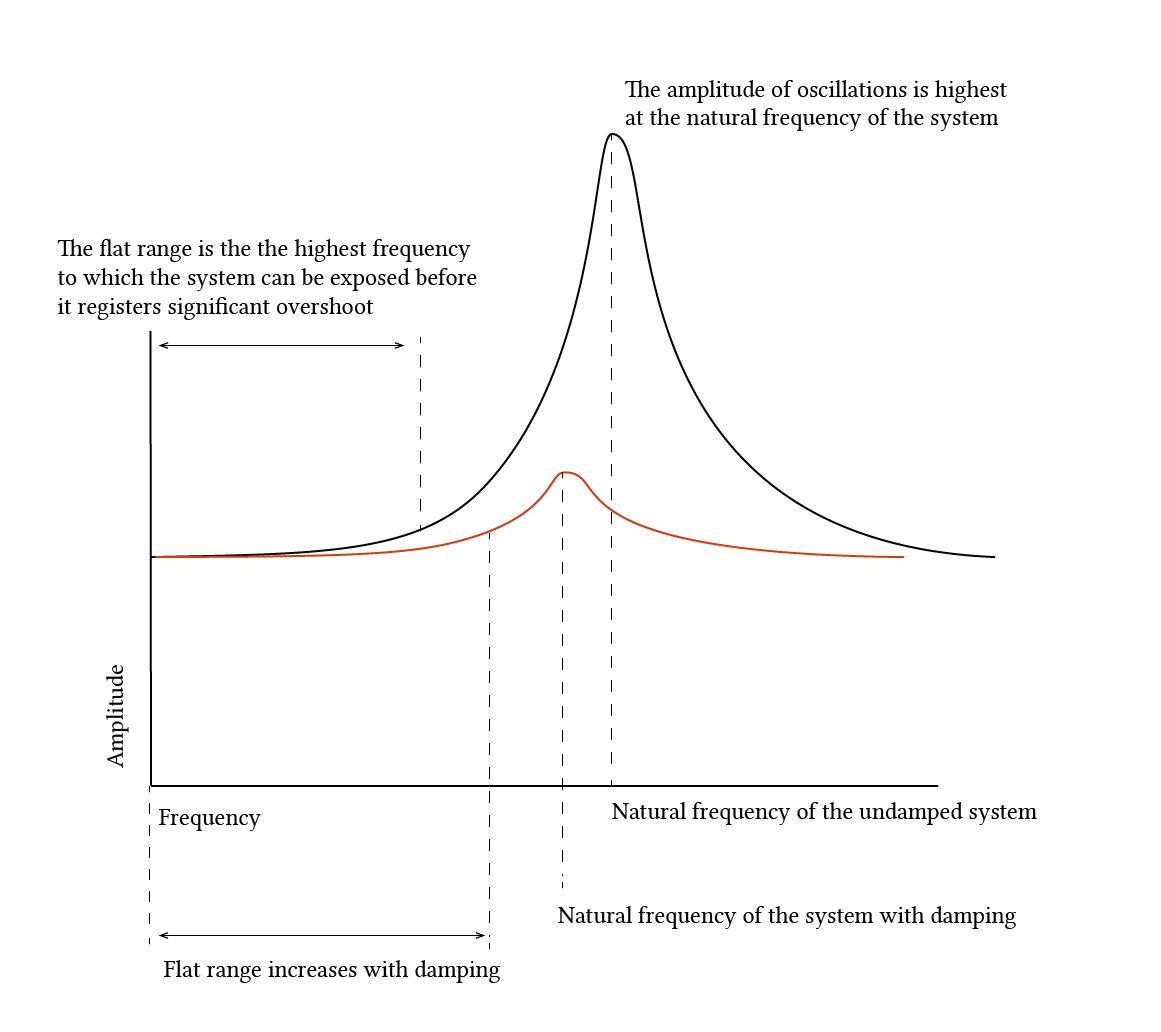
From this, the beneficial effects of damping become clear. The damped system has a larger range over which there is little amplitude increase with increasing frequency, and even at its natural frequency the amplitude change is smaller. As a result, the measured pressure waves will not be overestimated as much. In an ideal system, all frequencies of clinical interest will lie within this flat range. For an arterial line, for example, that would be all eight harmonics - i.e. there should be little amplitude change up to a frequency of around 24 Hz, if the heart rate is 180.
So, how do you know what the frequency response of a system is? Well. If you know what the natural frequency of the system is, you can predict that this is where the peak of the amplitude/frequency graph is going to fall, and from that, it is possible to predict where the flat range will be.
Frequency response range
With a very low natural frequency, the flat range is very narrow, and higher frequency waves will be distorted by resonant amplification. On the other hand, with a very high natural frequency, the system will not distort any waveforms within a clinically relevant range.

Observe above. Two systems, equally underdamped. One has a natural frequency of around 7Hz, well inside the clinically relevant range. Even when severely damped, the higher frequencies would be distorted and amplified, giving rise to inaccurately raised peaks of pressure. In contrast, the system with the natural frequency of 70 Hz could have any damping coefficient whatsoever- within the relevant range of frequencies it is always going to give results unaffected by resonance. This dependence of optimal damping ratio on natural frequency can be represented in a graph, which was first presented by Gardner et al (1981). A heavily modified version is presented here:

A clinical tl;dr for this would summarise this as:
- Underdamping leads to overshoot. A system with minimal damping will reverberate, the natural frequency of the system will amplify the measured waves and therefore the pressure registered by the tranducer will be higher than the actual pressure. Sharp jagged waveforms will be produced.
- Overdamping will produce underestimated values and slurred broad waveforms. With overdamping, some of the higher frequency harmonic waveforms will be lost (remember that these are the waveforms which already have a lower amplitude; with more damping their amplitude disappears to near zero).
The changes in waveform shape can be illustrated in a situation where the damping coefficient of a system is gradually increased while oscillations are occurring - in this case, a dog's pulse. Because damping increases dramatically with decreasing tube diameter, one may conveniently model an increasing damping coefficient by tightening a clamp over the arterial line tubing, just as Geddes et al did in 1984:

Note how first, the dicrotic notch is lost (because it is produced by high frequency, low amplitude elements). Then, the waveform begins to flatten as the amplitude of even the low-frequency waves is affected. At last, with the tubing clamped, the waveform flattens at the mean arterial pressure.
Testing for frequency response and damping
For arterial line pressure transducers, the "fast flush test" is the clinical bedside test which is used to assess the natural frequency of the system. To return to the model of the transducer system as a simple harmonic oscillator, this "fast flush" is dropping the ball from a height, or giving the pendulum a gentle nudge. Then you watch it and wait for it to swing through a few oscillations, and measure the frequency. In effect that is what you're doing when you open the fast flush valve on the arterial line transducer set.

The "bounce" of oscillations after a fast flush can be recorded on graph paper, vellum parchment or wet clay if you have a dislike of computers. More likely, as an intensivist you're an intensely technophilic organism, and prefer to measure the time interval between oscillations with the convenient digital calipers integrated into most monitoring software packages. You'd get a number, typically in milliseconds. That can be converted to a frequency in Hz (the number of oscillations per second). This is the natural frequency of your transducer system. If the natural frequency is over 30-40 Hz, you'd be able to confidently say that the clinically relevant range of frequencies (0-24 Hz) is well within the flat range of this system, and the pressure values you are recording are accurate.
References
Moxham, I. M. "Physics of invasive blood pressure monitoring." Southern African Journal of Anaesthesia and Analgesia 9.1 (2003): 33-38.
Stoker, Mark R. "Principles of pressure transducers, resonance, damping and frequency response." Anaesthesia & intensive care medicine 5.11 (2004): 371-375.
Gilbert, Michael. "Principles of pressure transducers, resonance, damping and frequency response." Anaesthesia & Intensive Care Medicine 13.1 (2012): 1-6.
Wilkinson, M. B., and M. Outram. "Principles of pressure transducers, resonance, damping and frequency response." Anaesthesia & Intensive Care Medicine 10.2 (2009): 102-105.
Back, Morgan, and Craig Carroll. "Principles of pressure transducers, resonance, damping and frequency response." Anaesthesia & Intensive Care Medicine (2023).
Kleinman, Bruce. "Understanding natural frequency and damping and how they relate to the measurement of blood pressure." Journal of clinical monitoring 5 (1989): 137-147.
Meyer, Paul-André. "The harmonic oscillator." Math 24: Ordinary Differential Equations (2008); Washington U. https://staff.washington.edu/seattle/physics227/reading/reading-2b.pdf
Schwid, Howard A. "Frequency response evaluation of radial artery catheter-manometer systems: sinusoidal frequency analysis versus flush method." Journal of clinical monitoring4.3 (1988): 181-185.
Gardner, Reed M. "Direct blood pressure measurement—dynamic response requirements." Anesthesiology: The Journal of the American Society of Anesthesiologists 54.3 (1981): 227-236.
Fujiwara, Shigeki, et al. "Effect of planecta and ROSE™ on the frequency characteristics of blood pressure-transducer kits." Journal of Clinical Monitoring and Computing 29 (2015): 681-6
O'Rourke, Michael F., Alfredo Pauca, and Xiong-Jing Jiang. "Pulse wave analysis." British journal of clinical pharmacology 51.6 (2001): 507.