The alveolar gas equation
This chapter is most relevant to Section F9(iii) from the 2023 CICM Primary Syllabus, which expects the exam candidates to "understand respiratory equations that describe ventilation, perfusion, blood flow and respiratory mechanics". Though there are no specific CICM primary or Fellowship exam questions which ask about this equation directly, virtually every ABG question requires the candidate to consider the A-a gradient, making the alveolar gas equation essential. In short, this equation describes the concentration of gases in the alveolus, and thus allows us to make educated guesses as to the effectiveness of gas exchange. One can use this to calculate the tension-based indices of oxygenation, such as A-a gradient or the a/A ratio (which is expressed as a percentage). The ABG machine frequently does this work for you, provided you have entered the FiO2 and have specified that your sample is "arterial". The result is usually reported as pO2(a/A).
The equation itself is so ubiquitous in medicine that high quality resources discussing it are common and easily available with even the laziest search strategy. The original paper ("A theoretical study of the composition of the alveolar air at altitude" by Fenn, Rahn and Otis from 1946) is, interestingly, somewhat hard to track down, and therefore worth linking to, purely out of respect. Among modern resources, the best article describing the derivation of the equation is Wang et al (2020).
The physical basis for the alveolar gas equation
The equation is necessary because there is no convenient way to sample alveolar gas. At the same time, it is gas, and therefore can be expected to behave according to some fundamental laws. Specifically, we are talking about Dalton's law, which states that
The total pressure of a mixture of gases is equal to the sum of the partial pressures of all of the constituent gases
In this scenario we can be confident that the total pressure of the mixture of gases in the alveolus is going to be basically the same as atmospheric pressure, as the alternative hypothesis would have us either explode or implode. Let us represent this total pressure as:
Patmos = 760 mmHg.
Next, the pressures of the constituent gases. Of these, some may be predictable. For example, the human body is usually at around 37 degrees, and the gas mixture is predictably humidified up to 100% humidity by its passage though the airways, such that the absolute water content of the alveolar gas mixture is predictably 44g/L. At this temperature, water vapour exerts a pressure of 47 mmHg (this, by the way, is Gay-Lussac's law). Thus, in a mixture of gases where there is 44g/m3 of water vapour present, the water vapour will exert a partial pressure of 47 mmHg.
That leaves only 713 mmHg of partial pressure for the rest of the gases. This is because the inhaled gas mixture does not have the water vapour added to it like a sum, i.e. the partial pressure of the alveolar gas is not 807 mmHg (760 mmHg + 47 mmHg). Rather, the inspired gas mixture is diluted with the addition of water vapour until the mixture is about 6.2% water vapour and 93.8% original gas mixture. The partial pressure exerted by the remains of the original atmospheric gas mixture is therefore 713 mmHg, and the total alveolar gas mixture can now be represented as:
Patmos + PH2O = 760 mmHg
Of this remaining gas mixture, the vast majority would surely have to be nitrogen and oxygen. The human body neither generates nor consumes significant amounts of atmospheric nitrogen, which means the alveolar gas should contain approximately the same amount of nitrogen as the ambient atmosphere. Thus, the nitrogen content of this 713 mmHg should be 78%, and the oxygen content should be 21%, because the Earth titrates its FiO2 to 21% (or, more precisely, 20.9%).
Why does it do that? Thankfully, this would not be the first ridiculous digression in physiology. For instance, John F. Nunn has written a chapter (Chapter 1 of Nunn's Respiratory Physiology) about the atmosphere. In it, he is grateful that greenhouse gases have allowed the existence of surface water for the last 4000 million years, and he laments that the sun "proceeds remorselessly towards becoming a red giant, which will ultimately envelop the inner planets". Unfortunately the rest of the textbook proceeds soberly along a straight and predictable path. A better introduction into the subject would probably be afforded by The Chemical Evolution of the Atmosphere and Oceans, by Heinrich D. Holland. The author confesses on page 2 that "the range of topics considered in the book is uncomfortably large", and that due to the mass of information "chaos was a continuous threat" during the assembly of the manuscript. In any case, for a monograph written between the years 1968 and 1981, this is a fine work. It is deserving of attention from anybody who has finished with their final CICM exams and still has some enthusiasm for the written word.
Anyway: to digress no further, let us again return to the idea that the alveolar gas mixture should contain similar proportions of oxygen and nitrogen to the atmosphere. In other words,
PN2 + PO2 = 713 mmHg
Or rather,
PN2 + PO2 + PH2O = 760 mmHg
The partial pressure of nitrogen is never directly measured because nitrogen is boring and is of no interest to anyone, except in the context of trying to measure dead space by the Fowler method. There is about as much nitrogen in the body fluids as there is in the alveolar gas mixture, and it is neither created nor consumed. The nitrogen concentration is therefore left out of the equation. Oxygen, on the other hand, is both interesting clinically, and variable in its concentration. Assuming that there is nothing in the inspired gas mixture other than oxygen, nitrogen and water vapour, the equation that describes the concentration of oxygen in while ignoring the unknown amount of nitrogen looks like this:
PO2 = FiO2 × (Patmos - PH2O)
This gives us 149.73 mmHg as the partial pressure of oxygen, and that would be the oxygen concentration of the inspired gas mixture. However, the alveolar gas also contains CO2. This also needs to be incorporated into the gas equation. Like water vapour, it is incorporated into the partial pressure fractions, which means it eats into the pressures of oxygen and nitrogen equally. If one were breathing 100% FiO2, the PCO2 would be subtracted directly from the PO2, i.e. a 10mmHg increase in PCO2 would result in a 10mmg Hg decrease in PO2. But while breathing room air, all fractions are reduced proportionally, i.e. that 10mmHg increase in PCO2 causes a 7.9 mmHg decrease in PN2 and a 2.1 mmHg decrease in PO2, preserving this relationship:
PO2 + PH2O + PCO2 + PN2= 760 mmHg
Or, incorporating FiO2, considering we do not know what the PO2 is:
FiO2 × (Patmos - PH2O) + PH2O + PCO2 + PN2 = 760 mmHg
Or
FiO2 × (Patmos - PH2O) + PCO2 = (760 mmHg - PN2 - PH2O)
If one were for whatever reason calculating the alveolar nitrogen equation, PN2 here should be
(1-FiO2) × (760 mmHg - PH2O)
But we do not care about the PN2, and moreover we are now also bored with the water vapour, as we are mainly interested in the alveolar oxygen concentration. Fortunately we do not need to involve them because they are fairly constant and predictable. We can therefore eliminate both of them from our thinking completely, and rearrange the equation so it produces the PAO2 as the result:
FiO2 × (Patmos - PH2O) - PCO2 = PAO2
This still leaves the alveolar CO2 concentration as an unknown. It would be inconvenient to sample it from the alveolar capillary blood (with which alveolar CO2 should be in reasonably good equilibrium), but we can sample it from the arterial blood, and introduce it into the equation with a respiratory quotient (RQ) modifier which represents the extra CO2 that is added during the passage of arterial blood through the tissues. For most normothermic people with a conventional diet this RQ modifier is around 0.8.
This gives us the modern form of the equation:
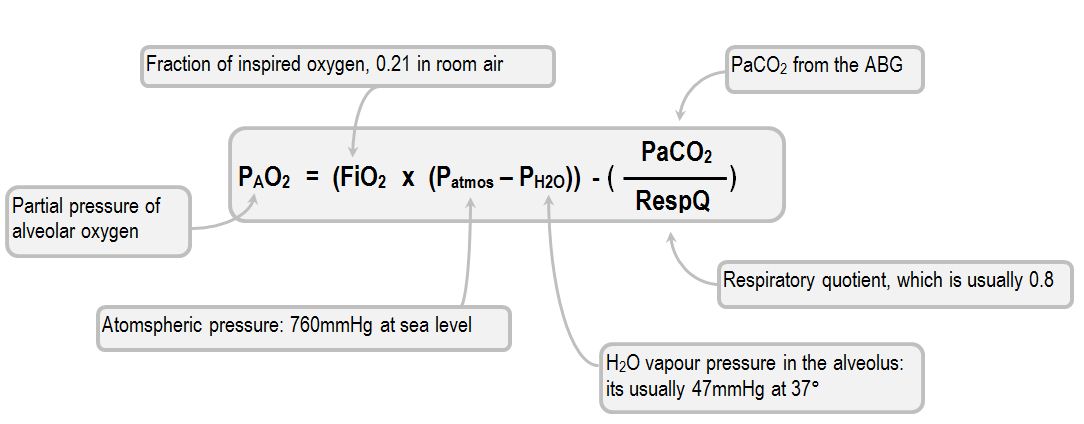
On room air and at sea level, we can assume certain constants:
PAO2 = (0.21 × (760 - 47)) - (PaCO2 × 1.25)
Thus:
PAO2 = (149 - (PaCO2 × 1.25)
Thus, the patient with a relatively normal PaCO2 (say, 40) :
PAO2 = (149 - 50)
So, a normal person should have a PAO2 of around 99 mmHg.
Or, for a patient with normal PaCO2 and an increased FiO2:
PAO2 = (FiO2 × 713) - 50
Of course, it is possible to have a strange respiratory quotient, but for this we would need to measure the total body VO2 and VCO2, which can only be accomplished by means of indirect calorimetry.
So, what should your PAO2 be at any given FiO2? In mmHg, the values are as follows:
| FiO2 21% | 100 |
| FiO2 30% | 164 |
| FiO2 40% | 235 |
| FiO2 50% | 307 |
| FiO2 60% | 378 |
| FiO2 70% | 449 |
| FiO2 80% | 520 |
| FiO2 90% | 592 |
| FiO2 100% | 662 |
In a nutshell, one can say that for every 10% increase in FiO2, the PAO2 will rise by about 71-72 mmHg.
Alveolar hypoventilation as the cause of hypoxia
Considering the limitations of the tension-based indices of oxygenation, the only role for the alveolar gas equation is said to be the detection of alveolar hypoventilation as the cause of hypoxia. Medical students and junior critical care trainees are captured during a highly susceptible impressionable age and indoctrinated with the idea that, while breathing room air, you can hypoventilate and accumulate so much CO2 in the alveolar gas mixture that the Daltonian balance of partial pressures cannot contain enough O2 to support normoxia. In other words, CO2 displaces O2 from the gas mixture, producing hypoxia - or so the fable reads. However, this is an inversion of the real causal relationship. The PAO2 drops not because of Dalton's law, but because oxygen is being consumed by being incorporated into CO2, and then the CO2 is not being exhaled effectively (because the minute ventilation has dropped). This is beautifully expressed by a letter from David A. Story from the Alfred in Melbourne to the editor of Anaesthesiology (1996), which was followed by a response by John F. Nunn. Considering the value of this exchange, it is curious that the concepts these authors had outlined are not better popularised. To hopefully improve its representation, what follows is an attempt to paraphrase and expand these excellent comments.
Consider: the rate of oxygen consumption, VO2, is described by this Fick equation:
VO2 = VA × (FiO2 - FAO2)
where:
VA is alveolar ventilation
FiO2 is the fraction of inspired O2
FAO2 is the fraction of alvolar (i.e. exhaled) O2
It's not rocket science: the minute volume multiplied by the difference between the amount of inhaled oxygen and exhaled oxygen is the total oxygen consumption (and if oxygen was not being consumed, that difference would be zero). From this equation, it follows that if the VO2 remains stable (as it does, because organs have got to keep metabolising stuff), and the FiO2 remains stable, then then the fraction of alveolar oxygen must decrease with decreasing VA:

It would be possible to end the explanation of hypoventilation-related hypoxia here, as by itself this is sufficient and self-evident, but we have yet to see how CO2 also increases. To elaborate, CO2 consumption (VCO2) is also described by a similarly straightforward equation:
VCO2 = VA × PACO2 / (Patmos - PH2O)
where:
Patmos is the total atmospheric pressure
PH2O is the partial pressure of water vapour
PACO2 is the partial pressure of alveolar CO2
VCO2 is the total CO2 production
VA is alveolar ventilation
Yes, the amount of CO2 produced and exhaled per unit time is logically just the minute volume times the fractional concentration of CO2 in the alveolar gas mixture. And you can also rearrange this to yield PACO2:
PACO2 = (Patmos - PH2O ) × (FiCO2 + VCO2 / VA)
The FiCO2 usually being zero,
PACO2 = 713 × (VCO2 / VA)
The bottom line is that the alveolar ventilation is an essential component of calculating both VO2 and VCO2. Why is this interesting? Well: VO2 and VCO2 are interrelated: for every unit of oxygen consumed, a certain amount of CO2 is produced. This relationship is represented as the respiratory quotient (RQ):
RQ = VCO2 / VO2
where:
VCO2 is CO2 production
VO2 is O2 consumption
This means that the rates of oxygen consumption CO2 production and alveolar ventilation are all inextricably linked. For example, if you make the RQ equation all about VCO2,
VCO2 = RQ × VO2
you can then represent the VCO2 using the Fick relationship mentioned above, and produce an equation that contains all three variables:
VA × PACO2 / (Patmos - PH2O) = RQ × VO2
This means you cannot alter the VA without changing the VCO2 and the VO2 in opposite directions, to a magnitude proportional to the RQ. Observe what happens when we plug some standard variables into this equation:
2852 × 50 / (760-47) = 0.8 × 250,
where
VA= 2852 ml/min
VO2 = 250 ml/min
RQ = 0.8
PH2O = 47 mmHg
If VCO2 obeys the rules, it should be 200 ml/min (because VCO2 = RQ × VO2)
Thus, PACO2 = 713 × (VCO2 / VA) = 50 mmHg
These numbers would then give us a PAO2 of 87.23 mmHg if they were plugged into Nunn's universal air equation, which describes the relationship of PAO2 to alveolar ventilation oxygen consumption and barometric pressure:
PAO2 = (Patmos - PH2O ) × (FiO2 - VO2 / VA)
= 713 × (0.21 - 250/2852)
= 87.23 mmHg
And, plugging these equations into a spreadsheet, we can produce a totally unrealistic graph that tracks the relationship of PAO2 and PACO2 for a respiratory quotient of 0.8, all the way down to a completely ludicrous PAO2 of 0 mmHg:

Yes, these gas mixtures do happen to obey Dalton's law, but that is probably because they all do. The point is that Dalton's law is not the reason the PAO2 is dropping here.
To summarise:
- With the oxygen consumption remaining the same, CO2 production by the tissues remains stable.
- With decreasing alveolar ventilation, CO2 removal from the alveolus decreases, which means the PACO2 increases.
- If the FiO2 remains the same, a larger fraction of the FiO2 ends up being removed from the alveolus to satisfy the stable delivery of oxygen, and the fraction of oxygen in the alveolus decreases, according to the equation
VO2 = VA × (FiO2 - FAO2)
- The rate of these changes in response to changes in alveolar ventilation is a function of the respiratory quotient.
- The total mixture of gases remains obedient to Dalton's Law, where the total pressure of the mixture of gases remains equal to the sum of the partial pressures of all of the constituent gases.
Can anyone be hypoxic due to hypoventilation when the PaCO2 is normal?
The respiratory quotient relationship suggests that it should be impossible to hypoventilate yourself down into blue hypoxia without becoming hypercapnic in the process; but occasionally some readers may observe something different clinically, and they should be grateful to a contributor (Professor Shyam Kothari) for bringing this conundrum into the open.
Perhaps you can just lay there and produce less CO2 through lowering your metabolism? Starting with the premise that CO2 production is the necessary consequence of O2 consumption, we assume that the only way you can produce little CO2 is to consume little oxygen. But if you consume little oxygen, then you only extract a small amount of oxygen from the alveolar gas (Nunn's universal air equation gives us the relationship of PAO2 to alveolar ventilation and oxygen consumption). So with changing VO2, the relationship between PACO2 and PAO2 will remain the same, i.e. they will still change in opposite directions, albeit more gradually. Observe, a hypothetical anaesthetic drops the alveolar ventilation at the same time as it decreases oxygen consumption:

From this, it follows that one might be able to find a rate of change at which the rate of VO2 decrease can match the rate of decreasing alveolar ventilation; i.e. where VO2 decreases in proportion to the decrease in VA, logically one should expect the alveolar gases to remain stable:

But this does not achieve the desired endpoints, as we are looking for a scenario where the patient has to be hypoxic, hypoventilating, and with a normal CO2. In this fashion we are giving the equation a series of fixed variables. Let's agree on how hypoxic we want this hypothetical patient to be:
- PACO2 = 40 mmHg, as we agree that it will remain normal, and
- PAO2 = 50 mmHg, as we agree that it will be low, for sats in the 80s.
- VO2 = 250 ml/min, as we agree that we will not meddle with it.
- VA = low, but let's keep it as the x-axis for consistency
Using the equation from above, we can plug these values in:
VA × 40 / (Patmos - PH2O ) = RQ × 250
So, the remaining variables are RQ, Patm, and FiO2. Solving for these variables:
RQ = (VA × PACO2 / (Patmos - PH2O)) / VO2
FiO2 = PAO2 / (Patmos - PH2O) + VO2 / VA
Patmos = PAO2 / (FiO2 - VO2 / VA) + PH2O
Graphing the results generates a series of nightmarishly unphysiological scenarios which produce the desired set of results at the expense of the reader's sanity:

Before they succumb to critical psychic damage, the reader is reminded that these pointless thought experiments are intended to be ridiculous, and that nobody is suggesting that the PACO2 will actually remain near normal when the PAO2 is zero due to low atmospheric pressure. The main point is that CO2 is tied to O2 consumption and it is impossible to cheat this relationship within the range of physiological performance characteristics of the human organism. To generate this situation, one would have to have an extremely low CO2 production relative to O2 consumption, and this could only be due to:
- A bizarrely low RQ ratio
- An unaccounted-for loss of oxygen
- An unaccounted-for loss of CO2
Even where there is an extreme reliance on fat metabolism (as there is less CO2 produced relative to O2 consumed during the oxidation of fatty acids), an RQ below 0.6 would be truly ridiculous. As an example, extreme ketosis can trend in the direction of 0.67, cardiac arrest survivors are occasionally observed to have RQs in the ~0.6 range because they are probably wasting their oxygen for nonmetabolic things (eg. free radical generation), but anything below this would be insane. For example, an RQ of 0.4 would mean that 60% of all the oxygen ends up being used by some mysterious process (is the patient combusting, decomposing, or feeding a giant population of microorganisms?) Bacteria and yeast can go this low, and an RQ of ~ 0.4 were measured during one experiment in fermentation by Slavov et al (2014), but it would be unexpected among eukaryotes.
More than likely, the observation of hypoventilation, hypoxia and normocapnia in a patient is the consequence of VQ scatter. Consider this memorable diagram from West (1977):

The reason for bringing this up is to remind us that a change in VQ ratio has a significant effect on oxygenation, but a modest effect on CO2 clearance. As such, it should be possible to have enough VQ scatter to create hypoxia without creating hypercapnia, provided enough of one's lung units had VQ ratios in the ~0.1 range. This is completely plausible in the context of, for example, atelectasis during sedation (where the patient is hypoventilating enough to collapse the bases of their lungs and become hypoxic, but is not sedated enough to become hypercapnic from respiratory depression).
References
The Alveolar Gas Equation was first described in a famous work by Wallace Fenn, Hermann Rahn, and Arthur Otis.
Fenn, Wallace O., Hermann Rahn, and Arthur B. Otis. "A theoretical study of the composition of the alveolar air at altitude." American Journal of Physiology--Legacy Content 146.5 (1946): 637-653.
Wang, Michael C., et al. "Teaching an intuitive derivation of the clinical alveolar equations: mass balance as a fundamental physiological principle." Advances in physiology education 44.2 (2020): 145-152.
Curran-Everett, Douglas. "A classic learning opportunity from Fenn, Rahn, and Otis (1946): the alveolar gas equation." Advances in physiology education 30.2 (2006): 58-62.
Carroll, Gilbert C. "Misapplication of alveolar gas equation." The New England journal of medicine 312.9 (1985): 586-586.
Mellemgaard, Kresten. "The Alveolar‐Arterial Oxygen Difference: Its Size and Components in Normal Man." Acta physiologica scandinavica 67.1 (1966): 10-20.
Hills, B. A. "Analysis of relative contributions to the alveolar-arterial oxygen gradient." The Bulletin of mathematical biophysics 33.2 (1971): 259-280.
Bergman, Norman A. "Components of the alveolar-arterial oxygen tension difference in anesthetized man." Anesthesiology 28.3 (1967): 517-527.
Harris, E. A., et al. "The normal alveolar-arterial oxygen-tension gradient in man." Clin Sci Mol Med 46.1 (1974): 89-104.
Atwell, Robert J., et al. "Factors Influencing the Alveolar-Arterial Oxygen Pressure Gradient Role of the Left Heart." American Journal of Physiology--Legacy Content 183.3 (1955): 451-453.
Ravin, Mark B., Robert M. Epstein, and James R. Malm. "Contribution of thebesian veins to the physiologic shunt in anesthetized man." J Appl Physiol20 (1965): 1148-1152.
Gould, Michael K., et al. "Indices of hypoxemia in patients with acute respiratory distress syndrome: Reliability, validity, and clinical usefulness."Critical care medicine 25.1 (1997): 6-8.
Sganga, G. A. B. R. I. E. L. E., et al. "The physiologic meaning of the respiratory index in various types of critical illness." Circulatory shock 17.3 (1984): 179-193.
Story, David A. "Alveolar oxygen partial pressure, alveolar carbon dioxide partial pressure, and the alveolar gas equation." Anesthesiology 84.4 (1996): 1011-1011.
Nunn, J. F. "The lung as a black box." Canadian Anaesthetists’ Society Journal 13.2 (1966): 81-97.