Oxygenation targets in mechanically ventilated adults
"Oxygen delivery systems" is a Level 1 topic from Section 2.1.5 in the first edition of the CICM Syllabus for the Second Part Examination, though the extension of this to a discussion of liberal and conservative oxygenation targets probably stretches this syllabus item beyond the point of comfort. It is as if a discussion of fun waterslides was appended to the design and function of municipal water supplies. Still, one needs to recognise the fact that any comprehensive syllabus for this impossibly broad field would extend to seven hundred pages, which would enrage and bewilder the trainee cohort, and the group of intensivists charged with the making of the syllabus wisely steered around any obviously insane design choices. Instead we have items with broad definitions and built-in elasticity, so that the absence of a specific item does not impede the asking of a question on a fundamental clinical practice point, which is "what oxygen will you instruct your staff to aim for, and why". To write this as an answer to an "advantages/disadvantages" style of question begins to feel rather monotonous in the middle, as the disadvantages of liberal oxygen targets are the same factors and concepts as the advantages of conservative ones, and so the following structure was adopted:
- Rationale for oxygenation targets
- Oxygen is a drug with both desirable and undesirable pharmacological effects
- Hypoxia and hyperoxia both have consequences
- Critically ill patients (especially mechanically ventilated patients) are both vulnerable to these effects and have oxygen therapy that is highly titratable
- The choice of endpoint for oxygen as an intervention therefore has the potential to improve outcomes in critical illness
- Definitions
- Oxygen saturation is usually the parameter used to define this, but PaO2 or P/F ratio are occasionally used.
- "Conservative" is usually 90-94% or 88-92%
- "Liberal" is usually 96-100% or 98-100%
- Conventional oxygenation targets for most patients fall into the range of 94-98% (BTS 2017 guidelines)
- Advantages of liberal oxygenation targets
- More likely to meet unrecognised oxygen requirements
- Buffer against respiratory accidents (eg. self-extubation) by maintaining an oxygen-rich FRC
- Buffer against undershot targets (i.e. if the high goals are not met the oxygenation would still be acceptable)
- Decreased work of breathing
- Decreased staff cognitive workload in titrating oxygen
- Protection of marginally perfused organs (eg. myocardium, renal medulla)
- Accidentally therapeutic effects (eg. where it leads to improved reabsorption of pneumnothoraces or treats carbon monoxide toxicity)
- Some patient populations may have a mortality benefit with higher targets
- Advantages of conservative oxygenation targets
- Reduced risk of oxygen toxicity and free radical mediated organ damage
- Prevention of hyperoxic vasoconstriction, improved microcirculatory function
- Prevention of absorption atelectasis
- Observation of respiratory disease progress through titration of FiO2
- Reduced risk of CO2 accumulation in unrecognised COPD
- Reduced cost of healthcare
- Some patient populations and some rare toxidromes (paraquat, bleomycin) may have a mortality benefit with lower targets
- Evidence to describe these practices:
- Own practice
- Normoxia (SpO2 94-98%) is unlikely to cause harm and the only population in whom relative hypoxia should be the goal are CO2-retaining COPD patients
This would probably fgo some of the way towards answering the only SAQ on this topic so far, which was Question 2 from the first paper of 2024. In terms of essential resources, the 2017 BTS guidelines for the use of oxygen is ideal for both pre-exam panic and leisurely revision, as it contains both short pithy guidelines and a wealth of background notes explaining the evidence they are based on. None of that would replace a familiarity with the recent literature, as the BTS guidelines are old, and will not have any reference to any of the major oxygen trials after 2016-2017. Asehnoune et al (2022) and Karunarathna et al (2024) are review articles that have incorporated them for quick revision, and the most important ones are also listed below.
Oxygen targets: what even are those, and do you need them
Indeed. We are only having this discussion because we have the luxury of being able to monitor arterial oxygenation in order to target it, and because we can control the oxygen delivery very precisely (well, most of the time). Prior to the late 1970s this was not even a topic of conversation (the pulse oximeter having been developed by Takuo Aoyagi in 1974), and in fact did not enter the mainstream until well into the late 1980s (with Taylor & Whitwam in 1986 still complaining that "this noninvasive system is not entirely satisfactory" even though they watched 20% of their ASA2 and ASA3 patients desaturate by 10% during induction of anaesthesia, with the blinded anaesthetist none the wiser). Prior to this continuous monitoring of oxygenation was unknown, and oxygen measurements were limited to ABG machines with the Clark electrode which was only developed in the mid-1950s. Yet again prior to that, the conditions were thoroughly unscientific. Davies & Gilchrist, writing a guideline for the use of oxygen, described the following clinical findings as concerning for the presence of "anoxæmia":
"...The appearance alters; at first flushed, the face assumes an anxious expression and cyanosis appears about the cheeks, lips, ears, and fingers. The pulse rate rises, the blood pressure tends to fall... ...chances of recovery are frequently diminished further by restlessness, and later delirium. The limbs feel heavy, weak, and powerless, and occasionally twitchings of the facial muscles are noted..."
One may point out that these features are sufficiently nonspecific that they could just as easily be used to describe the behaviour of CICM second part exam candidates, and so in this environment one should almost just treat hypoxia in all patients empirically without titration, as one would only have very crude methods of assessing whether the treatment is effective. Cyanosis was the only halfway reliable indicator; this correctly believed to be associated with an SaO2 of around 85% and a likely irreversible stage of whatever the disease was. The directive was therefore "to give initially a very high percentage in the inspired air and thereby abolish the anoxaemia rapidly (i.e., a volume of pure oxygen per minute which will practically equal the patient's respiratory minute volume)" until cyanosis disappeared and tachycardia abated.
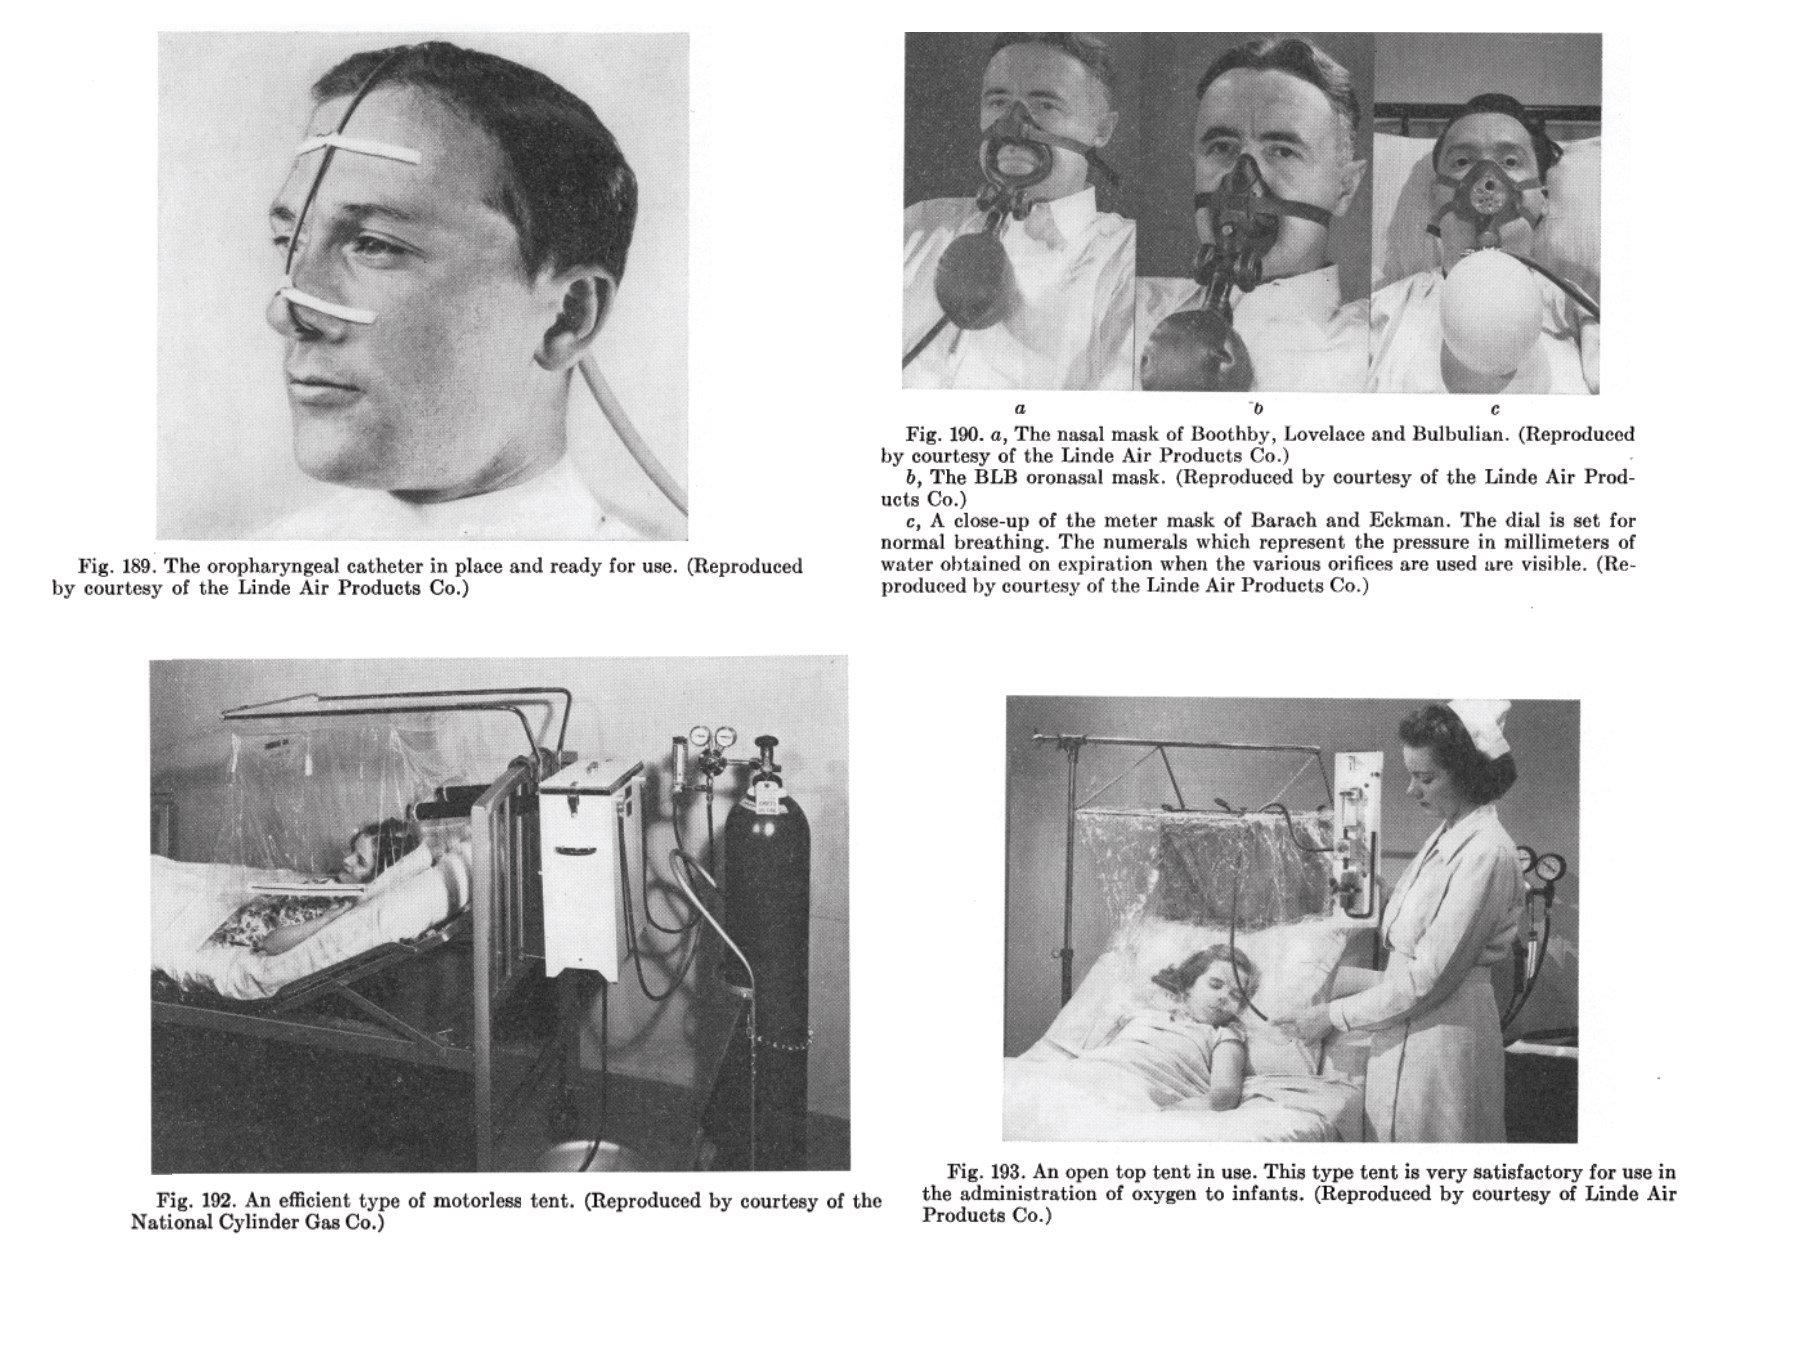
The de facto goal would therefore seem to have been an SpO2 of >85% in all patients, but in actual fact it was probably much higher than that. Other oxygen delivery devices being viewed as unreliable, non-intubated patients were commonly placed into oxygen tents with a prescribed oxygen concentration of 40-60%, which in practice was probably highly variable, as the seal was only intermittent and the fresh gas flow rate (usually 10-15L/min) was prescribed based on the clinician's assessment of the patient's breathing effort. Technicians from the hospital would test the gas inside the tent occasionally (perhaps a few times a day) but otherwise one would have only the most limited idea of what was happening in the bloodstream. The development of more sophisticated devices, for example various masks and tubes depicted in Ruzicka & Musgrave (1950), probably improved the efficiency of the use of oxygen rather than the monitoring of its delivery, which means the patients were probably oxygenated much more than was totally necessary to abolish cyanosis:
One might think that for critically ill patients, particularly ventilated ones, the threat of hypoxia was always viewed as greater than the threat of hyperoxia, and therefore one might have expected the clinicians of the era to have erred on the side of caution, prescribing more oxygen than was entirely necessary and constrained by cost than by any concerns about oxygen toxicity. Their reports suggest the opposite: that they were impossibly cavalier about their oxygenation goals and would tolerate values which would in the modern world appear monstrously negligent. For example, Ashbaugh et al (1967) in one of the earliest papers on ARDS reported the following ventilator data:

That's right, that's a dude on 40% FiO2 with sats of 72%. This was not an era of obsessively goal-directed pursuit of euboxia. "Patient 2 had a systemic blood-pressure of 65/40 mm. Hg when saturation was measured", the authors reported calmly, clearly choosing to treat the patient and not the number.
When numbers were eventually decided, the situation did not improve overmuch, because they were decided on the basis of what a recovering patient looked like, determined from large retrospective series. Of course this led to a different kind of madness which could be characterised as the Reverse McNamara Fallacy, where the pursuit of specific physiological variables was believed to be meaningless because their derangements did not seem to matter to the outcome (which surely makes logical sense, as they were not the subjects of targeted interventions). "Normal values were poor criteria for monitoring, since normal values were restored in an average of 75 per cent of the survivors and 76 per cent of the nonsurvivors for the five most frequently measured variables", elegised Shoemaker et al (1978); "moreover an average of 56 per cent of the 20 most commonly monitored variables of nonsurvivors was restored to the normal range". However the natural evolution of data (it becomes more prospective with funding) produced more information. The same primary author published new recommendations in 1983, based on a study comparing normal values versus the median values of surviving patients as the goals of therapy. An oxygen saturation of 95% was settled upon as the "correct" oxygen target. Incidentally, this paper may have had the largest effect size of any critical care trial, with absolute mortality dropping from 35% to 12.5%.
As 95% seems too specific, one might agree that a range might be better, and ideally with some statement to the effect that COPD patients might benefit from lower targets. That is basically how this concept evolved into the currently accepted state of affairs, of which the 2008 BTS oxygen therapy guideline is a good representative:
"Oxygen should be prescribed to achieve a target saturation of 94–98% for most acutely ill
patients or 88–92% for those at risk of hypercapnic respiratory failure"
But in the same year, de Jonge et al (2008) published retrospective data from over 36,000 patients, with the surprising finding that both low and high PaO2 were independently associated with increased mortality. The subsequent years added nothing but controversy, with multiple prospective and retrospective studies concluding variably that either liberal targets are worse, or not worse, or that targets in general are not meaningful, and that different populations react differently. The benefits of this mess is that it acts as a rich source of debate and makes for good CICM exam questions, because the lack of clear direction from the literature means that every oxygen dose decision is nuanced.
But why not PaO2?
Because it defies logic. The reader is redirected to the chapter on the tension-based indices of oxygenation for an explanation. In summary, PaO2 is not a meaningful parameter to pursue under most circumstances because what it measures (dissolved oxygen in the blood) is not something the bedside clinician is ever likely to be interested in. It certainly does not reflect the oxygen content of the blood, which is more related to the saturation of haemoglobin, nor the oxygen delivery, which is better represented by the DO2 calculated using the cardiac output. Moreover, its effect on those parameters depends on the affinity of haemoglobin for oxygen (described by the p50 value), which can vary considerably (eg. at a Hb of 100 and PaO2 of 60 mmHg, the oxygen content of arterial blood may vary from 125 to 106 ml/L if the p50 varies from 18 to 34). It is therefore baffling that some still make oxygen therapy decisions made on the basis of the PaO2, outside of nightmarish situations where anaemia has decimated the oxygen carrying capacity of the blood, and one becomes dependent on the dissolved fraction because transfusion is for whatever reason impossible.
Advantages of liberal oxygen targets
This is a slightly longer version of the grey box above, but on closer inspection it really does not have any additional content.
- Oxygen delivery is abundant. Given that haemoglobin is not always tracked, p50 rarely thought about, and cardiac output practically never measured, one can conceive of a situation where a patient may suffer form a drop in DO2 which would go unrecognised. A decent oxygen saturation is a buffer against this possibility.
- Buffer against respiratory accidents - the well-oxygenated FRC would act as a safety reservoir that ameliorates the risk from various adverse events, eg. where the patient transiently becomes apnoeic because of a bolus of sedation, or self-extubates randomly.
- Buffer against undershoot: for patients in whom lower oxygenation is targeted, presumably a proportion of the time would be spent below the target value, exposing them to the effects of hypoxia.
- Decreased workload: Titrating FiO2 to achieve low oxygenation targets is laborious, and it might just be easier to put the patient on a uniformly high FiO2 and focus on something more important.
- Protection of marginally perfused organs: good oxygen content could protect tissues that have poor blood flow or that have a baseline high oxygen extraction ration (eg. myocardium and the renal medulla). A high oxygen concentration gradient could also promote the survival of devitalised free flaps, for example.
- Protection from rare weirdness like carboxyhaemoglobin may be applicable in certain scenarios (eg. in the ED where carbon monoxide toxicity may not be recognised).
- Reabsorption of pneumothoraces and pneumocephalus: which, to be fair, are niche cases
- Improved oxygen delivery to tissue: theoretically, the increased gradient should improve the oxygenation of
- Stopping or reducing oxygen therapy is the opposite of therapy, i.e. there is no direct benefit - it is a step that is indirectly beneficial if it is preventative, an effect which we are still debating.
On the other hand:
Advantages of conservative oxygen targets
- Reduced risk of oxygen toxicity, which is something that contributes to lung injury and CNS toxicity at FiO2 in excess of 60%.
- Reduced oxidative stress: one cannot answer a question about hyperoxia without mentioning reactive oxygen species. There does not seem to be an organ system where this has not been demonstrated in the laboratory (Singer et al, 2021, list several such experiments)
- Prevention of absorption atelectasis which, admittedly, is not really a major contributor to atelectasis in ICU patients, as being on 21% FiO2 does not seem to protect them.
- Prevention of hyperoxic vasoconstriction: Hyperoxia leads to vasoconstriction (Smit et al, 2018) which could theoretically lead to organ damage if aforementioned organs were already poorly perfused
- Reduced cost: oxygen is not cheap, and keeping patients in ICU because they "need" higher oxygen targets is not cheap; whereas aiming for lower targets may allow one to deescalate their care sooner, with no additional morbidity. On the other hand, oxygen itself contributes a tiny fraction to the overall cost of intensive care, where staff are the most expensive resource and consumables account for only 15-20% of the total.
- Observation of respiratory progress: titrating oxygen therapy can have the effect of tracking the improvement or deterioration of gas exchange, whereas a fixed high oxygen concentration is less informative.
- Retinopathy of prematurity in neonates is not relevant to the adult ICU patient but is worth remembering.
- Rare toxic syndromes, eg. paraquat and bleomycin toxicity, are exacerbated by hyperoxia
And then there is the trial evidence:
Trials and guidelines regarding oxygenation targets
Randomised controlled trials of oxygenation targets include:
- CLOSE - 2016 - sats 88-92 versus >96%; n=103 in Australia. Feasibility only, demonstrating that it is safe to achieve this sort of separation for 7 days.
- OXYGEN-ICU - 2016 - sats 94-98% vs 97%, n=434, single centre in Italy. Mortality significantly lower in the low sats group (11.6% vs 20.2%).
- ICU-ROX - 2019 - SaO2 91-96%, vs normal targets, in ventilated patients. n=965 in Australia and NZ. No difference in ventilator free days (21.3 vs 22.1).
- LOCO2 - 2020 - PaO2 55-70 vs 70-105 in ARDS. n=201, in France. No significant difference at 28 days, but enough of a difference (34.3% conservative vs. 26.5% liberal) to stop the trial early. Increased signal for risk of mesenteric ischaemia.
- HOT-ICU - 2021 - PaO2 60 vs 90 in acute hypoxic respiratory failure (mostly pneumonia, 57%). n=2888 in Europe. No mortality difference (42.9% vs 42.4%)
- PILOT - 2022 - sats 88-92 vs 92-96 vs 96-100. n=2541 in Nashville. No difference in mortality (34.8% vs 34% vs 33.2%) or ventilator-free days (20, 21 and 21).
- BOX - 2022 - PaO2 68-75 vs 98-105, n=789 comatose survivors of cardiac arrest in Denmark. No difference in outcome (but weirdly powered to detect an ambitious change from 28 to 18%)
- EXACT - 2022 - sats of 90-94% vs 98-100%; n=428 in Australian out of hospital cardiac arrest. No difference.
- ICONIC - 2023 - sats 91-94% vs 96-100%, n= 664 instead of 1512 because COVID (Netherlands and Italy). No difference, even though the groups were well separated.
Oxygen targets in specific patient populations:
- Traumatic brain injury: analysis of TBI trial data by Rezoagli et al (2022) suggested that hyperoxia has some kind of toxic effect in this population, but the effect was extremely small (OR for worse neurological outcome was 1.03-1.07).
- Out of hospital cardiac arrest survivors: in the ICU-ROX trial had a subgroup (n= 166) of patients with hypoxic-ischaemic brain injury, among whom the outcomes were better with a conservative oxygen goal (OR 0.58). On the other hand, HOT-ICU had an even larger subgroup (n=335) and found an increase in mortality associated with conservative oxygen therapy (by 5.6%). And large dedicated trials looking specifically at the cardiac arrest population (EXACT, BOX) trial found no difference.
- ARDS: the LOCO2 findings suggest that conservative oxygen targets don't help, and so far there is little evidence that pulmonary oxygen toxicity somehow exacerbates their lung disease.
- Sepsis: the ICU-ROX trial cohort with sepsis and septic shock had a 7% improvement in survival with liberal oxygen.
- Myocardial infarction: the AVOID trial (2015) had presented STEMI patients with oxygen and found that they had reinfarcted more often (5.5% vs 0.9%) and had larger infarct size on average, which might suggest that this population is probably better off with conservative targets. On the other hand, it was followed by multiple other larger trials (DETO2X-AMI in 2017, Stewart in 2021, detailed by Liang et al 2023), none of which were able to demonstrate this difference
In summary, as with all such things, large methodologically sound trials have diluted the signal from older smaller trials which may have suffered from some kind of local bias. When the same data is examined and interpreted by large international societies, they tend to offer a relatively broad range:
- BTS (2017): 94–98% for all
- TSANZ (2021): >92% for all
- AHA (2014): 92-98% for cardiac arrest, >90% for MI
- ANZCOR (2020): 94-98% for cardiac arrest
- ESC (2017): >90% for MI
- BTF4: > 90% for TBI
- SSG (2021): >92%, but they say this indirectly (by explicitly rejecting the 88-92% targets)
- Everyone, regarding COPD: 88-92%
Own practice
In this climate of U-shaped homogenisation of oxygen trial data, the trainee trying to answer the "what would you do" question in a consultoid manner would find themselves forced to target the normal range of oxygen saturation in most cases outside of COPD. What does that look like? When the same data is examined and interpreted by large international societies, they tend to offer a relatively broad range, as seen above, and most accept 92-94% as the lower range, with nobody insisting on anything higher than 98%, nor on a strict adherence to anything under 92%. The trainee whose approach to oxygen prescribing has been entirely vibes-based will therefore still likely be able to answer such a question with a generic response, such as "all patient groups would benefit from a normal range of oxygen saturation values (92-98%)".
References
Buell, Kevin G., et al. "Individualized treatment effects of oxygen targets in mechanically ventilated critically ill adults." JAMA 331.14 (2024): 1195-1204.
Severinghaus, John W. "Takuo Aoyagi: discovery of pulse oximetry." Anesthesia & Analgesia 105.6 (2007): S1-S4.
Taylor, M. B., and J. G. Whitwam. "The current status of pulse oximetry: clinical value of continuous noninvasive oxygen saturation monitoring." Anaesthesia 41.9 (1986): 943-949.
Davies, H. Whitridge, and A. Rae Gilchrist. "Oxygen Therapy: Indications, Principles, and Methods." Edinburgh Medical Journal 32.5 (1925): 225.
Haynes, Lewis L., and Phyllis Harrington. "Three Years' Experience with Intensive Treatment and Recovery Unit in Medicine and Surgery." Military Medicine 125.6 (1960): 398-402.
Radford Jr, Edward P., Benjamin G. Ferris Jr, and Bertrand C. Kriete. "Clinical use of a nomogram to estimate proper ventilation during artificial respiration." New England Journal of Medicine 251.22 (1954): 877-884.
Hawthorne, Margaret J., et al. "Oxygen Therapy: A Study in Some Nursing Aspects of the Operation of an Oxygen Tent." The American Journal of Nursing (1938): 1203-1216.
Wayne, D. J., and Anne R. Chamney. "Oxygen tent performance." Physics in Medicine & Biology 14.1 (1969): 9.
Ruzicka, Edwin R., and Homer S. Musgrave. "Oxygen Therapy." Surgical Clinics of North America 30.3 (1950): 761-771.
Ashbaugh, DavidG, et al. "Acute respiratory distress in adults." The Lancet 290.7511 (1967): 319-323.
Jubran, Amal, and Martin J. Tobin. "Reliability of pulse oximetry in titrating supplemental oxygen therapy in ventilator-dependent patients." Chest 97.6 (1990): 1420-1425.
Waxman, Kenneth, and William C. Shoemaker. "Management of postoperative and posttraumatic respiratory failure in the intensive care unit." Surgical Clinics of North America 60.6 (1980): 1413-1428.
Bland, R., W. C. Shoemaker, and M. M. Shabot. "Physiologic monitoring goals for the critically ill patient." Surgery, Gynecology & Obstetrics 147.6 (1978): 833-841.
Shoemaker, William C., Paul Appel, and Richard Bland. "Use of physiologic monitoring to predict outcome and to assist in clinical decisions in critically ill postoperative patients." The American Journal of Surgery 146.1 (1983): 43-50.
van der Wal, L. Imeen, et al. "Conservative versus liberal oxygenation targets in intensive care unit patients (ICONIC): a randomized clinical trial." American journal of respiratory and critical care medicine 208.7 (2023): 770-779.
Smit, Bob, et al. "Moderate hyperoxic versus near-physiological oxygen targets during and after coronary artery bypass surgery: a randomised controlled trial." Critical Care 20 (2016): 1-10.
Singer, Mervyn, et al. "Dangers of hyperoxia." Critical Care 25 (2021): 1-15.
de Jonge, Evert, et al. "Association between administered oxygen, arterial partial oxygen pressure and mortality in mechanically ventilated intensive care unit patients." Critical care 12 (2008): 1-8.
Carrandi, Alayna, et al. "Costs of Australian intensive care: A systematic review." Critical Care and Resuscitation (2024).
Smit, Bob, et al. "Effects of hyperoxia on vascular tone in animal models: systematic review and meta-analysis." Critical Care 22 (2018): 1-16.
Calzia, Enrico, et al. "Hyperoxia may be beneficial." Critical care medicine 38.10 (2010): S559-S568.
Rezoagli, Emanuele, et al. "High arterial oxygen levels and supplemental oxygen administration in traumatic brain injury: insights from CENTER-TBI and OzENTER-TBI." Intensive care medicine 48.12 (2022): 1709-1725.
Asehnoune, Karim, Fabio S. Taccone, and Mervyn Singer. "High oxygen level in traumatic brain injury patients. Never ending story?." Intensive Care Medicine 48.12 (2022): 1772-1774.
Karunarathna, Indunil, et al. "Oxygen Therapy in Neurocritical Care: Examining the Evidence and Uncertainties."
Nedeljkovic, Zoran S., and Alice K. Jacobs. "Oxygen for ST-Segment–Elevation Myocardial Infarction: Still Up in the Air." Circulation 131.24 (2015): 2101-2103.
Liang, Yafen, et al. "Interplay of hypoxia-inducible factors and oxygen therapy in cardiovascular medicine." Nature Reviews Cardiology 20.11 (2023): 723-737.
Bernard, Stephen A., et al. "Effect of lower vs higher oxygen saturation targets on survival to hospital discharge among patients resuscitated after out-of-hospital cardiac arrest: the EXACT randomized clinical trial." Jama 328.18 (2022): 1818-1826.
Hofmann, Robin, et al. "Oxygen therapy in suspected acute myocardial infarction." New England Journal of Medicine 377.13 (2017): 1240-1249.
Stewart, Ralph AH, et al. "High flow oxygen and risk of mortality in patients with a suspected acute coronary syndrome: pragmatic, cluster randomised, crossover trial." bmj 372 (2021).