Printable list of all neurology and neurosurgery SAQs
Question 15 - 2001, Paper 1
What is the significance of persistent hiccoughs in a ventilated ICU patient and how will you manage them?
College Answer
Hiccoughs may be due to
- Irritation of diaphragm (subphrenic abscess, cholecystitis, pneumonia, pericarditis)
- Irritation of stomach wall (distension, ulcer, ileus)
- Phrenic nerve stimulation /irritation (neoplasm, goitre)
- Brainstem lesion (neoplasm, ischaemia, surgery)
- Metabolic (uraemia)
Management is often unsatisfactory:
- diagnosis and treatment of underlying cause (NG tube, drain subphrenic )
- many medications have been used, indicative of their poor efficacy (eg chlorpromazine, metaclopramide, haloperidol, phenytoin, carbamazapine)
- physical stimulation of posterior pharynx by NG tube may interrupt the reflex arc
In the event of persistent, fatiguing hiccoughs phrenic nerve block has been tried.
Discussion
Never since this question have "hiccoughs" been asked about in the ICU fellowship paper. However, one must answer these things.
A hiccup, or singultus, or synchronous diaphragmatic flutter, is a myoclonic spasm of the diaphragm, which is stimulated by the prehinc nerve. The signal to hiccup is sent from the nucleus tractus solitarius. This signal can be stimulated by a number of pathological conditions. A brief review lays these bare:
- Foeign body in the external auditory canal
- Medullary lesions (especially PICA artery)
- Medullary demyelination
- Spinal syrinx
- Encephalitis
- Meningitis
- Gastro-esophageal reflux
- Gastric distension
- Pancreatitis
- Thoracic aortic aneurysm
- Mediastinal tumours
- Pleural and pericardial effusion
- Uremia
- Hypocalcemia
- Hyponatremia
- Methyldopa
The review article remarks that "The more than 100 forms of physical or pharmacological treatment for intractable hiccups include prayers to St Jude, the patron saint of lost causes". As reliable remedies, the author recommends to raise the PaCO2 and to vigorously stimulate the posterior pharynx. Apparently, chlorpromazine remains the most consistently effective agent. Other lesser known solutions are discussed elsewhere.
References
Kolodzik, Paul W., and Mark A. Filers. "Hiccups (singultus): review and approach to management." Annals of emergency medicine 20.5 (1991): 565-573.
Howard, Robin S. "Persistent hiccups." BMJ: British Medical Journal 305.6864 (1992): 1237.
Question 2 - 2001, Paper 1
A patient with Guillain-Barré Syndrome is quadriparetic and ventilated via a tracheostomy.
She wishes to eat. How does a tracheostomy interfere with swallowing? How will you assess her ability to swallow safely?
College Answer
This is not an uncommon question in long-stay ICU patients. Is eating possible? The two parts to be covered are:
(a) How does a tracheostomy interfere with swallowing?
Normal swallowing requires timing and coordination of many muscles and several cranial nerves, which are under voluntary and involuntary nervous control. The phases are; (1) oral preparatory –mastication and creation of a bolus, (2) oral transit –delivering the bolus to the back of the tongue, soft palate is elevated to allow passage, (3) pharyngeal – is most complex with pharyngeal constriction to create a dynamic pressure gradient, breath-holding, elevation of arytenoids, cord adduction and epiglottic inversion, (4) oesophageal stage –with coordinated contraction and relaxation of oesophageal sphincters and peristaltic waves carrying the bolus.
A list of therefore could have included: Placement of a tracheostomy -
- impedes laryngeal elevation
- impairs hypopharyngeal and laryngeal sensation by desensitisation
- leads to disuse atrophy of laryngeal and pharyngeal muscles
- impairs glottic reflex closure
- reduces subglottic pressure
(b) How will you assess her ability to swallow safely?
A tracheostomy cuff does not guarantee prevention of aspiration. Assessment is best achieved by:
- assessment of (1) general condition and (2) specific ability to handle a test swallow.
A breathless and weak patient, who is unwell with sepsis etc., is unable to coordinate swallowing.
- motor movements of the lips face tongue jaw and palate are evaluated for strength, symmetry, speed, accuracy and range of motion for specific nerve deficits. Elevation of the larynx with attempted swallowing should be observed. Strength of cough and timing and fullness of laryngeal excursion give clues to general laryngeal protection.
-test of swallowing and airway protection: this is commonly performed with blue dye mixed with a variety of food consistencies. A bolus of thick liquid is more easily maintained in a bolus and more safely swallowed. After swallowing the tracheostomy is suctioned at intervals to detect leak of dye into the airway. Unfortunately, false negative tests are common (confirmed by video fluoroscopic imaging) so vigilance should be maintained even if the test is passed.
Discussion
A good paper from 1971 discusses this question in some detail.
In summary, the swallowing defects due to tracheostomy are as follows:
- It prevents the larynx from elevating normally
- thus, hypopharyngeal sphincter fails to open
- thus, food spills into the larynx
- It desensitises the sensation of the larynx, preventing normal cough in response to aspiration. The effect is likened to stroke-related bulbar dysfunction
- Long periods of being NG-fed result in the deconditioning of muscles involved in swallowing
Assessment of swallowing is a fine art. See this detailed proforma to help speech pathologists. Others are even more extensive.
To summarise,
- Physical assessment:
- intact cough reflex
- intact gag reflex
- adequate laryngeal elevation
- absence of obvious cranial nerve signs
- Investigations
- videolaryngoscopy
- Test swallow
- blue food dye in the swallow
- sequential tracheal aspirates to demonstrate that no blue dye is in the lung
- alternatively, barium swallow
- The gold standard is a videofluoroscopic swallowing study, AKA the modified barium swallow.
References
LITFL have a good page on this (they have a good page on everything).
Bonanno, P. C. "Swallowing dysfunction after tracheostomy." Annals of surgery174.1 (1971): 29.
Mann, Giselle. MASA, the mann assessment of swallowing ability. Vol. 1. Cengage Learning, 2002.
Goldsmith, Tessa. "Evaluation and treatment of swallowing disorders following endotracheal intubation and tracheostomy." International anesthesiology clinics38.3 (2000): 219-242.
Prigent, Hélène, et al. "Effect of a tracheostomy speaking valve on breathing–swallowing interaction." Intensive care medicine 38.1 (2012): 85-90.
Macht, Madison, et al. "ICU-Acquired Swallowing Disorders." Critical care medicine 41.10 (2013): 2396-2405.
Question 8 - 2001, Paper 2
Critically evaluate the use of hypertonic saline and mannitol in the management of severe closed head injury.
College Answer
Hypertonic Saline has theoretical advantages in the initial resuscitation of head injured patients because smaller volumes of fluid are required and blood pressure restoration is more effective. Brain oedema may be decreased to lower ICP and CPP may be increased. Post resuscitation use is less clear. In this setting, reduction in intracranial hypertension is due to improved systemic and cerebral haemodynamics and modulation of vasospasm. Adverse effects include renal impairment, rebound ICP rise and osmotic myelinolysis. Trials are continuing and a well defined role is not apparent as yet.
Mannitol has a long history of use in the management of head injuries. It lowers ICP initially by increasing CBF and producing a compensatory vasoconstriction. An osmotic effect and diuresis produce delayed fall in ICP. Efficacy would be dependent initially on the presence of adequate brain with intact autoregulation. Prolonged use may lead to leak into damaged brain with concomitant increase in ICP and swelling. The accepted role is in the urgent lowering of ICP before definitive therapy (eg. evacuate haematoma or perform decompression craniectomy). Chronic use is not supported by evidence.
Discussion
Another question is very similar- Question 4 from the first paper of 2007. It asks one to discuss hypertonic saline, which of course is impossible without discussing mannitol.
In brief:
aised intracranial pressure falls within the realm of osmotherapy, which enjoys a thorough discussion elsewhere:
- Intracranial pressure as a therapeutic target
- Management of raised intracranial pressure
- Osmotherapy for management of raised intracranial pressure
From those summary, a table of comparison can be compiled, which is presented below.
Category |
Mannitol |
Hypertonic saline |
| Advantages |
|
|
| Disadvantages |
|
|
References
Chapter 43 (pp. 563) Cerebral protection by Victoria Heaviside and Michelle Hayes, and
Chapter 67 (pp. 765) Severe head injury by John A Myburgh.
Francony, Gilles, et al. "Equimolar doses of mannitol and hypertonic saline in the treatment of increased intracranial pressure*." Critical care medicine 36.3 (2008): 795-800.
Kamel, Hooman, et al. "Hypertonic saline versus mannitol for the treatment of elevated intracranial pressure: A meta-analysis of randomized clinical trials*."Critical care medicine 39.3 (2011): 554-559.
Nau, Roland. "Osmotherapy for elevated intracranial pressure." Clinical pharmacokinetics 38.1 (2000): 23-40.
Rickard, A. C., et al. "Salt or sugar for your injured brain? A meta-analysis of randomised controlled trials of mannitol versus hypertonic sodium solutions to manage raised intracranial pressure in traumatic brain injury." Emergency Medicine Journal (2013).
Lazaridis, Christos, et al. "High-Osmolarity Saline in Neurocritical Care: Systematic Review and Meta-Analysis*." Critical care medicine 41.5 (2013): 1353-1360.
Bhardwaj, Anish, and John A. Ulatowski. "Hypertonic saline solutions in brain injury." Current opinion in critical care 10.2 (2004): 126-131.
Arbabi, Saman, et al. "Hypertonic saline induces prostacyclin production via extracellular signal-regulated kinase (ERK) activation." Journal of Surgical Research 83.2 (1999): 141-146.
R LAWRENCE REED, I. I., et al. "Hypertonic saline alters plasma clotting times and platelet aggregation." Journal of Trauma-Injury, Infection, and Critical Care 31.1 (1991): 8-14.
Question 5 - 2002, Paper 2
Outline the techniques you would use to control intra-cranial pressure in a patient with a severe closed head injury.
College Answer
Management priorities will be determined by the exact clinical scenario, though the general principles are consistent. Consider recommendations (eg. Brain Trauma Foundation).
• Ensure simple reversible causes are not present (elevate head, maintain head in central position with no venous occluding tapes, adequate sedation, treatment of seizures, adequate volume status, adequate oxygenation, arterial carbon dioxide not elevated).
• Consider exclusion of reversible mass lesion (CT or repeat CT).
• Drain CSF from ventricle (if drain in situ).
Further techniques that could be considered at this point include: further decrease in arterial carbon dioxide (to 30-35 mmHg), mannitol (keeping euvolaemic and osmolarity < 320 mOsm/L), additional sedation (including barbiturates) ± paralysis (decrease straining against ETT/ventilation), hypertonic saline, induced hypothermia, decompressive craniectomy, (? hypertensive therapy, further hyperventilation).
Discussion
This question closely resembles Question 12 from the first paper of 2004.
Stereotypical steps in ICP management:
- Position the head (45 °head up, facing straight)
- Loosen the ETT ties
- Remove the C-spine collar
- Decrease PEEP as much as possible
- Increase sedation
- Propofol sedation to decrease distress and thus decrease ICP
- Benzodiazepines may be of use (but they do not decrease the CMRO2 as much as propofol)
- Drain some CSF from the EVD
- Paralysis with neuromuscular junction blocker
- Osmotherapy
- Mannitol 20%
- Hypertonic saline
- Super-refractory ICP
- Hypothermia
- THAM
- Dihydroergotamine
- Controversial measures
- Barbiturate coma if other methods of lowering ICP have failed
- Decompressive craniectomy
References
Question 15 - 2002, Paper 2
List the potential causes of delayed awakening in a patient after a prolonged stay in Intensive Care, and outline how you would determine what factors were contributory.
College
• Potential causes include: prolonged effects of sedative drugs, metabolic encephalopathy (especially renal or hepatic failure), endocrine problems (especially hypothyroidism), systemic sepsis, and a myriad of specific neurological problems (eg. status epilepticus, raised intracranial pressure, intracranial haemorrhages, severe Guillain Barre, critical illness polyneuropathy). Residual muscular paralysis must be excluded.
• Sedative drugs may have a prolonged effect because of altered kinetics (including context sensitive half-time, or decreased biotransformation or excretion eg. renal or hepatic failure) or altered dynamics (potentiation of effect by other drugs or organ failure, sensitivity to effect of usual dosage).
Assessment of contributory factors may be a complex process. Important steps include:
• Detailed history of neurological state, drugs administered, previous neurological problems
• Careful examination (in particular neurological, but also for signs of other chronic diseases).
Detailed neurological exam should include global CNS assessment (including ability to move eyes or poke out tongue if no other apparent motor responses: locked in syndrome, severe myoneuropathy), and search for focal signs (pupils, tone, movement, reflexes). Nerve stimulator should be used to assess residual paralysis.
• Biochemical investigations for severity of electrolyte imbalance, creatine kinase, renal and hepatic dysfunction (including ammonia), and to exclude treatable endocrine disorders (including T4/TSH).
• Consider use of specific reversal agents (eg. naloxone and flumazenil [may need multiple ampoules]).
• May require other specific investigations (but put into context, and not done as a routine).
Such investigations include CT scan of head, MRI, EEG, EMG and lumbar puncture.
Discussion
List the potential causes of delayed awakening? There could be thousands.
A tabulated answer is called for.
| Classification | Aetiology | Investigations |
| Vascular causes | Hypotension, cerebral hypoxia | Routine monitoring of BP and SaO2 |
| Vasospasm post SAH | CTA, DSA | |
| Stroke | MRI | |
| Intracranial haemorrhage | CT | |
| Infectious causes | Meningitis | LP |
| Encephalitis | LP, MRI | |
| Septic encephalopathy | Diagnosis of exclusion | |
| Neoplastic causes | CNS malignancy | Contrast CT |
| Cerebral oedema | CT | |
| Drug-related causes | Sedative drugs | Drug levels, drug history |
| Impaired clearance of sedative drugs | Renal and hepatic function testing | |
| Intrinisic neurological causes | Status epilepticus | EEG |
| Cerebral oedema (of whatever aetiology) | CT | |
| Autoimmune causes | CNS vasculitis | Vasculitic screen, LP, CTA, MRA |
| Traumatic causes | Intracranial injury (eg. contusion) | CT |
| Concussion | Diagnosis of exclusion | |
| Endocrine/metabolic causes | Electrolyte derangement, eg. hyponatremia | EUC / CMP |
| Hypothyroidism | TFTs | |
| Uremic encephalopathy | Renal function tests | |
| Hypoglycaemia | BSL | |
| Hypoadrenalism | Random cortisol | |
| Hepatic encephalopathy | LFTs, ammonia level |
Thus, investigations should consist of:
- Biochemistry:
- BSL, EUC, CMP, LFT, TFT and random cortisol
- Samples:
- Blood cultures
- CSF analysis
- Imaging:
- CT brain pre and post-contrast
- CTA
- MRI / MRA
- Functional studies:
- EEG
- Routine monitoring obs of BP and SaO2
Management would obviously be directed at the possible causes.
References
Question 10 - 2003, Paper 1
Outline the diagnostic features of Horner’s Syndrome and list the likely causes in patients in Intensive Care.
College Answer
Horner’s Syndrome is due to damage to the cervical sympathetic pathway, and exhibits a smaller pupil , a variable degree of ptosis and anhydrosis [impaired sweating over variable area] ± bloodshot eye [loss of vasoconstrictor]. The presence of enophthalmos is controversial. Likely causes include common lesions along the path of the sympathetic pathway: including from brainstem (CVA) and cervical cord lesions (including trauma and local anaesthetic eg. epidural), through T1 root lesions (malignant disease eg. Pancoast syndrome; traction injuries to arm or aneurysms of aortic arch or subclavian artery), along the chain in the neck (malignancy, neck surgery, carotid artery dissection). Transient Horner’s can occur with cluster headaches and with migraine. Many cases have no demonstrable cause.
Discussion
Features of Horner's Syndrome:
- Ptosis
- Miosis
- Anhidrosis of the forehead
- Enophthalmos
Causes of Horner's |
Associated clinical findings: |
| Cluster headache |
|
| Cortical stroke (hemispheric) |
|
| Brainstem stroke (lateral medullary syndrome) |
|
| Cavernous sinus pathology |
|
| Syringobulbia |
|
| Syringomyelia |
|
| Spinal injury or infarction |
|
| Malignancy in the apex of the lung |
|
| Thyroid cancer |
|
| Neck trauma or surgery |
|
| Lower trunk brachial plexus injuries |
|
| Carotid aneurysm or dissection |
|
References
Question 15 - 2003, Paper 2
List the potential causes of profound weakness in the critically ill, and outline how you would determine which factors were contributory.
College Answer
Profound weakness in the critically ill can be as a result of a number of different pathophysiologic mechanisms. Residual paralysis should be considered and excluded by nerve stimulator examination (minimal response to train of four; post-tetanic facilitation, possibly some improvement with reversal of blockade). Residual sedation should also be considered, but once aroused, patient should be able to demonstrate more appropriate strength (and/or response to antidotes: e.g. naloxone, flumazenil). Critical illness polyneuropathy presents after a week or so of critical illness, typically with limb weakness and atrophy, reduced deep tendon reflexes, loss of peripheral sensation to touch and pin prick, but relative preservation of cranial nerve function. Electrophysiological studies reveal motor and sensory axonal neuropathy, and biopsies reveal axonal degeneration and denervation atrophy of muscles. An acute myopathy (especially in association with neuromuscular blockade and corticosteroids) may present with similar motor findings but with no sensory abnormalities. Creatine kinase should be elevated. Electrophysiological testing is consistent with a myopathy, and muscle biopsy reveals loss of thick filaments. Spinal cord lesions should be associated with a sensory level and hyperreflexia. Cranial nerve abnormalities suggest brain-stem problems or Guillain-Barre syndrome.
Discussion
The topic of weakness comes up frequently in these exams.
A generic approach to the patient with generalised weakness in the ICU is discussed elsewhere.
In short:
- Exclude sedation and paralysis
- Gather a history to exclude an existing illness which might be contributing
- Perform a physical examination looking for characteristic signs
The following tests and imaging studies could be useful:
- Electrolyte levels
- CK level
- B12 level
- Acetylcholine receptor antibodies (for myasthenia gravis)
- CXR looking for malignancy (as support for a diagnosis of Eaton-Lambert syndrome)
- Inflammatory markers
- Lumbar puncture
- Nerve conduction studies
- Electromyography
- MRI of the brainstem and spine
- Muscle biopsy if no satisfactory explanation is found.
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Jani, Charu. "Critical Illness Neuropathy." Medicine (2011): 237.
Young, G. Bryan, and Robert R. Hammond. "A stronger approach to weakness in the intensive care unit." Critical care 8.6 (2004): 416.
Mareska, Michael, and Laurie Gutmann. "Lambert-Eaton myasthenic syndrome." Seminars in neurology. Vol. 24. No. 2. [New York]: Thieme-Stratton Inc.,[c1981-, 2004.
Reeves and Swenson have an excellent online textbook chapter (12) entitled "Evaluation of the Patient with Weakness"
Question 12 - 2004, Paper 1
Outline the causes, and principles of management of raised intra-cranial pressure in the patient with a severe closed head injury.
College Answer
Raised intracranial pressure (usually considered > 20 to 25 mmHg) in the setting of severe closed head injury is a relatively frequent phenomenon. The causes usually dictate the specific therapy. specific causes to be considered included artefact, transient elevations associated with coughing/valsalva manoeuvres, , increased brain parenchymal volume (ie. cerebral oedema), increased cerebral blood volume (especially haematomata), increased CSF volume (especially decreased drainage). The likelihood of each is related to the individual circumstances, and relative timing with respect to the injury itself.
Principles of management depend upon what techniques/interventions have already been instituted, but include: provision of adequate oxygenation, ventilation (usually mechanical, aiming for normocapnia if normal bicarbonate [situation less clear if abnormal bicarbonate]) and circulation (adequate CPP [usually considered > 70 mmHg] with euvolaemia and/or use of vasopressors); elevation of head and neck, and ensuring that there is no obstruction to venous drainage; if not already done, establishment of invasive monitoring (to confirm diagnosis and allow titration of therapy); exclusion of artefactual error (zeroing, levelling and calibration as able); minimisation of coughing/valsalva and reduction of metabolic demand with sedation and/or paralysis; drainage of CSF via ventricular drain (if available); detection and drainage of intracerebral haematomata; correction of hyponatraemia (administration of hypertonic saline may provide some short term control); techniques to decrease metabolic demand include anti-seizure treatment/prophylaxis, and temperature control at least to normothermic levels (induced hypothermia is controversial, but seems to decrease ICP in refractory cases); osmotherapy using mannitol may be useful in refractory cases or when buying time before definitive surgery (keeping osmolality < 320 mOsm/kg); other techniques for refractory cases include barbiturate coma, decompressive craniectomy, and possibly hyperventilation (for short term use only).
Discussion
This was a broad question, about a familiar topic, and could be answered with gusto. A detailed examination of management of raised intracranial pressure is available elsewhere.
Causes:
- Increase in the volume of CSF (eg. hydrocephalus)
- Increase in the volume of the brain parenchyma (eg. cerebral oedema)
- Increase in the volume of intracranial blood (eg. haemorrhage or decreased venous drainage)
- Foreign material inside the skull (eg. tumour or abscess).
Methods of management: I will not digress extensively about these;
In summary:
- Draining the EVD
- Positioning the head
- Removing the C-spine collar
- Sedation
- Propofol sedation to decrease distress and thus decrease ICP
- Barbiturate coma if other methods of lowering ICP have failed
- Paralysis
- Osmotherapy
- Controversial measures
- Decompressive craniectomy
- Hypothermia
- Dexamethasone
References
Chapter 43 (pp. 563) Cerebral protection by Victoria Heaviside and Michelle Hayes, and
Chapter 67 (pp. 765) Severe head injury by John A Myburgh.
Brain Trauma Organisation Guidelines for Management Traumatic Brain Injury.
Question 12 - 2004, Paper 2
List the possible causes of an altered swallowing reflex in a critically ill patient, and outline how you would assess this.
College Answer
Swallowing is a complex reflex and requires an oral preparatory phase, and oral voluntary phase, a pharyngeal phase and as oesophageal phase. A myriad of potential causes exist. Possible causes of altered swallowing include: drug induced (eg. anti-cholinergic, neuroleptics), mechanical (eg. trauma from Trans-Oesopgageal Echocardiography or endotracheal intubation; presence of tracheostomy; rarely pre-existing structural problems eg. diverticula/pouches), infectious (eg mucositis), metabolic (eg. thyrotoxicosis), myopathic (eg. specific or non-specific neurological syndromes effecting bulbar function) and neurological (eg. stroke, severe head injury, Guillain-Barre syndrome etc.). Assessment is via history (previous problems, recent procedures and medications) and examination (local mechanical and bulbar neurological problems, systemic diseases and
systemic neurology). Specific procedures may involve watching attempts at swallowing (eg. speech therapist ± dye or different consistencies of food, looking for signs of aspiration
etc.), or more sophisticated techniques including naso-endoscopy (mainly anatomic assessment), and video-fluoroscopy or barium swallow (both providing a functional assessment).
Discussion
This question closely resembles Question 14 from the second paper of 2008.
References
Question 15 - 2004, Paper 2
A 62-year-old woman is still not awake 6 hours after clipping of a cerebral aneurysm for a Grade 1 Sub-Arachnoid Haemorrhage. List the potential causes and outline your management strategy.
College Answer
Potential causes of delayed awakening early after surgical clipping of a SAH include specific neurological causes (rebleeding, cerebral infarction/ischaemia [including intra- operative technical problems, hypotension]; too early for vasospasm), metabolic causes (including hypothermia, hypo- or hyper-natraemia and hypo- or hyper-glycaemia, hyper- or hyper-capnia) and pharmacological causes (including prolonged effects of sedatives [relative or absolute] and muscle relaxants [not reversed or prolonged/excessive effects: including suxamethonium apnoea].
Management strategy requires exclusion of treatable causes prioritised according to their urgency. Early consultation with the treating neuro-surgical team is critical. Clinical history and examination reveal details of drugs used (including amounts and timing of doses), temperature, ventilation, haemodynamics, and identifies specific surgical issues/problems. Specific investigations that should be considered range from bedside (eg. nerve stimulator to assess residual neuromuscular blockade, or BIS monitor to assess EEG) and simple blood tests (eg. blood gases [oxygenation and exclude significant abnormalities in ventilation], electrolytes [especially Na] and glucose), to more complex and invasive (eg. repeat head CT [to exclude re-bleed, ischaemia] or angiography). These latter investigations would be organised in concert with the treating neuro-surgical team.
Discussion
The approach to this unconscious patient is going to be vary similar to the generic Approach to the unconscious patient in the ICU except you will have some strong suspicions.
Let us recall the broad list of differentials for unconsciousness, and select from it only those which can be sensibly applied in this instance:
With focal neurological signsVascular causes:
Infectious causes:
Neoplastic causes
Idiopathic causes
Autoimmune causes
Traumatic causes
|
Without focal neurological signsVascular causes:
Infectious causes:
Drug-related causes:
Idiopathic causes
Autoimmune causes
Traumatic causes
Endocrine and metabolic causes:
|
The remaining causes:
- Use of long-acting sedatives (eg. thiopentone) in theatre
- Delayed drug metabolism post-operatively
- Hypothermia and delayed rewarming postoperatively
- Metabolic abnormalities (glucose, CO2)
- Cerebral infarction
- Contusions due to retraction
- Re-bleeding from the aneurysm
- Non-convulsive status epilepticus
Approach to management
- Ensure the ABCs are stable:
- normoxia
- normocapnea
- normotension
- Collect routine bloods and correct the correctable metabolic abnormalities
- Inform the neurosurgeon
- Ask the anaesthetist regarding the specifics of the operation
- Get a CT brain
- Consider an EEG
- Avoid sedatives and muscle relaxants
References
Question 2 - 2005, Paper 1
Critically evaluate the role of EEG and Evoked Potentials in the critically ill.
College Answer
The Electro-EncephaloGram is the recording of brain electrical activity from standard sites on the scalp. It is commonly used in ICU to evaluate patients with abnormal movements or neurological impairment. Studies have not been directed at the use or not of EEGs and their effect on outcome except for prognostication (eg. after cardiac arrests). The EEG is useful to distinguish between potential causes of encephalopathy (eg. metabolic or drug induced) and to establish the presence of and guide therapy for potential epileptiform activity (eg. generalised or focal). More recent applications include prognostication (eg. after cardiac arrests) where it still has significant limitations regarding sensitivity and specificity. The more widespread and successful use of BiSpectral monitoring in anaesthesia to limit the incidence of awareness in high risk patients (“B-Aware” Myles Lancet 2004), may have relevance for some components of ICU practice.
Somato-Sensory Evoked Potentials (SSEP) are the averaged electrical responses in the CNS to somatic stimulation (usually from median nerve at the wrist, or nerves in the leg). The predominant use in Intensive Care has been to evaluate patients after cerebral hypoxic insult (eg cardiac arrest). In this setting median nerve SSEPs (eg. Bilateral absence of the N20 component) have been used in normothermic patients, comatose for at least 72 hours after cardiac arrest, to predict poor outcome with 100% specificity (see metanalysis: Zandbergen Lancet 1998).
Discussion
A 2012 article by Eric S Rosenthal -"The utility of EEG, SSEP, and other neurophysiologic tools to guide neurocritical care"- seems tailor-made to answer this question, even though it was published almost seven years after the paper.
I have used it to compile the tabulated answer below. It is a merger of two tables, available in the respective sections:
Modality |
Advantages |
Disadvantages |
| EEG |
|
|
|
|
||
| SSEPs |
|
|
|
|
||
EEG:
- Advantages
- Characteristic findings can distingusih between different causes of encephalopathy
- Can detect non-convulsive status epilepticus
- Can monitor response to antiepileptic treatment
- Can localise epileptiform activity to a focus
- Can detect organised activity in patients with locked-in syndrome
- Can monitor awareness in anaesthetised patients
- Can be used to confirm brain death
- Non-invasive
- Disadvantages
- This is a low-yield investigation
- It requires specialist interpretation
- It is confounded by sedation and hypothermia
Somatosensory Evoked Potentials (SSEP):
- Advantages:
- Non-invasive
- Absence of responses can be used to confirm diagnosis of severe hypoxic brain injuryafter cardiac arrest
- Can be used to identify cortical blindness
- May be useful in prognostication of neurological recovery after cardiac arrest
- Less confounded by sedation or hypthermia than EEG
- Disadvantages:
- This is a low-yield investigation
- It requires specialist interpretation
- In subarachnoid haemorrhage or traumatic brain injury, it is of limited value
References
Tjepkema-Cloostermans, Marleen Catharina, J. Horn, and M. J. A. M. Putten. "The SSEP on the ICU: Current applications and pitfalls." Netherlands journal of critical care 17.1 (2013): 5-9.
Rosenthal, Eric S. "The utility of EEG, SSEP, and other neurophysiologic tools to guide neurocritical care." Neurotherapeutics 9.1 (2012): 24-36.
Zandbergen, Eveline GJ, et al. "Systematic review of early prediction of poor outcome in anoxicischaemic coma." The Lancet 352.9143 (1998): 1808-1812.
Zandbergen, E. G. J., et al. "SSEPs and prognosis in postanoxic coma Only short or also long latency responses?." Neurology 67.4 (2006): 583-586.
Guérit, J-M., et al. "Consensus on the use of neurophysiological tests in the intensive care unit (ICU): electroencephalogram (EEG), evoked potentials (EP), and electroneuromyography (ENMG)." Neurophysiologie Clinique/Clinical Neurophysiology 39.2 (2009): 71-83.
Question 4 - 2005, Paper 1
Critically evaluate the risks versus benefits for the monitoring of Intra-Cranial Pressure in a patient with a closed head injury.
College Answer
The benefits of monitoring ICP in closed head injury are still debated. Standard guidelines have been published but no prospective studies have demonstrated clear outcome benefits. The main purpose of monitoring the ICP is to allow the clinician to either guide therapy (add or remove) based on the ICP or CPP, or to alert the clinician to changes which may require further investigation. The lowest risk patients are least likely to benefit, so most criteria are based on a combination of patient characteristics and CT abnormalities.
Some risks (eg. haemorrhage) are related to insertion, and others (especially infection) are more likely with longer times in situ. Additional risks are associated with incorrect readings (abnormally high or low leading to the risk inappropriate/un-necessary interventions or investigations. Risks (and additional benefits) associated with ICP monitoring are largely dependent on the type of monitoring device.
Intraventricular catheters are more difficult to place, and are associated with a higher risk of haemorrhage during insertion, and subsequent infection (which increases in incidence with longer time in situ). These catheters have the additional advantage of being able to drain CSF (potentially therapeutic) and sample CSF (monitoring for infection and bleeding). Intraparenchymal devices (eg. fibreoptic Camino system) are easier to insert and are associated with a lower risk of haemorrhage and infection. Unfortunately, the transducer cannot be recalibrated, so reliability becomes a problem.
Less commonly used devices include: subarachnoid bolts which often clog with debris, and epidural catheters which are often inaccurate.
Discussion
The methods of ICP monitoring are discussed elsewhere.
Additionally, the chapter on the indications for ICP monitoring has a section outlining the risks of this practice.
In short:
Risks of ICP monitoring:
- Risks of anaesthesia
- Risks of craniotomy
- Risks of haemorrhage
- Risk of infection
- Malposition and poor monitoring quality
- Incorrect readings may stimulate incorrect management
- EVDs may clog with debris; parenchymal monitors may "drift" from their zero calibration value
- CPP-guided therapy may not improve outcomes
Benefit of ICP monitoring:
- Prevention of secondary brain injury (however, may not improve outcomes)
- Guide for hemodynamic therapy
- Guide for timing of imaging and neurosurgical intervention
- With EVD, the option to drain CSF contributes to ICP management
- With EVD, sampling of the CSF is possible
In detail:
|
|
References
Rosner, M. J., and D. P. Becker. "ICP monitoring: complications and associated factors." Clinical neurosurgery 23 (1975): 494-519.
Bekar, A., et al. "Risk factors and complications of intracranial pressure monitoring with a fiberoptic device." Journal of Clinical Neuroscience 16.2 (2009): 236-240.
Smith, Martin. "Monitoring intracranial pressure in traumatic brain injury."Anesthesia & Analgesia 106.1 (2008): 240-248.
Question 16 - 2005, Paper 1
Compare and contrast the advantages and disadvantages of coiling versus clipping of cerebral aneurysms after Sub-Arachnoid Haemorrhage.
College Answer
Recent published experience demonstrates that there are some significant potential benefits associated with coiling of cerebral aneurysms. These include decreased costs, no need for craniotomy and associated neuroanaesthetic, and increased independent survival (“ISAT” Lancet 2002; 360:1267-74). Other potential advantages include no need for temporary clipping. Major disadvantages include the need for a skilled operator, the fact that technique is not suitable for all aneurysms, requirement for anticoagulation, and inability to deal with major complications. A neurosurgical procedure may still be required if complications ensue.
Clipping has a long track record with clearly defined risks, with no evidence of increased mortality. Most aneurysms are amenable to clipping, though in some regions (eg. posterior fossa), because of accessibility, coiling is considered the procedure of choice. Disadvantages of surgical clipping include need for a skilled operator, a craniotomy and neuroanaesthesia, and potentially increased costs.
Both techniques require some degree of sedation/paralysis, and subsequent neuro-Intensive care with close monitoring and re-evaluation for complications. Either technique may be quite prolonged.
Discussion
The coiling vs clipping debate is aired briefly in the chapter on management of the unsecured aneurysm in subarachnoid haemorrhage. In it, there is this table:
|
Advantages of coiling:
|
Advantages of clipping:
|
|
Disadvantages of coiling
|
Disadvantages of clipping:
|
References
Bakker, Nicolaas A., et al. "International subarachnoid aneurysm trial 2009: endovascular coiling of ruptured intracranial aneurysms has no significant advantage over neurosurgical clipping." Neurosurgery 66.5 (2010): 961-962.
Connolly, E. Sander, et al. "Guidelines for the Management of Aneurysmal Subarachnoid Hemorrhage A Guideline for Healthcare Professionals From the American Heart Association/American Stroke Association." Stroke 43.6 (2012): 1711-1737.
Question 5 - 2005, Paper 2
Compare and contrast the clinical and diagnostic features of ascending polyneuritis (Guillain Barre Syndrome), myasthenia gravis and motor neurone disease.
This could be answered using a table format. Suggestions include the following:
|
ascending, |
myasthenia |
motor neurone |
|
|
weakness |
yes |
yes |
yes |
|
reflexes |
absent |
present |
May be increased (eg. amyotrophic lateral sclerosis) |
|
characteristic distribution |
ascending |
Eyes & cranial |
asymmetrical` |
|
progression |
acute and |
relapsing |
progressive |
|
fatigue |
no |
characteristic |
no |
|
fasiculation |
no |
no |
characteristic |
|
increased CSF protein |
yes |
no |
no |
|
UMN signs present |
no |
no |
May be present(eg. amyotrophic lateral sclerosis) |
|
sensory features |
often dysthesia |
no |
no |
|
pain |
May be |
no |
no |
|
delayed nerve conduction |
yes |
no |
no |
|
fade + post tetanic facilitation |
no |
yes |
no |
|
‘jitter’ on EMG |
no |
no |
yes |
|
response to anticholinesterases |
no |
yes |
no |
|
response to plasmapheresis |
May occur |
yes |
no |
Discussion
Approach to the ICU patient with generalised weakness is discussed elsewhere.
This table is a detailed version. The features listed by the college here have been incorporated into the greater table in the abovelinked summary ("Causes of Weakness in Intensive Care Patients ")
In short:
- Only Guillain-Barre will have delayed nerve conduction, increased CSF protein and sensory features
- Only myasthenia will have characteristic fatiguability, and will respond to anticholinesterase treatment (or plasmapheresis)
- Only motor neuron disease will have increased reflexes, and will be assymetrical.
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
Reeves and Swenson have an excellent online textbook chapter (12) entitled "Evaluation of the Patient with Weakness"
Question 22 - 2005, Paper 2
Outline your principles of management of status epilepticus.
College Answer
Diagnosis: status epilepticus as > 5 minutes generalised convulsive, non-convulsive, (no return of consciousness), simple partial [Definition 2 or more convulsions with no recovery in between, or continuous convulsion > 30 min (alternative more recently accepted definition is > 5 min)]
Support: Airway, Breathing, Circulation.
Control: using hierarchy of drugs: benzodiazepine (midazolam) + phenytoin loading, propofol, barbiturate (phenobarbitone loading, thiopentone infusion), isoflurane, others. EEG to confirm, avoid paralysis.
Restore: therapeutic prophylaxis drugs if appropriate - check levels. Consider add newer generation agent in difficult cases.
Look for and treat cause:
History of epilepsy, Anti-convulsant compliance, Check and correct biochemical disturbance eg Na
(appropriate speed), hypoglycaemia, low Ca++, severe azotemia.
Look for toxins (TCA, theophylline, amphetamine and other recreational drugs, salicylate, glycols, alcohols, hydrocarbons etc).
Diagnose infective, hypoxic, vascular, metabolic or structural (trauma, neoplasm), physical(hyperthermia) cause - CT, LP, MR, porphyrins.
Treat CNS viral and bacterial infection empirically until excluded. Eclampsia specific management including LSCS, Mg, BP control.
Don't forget factitious epilepsy - look for atypical features, check lactate, EEG, reflexes etc. Consider drug withdrawal.
Treat complications - aspiration, rhabdomyolysis, hyperthermia.
Discussion
Its another one of those.
- Attention to the ABCS, with management of life-threatening problems simultanous with a rapid focused examination and a brief history.
- An attempt to reverse the status epilepticus with a bolus dose of benzodiazepine may be undertaken while the above assessment takes place.
- Airway:
- The need for airway support shoud be assessed
- The patient will likely need to be intubated
- This has the added benefit of exposing the patient to barbiturate anaesthetics, benzodiazepines or propofol
- Breathing/ventilation
- Routine pursuit of normoxia and normocapnea;
- Minute volume may need to be titrated up in view of increased metabolic CO2production
- Circulatory support
- Hypotension arsiing from the use of sedating medications may require vasopressors
- Supportive management
- Nutrition, thromboprophylaxis and pressure area care need attention, as the patient may remain immobile for a prolonged period
- Specific investigations
- A CT brain and an EEG to confirm status epilepticus (if it is non-convulsive)are all but mandatory
- Drug screening of serology, urine and history should be undertaken, to exclude reversible causes (eg. intoxication or withdrawal)
- Specific management
- Correction of the aetiology (eg. intoxication)
- First line antiepileptics should be given (phenytoin )
- If response is not achieved, second and third line agents may be deployed (levitiracetam, valproate, benzodiazepine infusion)
- Barbiturate coma may be required with EEG monitoring of response
Related content would consist of the following chapters:
References
Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Chapter 50 (pp. 560) Status epilepticus by Helen I Opdam
Brophy, Gretchen M., et al. "Guidelines for the evaluation and management of status epilepticus." Neurocritical care 17.1 (2012): 3-23.
Question 20 - 2006, Paper 1
An elderly woman presents with a 9 month history of increasing weakness of all four (4) limbs and a two-day history of inability to swallow her saliva, or cough. She is dyspnoeic, hypoxaemic and her Vital Capacity is 400mls. Outline the key features of your management.
College Answer
This appears to be a chronic problem, and there is probably not time to discuss possible/probable
futility of more active therapy. Key features of management should include:
• clinical assessment to help establish the diagnosis (especially sensation, pattern of weakness
[eg. lower motor neurone, long tract signs etc])
• reasonable to intubate/ventilate (hopefully after a full clinical examination has been performed)
• drugs for intubation – such as the acute risk with suxamethonium, and the potential harm associated with the use of neuromuscular blockade
• establishment of specific diagnosis (from disorders of muscle, neuromuscular junction, peripheral nerves, anterior horn cell disease, cord lesions and central lesions)
• collaboration with neurologists,
• relevant investigations (eg. EMG, LP, CT, MRI etc)
• general supportive care, including consideration of early tracheostomy.
Common problems related to lack of relevant detailed knowledge.
Discussion
This question brings about another round of differential diagnosis generation, for the question "what is causing this whole-body weakness". The assessment of the critically ill patient with weakness is well discussed elsewhere.
Thus:
- First, one would take a detailed history, and perform a focused clinical examination, with attention paid to airway and breathing.
- If these are stable (i.e. intubation is not imminent) then a complete neurological examination can be performed.
- Then, the airway control can be definitively established. The patient needs intubation before she aspirates.
- Muscle relaxant choice would rest with some sort of non-depolarising agent
- Once intubated, the ventilation can be addressed, and normoxia established.
- Now, aspiration pneumonia can be investigated with a chest Xray, which would also confirm line placement and ETT position.
- Once the ABCs have been controlled, investigation of the underlying disrder can be approached
- Potential causes and their investigations include
- Central cerebral lesions - CT brain
- Brainstem lesions - CT/MRI
- Spinal cord lesions - MRI
- Infectious and autoimmune CNS pathology - LP
- Peripheral nerves - nerve conduction studies
- NMJ diseases - electromyography (EMG) and acetylcholine receptor antibodies
- Myopathy - raised CK and muscle biopsy
- Critical illness polyneuropathy - clinical diagnosis
- Steroid myopathy - history, and its a clinical diagnosis
- Electrolyte derangement - electrolyte levels
- Collaboration with neurologists is essential, because you will be discharging this patient into their care
- A tracheostomy needs to be thought about if the course of ventilation is expected to be prolonged.
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Jani, Charu. "Critical Illness Neuropathy." Medicine (2011): 237.
Young, G. Bryan, and Robert R. Hammond. "A stronger approach to weakness in the intensive care unit." Critical care 8.6 (2004): 416.
Mareska, Michael, and Laurie Gutmann. "Lambert-Eaton myasthenic syndrome." Seminars in neurology. Vol. 24. No. 2. [New York]: Thieme-Stratton Inc.,[c1981-, 2004.
Question 23 - 2006, Paper 2
A previously fit 36-year-old patient has been admitted to your Intensive Care Unit with an isolated severe head injury. 18 hrs after admission he develops polyuria. Outline the way in which you would evaluate this polyuria.
College Answer
The causes of polyuria in this patient include
a) Diabetes insipidus
b) Mannitol or other diuretics
c) Use of hypertonic saline
d) Cerebral salt wasting syndrome
e) Effects of ingested alcohol prior to the trauma
Evaluation and treatment
a) DI : Serum and urine osmolality and Na measurements,
b) If mannitol: check serum osmolar gap, and ensure it is < 320 mOsm/kg to prevent renal toxicity
c) Hypertonic saline: Large urine outputs are a feature of hypertonic saline therapy and this can be confirmed by high serum and high urine Na.
d) CSW: Low intravasc volume, low serum Na, high urine Na.
e) Residual alcohol: based on index of suspicion, check serum osmolar gap and ethanol levels.
Discussion
LITFL do justice to this topic; theirs is a succinct and accurate answer. In addition to it, one may wish to read a relevant article by Bradshaw and Smith.
To paraphrase the already well-written college answer, the causes of polyuria following a head injury include the following:
- Diabetes insipidus
- Cerebral salt wasting
- Appropriate post-resuscitation diuresis
- Appropriate natriuresis following hypertonic saline infusion
- Mannitol-induced diuresis
- Hypothermic diuresis due to therapeutic cooling
A more detailed tabulated answer would look like this:
Serious differentials:
|
Unlikely differentials:
|
Risk factors for diabetes insipidus in traumatic brain injury:
|
|
An approach to the investigations and management of polyuriaOnce the polyuria is discovered:
After 3 hours of obervation:
If the serum sodium continues to rise, with low urinary sodium and urine osmolality under 300mOsm/kg, consider 0.5μg of DDAVP.
|
|
One should hope that the ADH-inhibiting effects of alcohol would have worn off after 18 hours, or else this gentleman had a minimum blood alcohol level of around 0.36% at the time of his injury (which is not entirely unreasonable).
The college did not ask for treatment options in their question, and so I have offered none.
References
Bradshaw, Kate, and Martin Smith. "Disorders of sodium balance after brain injury." Continuing Education in Anaesthesia, Critical Care & Pain 8.4 (2008): 129-133.
Robertson, Gary L. "Differential diagnosis of polyuria." Annual review of medicine 39.1 (1988): 425-442.
Question 24 - 2006, Paper 2
Define cerebral perfusion pressure (CPP). List the advantages and limitations of using
CPP as a therapeutic target in the management of traumatic brain injury
References
Definition : CPP = MAP-ICP Advantages: Easily monitored
Can be monitored continuously
Nursing staff familiar
BTF guidelines endorse use of CPP at 60
Limitations: Used as a surrogate for CBF
CVR is variable and therefore changes in CBF not detected by CPP
Does not allow for differential autoregulation in the normal and injured brain. Therapy to maintain CPP can result in lung injury
No Class I data to support use
Poor correlation between CPP and indices of brain oxygenation
Discussion
This question closely resembles Question 1 from the second paper of 2009.
References
Question 26 - 2006, Paper 2
You are asked to admit a 76-year-old man with a past history of ischaemic heart disease and paroxysmal atrial fibrillation who has just been intubated in Accident and Emergency after collapsing from a brain stem stroke (diagnosed clinically). He had a Glasgow Coma Score of 6 before being intubated. Outline your management strategy for him for the first 24 hours.
College Answer
Key Features
Obvious attention to ABC.
a) Urgency is required for the best results here. .
b) Investigation: CTA scan of brainstem to exclude a bleed (Although not the best investigation compared to a MRI, but quickest and easiest to arrange) and to elucidate the vascular supply. Plus exclusion of an embolic cause ie TOE should be done.
c) Therapy: Discussion with neurologist/interventional neuroradiologist re urgent regional thrombolysis/ angioplasty / platelet antagonists. .
d) Discussion with family re therapy and outlook.
Discussion
This brainstem stroke question is another one of these "outline your management" questions, where one ought to go through a stereotypical pathway. Yes, you would direct your attention to the A B Cs and you would maintain airway patency, ensure normoxia and normocapnea with mechanical ventilation, etc etc. Ultimately, it is not the general supportive management which is the real question here. The college - I assume - wants to know how well you understand the management of stroke. This topic is well explored elsewhere.
In brief:
Definitive management option:
- Intravenous thrombolysis
- Intraarterial thrombolysis
- Endovascular embolectomy
- Conservative management and subsequent antiplatelet therapy
Supportive management:
- Airway: intubation, for the protection thereof (being mindful that it may be futile)
- Ventilation: aiming for normocapnea and normoxia
- Circulatory support: to keep BP normal, and below 220 mmHg systolic (or 180 if thrombolysis is being explored as an option)
- Sedation: as needed to tolerate ICU management in comfort
- Management of raised intracranial pressure is not going to be a major issue outside of the setting of malignant MCA.
- If the brainstem stroke is extensive or involves a large proportion of the cerebellum, decompression may still be relevant. Hydrocephalus may eventually develop and an EVD may be useful as a route of CSF egress.
- Electrolyte and endocrine control: ensuring normoglycaemia and normothermia
- Fluid balance management to ensure protection of renal function following contrast
- Enteric nutrition may commence by the nasogastric route
- Heparin is not indicated given the risk of haemorrhagic transformation
- Family discussion so as to address the possibility of poor prognosis
After the airway has been controlled, the ventilation managed and the circulation appropriately supported, one needs to establish whether this patient has had an embolic stroke (from his AF) or whether there has been a haemorrhage. This is best done with a non-contrast CT brain.
If a haemorrhage has developed, giving features of brainstem pathology, it must be a central one, or one which is extensive. In any case, hydrocephalus may develop, and one would get on the phone to the neurosurgeons to get an EVD in, if not to evacuate the bastard. Surely the earlier this is done the better.
If there is no haemorrhage, there is no point debating whether the stroke is embolic or ischaemic. One would give thrombolysis immediately. The evidence for this is discussed elsewhere. Suffice to say, we give people alteplase because the NINDS Study demonstrated a neurological recovery benefit without any increased bleed-related mortality. Mechanical embolectomy is an option if thrombolysis is contraindicated, but it is a poorer option, and not as well supported.
Then, the next 24 hours will be spent in anxious anticipation of a killing-blow intracranial bleed (as with thrombolysis) or recovering from neurosurgical evacuation and EVD insertion. In either case, one ought to have a word with the next of kin, so as to manage their expectations.
Though not immediately indicated, a carotid doppler and TOE should be performed to determine whether the carotid artery or the fibrillating atrium are sources of the clot.
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer.
The Internet Stroke Centre has an excellent summary of stroke syndromes.
Kammersgaard, Lars Peter, et al. "Short-and long-term prognosis for very old stroke patients. The Copenhagen Stroke Study." Age and Ageing 33.2 (2004): 149-154.
National Collaborating Centre for Chronic Conditions (Great Britain). "Stroke: national clinical guideline for diagnosis and initial management of acute stroke and transient ischaemic attack (TIA)." Royal College of Physicians, 2008.
Friedman, Howard S., W. J. Koroshetz, and N. Qureshi. "Tissue plasminogen activator for acute ischemic stroke." N Engl J Med. 1995;333(24):1581.
Question 4 - 2007, Paper 1
Discuss the use of hypertonic saline in the treatment of intra-cranial hypertension following head injury.
College Answer
Principal Advantages
• The effect is rapid, peaking at 10 minutes and waning after 1 hour.
• End point for therapy is serum Na between 145-155 and easily achieved in ICU through blood gas machines.
• Less potential for hypovolemia than with mannitol.
• May have a better effect on CBF for a given reduction in ICP.
• Theoretical benefit in modulating the inflammatory response
• HS is inexpensive
Disadvantages
• Need for a central venous access .
• "Hypokalaemia and hyperchloraemic acidosis
• Lack of outcome data,
• Increase in circulating volume and risk of CCF.
• Coagulopathy-HS may affect APTT and INR as well as platelet aggregation.
• Rapid changes in serum sodium concentrations may result in seizures and encephalopathy
• Some suggest that HS affects normal brain more that injured brain which theoretically may worsen herniation
Discussion
The use of hypertonic saline in the treatment of raised intracranial pressure falls within the realm of osmotherapy, which enjoys a thorough discussion elsewhere:
- Intracranial pressure as a therapeutic target
- Management of raised intracranial pressure
- Osmotherapy for management of raised intracranial pressure
From those summary, a table of comparison can be compiled, which is presented below.
Category |
Mannitol |
Hypertonic saline |
| Advantages |
|
|
| Disadvantages |
|
|
References
Chapter 43 (pp. 563) Cerebral protection by Victoria Heaviside and Michelle Hayes, and
Chapter 67 (pp. 765) Severe head injury by John A Myburgh.
Francony, Gilles, et al. "Equimolar doses of mannitol and hypertonic saline in the treatment of increased intracranial pressure*." Critical care medicine 36.3 (2008): 795-800.
Kamel, Hooman, et al. "Hypertonic saline versus mannitol for the treatment of elevated intracranial pressure: A meta-analysis of randomized clinical trials*."Critical care medicine 39.3 (2011): 554-559.
Nau, Roland. "Osmotherapy for elevated intracranial pressure." Clinical pharmacokinetics 38.1 (2000): 23-40.
Rickard, A. C., et al. "Salt or sugar for your injured brain? A meta-analysis of randomised controlled trials of mannitol versus hypertonic sodium solutions to manage raised intracranial pressure in traumatic brain injury." Emergency Medicine Journal (2013).
Lazaridis, Christos, et al. "High-Osmolarity Saline in Neurocritical Care: Systematic Review and Meta-Analysis*." Critical care medicine 41.5 (2013): 1353-1360.
Bhardwaj, Anish, and John A. Ulatowski. "Hypertonic saline solutions in brain injury." Current opinion in critical care 10.2 (2004): 126-131.
Arbabi, Saman, et al. "Hypertonic saline induces prostacyclin production via extracellular signal-regulated kinase (ERK) activation." Journal of Surgical Research 83.2 (1999): 141-146.
R LAWRENCE REED, I. I., et al. "Hypertonic saline alters plasma clotting times and platelet aggregation." Journal of Trauma-Injury, Infection, and Critical Care 31.1 (1991): 8-14.
Question 5 - 2007, Paper 1
List the causes of the various pupillary abnormalities which may assist in the differential diagnosis of the comatose patient
College Answer
|
ABNORMALlTY |
CAUSE |
NEUROANATOMICAL |
|
Miosis{<2mm in size) Unilateral |
Homer's syndrome |
Sympathetic paralysis |
|
Bilateral |
Pontine lesions |
Sympathetic paralysis |
|
Drug ingestion |
||
|
Organophosphate |
Cholinesterase inlnoition |
|
|
Barbiturate |
||
|
Narcotics |
Cetrtral Effect |
|
ABNORMALITY |
CAUSE |
NEUROANATOMICAL |
|
Mydriasis (>5mm in size) Unilateral fixed pupil |
Midbrain lesion |
3 'nerve damage |
|
. Bilateral fixed pupils |
Massive midbrain |
Bilateral 3rd nerve damage Mesencephalic damage |
|
Drugs |
||
|
Atropine |
Paralysis of athetics |
|
|
Tricyclics |
Prevent local reuptake of catecholamines by nerve |
|
|
Sympathomimetics |
Stimulation of sympathetics |
|
Discussion
The college produces a nice table of explanations. Unfortunately, my copy-and-paste process has done some serious harm to its layout. In reponse to this failure, I have produced my own table, which neither better nor worse than the college table. This table can be found in the chapter on Examination of pupil reactivity and diameter (CN II, III)
| Unaided observations of the pupillary diameter | ||
| Miosis | Bilateral miosis | Bilateral pontine lesion, with damage to the descending sympathetic fibers |
| Bilateral thalamic lesion, also with damage to decsending sympathetic fibers | ||
| Opiate intoxication | ||
| Organophosphate poisoning (thus, a pharmacological excess of parasympathetic stimulation) | ||
| Barbiturate poisoning | ||
| Unilateral miosis | Horner's syndrome | |
| Sympathetic damage at any level:
Ipsilateral thalamic lesion Ipsilateral pontine lesion Ipsilateral sympathetic chain lesion |
||
| Mydriasis | Bilateral mydriasis | That is what the end of brainstem herniation looks like |
| Bilateral midbrain lesion- eg. basilar artery infarct | ||
| Bilateral 3rd nerve damage, eg. due to severe base of skull fracture | ||
| Severe global brain injury (eg. due to hypoxia) | ||
| Anticholinergic drugs | ||
| Sympathomimetic drugs | ||
| Serotonin syndrome | ||
| Unilateral mydriasis | Midbrain lesion- ipsilateral damage to the Edinger-Westphal nucleus of the 3rd nerve (thus resulting in loss of parasympathetic input to the ipsilateral eye) | |
| Uncal herneation - stretch of the 3rd nerve across the petroclinoid ligament | ||
| Direct trauma to the eyeball | ||
The reaction to light |
||
| Normal consensual reaction of both pupils | The optic nerve on the tested side, the midbrain and both the third nerves are probably intact. Massive midbrain damage can be ruled out. | |
| Failure of either pupil to constrict | Either the tested optic nerve is damaged and light is not registering in the midbrain, or the midbrain is massively damaged. | |
| Successful constriction of the tested pupil, but failure of conjugate constriction | ||
The reaction to swinging light |
||
| The pupils consensually constrict in the presence of light, and rapidly re-dilate when the light source is removed. | Normally, with swinging light, the pupils of both eyes will constrict whenever light is directed at either pupil. This demonstrates normal optic nerve, 3rd nerve and midbrain function. | |
| With rapid sequential light stimulus, the affected pupil will paradoxically dilate in response to light. | This is an afferent pupilalry defect, or a Marcus Gunn pupil. It means that the tested optic nerve is damaged in the pre-chiasmal portion. During the swinging light test, there is a moment when the contralateral (healthy) pupil is again submerged in darkness, while the ipsilateral (affected) pupil has light shining upon it. With the darkness stimulating the dilation of both pupils, and the light stimulating nothing (owing to the optic nerve pathology on the tested side), the pupil exposed to light will dilate abnormally, until it is the same diameter as the unlit pupil. | |
Test of accomodation |
||
| The pupil dilates to observe distant objects, and constricts to regard near objects. | This is a normal accomodation reflex. | |
| The pupil accomodates to near and far objects,but fails to react to light | This is an Argyle-Robertson pupil, and it is seen in various conditons:
Syphilis Diabetes Alcoholic midbrain degerenation |
|
References
Clinical Methods: The History, Physical, and Laboratory Examinations. 3rd edition. Chapter 58 The Pupils - by Robert H. Spector.
Broadway, David C. "How to test for a relative afferent pupillary defect (RAPD)."Community Eye Health 25.79-80 (2012): 58.
Fincham, Edgar F. "The accommodation reflex and its stimulus." The British journal of ophthalmology 35.7 (1951): 381.
Question 10 - 2007, Paper 1
Critically evaluate the current approaches to the treatment of cerebral vasospasm following aneurysmal subarachnoid haemorrhage.
College Answer
Treatment
b) Triple H therapy-HT, hypervolemia and hemodilution-controversial, not evidence based
c) Early clipping / coiling
d) Nimodipine -useful in prophylaxis,
e) Endoluminal·therapies: Balloon angioplasty and intra-arterial papaverine
Investigational therapies -proven in animal models, no hard clinical evidence, no RCT
1) Statins-Early human data
2) Cisternal tPa
3) Endothelin antagonists
Discussion
This topic is well developed in the chapter on subarachnoid haemorrhage.
True to the college answer, there is only strong evidence for nimodipine and endovascular vasodilators. Of the "triple-H" therapy, the only evidence-based component is probably hypertension, and even this is being debated.
Judging by the college answer, they did not want a discussion of Class I recommendations from highly regarded advisory bodies. The model answer mentions some wacky "failed therapies" for vasospasm which have subsequently receded into historical background noise.
In summary:
Well-supported therapies
- Once vasospasm is suspected, DSA (the gold standard investigation) should be performed.
- On DSA, one can access the vessels involved and inject intra-arterial papaverine or verapimil.
- Nimodipine is the only preventative pharmacotherapy supported by evidence. The BRANT trial from England has demonstrated a 34% decrease in the risk of SAH-induced stroke.
- Of the "Triple H" circulating volume expansion strategies, only hypertension persists as a valid treatment - and it is only supported by a consensus of neurosurgeons.
Poorly supported therapies
- "Triple H therapy" in general- i.e. prophylactic hypertension, haemodilution and hypervolaemia - has little to recommend it. Myburgh was already tearing shreds out of it in 2005.
- Intrathecal thrombolysis is promising, but not well supported - a 2004 Japanese study found intrathecal urokinase decreased the incidence of vasospasm by almost 50%.
- Statins - no benefit (STASH trial)
- Endothelin 1 antagonists (eg. clazosentan) - no strong support, perhaps some subtle benefit (CONSCIOUS-1 trial)
- Magnesium – no benefit (MASH-2 trial)
- Tirilazad - a non-glucocorticoid aminosteroid that blocks lipid peroxidation - fiver RCTs; only one showed any benefit, and its efect was lost in the noise accoridng to a Cochrane meta-analysis.
- Fasudil - a Rho kinase inhibitor that prevents the effects of extracellular calcium on smooth muscle contraction - promising on the basis of 8 RCTs, but still not fully supported by the evidence according to a 2012 meta-analysis.
- Eicosapentaenoic acid - which also inhibits Rho kinase, like fasudil - promising results of one small study (the EVAS trial); thus far it still falls into the "experimental" category.
References
Connolly, E. Sander, et al. "Guidelines for the Management of Aneurysmal Subarachnoid Hemorrhage A Guideline for Healthcare Professionals From the American Heart Association/American Stroke Association." Stroke 43.6 (2012): 1711-1737.
Myburgh, J. A. "Triple h” therapy for aneurysmal subarachnoid haemorrhage: real therapy or chasing numbers." Crit Care Resusc 7.3 (2005): 206-212.
Bederson, Joshua B., et al. "Guidelines for the management of aneurysmal subarachnoid hemorrhage a statement for healthcare professionals from a special Writing Group of the Stroke Council, American Heart Association."Stroke 40.3 (2009): 994-1025.
Kawamoto, Shunsuke, et al. "Effectiveness of the head-shaking method combined with cisternal irrigation with urokinase in preventing cerebral vasospasm after subarachnoid hemorrhage." Journal of neurosurgery 100.2 (2004): 236-243.
Vergouwen, Mervyn DI, et al. "Biologic effects of simvastatin in patients with aneurysmal subarachnoid hemorrhage: a double-blind, placebo-controlled randomized trial." Journal of Cerebral Blood Flow & Metabolism 29.8 (2009): 1444-1453.
Macdonald, R. Loch, et al. "Clazosentan to Overcome Neurological Ischemia and Infarction Occurring After Subarachnoid Hemorrhage (CONSCIOUS-1) Randomized, Double-Blind, Placebo-Controlled Phase 2 Dose-Finding Trial."Stroke 39.11 (2008): 3015-3021.
Question 11 - 2007, Paper 1
A sixty year old male is brought unconscious to the hospital after a motor vehicle accident. He has an initial GCS of 6 and is intubated at the scene. A non contrast CT head is performed.
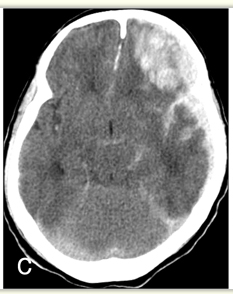
a) List the most significant abnormalities that are present on this CT scan? ·
b) List the major factors that may adversely affect his prognosis?
c) What is the simplest score in common usage that could be used to describe the patient's outcome?
College Answer
a) List the most significant abnormalities that are present on this CT
scan? ·
a) R. fronto parietal subdural
b) Midline shift
c) Obliteration of R.lateral ventricle
d) Effacement of sulci
e) Traumatic subarachnoid hemorrhage
f) Contusions
b) List the major factors that may adversely affect his prognosis?
a) Age
b) ICP control
c) Severity of injury - GCS, traumatic SAH
d) Hypoxia
e) Hypotension
c) What is the simplest score in common usage that could be used to describe the patient's outcome?
a) (Extended) Glasgow outcome score
b) SF-36
Discussion
The image for the CT I have used is obviously not the (missing)image from the college paper, but one which was used in this BMJ paper to illustrate the progression of SAH. On this CT, there is an SDH, an SAH and cerebral contusions which are undergoing haemorrhagic transformation. Certainly, the ventricle and the sulci are effaced, and grey-white differentiation is lost.
As for the prognostic influences on the fate of traumatic brain injury patients - these are well covered elsewhere. I will summarise by saying that they consist of
- Age over 60
- Low presenting GCS
- The presence of pupillary abnormalities
- An abnormal CT
- Hypoxia and hypotension
- Medical comorbidities
The utility of the Glasgow Coma Scale is also discussed in another chapter; and the SF-36 is not in common use. The GCS was actually initially designed with outcome in mind, and the motor components particularly are well correlated with survival.
The college answer mentions the Extended Glasgow Coma Score (which is the eight-point version). This revision was made by Jennett et al in 1981, to better classify patients who had regained consciousness.
References
Chesnut, R. M., et al. "Part 2: Early indicators of prognosis in severe traumatic brain injury." Journal of Neurotrauma 17.6-7 (2000): 555-+.
Fearnside, Michael R., et al. "The Westmead Head Injury Project outcome in severe head injury. A comparative analysis of pre-hospital, clinical and CT variables." British journal of neurosurgery 7.3 (1993): 267-279.
TEASDALE, GRAHAM, and BRYAN JENNETT. "Assessment of coma and severity of brain damage." Anesthesiology 49.3 (1978): 225.
Green, Steven M. "Cheerio, laddie! Bidding farewell to the Glasgow Coma Scale." Annals of emergency medicine 58.5 (2011): 427-430.
Gill, Michelle R., David G. Reiley, and Steven M. Green. "Interrater reliability of Glasgow Coma Scale scores in the emergency department." Annals of emergency medicine 43.2 (2004): 215-223.
Riechers, Ronald G., et al. "Physician knowledge of the glasgow coma scale."Journal of neurotrauma 22.11 (2005): 1327-1334.
Jennett, B., et al. "Disability after severe head injury: observations on the use of the Glasgow Outcome Scale." Journal of Neurology, Neurosurgery & Psychiatry 44.4 (1981): 285-293.
Question 30 - 2007, Paper 1
List the potential causes of delayed awakening in a patient after a prolonged stay in Intensive Care and outline how you would determine what factors were contributory.
College Answer
Potential causes include:
prolonged effects of sedative drugs, metabolic encephalopathy (especially renal or hepatic failure), endocrine problems (especially hypothyroidism), systemic sepsis, and a myriad of specific neurological problems ( eg. status epilepticus, raised intracranial pressure, intracranial haemorrhages, severe Guillain Barre, critical illness polyneuropathy). Residual muscular paralysis must be excluded.
Sedative drugs may have a prolonged effect because of altered kinetics (including context sensitive half-time, or decreased biotransformation or excretion eg. renal or hepatic failure) or altered dynamics (potentiation of effect by other drugs or organ
failure, sensitivity to effect of usual dosage).
Assessment of contributory factors may be a complex process. Important steps include:
1) Detailed history of neurological state, drugs administered, previous neurological problems
2) Careful examination (in particular neurological, but also for signs of other chronic diseases). Detailed neurological exam should include global CNS assessment (including ability to move eyes or poke out tongue if no other apparent motor responses: locked in syndrome, severe myoneuropathy), and search for focal signs (pupils, tone, movement, reflexes). Nerve stimulator should be used to assess residual paralysis.
3) Biochemical investigations for severity of electrolyte imbalance, creatine kinase, renal and hepatic dysfunction (mcluding ammonia), and to exclude treatable endocrine disorders (including T4/TSH).
4) Consider use of specific reversal agents (eg. naloxone and flumazenil [may need multiple ampoules]). ·
5) May require other specific investigations (but put into context, and not done as a routine). Such investigations include CT scan of head, MRI, EEG, EMG and lumbar puncture.
Discussion
This is a question about the approach to the unconscious patient in the ICU, with a view to generate a nice juicy series of differentials. The key feature of the question is that the patient is failing to wake after a prolonged ICU stay.
Let us go though the differentials systematically.
With focal neurological signsVascular causes:
Infectious causes:
Neoplastic causes
Idiopathic causes
Autoimmune causes
Traumatic causes
|
Without focal neurological signsVascular causes:
Infectious causes:
Drug-related causes:
Idiopathic causes
Autoimmune causes
Traumatic causes
Endocrine and metabolic causes:
|
How does one approach such a patient?
- A history is mandatory
- A physical examination is in order, looking for focal signs and characteristic findings
- Some basic bloods, looking for hepatic and renal derangement
- One ought to at least think about reversal agents such as naloxone.
- A CT brain, to exclude structural cerebral disease
- An LP or MRI may be in order depending on the history
- An EEG may be the last investigation, to exclude non-convulsive status epilepticus
References
Oh's Intensive Care manual: Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Question 3 - 2007, Paper 2
A 20 year old female in ICU following a diffuse axonal head injury develops a severe exacerbation of intracranial hypertension on day 3. She is mechanically ventilated, paralysed and sedated. Investigations during a subsequent episode of marked polyuria are summarised below.
|
Variable |
Normal range |
||
|
pH |
7.50 |
||
|
PaCO2 |
28mm Hg |
||
|
HCO3- |
21mmol/L |
||
|
Standard base excess |
-1.5mmol/L |
||
|
Sodium |
147mmol/L |
(135 -145) |
|
|
Potassium |
3.2mmol/L |
(3.2 - 4.5) |
|
|
Chloride |
110mmol/L |
(100 -110) |
|
|
Urea |
3.0mmol/L |
(3.0 - 8.0) |
|
|
Creatinine |
65Dmol/L |
(50- 100) |
|
|
Glucose |
4.0mmol/L |
(3.0 – 6.0) |
|
|
Measured plasma osmolality |
333mosmol/kg |
||
|
Urine osmolality |
410mmol/L |
||
1) What is the most likely explanation for the polyuria?
2) Give the reasoning behind your answer.
3) What action needs to be taken concerning the polyuria, and why?
4) Describe the acid-base status
5) What action needs to be taken concerning the ventilation, and why?
College Answer
1. Mannitol therapy
2. There is increased measured plasma osmolality with an elevated osmolar gap. The
gap is 44 mosmol/kg, if we use a calculated osmolality of 1.86 × ([Na] + [K]) + [urea]
+ [glucose]. If we use the simple formula of 2 × [Na] + [urea] + [glucose] for calculated osmolality, the gap is 32 mosmol/kg. (There are also other formulae which are more difficult to remember). In the setting of treatment for an exacerbation of intracranial hypertension, the increased osmolar gap is likely to be due to mannitol administration. The high urinary osmolality rules out diabetes insipidus, and supports the diagnosis of mannitol induced polyuria.
3. Mannitol should be ceased until the measured plasma osmolality is < 320 mosmol/kg.
There is no benefit and higher death rates in case controlled studies at higher induced osmolality.
4. Acute (uncompensated) respiratory alkalosis.
5. Minute ventilation should be reduced as soon as possible to return the PaCO2 to 35 –
40 mm Hg. Hypocapnia should be reserved for brief intermittent use to buy timeduring critical neurological events (eg pupillary dilation, new lateralising signs). Prolonged hypocapnia reduces cerebral blood flow and oxygenation, and eventually becomes ineffective as CSF pH returns towards normal.
Discussion
This question is remarkably similar to Question 3.1 from the second paper of 2010, and Question 22.1from the second paper of 2011.
Let us dissect these results systematically.
- The A-a gradient cannot be calculated
- There is alkalaemia
- The PaCO2 is contributing to the alkalosis
- The SBE is -1.5, suggesting a normal acid-base balance; it and the bicarbonate is mildly decreased suggesting a trend towards metabolic acidosis
- The metabolic compensation is appropriate. It is expected that the bicarbonate would decrease by 2mmol/L for every 10mmHg decrease in PaCO2, and thus we would expect to see a bicarbonate value around 22, which we do.
- The anion gap is slightly raised:
(147+3.2) - (110+21) = 19.2
The delta ratio suggests that there is a combination of pure high anion gap metabolic acidosis and metabolic alkalosis here.
(19.2 - 12) / (24 - 21) = 2.4 - The osmolar gap is increased:
333 - (2 × 147 + 3 + 4) = 32 (normal is under 10)
The head injury story and the polyuria together make one want to cry "DI!" but in actual DI the urinary osmolality is frightfully low, as torrents of dilute urine issue forth from the vasopressin-deficient patient. The urinary osmolality here is given, so that the candidate does not become confused. The history of a recent spike in ICP inflames the imagination, promoting the idea that someone may have given this patient some hypertonic syrup.
The physiological consequences of mannitol therapy are discussed in greater detail elsewhere.
So, "what action needs to be taken" concerning the polyuria?
Well. The mannitol should be ceased, for one. And then the tincture of time should be liberally applied. The mannitol will exit via the urine, taking with it some water, and the serum osmolality will settle into a more tolerable range.
The ventilation adjustment required to correct this hyperventilation is a decreased respiratory rate. No head-injured patient needs a PaCO2 of 28; hyperventilation in head injury is a last-ditch effort to decrease intracranial pressure, and it may reduce cerebral blood flow in the process.
References
UpToDate has a nice article on the complications of mannitol therapy.
The specific features of it, being the diuresis and the resulting electrolyte derangement, are well explored in this ancient yellowed scroll from NEJM:
GIPSTEIN RM, BOYLE JD. HYPERNATREMIA COMPLICATING PROLONGED MANNITOL DIURESIS. N Engl J Med. 1965 May 27;272:1116-7.
Question 7 - 2007, Paper 2
You are asked to review a 48 year old man with a moderate head injury following a bicycle accident 1 hour ago.
a) What do you understand by the term moderate head injury?
b) List the major determinants of prognosis in moderate traumatic brain injury?
c) What additional factors would warrant admission of these patients to an intensive care or a high dependency unit?
College Answer
A moderate head injury has a presenting coma score in the range 9 to 12 or 13, and is the best score in the absence of sedation and post non-surgical resuscitation.
Prognostic determinants:
a) Age > 60
b) Pupillary abnormalities
c) Presence of hypotension and hypoxia
d) CT scan abnormalities – intracranial collections, presence of traumatic subarachnoid haemorrhage
e) Co-morbidities
Factors warrant admission in intensive care :
i) Presence of a skull fracture,
j) convulsions,
k) influence of any drug including alcohol, anticoagulation,
l) presence of other injuries
Discussion
Well, from one's feeble memory one may be able to extract the recollection that "mild" head injury is one with a GCS of 14-15, and "severe" head injury is a GCS of less than 8, which would mean that "moderate" head injury should have a GCS between 9 and 13.
The major determinants of prognosis are
- Age
- GCS on admission
- Hypotension
- Hypoxia
- Pupillary abnormalities
- CT scan abnormalities
- Medical comorbidities
Prognosis in severe brain injury is discussed elsewhere.
What factors would warrant admission of these patients to an intensive care or a high dependency unit? Well. The semiconscious patient in general should be managed in the ICU or HDU. But more precisely, I would use the following criteria:
- Need for airway control
- Seziures and the sedating consequences of benzodiazepines
- Multiple traumatic injuries
- Multiple medical comorbidities
- Influence of illicit substances, distorting the level of consciousness and decreasing the accuracy of physical examination though incooperation.
References
Wu, Christopher L., et al. "Thoracic epidural analgesia versus intravenous patient-controlled analgesia for the treatment of rib fracture pain after motor vehicle crash." Journal of Trauma-Injury, Infection, and Critical Care 47.3 (1999): 564-567.
MACKERSIE, ROBERT C., et al. "Prospective evaluation of epidural and intravenous administration of fentanyl for pain control and restoration of ventilatory function following multiple rib fractures." Journal of Trauma-Injury, Infection, and Critical Care 31.4 (1991): 443-451.
Kieninger, Alicia N., et al. "Epidural versus intravenous pain control in elderly patients with rib fractures." The American journal of surgery 189.3 (2005): 327-330.
Moon, M. Ryan, et al. "Prospective, randomized comparison of epidural versus parenteral opioid analgesia in thoracic trauma." Annals of surgery 229.5 (1999): 684.
Jarvis, Amy M., et al. "Comparison of epidural versus parenteral analgesia for traumatic rib fractures: a meta-analysis." OPUS 12 (2009): 50-57.
Scherer, R., et al. "Complications related to thoracic epidural analgesia: a prospective study in 1071 surgical patients." Acta anaesthesiologica scandinavica 37.4 (1993): 370-374.
Kapral, Stephan, et al. "The effects of thoracic epidural anesthesia on intraoperative visceral perfusion and metabolism." Anesthesia & Analgesia 88.2 (1999): 402-406.
Question 16 - 2007, Paper 2
Outline the important distinguishing clinical features and the site of lesion for the following neurological states (you may tabulate your answer).
a) Locked in syndrome (de-efferented state)
b) Persistent vegetative state
c) Akinetic mutism
College Answer
|
Syndrome |
Features |
Site of lesion |
|
Locked-in |
Alert and aware, vertical eye movements present, and able to blink. Quadriplegic, lower cranial nerve palsies, no speech , facial or pharyngeal movements |
Bilateral anterior pontine lesion |
|
Persistent |
Previously comatose, who now appear to be awake. Spontaneous limb movements, eye movements and yawning seen. However patient inattentive, no speech, no awareness of environment and total inability to |
Extensive damage to both cerebral |
|
Akinetic |
Partially or fully awake patient, immobile and silent |
Lesion in bilateral frontal lobes or hydrocephalus or third ventricular masses |
Discussion
A description of the various vegetable-like states is available elsewhere.
It is easy to summarise:
PVS is characterised by a preserved autonomic regulation and sleep-wake cycle, but the absence of any behavioural evidence of consciouseness. The lesion is typically diffuse, eg. severe hypoxic brain injury.
Locked in syndrome is usually caused by damage to the ventral pons, and the characteristic features are total tetraplegia and facial/oral musuclar paralysis, with preserved eye opening and vertical eye movements, in the presence of a totally intact level of consciousness.
Akinetic mutism is usually caused by bilateral frontal lobe damage, and the characteristic features are immobility and silence with preserved eye tracking. These people are not paralysed, but rather lack any volition to move.
The abovelinked summary contains a table to help discriminate between states of persistent unconsciousness, which I will reproduce below to simplify revision.
| Category | Chronic Coma | Persistent vegetative state (PVD) | Minimally conscious state | Locked-in syndrome | Alinetic mutism | Brain death |
| Awareness |
None |
None |
Some |
Totally alert |
Some |
None |
| Sleep-wake cycle |
None |
Present |
Present |
Present |
Present |
None |
| Response to pain |
Possibly |
Possibly |
Present |
Only in eyes |
Present |
None |
| GCS |
E1-2 M1-4 V1-2 |
E4 V1-2 M1-4 |
E4 V1-4 M1-5 |
E4 M1 V1 |
E4 V1-4 M4 |
E1 V1 M1 |
| Motor function |
Nothing purposeful |
Nothing purposeful |
Some purposeful-seeming motor behaviour |
Immobile |
Nothing voluntary |
None |
| Respiration |
Possibly spontaneous |
Spontaneous |
? |
Possibly spontaneous |
Spontaneous |
None |
| EEG features |
Slow wave activity |
Slow wave activity |
? |
Completely normal |
Slow wave activity |
Isoelectric |
| PET: cerebral metabolism |
Severely reduced |
Severely reduced |
? |
Normal, except the area of the lesion |
Reduced |
Absent |
This table, as the summary it is derived from, is based heavily on the diagnostic guidelines published in 2003 by the Royal College of Physicians.
References
Oh's Intensive Care manual: Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Working Party of the Royal College of Physicians. "The vegetative state: guidance on diagnosis and management." Clinical Medicine 3.3 (2003): 249-254.
Schnakers, C., J. Giacino, and S. Laureys. "Coma: Detecting signs of consciousness in severely brain injured patients recovering from coma."Coma Science Group, Cyclotron Research Centre University of Liege, Liège, Belgium
Monti, Martin M., Steven Laureys, and Adrian M. Owen. "The vegetative state."Bmj 341.c3765 (2010): 292-296.
Giacino, Joseph T., et al. "The minimally conscious state definition and diagnostic criteria." Neurology 58.3 (2002): 349-353.
Plum, Fred, and Jerome B. Posner. The diagnosis of stupor and coma. Vol. 19. Oxford University Press, 1982.
Smith, Eimear, and Mark Delargy. "Locked-in syndrome." BMJ: British Medical Journal 330.7488 (2005): 406.
Cairns, Hugh, et al. "Akinetic mutism with an epidermoid cyst of the 3rd ventricle." Brain 64.4 (1941): 273-290.
Question 8 - 2008, Paper 1
Outline the advantages and disadvantages of the various techniques used in the diagnosis and monitoring for vasospasm secondary to aneurysmal subarachnoid haemorrhage.
College Answer
Techniques that have proven or demonstrated potential in the diagnosis and monitoring of vasospasm include:
Clinical; in the conscious patient, may be detected clinically by new focal neurology or a drop in GCS.
Major disadvantage is lack of specificity often necessitating CT/angiography. EEG; May provide prognostic information, focal areas of slowing correlate with
angiographic vasospasm and a decrease in alpha to delta ratio strongly correlates with ischaemia. Sensitivity and specificity for detecting vasospasm is high.
Disadvantage: Not readily available however and their may be issues with interpretation.Conventional 4 vessel DSA angiography-
- remains the gold standard for diagnosis of DIND
- may allow therapeutic intervention (angioplasty) at the time.
Disadvantages -invasive, risks of bleeding, embolism, radiation/contrast exposure and transport. Requires skilled interventional radiology and therefore resource heavy.
Transcranial Doppler (TCD):
- It is low risk, performed at the bedside, non invasive and able to be repeated daily enabling trend analysis.
Disadvantages:
- The technique is however operator dependent and there is a high inter observer variability.
- Debate exists regarding correlation of flow velocity and vasospasm and although high velocities (> 200cm/sec) are predictive, lower velocity may not be as good.
- The technique may be more accurate when MCA velocity is indexed to the ipsilateral extracranial carotid artery (Lindegaard index, >3 strongly predictive).
- Colour coded TCD may offer greater accuracy than plain TCD alone.
CTA/MRI: may be combined with perfusion allowing characterisation of both vascular anatomy and associated perfusion abnormalities.
Image clarity will be affected by clip/coil and contrast related issues need consideration. The overall diagnostic capability of this modality however remains unclear until further prospective studies are performed. MR diffusion weighted imaging accurately identifies brain tissue at high risk of infarction; perfusion weighted imaging reveals asymmetries in regional perfusion. Both methods show correlation with DIND
SPECT/PET:
-can be used to obtain a picture of brain perfusion and metabolism and have shown variable correlation with vasospasm as assessed by more conventional methods.
Disadvantages: They are resource heavy not easily available, radiation exposure, patient transport are issues.
The use of measures of tissue oxygenation using parenchymal sensors and microdialysis for monitoring biochemical indices of ischaemia are largely research tools.
Discussion
This question closely resembles Question 2 from the second paper of 2013.
References
Question 27.2 - 2008, Paper 1
Examine the photograph below.

a) List the indications for the use of this device in traumatic brain injury.
b) List 3 important principles of measurement/management of this device
College Answer
a) List the indications for the use of this device in traumatic brain injury.
1. Intracranial pressure monitoring in patients with traumatic brain injury associated with an initial non-sedated Glasgow Coma Score > 8 prior to non-surgical resuscitation
a. AND an abnormal CT scan associated with trauma:
i. Diffuse axonal injury grade II – IV or ii. Mass lesions with midline shift > 5mm
b. AND in the following patients with a normal CT Scan
i. Age >40
ii. Lateralising signs
iii. Hypotension
iv. Significant extra-cranial trauma
b) List 3 important principles of measurement/management of this device
1. Attached flushed transducer to fluid-filled catheter – do not inject
2. Set transducer to reference level (EAM or aortic root)
3. Attach drainage manometer and set at 10-20 cm H2O at level of EAM.
4. Monitor ICP continuously with intermittent drainage (hourly) unless clinically
indicated, for which drainage may be increased in frequency or continuously.
5. Septic surveillance of CSF daily.
Discussion
Methods of intracranial pressure monitoring and indications for intracranial pressure monitoring are discussed elsewhere.
The modern indications for ICP monitoring come from the Brain Trauma Foundation (4th edition), which are simply "anyone with an abnormal CT and GCS 3-8 gets ICP monitoring".
The setup of the EVD, its waveforms, and various other tidbits all have their own chapter.
In short, the normal principles of ICP measurement are:
- Inserted into the lateral ventricle, about 2.5 centimetres left or right from the midline, 11cm posterior to the junction between the frontal bone and the nasal bones.
- The drain connects to the transducer via a three-way tap
- The connecting tubing is incompressible, and primed with saline
- The transducer is zeroed to atmospheric pressure at the level of the tragus.
- The height of the drain is set to a certain specified height (in cm) above the patients tragus; lets say, 15cm
- The ICP is measured continuously; drainage occurs hourly, or sporadically.
- Daily CSF samples are sent for protein, glucose, cell count, Gram stain and culture.
References
Chawla, Lakhmir S., et al. "Lack of equivalence between central and mixed venous oxygen saturation." CHEST Journal 126.6 (2004): 1891-1896.
Question 7.2 - 2008, Paper 2
7.2 The following assessment was made on the visual field testing of a patient who presented with impaired vision.

(The darkened halves of the fields indicate the area of impaired vision).
a) What does the visual field testing indicate?
b) List 3 likely anatomical sites of lesion which may result in this visual defect.
College Answer
a) What does the visual field testing indicate?
Rt. homonymous hemianopia
b) List 3 likely anatomical sites of lesion which may result in this visual defect.
Left optic tract
Left optic radiation
Left occipital lobe
Discussion
The localisation of visual field defects lends itself especially well to a massive insane-looking eyeball diagram, which I have put together many years ago in med school.
For detailed references, one can be directed to Chapter 116 by R.H Spector from Clinical Methods(1990), or "Topical diagnosis of chiasmal and retrochiasmal disorders" by Levin, from Walsh and Hoyt clinical neuro-ophthalmology, 6th ed.
Alternatively, one can explore this table cut-and-pasted from the Required Reading section (Visual fields and lesions of the visual pathways). As you can plainly see, one can put "tumour" down as a cause for pretty much any of these
Lesion |
Localisation |
Causes |
|
Big blind spot |
|
|
|
Tunnel vision |
|
|
|
Central scotoma |
|
|
|
Unilateral blindness |
|
|
|
Bitemporal hemianopia |
|
|
|
Homonymous hemianopia |
|
|
|
Richly vascularised; difficult to take out with one ischaemic stroke: anterior choroidal artery and lateral geniculate artery are both involved in blood supply.
|
|
|
|
|
|
|
|
|
Homonymous hemianopia with macular sparing |
|
|
|
Superior quadrantinopia |
|
|
|
Inferior quadrantinopia |
|
|
References
Levin, Leonard A. "Topical diagnosis of chiasmal and retrochiasmal disorders."Walsh and Hoyt clinical neuro-ophthalmology, 6th ed. Baltimore: Williams & Wilkins (2005): 503-573.
Robert H. Spector. "Visual Fields." (1990). Clinical Methods: The History, Physical, and Laboratory Examinations. 3rd edition.
Question 11.1 - 2008, Paper 2
A 27 year old male with a prolonged ICU stay following a subarachnoid
haemorrhage has a CSF specimen taken from his external ventricular drain.
The CSF gram stain result is:
|
Red Blood Cells |
1946 x 106/L |
(0-5 x 10⁶/L) |
|
Polymorphs |
198 x 106/L |
(0-5 x 10⁶/L) |
|
Mononuclear cells |
74 x 106/L |
Gram stain: scant gram positive cocci.
a). What is your assessment of the CSF result and provide a reason ?
b). List two likely organisms commonly reported on the Gram stain in this setting.
c). List 2 therapies you may consider based on this report .
College Answer
a). What is your assessment of the CSF result and provide a reason ?
Ventriculitis : due to raised WCC:RCC ratio and a positive gram stain
b). List two likely organisms commonly reported on the Gram stain in this setting.
Staphylococcus epidermidis
Staphylococcus aureus
c). List 2 therapies you may consider based on this report .
Removal of EVD / replacement
Vancomycin
Discussion
This patient has ventriculitis. The ratio of WCCs to RBCs is around 1:10, rather than 1:500-1500. Therefore, there is "CSF pleocytosis". The presence of monocytes is also much higher than would be expected purely from the presence of the EVD.
The gram positive cocci found in this CSF sample are likely tourist organisms from the skin, which took a ride into the brain on the back of the EVD. Likely, these are going to be either Staphylococcus aureus, Staphylococcus epidermidis or Streptococcus pyogenes.
The two things one should immediately consider is
1) Get the infected EVD out
2) Start some antibiotics, which in the context of unknown sensitivities should consist of cephalosomething and vancomycin.
The normal properties and contents of the CSF are discussed in detail elsewhere.
Meningitis is favoured with a chapter in Oh's Manual, and is also discussed elsewhere.
References
Beer, R., P. Lackner, and B. Pfausler. "Nosocomial ventriculitis and meningitis in neurocritical care patients." Journal of neurology 255.11 (2008): 1617-1624.
Question 11.3 - 2008, Paper 2
A 66yo diabetic female with a history of a recent febrile illness now presents with increasing weakness and altered sensation in both legs. A lumbar puncture is performed and the initial CSF result is shown.
|
Red blood cells |
594 x 106/L |
(0-5 x 10⁶/L) (0-5 x 10⁶/L) |
|
Mononuclear cells |
154 x 106/L |
|
|
Protein |
0.99g/L |
(0.15 – 0.40g/L) |
|
Glucose |
10.4 mmol/L |
(2.5-5.6 mmol/L) |
|
No organisms seen |
a). What is the most important diagnostic investigation indicated in this clinical scenario?
b). What is the most likely diagnosis?
College Answer
a). What is the most important diagnostic investigation indicated in this clinical scenario?
MRI of the spine
b). What is the most likely diagnosis?
Epidural abscess
Discussion
This elderly diabetic woman has a bilateral motor and sensory loss in her legs. The CSF looks infected; perhaps the glucose is raised, but this could be because the serum glucose is also raised, so I would not be deterred from a suspicion of epidural abscess by the presence of these findings.
The most important investigation in this context would be an MRI of the whole spine.
References
Reihsaus, E., H. Waldbaur, and W. Seeling. "Spinal epidural abscess: a meta-analysis of 915 patients." Neurosurgical review 23.4 (2000): 175-204.
Question 14 - 2008, Paper 2
List the possible causes of an altered swallowing reflex in a critically ill patient, and outline how you could assess this.
College Answer
Causes:
• Iatrogenic - Medications – chemotherapy, antihistaminics, neuroleptics. Trauma - TOE, intubation , tracheostomy
• Infectious - candidial mucositis. Metabolic – thyrotoxicosis, Cushing’s
• Myopathic – myasthenia gravis, connective tissue disorders, myotonic dystrophy
• Neurological – severe head injury, stroke, Guillain-Barre syndrome. Structural - Zenker's diverticulum, Oropharyngeal and oesophageal tumours.
Assessment:
• History – hoarseness, weak cough – vocal cord palsy, slurred speech, nasal regurgitation – neuromuscular. Odynophagia – infections , malignancy
• Clinical assessment – oral cavity –poor dentition, dry mouth. Neurological –
cranial nerves – V. VII, IX, X, XI, XII.
• Bedside assessment by speech therapist – coordination of swallowing, aspiration of dye (methylene blue).
• Nasopharyngeal laryngoscopy – visual inspection oropharynx, vocal cords for anatomical abnormality.
• Video fluoroscopy – accurately analyses aspiration, pooling of secretions and movements of muscles during swallowing.
• Barium swallow – identifies anatomical abnormalities – diverticuli, tumours, Upper GI endoscopy.
Discussion
Altered swallowing in an ICU patient could be the result of a number of aetiological processes. Not all of the belowmentioned processes are causing an "altered reflex" per se.
|
Vascular causes:
Infectious causes:
Neoplastic causes:
Drug-induced swallowing dyfunction:
Idiopathic miscellaneous causes:
|
Autoimmune causes
Traumatic causes:
Endocrine and metabolic causes:
|
Investigation of abnormal swallowing in ICU follows a familiar pattern:
- History (suggestive of stroke or malignancy)
- Examination (of whole body neurology, but focusing on the cranial nerves)
- Speech therapist assessment
- Nasendoscopy to observe the vocal cords directly
- Barium swallow
- CT of the neck
- A VFSS (videofluoroscopic swallowing study) is the gold standard.
References
de Larminat, Valentine, et al. "Alteration in swallowing reflex after extubation in intensive care unit patients." Critical care medicine 23.3 (1995): 486-490.
Macht, Madison, et al. "ICU-Acquired Swallowing Disorders." Critical care medicine 41.10 (2013): 2396-2405.
Question 9 - 2009, paper 1
What are the indications for decompressive craniectomy? Briefly outline the complications of decompressive craniectomy. Comment briefly on the outcome from decompressive craniectomy.
College Answer
Recognised indications
- Malignant MCA infarction
Indications for which there is anecdotal evidence:
- Refractory intracranial hypertension following TBI
- Cerebral swelling from vasospasm and SAH
- Hypertensive bleeds
- Encephalitis
- Cerebral venous thrombosis
Complications:
- Infection
- Collections –subgaleal and subdural collections usually on the ipsilateral side.
- Bleeding
- Brain herniation through the craniotomy
- Venous thrombosis secondary to herniation through the defect and occlusion of venous circulation.
- Sinking flap syndrome
- Paradoxical subtentorial herniation with LP or CSF drainage – due to atmospheric pressure – intracranial pressure gradient
- Hydrocephalus
- Bone flap resorption
- Worsening of brain injury
Outcome:
Long term data are lacking. Although hospital survival is improved in patients with refractory ICP in head injury and malignant infarction, quality of survival needs further evaluation. Age is important in patient selection and current recommendation for DCI in malignant MCA infarcts is <50 and considered on a case by case basis over 50. Paediatric data suggest better outcome in paediatric head injuries.
Discussion
Decompressive craniectomy in general, and within the specific context of a malignant MCA infarction, is discussed in great detail elsewhere:
- Decompressive craniectomy for traumatic brain injury
- Decompressive craniectomy for malignant MCA infarction
Additionally, LITFL have a nice summary page on this topic.
To simplify revision, a summary table is lazily pasted here.
Indications: |
Outcomes: |
Complications:
|
|
Traumatic brain injury |
|
|
|
Malignant MCA infarction syndrome |
|
|
|
Subarachnoid haemorrhage |
|
|
|
Intraparenchymal intracranial haemorrhage |
|
|
|
Dural sinus thrombosis |
|
|
|
Encephalitis |
|
|
|
Subdural haematoma |
|
In a nontabulated form, one might answer thus:
Indications for a decompressive craniectomy:
- Raised intracranial pressure due to
- Traumatic brain injury
- Severe intracranial haemorrhage with midline shift
- Malignant MCA infarction syndrome
- Subarachnoid haemorrhage
- Intraparenchymal intracranial haemorrhage
- Dural sinus thrombosis
- Encephalitis
- Subdural haematoma
Why is malignant MCA infarction a "recognised indication"? Well. Three European trials confirmed that mortality from massive MCA infarction is halved with craniectomy, and that is hard to argue with.
Complications of decompressive craniectomy:
- Brain hernation though the opening
- Delayed paradoxical herneation
- Subdural hygroma
- Infection
- Bleeding
- Post-traumatic hydrocephalus
- Syndrome of the Trephined, or "Sinking Flap Syndrome"
- Bone resorption
Outcome of decompressive craniectomy:
- MCA infarct patients: mortality improved by 50%
- Traumatic brain injury patients: mortality unchanged, but neurological outcome was worse in the craniectomized patients.
References
Cooper, D. James, et al. "Decompressive craniectomy in diffuse traumatic brain injury." New England Journal of Medicine 364.16 (2011): 1493-1502.
Vahedi, Katayoun, et al. "Sequential-design, multicenter, randomized, controlled trial of early decompressive craniectomy in malignant middle cerebral artery infarction (DECIMAL Trial)." Stroke 38.9 (2007): 2506-2517.
Hofmeijer, Jeannette, et al. "Surgical decompression for space-occupying cerebral infarction (the Hemicraniectomy After Middle Cerebral Artery infarction with Life-threatening Edema Trial [HAMLET]): a multicentre, open, randomised trial." The Lancet Neurology 8.4 (2009): 326-333.
Jüttler, Eric, et al. "Decompressive surgery for the treatment of malignant infarction of the middle cerebral artery (DESTINY) a randomized, controlled trial." Stroke 38.9 (2007): 2518-2525.
Lee, Kyeong Woo, et al. "Functional Outcomes of Patients with Severe MCA Infarction after Decompressive Craniectomy." Brain & Neurorehabilitation 7.1 (2014): 48-53.
Tuzgen, Saffet, et al. "Decompressive craniectomy in patients with cerebral infarction due to malignant vasospasm after aneurysmal subarachnoid hemorrhage." Journal of neurosciences in rural practice 3.3 (2012): 251.
Murthy, J. M. K., et al. "Decompressive craniectomy with clot evacuation in large hemispheric hypertensive intracerebral hemorrhage." Neurocritical care 2.3 (2005): 258-262.
Güresir, Erdem, et al. "Decompressive craniectomy in subarachnoid hemorrhage." Neurosurgical focus 26.6 (2009): E4.
Keller, E., et al. "Decompressive craniectomy in severe cerebral venous and dural sinus thrombosis." New Trends of Surgery for Stroke and its Perioperative Management. Springer Vienna, 2005. 177-183.
Schirmer, Clemens M., Daniel A. Hoit, and Adel M. Malek. "Decompressive hemicraniectomy for the treatment of intractable intracranial hypertension after aneurysmal subarachnoid hemorrhage." Stroke 38.3 (2007): 987-992.
Adamo, Matthew A., and Eric M. Deshaies. "Emergency decompressive craniectomy for fulminating infectious encephalitis." (2008). Journal of Neurosurgery January 2008 / Vol. 108 / No. 1 / Pages 174-176
Hutchinson, Peter, Ivan Timofeev, and Peter Kirkpatrick. "Surgery for brain edema." Neurosurgical focus 22.5 (2007): 1-9.
Margules, Andrew, and Jack Jallo. "Complications of decompressive craniectomy." JHN Journal 5.1 (2010): 4.
Question 16 - 2009, paper 1
What are the indications for intracranial pressure monitoring in traumatic brain injury? What are the limitations of intracranial pressure monitoring?
College Answer
All patients with severe head injury and moderate head injury whose progress can not be followed by serial neurological evaluation should be considered for ICP monitoring.
The Brain Trauma Foundation guidelines suggest ICP-monitoring should be considered in the following settings:
• Severe head injury (GCS 3-8) + abnormal CT scan
• Severe head injury (GCS 3-8) + normal CT scan if 2 of the following are presen):
o Age > 40
o BP < 90 mmHg
o Abnormal motor posturing
Individual intracranial pressure monitors have different limitations:
• Intraparenchymal monitors/subdural bolts: can not be calibrated, subject to “drift”, do not allow CSF drainage for control of ICP
• Require expertise and resource availability for placement
• Infection
No RCTs have demonstrated that ICP-guided therapy improves patient-centred outcomes.
Some observational studies have noted an association between ICP guided management and prolonged length of stay (Cramer, 2005) and worse outcome (Shafi, 2008).
Discussion
The indications listed in the college answer (including age, posturing etc) are from the old 3rd edition of the BTF guidelines. The enlightened 4th edition had reduced these recommendations to simply "anyone with an abnormal CT and GCS 3-8".
Limitations of intracranial pressure monitoring:
- No evidence that it impoves outcomes
- Monitors can become infected, inaccurate due to drift, or they can cause more intracranial bleeding.
- Neurosurgical expertise is required to insert these monitors
The college answer references papers by Cramer (2005) and Shafi (2008).
Presumably, they meant Olaf L. Cremer, who in 2005 was the first author of a retrospective cohort study which associated ICP-guided therapy with increased intensity of therapy and more prolonged mechanical ventilation, without a benefit to either survival or functional outcome. The examiners also mention Shahid Shafi's 2008 analysis of The National Trauma Data Bank (1994–2001) which found that ICP monitoring was associated with a 45% reduction in survival.
Greated detail is afforded by the summary of indications for intracranial pressure monitoring andmethods of intracranial pressure monitoring in the Required Reading section; to simplify revision the relevant grey boxes have been reproduced below.
|
(Recommendations of The Brain Trauma Foundation, 4th edition)
|
EVD |
Codman Microsensor |
|
Gold standard of ICP monitoring |
|
|
Pressure is transmitted to a Wheatsone bridge transducer via fluid-filled non-compressible tubing |
Piesoelectric strain gauge pressure sensor is intracranial; connected to the monitor via fiberoptic cable |
|
Requires a certain expertise to place correctly. |
Requires less expertise to place (however, this should still be done by somebody with neurosurgical experience) |
|
More traumatic owing to depth of insertion and diameter of catheter |
Less traumatic, because the catheter placement is not as deep, and the catheter tip is finer. The Codmans typically sits about 2cm below the cerebral surface. |
|
CSF can be drained though the EVD |
CSF cannot be drained or sampled |
|
The catheter can become blocked by clots or debris |
The catheter cannot block |
|
Measures intraventricular pressure, |
Measures local parenchymal pressure |
|
Can be re-zeroed to atmorpsheric pressure |
Cannot be re-zeroed after insertion; |
|
Insertion is impossible if the ventricles are collapsed |
Does not rely on venticular placement, and thus is the only option in a patient with small collapsed ventricles |
|
Dangerous in coagulopathy. Even when non-coagulopathic, the risk of haemorrhagic complications is around 5-7% on average |
Coagulopathy is only a relative contraindication; hemorrhagic complications are infrequent. One study puts the rate of bleeding at 1.1%. |
|
Places the patient at risk of ventriculitis after 5 days. Bacterial colonisation rates range up to 27%, but studies vary in their definition of what a clinically significant infection actually is. |
Less likely to become infected; highly unlikely to cause ventriculitis, as it does not communicate with the entricles. |
|
Cheap |
Expensive |
References
Chapter 43 (pp. 563) Cerebral protection by Victoria Heaviside and Michelle Hayes, and
Chapter 67 (pp. 765) Severe head injury by John A Myburgh.
Brain Trauma Organisation Guidelines for Management Traumatic Brain Injury.
Narayan, Raj K., et al. "Intracranial pressure: to monitor or not to monitor? A review of our experience with severe head injury." Journal of neurosurgery 56.5 (1982): 650-659.
Forsyth, Rob J., Susanne Wolny, and Beryl Rodrigues. "Routine intracranial pressure monitoring in acute coma." Cochrane Database Syst Rev 2 (2010).
Meythaler, Jay M., et al. "Current concepts: Diffuse axonal injury - associated traumatic brain injury." Archives of physical medicine and rehabilitation 82.10 (2001): 1461-1471.
Tasker, R. C., et al. "Monitoring in non-traumatic coma. Part I: Invasive intracranial measurements." Archives of disease in childhood 63.8 (1988): 888-894.
Cremer, Olaf L., et al. "Effect of intracranial pressure monitoring and targeted intensive care on functional outcome after severe head injury*." Critical care medicine 33.10 (2005): 2207-2213.
Shafi, Shahid, et al. "Intracranial pressure monitoring in brain-injured patients is associated with worsening of survival." Journal of Trauma and Acute Care Surgery 64.2 (2008): 335-340.
Lane, Peter L., et al. "Intracranial pressure monitoring and outcomes after traumatic brain injury." Canadian Journal of Surgery 43.6 (2000): 442.
Question 24.4 - 2009, paper 1
A patient was noted to have a persistent tonic conjugate deviation of the eyes to the right. List 2 likely causes.
College Answer
° Irritative lesion of the left frontal lobe
° Paralytic lesion of the right frontal lobe
° Rt. Pontine lesion
Discussion
The college sure do love the disorders of conjugate gaze.
A right-sided lesion in Brodmann's Area 8 (right prefrontal cortex) tends to produce a tonic deviation towards the lesion. I suppose a stroke can be described as a "paralytic" lesion, although decribing stroke as "paralytic" or "apoplectic" has gone out of fashion since definitions of stroke underwent some revisions in the mid-1950s.
Alternatively, epilepsy can cause a tonic deviation of the eyes (and head), in which case the eyes will deviate away from the clearly lateralised seziure focus. I suppose, by this odd nomenclature, one could describe a clearly lateralised focus of epilepsy as an "irritative lesion".
A pontine lesion causes an interruption of ipsilateral gaze motor control, resulting in a deviation of the eyes away from the lesion, towards the intact pons and towards the hemiparetic side of the patient. Thus, a right gaze deviation could never be caused by a right pontine infarct. In this, the college answer is probably wrong.
The non-tonic version of this finding is called Prévost's sign, and is associated with hemineglect (the eyes merely "trend" towards one side).
In general, the chapter on Examination of eye movements contains some relevant persistent eye deviation syndromes and their associated observation findings whereas the chapter on Disorders of conjugate gaze deals more with findings on active oculomotor examination.
References
Berger, M. Fruhmann, et al. "Deviation of eyes and head in acute cerebral stroke." BMC neurology 6.1 (2006): 23.
Kernan, J. C., et al. "Lateralizing significance of head and eye deviation in secondary generalized tonic‐clonic seizures." Neurology 43.7 (1993): 1308-1308.
Bassetti, Claudio, et al. "Isolated infarcts of the pons." Neurology 46.1 (1996): 165-175.
Question 24.5 - 2009, paper 1
List 4 causes of neck stiffness
College Answer
° Meningitis/encephalitis
° Subarachnoid hemorrhage
° Post fossa syndrome
° Tetanus
° Cervical spondylitis
° Neck abscess
° Wry neck / Torticollis
Discussion
To this predictable list, I could also add
- dural sinus thrombosis
- epidural abscess
- cervical facet joint arthritis
- "whiplash" - musculoskeletal hyperextension injury
And many others. One can go right to town on this. Consider a cause for neck stiffness from any of the major pathological categories, and I guarantee you will find one.
Observe:
Vascular:
- Dural sinus thrombosis
- Subarachnoid hemorrhage
Infectious:
- Epidural abscess
- Neck abscess
- Meningitis/encephalitis
- Tetanus
Neoplastic:
- C-spine vertebral metastasis or primary
Drug-related:
- Dystonic reaction
- Withdrawal
Idiopathic/inflammatory:
- Osteoarthritis
- Cervical spondylitis
- Torticollis
Autoimmune:
- Rheumatoid arthritis
- Ankylosing spondylitis
Traumatic
- Whiplash
- C-spine dislocation, subluxation or fracture
- Prolonged neck hyperextension during surgery (eg. tracheostomy)
Endocrine:
- Hypocalcemia
References
Question 1 - 2009, Paper 2
Define cerebral perfusion pressure (CPP). List the advantages and limitations of using CPP as a therapeutic target in the management of traumatic brain injury
College Answer
Definiton : CPP = MAP-ICP
- Advantages:
- Easily monitored
- Can be monitored continuously
- Nursing staff familiar
- BTF guidelines endorse use of CPP at 60
Limitations:
- Used as a surrogate for CBF.CVR is variable and therefore changes in CBF not detected by CPP
- Does not allow for differential autoregulation in the normal and injured brain.
- Therapy to maintain CPP can result in lung injury
- No Class I data to support use
- Poor correlation between CPP and indices of brain oxygenation
Discussion
The general topic of cerebral bloodflow autoregulation is discussed elsewhere.
More specific information regarding using CPP as a therapeutic target in traumatic brain injury is explored in the Required Reading section.
In brief:
Category |
Advantages |
Limitations |
Physiology |
|
|
Pragmatism |
|
|
Support |
|
|
Evidence |
|
|
Cerebral perfusion pressure is the driving pressure gradient which produces flow in the cerebral circulation against the resistance of cerebral vessels. Thus, it is the difference in mean cereberal arterial pressure and the mean cereral venous pressure. Because we can hardly measure the latter and we only guess at the former, a useful approximation is to subtract intracranial pressure (ICP) from the mean systemic arterial pressure (MAP). Thus, CPP = (MAP - ICP).
There are some advantages of using CPP as a treatment target in traumatic brain injury. The brain-injured patient is unable to autoregulate their cerebral blood flow, and thus they rely on you to make sure that their cerebral arterial pressure remains reasonably high. Its easy enough to monitor it continuously if you have both an arterial line and an ICP monitor.
However, it is not a measure of cerebral blood flow. Flow is a very different property; cerebral blood flow is a function of both the pressure gradient and the resistance. Cerebral vascular resistance might change randomly and regionally, all without any change in systemic MAP. Not only that, but "flow" alone does not determine cereberal oxygenation - there are even more factors involved in this, such as the oxygen carrying capacity of red cells, the viscosity of the blood, etc etc...
In short, as has been demonstrated experimentally, CPP does not correlate well with brain tissue oxygenation.
Furthermore, targeting a CPP tends to ignore the fact that no brain is uniformly injured, and that there are regions which are still able to autoregulate their bloodflow. In one's desperate bid to protect the brain, one may inadvertantly flood the patient with fluid and cause pulmonary oedema, or exacerbate existing neurogenic pulmonary oedema.
Lastly, the college makes a statement regarding there being no Class I evidence to suport the use of CPP-guided blood pressure management in traumatic brain injury. True, but the entire set of BTF guidelines only has one single piece of Class I evidence, which is "don't you ever use steroids". Thus, one cannot single out the CPP guidelines as somehow "baseless" on the grounds that no investigator has thus far dared to randomise a group of brain-injured patients to an experimental group in whom the CPP is totally unmanaged.
References
Chapter 52 (pp. 580) Cerebral protection by Victoria Heaviside and Michelle Hayes
Harper, A. MURRAY. "Autoregulation of cerebral blood flow: influence of the arterial blood pressure on the blood flow through the cerebral cortex." Journal of neurology, neurosurgery, and psychiatry 29.5 (1966): 398.
Phillips, Stephen J., and Jack P. Whisnant. "Hypertension and the brain."Archives of internal medicine 152.5 (1992): 938-945.
Paulson, O. B., S. Strandgaard, and L. Edvinsson. "Cerebral autoregulation." Cerebrovascular and brain metabolism reviews 2.2 (1989): 161-192.
Busija, David W., and Donald D. Heistad. Factors involved in the physiological regulation of the cerebral circulation. Springer Berlin Heidelberg, 1984.
Eriksson, Evert A., et al. "Cerebral perfusion pressure and intracranial pressure are not surrogates for brain tissue oxygenation in traumatic brain injury."Clinical Neurophysiology 123.6 (2012): 1255-1260.
Question 11 - 2009, Paper 2
You are asked to assess a 54 year old man scheduled for an urgent laparotomy for a suspected perforated duodenal ulcer. He has recently developed symptoms of double vision, ptosis, dysarthria and generalised muscle weakness. He was due to be reviewed by a neurologist next week. The anaesthetist asks for a post-op bed in ICU. The patient has a 25-pack year history of smoking but ceased smoking 3 months ago.
11.1 What are your differential diagnoses for his weakness?
11.2 The above patient is admitted to ICU post-op. A perforated DU was oversewn in theatre.
a) What are the essential pieces of information you would expect from the anaesthetist at handover upon the patient’s admission to ICU?
11.3 What investigations could help you establish the diagnosis for his weakness?
College Answer
11.1 What are your differential diagnoses for his weakness?
- Gullian-Barre syndrome
- Myasthenia gravis
- Motor neurone disease
- Paraneoplastic syndrome – Eaton Lambert
- (Myotonic dystrophy)
- Periodic paralysis
- Botulism
- (Endocrine & metabolic myopathies)
- (Drug induced myopathies)
11.2 The above patient is admitted to ICU post-op. A perforated DU was oversewn in theatre.
a) What are the essential pieces of information you would expect from the anaesthetist at handover upon the patient’s admission to ICU?
Specific:
GA drugs used – esp muscle relaxants; muscle relaxation in response to sux (if used)
Findings on nerve stimulator NMJ monitoring
Reasons extubation could not be attempted
General:
Operative findings
Haemodynamic stability
Antibiotics used
11.3 What investigations could help you establish the diagnosis for his weakness?
- Edrophonium or neostigmine test (with atropine cover)
- ACh receptor Abs
- EMG NCS – Muscle biopsy
- LP – CSF protein
- Neurological review
Discussion
The fist part of the question is a straightforward differential-generating exercise. What are the causes of subacute-onset weakness in a smoker? Guillain-Barre, myasthenia gravis and motor neuron disease are reasonable guesses which apply everywhere. Particularly, diplopia would make one think of myasthenia gravis. The Lambert-Eaton (or Eaton-Lambert) Myasthenic Syndrome is a special one, which relates partiocularly to people with neoplasms (it is a paraneoplastic syndrome of autoantibody secretion, resulting in the destruction of voltage-gated calcium channels). Botulism is thrown in for some reason. Periodic paralysis is also mentioned, even though it is an insanely rate genetic disorder. Drug-induced myopathies are more common, but are mentioned last.
What would you want to know from the anaesthetist?
Well; for one, you would like to know whether they used any muscle relaxant, and if yes- then how much, what kind, and when. One would also be interested in the nerve stimulator test. The administration of gentamicin may potentiate NMJ disturbances and it would be good to know whether one should expect something like this.
As for investigations... A panel of standard tests would include the following:
- Electrolyte levels
- CK level
- B12 level
- Acetylcholine receptor antibodies (for myasthenia gravis)
- CXR looking for malignancy (as support for a diagnosis of Eaton-Lambert syndrome)
- Inflammatory markers
- Lumbar puncture
- Nerve conduction studies
- Electromyography
- MRI of the brainstem and spine
- Muscle biopsy if no satisfactory explanation is found.
It is worth noting that the college is not too proud to seek a neurology consult when confronted by this sort of problem.
Approach to the ICU patient with generalised weakness is discussed elsewhere.
References
Oh's Intensive Care manual: Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Jani, Charu. "Critical Illness Neuropathy." Medicine (2011): 237.
Young, G. Bryan, and Robert R. Hammond. "A stronger approach to weakness in the intensive care unit." Critical care 8.6 (2004): 416.
Mareska, Michael, and Laurie Gutmann. "Lambert-Eaton myasthenic syndrome." Seminars in neurology. Vol. 24. No. 2. [New York]: Thieme-Stratton Inc.,[c1981-, 2004.
Engel, Andrew G., ed. Myasthenia gravis and myasthenic disorders. Oxford University Press, 2012.
Question 12.4 - 2009, Paper 2
List 4 clinical signs, (not involving the limbs) of cerebellar dysfunction.
College Answer
1. Nystagmus
2. Titubation (head bobbing)
3. Truncal ataxia
4. Staccato speech
5. Dysarthria
6. Hypotonia
7. Kinetic tremor
Discussion
This is cheating, because kinetic tremor and hypotonia are difficult to test without involving the limbs.
Walker, in the below-linked book chapter, identifies the following signs:
- Titubation
- Resting tremor of the trunk
- Trunkal ataxia
- Nystagmus
- Ocular dysmetria (the eyes overshooting the target of their gaze)
- Impaired smooth tracking of gaze
- Stacatto speech
- Dysarthria (ataxia of speech)
References
Walker, Henry Kenneth, Wilbur Dallas Hall, and John Willis Hurst. Clinical Methods: The History, Physical, and Laboratory Examinations. Chapter 69, by Kenneth Walker. Butterworths, 1990.
Question 25.1 - 2009, Paper 2
An 82 year old woman presents with fever, seizures and a history of anorexia, diarrhoea and vomiting.
List three (3) clinical features which would indicate the need for a brain CT scan prior to lumbar puncture in this patient?
College Answer
1. New onset seizures
2. Immunocompromised state
3. Moderate to severe impaired level of consciousness
4. Focal neurological signs (signs suspicious of a space occupying lesion)
Discussion
The question is really asking, "what are the features of increased intracranial pressure in the presence of a space-occupying lesion?"
- Hypertension and bradycardia
- Focal neurological signs
- Decreased level of consciousness
- No previous history of epilepsy
- Predisposition to infection (eg. immunocompromised state)
- Papilloedema
- History of stroke or intracranial space-occupying lesion
Clinical features of increased intracranial pressure, specifically referring to patients with meningitis, are discussed elsewehere. The References section below contains a single article on this topic, well worth reading. The most important feature of it - Tabel 2 - is reproduced below to simplify revision.
Immunocompromised host |
|
History of focal CNS disease |
|
New onset of seizures |
|
Ongoing or recent seizures |
(Seizures in general seem to cause an increase in intracranial pressure, in the absence of a space-occupying lesion, and with a deceptively normal head CT.) |
Papilloedema |
|
Decreased level of consciousness |
|
Focal neurological signs |
|
References
Tunkel, Allan R., et al. "Practice guidelines for the management of bacterial meningitis." Clinical infectious diseases 39.9 (2004): 1267-1284.
Question 29 - 2009, Paper 2
29.1 Define delirium.
29.2 What is the prevalence of delirium in the critically ill?
29.3 What is its prognostic significance?
29.4 Briefly outline how you will manage delirium in the critically ill patient.
College Answer
29.1 Define delirium.
A disturbance of consciousness with inattention accompanied by a change in cognition or perceptual disturbance that develops over a short period of time and fluctuates over time. DSM4. Inattention is one of the hallmarks and pivotal features of delirium.
29.2 What is the prevalence of delirium in the critically ill?
Reported as being greater that 8 out of 10 (An answer suggesting that it is highly prevalent should get some credit.
29.3 What is its prognostic significance?
The presence of delirium has been assoc with increased mortality, prolonged ICU and hospital stay, greater dependency on community services and care on discharge and higher nursing home placement rates.
29.4 Briefly outline how you will manage delirium in the critically ill patient.
Treatment of Delirium (marks) – Early recognition
Identify etiology (metabolic, infective, drugs, drug withdrawal,alcohol etc) and treat this
Non Pharmacologic treatment i.e. recurrent orientation of patients, early mobilization, early removal of catheters etc
Pharmacologic-
Benzodiazepines Thiamine Haloperidol
decrease analgesics sedatives and anticholinergic drugs. NOTE there are NO FDA drugs approved for the treatment of delirium.
Discussion
Delirium is discussed in greater detail elsewhere ("Delirium in the ICU").
It is also covered in some depth in the answer to Question 6 from the second paper of 2013, "Define delirium and describe your management approach to this problem in the ICU. "
However, prevalence and prognostic significance are not discussed in the 2013 paper.
Thus:
Prevalence of delirium in the ICU
"An answer suggesting that it is highly prevalent should get some credit." Indeed, recent publicationsquote a figure of 32-77%.
Prognostic significance of delirium in the ICU
The 2004 Ely prospective cohort study gets brought out whenever anybody talks about the prognostic significance of delirium in the ICU. There are many others. In summary, their findings were as follows:
- Mortality at 6 months: increases × 3.2
- Length of hospital stay doubles
- Every additional day of delirium increases the hazard of deatha t 1 year by about 10%.
- Increased risk of cognitive impairment in the long term (in ~ 70%)
References
Cavallazzi, Rodrigo, Mohamed Saad, and Paul E. Marik. "Delirium in the ICU: an overview." Ann Intensive Care 2.1 (2012): 49.
Ely, E. Wesley, et al. "Delirium as a predictor of mortality in mechanically ventilated patients in the intensive care unit." Jama 291.14 (2004): 1753-1762.
Question 3.1 - 2010, Paper 1
What are the distinguishing features on clinical examination between a neuropathy and a myopathy?
College Answer
|
Neuropathy |
Myopathy |
|
|
Site of weakness |
Distal weakness |
Usually proximal |
|
Sensory |
May have concomitant sensory symptoms and signs |
Usually pure motor |
|
Reflexes |
Reflexes lost early |
Reflexes preserved till late |
|
Fasciculations |
Fasciculations may be |
Not typical |
|
Contractures |
Contractures not a |
Contractures present |
|
Myocardial dysfunction |
Not a typical feature |
May have |
Discussion
This question closely resembles Question 14.1 from the first paper of 2013.
This college answer is slightly different, and better organised.
References
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
UpToDate: An approach to the patient with muscle weakness
Young, G. Bryan, and Robert R. Hammond. "A stronger approach to weakness in the intensive care unit." Critical care 8.6 (2004): 416.
Question 8 - 2010, Paper 1
Compare and contrast the intraventricular catheter and the intra-parenchymal fibre- optic transducer for intracranial pressure monitoring in critically ill patients.
You may tabulate your answer.
College Answer
|
Intraventricular catheters |
Intra – parenchymal devices |
|
Gold standard for ICP monitoring |
Not a gold standard though fairly accurate |
|
Catheters are Surgically placed into the |
Thin cable with an electronic fibre-optic |
|
Can be rezeroed (re-calibrated)after |
Not possible to re-calibrate after insertion |
|
Accurate provided catheter patent |
Drift leading to inaccuracy particularly after 5 to 7 days |
|
Can drain CSF to treat raised ICP |
No ability to drain CSF |
|
Ventriculitis - a serious life threatening |
Lower risk of Infection |
|
Blocked Catheter and intra-cerebral or intra-ventricular haemorrhage other complications. |
Solid state systems. Less chance of haemorrhage. |
|
Requires special expertise for insertion |
Easier to place |
|
Difficult to insert in patients with collapsed ventricles due to severe cerebral oedema |
Can be inserted in these patients easily |
|
Other indication – Subarachnoid |
Other indications ( controversial) – |
|
Coagulopathy – absolute contraindication |
Coagulopathy – relative contraindication |
|
Cheap |
Expensive |
Discussion
The college table is fairly comprehensive. One cannot add very much to this list of advantages and disadvantages.
A discussion of EVDs and the indications/contraindications of ICP monitoring can be found here:
- Methods of intracranial pressure monitoring
- Indications for intracranial pressure monitoring
- Interpretation of intracranial pressure waveforms
- Correlation of ICP waveforms with intracranial pathology
Specifically, methods of ICP monitoring are discussed, and a table similar to the above is constructed on the basis of published data. This table is reproduced below:
| EVD | Codman Microsensor |
| Gold standard of ICP monitoring | Similar accuracy to EVD |
| Pressure is transmitted to a Wheatsone bridge transducer via fluid-filled non-compressible tubing | Piesoelectric strain gauge pressure sensor is intracranial; connected to the monitor via fiberoptic cable |
| Requires a certain expertise to place correctly. About 12% areplaced into an inappropriate position. | Requires less expertise to place (however, this should still be done by somebody with neurosurgical experience) |
| More traumatic owing to depth of insertion and diameter of catheter | Less traumatic, because the catheter placement is not as deep, and the catheter tip is finer. The Codmans typically sits about 2cm below the cerebral surface. |
| CSF can be drained though the EVD | CSF cannot be drained or sampled |
| The catheter can become blocked by clots or debris | The catheter cannot block |
| Measures intraventricular pressure, which is thought to be representative of the pressure within the intracranial CSF | Measures local parenchymal pressure |
| Can be re-zeroed to atmorpsheric pressure | Cannot be re-zeroed after insertion; calibration tends to drift after 72 hours |
| Insertion is impossible if the ventricles are collapsed | Does not rely on venticular placement, and thus is the only option in a patient with small collapsed ventricles |
| Dangerous in coagulopathy. Even when non-coagulopathic, the risk of haemorrhagic complications is around 5-7% on average | Coagulopathy is only a relative contraindication; hemorrhagic complications are infrequent. One study puts the rate of bleeding at 1.1%. |
| Places the patient at risk of ventriculitis after 5 days. Bacterial colonisation rates range up to 27%, but studies vary in their definition of what a clinically significant infection actually is. | Less likely to become infected; highly unlikely to cause ventriculitis, as it does not communicate with the entricles. One study puts the infection rate at 0.6%. |
| Cheap | Expensive |
References
Brean, A., P. K. Eide, and Audun Stubhaug. "Comparison of intracranial pressure measured simultaneously within the brain parenchyma and cerebral ventricles." Journal of clinical monitoring and computing 20.6 (2006): 411-414.
Raboel, P. H., et al. "Intracranial pressure monitoring: invasive versus non-invasive methods—a review." Critical care research and practice 2012 (2012).
Lozier, Alan P., et al. "Ventriculostomy-related infections: a critical review of the literature." Neurosurgery 51.1 (2002): 170-182.
Saladino, Andrea, et al. "Malplacement of ventricular catheters by neurosurgeons: a single institution experience." Neurocritical care 10.2 (2009): 248-252.
Bekar, A., et al. "Risk factors and complications of intracranial pressure monitoring with a fiberoptic device." Journal of Clinical Neuroscience 16.2 (2009): 236-240.
Khan, S. H., et al. "Comparison of percutaneous ventriculostomies and intraparenchymal monitor: a retrospective evaluation of 156 patients."Intracranial Pressure and Neuromonitoring in Brain Injury. Springer Vienna, 1998. 50-52.
Question 27 - 2010, Paper 1
A 26 year old lady presents from home confused with a low-grade fever. Her blood pressure is 160/100 mm Hg. She has no gross motor deficits. Ten days ago she had an emergency termination of pregnancy for an intrauterine death that was complicated by disseminated intravascular coagulation. She was 32 weeks gestation and had been on labetalol for a pregnancy-induced hypertension.
Her discharge medications included paracetamol, tramadol and a selective serotonin reuptake inhibitor. She has a 6-year history of uncomplicated Hepatitis C.
27.1. List the differential diagnoses for her confusion and temperature.
27.2. Outline your approach to establishing the diagnosis.
College Answer
27.1. List the differential diagnoses for her confusion and temperature.
Pregnancy related: Eclampsia / preeclampsia / HELLP, Retained products with sepsis, Sheehan’s syndrome / pituitary apoplexy, Posterior reversible encephalopathy syndrome (PRES), Hypertensive encephalopathy
Primary neurological: Infection (meningitis / encephalitis), cerebral venous thrombosis, seizure disorder, other cerebro-vascular
Metabolic: Sodium (hypo/hyper), Glucose (hypo/hyper), Renal failure, Liver failure (HCV / Paracetamol / Antidepressants),
Drugs: Accidental / intentional overdose, drug reactions (serotonin syndrome) Infection: Uterine, intracranial, other (renal, chest etc)
27.2. Outline your approach to establishing the diagnosis.
History: Collateral, Pregnancy issues, Ongoing blood loss, bleeding / bruising, drug ingestions, mood / affect, headaches
Examination: BP, uterine size / discharge, oedema, meningism, neurological (tone, reflexes, symmetry), chronic liver disease
Investigations:
FBC: Bleeding, platelets, WCC
UEC: urea / creatinine, Na, Ca, glucose
Coagulation: DIC, INR for CLD
LFT / Ammonia: hepatic encephalopathy, drug reactions
ABG: hypoxia / hypercarbia
Urinary drug screen / paracetamol level
Sepsis Screen, CT head +/- LP
Discussion
The college have presented a high quality systematic answer.
One can generate no better differentials for this decreased level of consciousness. They even included cerebral venous thrombosis.
The history is rich in possibilities.
Vascular causes:
- cerebral venous thrombosis
- PRES
- Hypertensive encephalopathy
Infectious causes
- Sepsis due to retained products
- Meningitis / encephalitis
Neurological causes
- Seizures (potentiated by tramadol)
- Serotonin syndrome
Drug related
- Intoxication
Autoimmune
- Cerebral vasculitis
Traumatic
- Head injury
Endocrine/metabolic/electrolyte related
- Hyponatremia
- Hypoglycaemia
- Hepatic encephalopathy (HELLP)
- Uremia
A genric approach to the unconscious patient in the ICU is available locally.
References
Question 3.1 - 2010, Paper 2
A 20 year old female in ICU following a diffuse axonal head injury develops a severe exacerbation of intracranial hypertension on day 3. She is mechanically ventilated, paralysed and sedated. Investigations during a subsequent episode of marked polyuria are summarised below.
|
Test |
Value |
Normal Range |
|
pH* |
7.50 |
(7.36 –7.44) |
|
PaCO2* |
28 mm Hg |
(36 – 44) |
|
HCO3-* |
21 mmol/L |
(23 – 26) |
|
Standard base excess |
-1.5 mmol/L |
(-2 .0 to +2.0) |
|
Sodium* |
147 mmol/L |
(135 – 145) |
|
Potassium |
3.2 mmol/L |
(3.2 – 4.5) |
|
Chloride |
110 mmol/L |
(100 –110) |
|
Urea |
3.0 mmol/L |
(3.0 – 8.0) |
|
Creatinine |
65 mmol/L |
(50 – 100) |
|
Glucose |
4.0 mmol/L |
(3.0 – 6.0) |
|
Measured plasma osmolality* |
333 mosmol/kg |
(280 –290) |
|
Urine osmolality |
410 mosmol/L |
(50– 1200) |
a) What is the most likely explanation for the polyuria? Give the reasoning behind your answer.
College Answer
a) What is the most likely explanation for the polyuria? Give the reasoning behind your answer.
Mannitol therapy
There is increased measured plasma osmolality with an elevated osmolar gap. The gap is 44 mosmol/kg, if we use a calculated osmolality of 1.86 × ([Na] + [K]) + [urea]
+ [glucose]. If we use the simple formula of 2 × [Na] + [urea] + [glucose] for
calculated osmolality, the gap is 32 mosmol/kg. (There are also other formulae which are more difficult to remember). In the setting of treatment for an exacerbation of intracranial hypertension, the increased osmolar gap is likely to be due to mannitol administration. The high urinary osmolality rules out diabetes insipidus, and supports the diagnosis of mannitol induced polyuria
Discussion
This question is identical to Question 22.1 from the second paper of 2011, and Question 3 from the second paper of 2007 (which contains an answer with a more complete interpretation of this issue).
References
Question 3.2 - 2010, Paper 2
(Both this question and Question 3.1 use the same flavour text:)
A 20 year old female in ICU following a diffuse axonal head injury develops a severe exacerbation of intracranial hypertension on day 3. She is mechanically ventilated, paralysed and sedated. Investigations during a subsequent episode of marked polyuria are summarised below.
|
Test |
Value |
Normal Range |
|
pH* |
7.50 |
(7.36 –7.44) |
|
PaCO2* |
28 mm Hg |
(36 – 44) |
|
HCO3-* |
21 mmol/L |
(23 – 26) |
|
Standard base excess |
-1.5 mmol/L |
(-2 .0 to +2.0) |
|
Sodium* |
147 mmol/L |
(135 – 145) |
|
Potassium |
3.2 mmol/L |
(3.2 – 4.5) |
|
Chloride |
110 mmol/L |
(100 –110) |
|
Urea |
3.0 mmol/L |
(3.0 – 8.0) |
|
Creatinine |
65 mmol/L |
(50 – 100) |
|
Glucose |
4.0 mmol/L |
(3.0 – 6.0) |
|
Measured plasma osmolality* |
333 mosmol/kg |
(280 –290) |
|
Urine osmolality |
410 mosmol/L |
(50– 1200) |
a) What is the most likely explanation for the polyuria? Give the reasoning behind your answer (this is answered as Question 3.1 in this paper)
b) List the major determinants of prognosis in traumatic brain injury.
College Answer
b) List the major determinants of prognosis in traumatic brain injury.
Prognostic determinants:
• Age > 60
• Pupillary abnormalities
• Presence of hypotension and hypoxia
• Low GCS on presentation
• CT scan abnormalities – intracranial collections, presence of traumatic subarachnoid haemorrhage
• Co-morbidities
Discussion
Part a) of this question (Question 3.1) was a more electrolyte-based question: "What is the most likely explanation for the polyuria? Give the reasoning behind your answer."
The answer to the question about prognosis of traumatic brain injury can be found in the Brain Trauma Foundation's document on the Early Indicators of Prognosis in Severe Traumatic Brain Injury .
- Age > 60 (poor outcome risk increases by 20-30%)
- Pupillary abnormalities (70-90% mortality with bilaterally absent light reflex)
- Presence of hypotension (doubles mortality)
- Presence of hypoxia (doubles the likelihood of a poor neurological outcome)
- Low GCS on presentation (65% mortality if the GCS is 3)
- CT scan abnormalities (absence of abnormalities equates to a better prognosis)
- Co-morbidities
This is discussed in greater detail in "Prognosis in severe brain injury" from the Required Reading section.
References
Chesnut, R. M., et al. "Part 2: Early indicators of prognosis in severe traumatic brain injury." Journal of Neurotrauma 17.6-7 (2000): 555-+.
Fearnside, Michael R., et al. "The Westmead Head Injury Project outcome in severe head injury. A comparative analysis of pre-hospital, clinical and CT variables." British journal of neurosurgery 7.3 (1993): 267-279.
Oddo, Mauro, et al. "Brain hypoxia is associated with short-term outcome after severe traumatic brain injury independently of intracranial hypertension and low cerebral perfusion pressure." Neurosurgery 69.5 (2011): 1037-1045.
McHugh, Gillian S., et al. "Prognostic value of secondary insults in traumatic brain injury: results from the IMPACT study." Journal of neurotrauma 24.2 (2007): 287-293.
Collaborators, MRC CRASH Trial, et al. "Predicting outcome after traumatic brain injury: practical prognostic models based on large cohort of international patients." bmj 336.7641 (2008): 425-9.
Stevens, Robert D., and Raoul Sutter. "Prognosis in severe brain injury." Critical care medicine 41.4 (2013): 1104-1123.
Steyerberg, Ewout W., et al. "Predicting outcome after traumatic brain injury: development and international validation of prognostic scores based on admission characteristics." PLoS medicine 5.8 (2008): e165.
Lingsma, Hester F., et al. "Early prognosis in traumatic brain injury: from prophecies to predictions." The Lancet Neurology 9.5 (2010): 543-554.
Utomo, Wesley K., et al. "Predictors of in-hospital mortality and 6-month functional outcomes in older adults after moderate to severe traumatic brain injury." Injury 40.9 (2009): 973-977.
Holcomb, Erin M., Scott R. Millis, and Robin A. Hanks. "Comorbid Disease in Persons With Traumatic Brain Injury: Descriptive Findings Using the Modified Cumulative Illness Rating Scale." Archives of physical medicine and rehabilitation 93.8 (2012): 1338-1342.
Question 5.2 - 2010, Paper 2
List 4 clinical signs of intracranial hypertension.
College Answer
List 4 clinical signs of intracranial hypertension.
• Unilateral or bilateral papilledema
• Unilateral or bilateral papillary dilatation
• Impaired conscious state
• Bradycardia
Discussion
Little can be added to this answer.
In the section on the methods of monitoring intracranial pressure, one can find this table:
|
These are the clinical features of increasing intracranial pressure: |
|
Cardinal features:
|
Associated features:
|
There, one can also find extensive digressions on the advantages and disadvantages of using these clinical signs instead of waveform-generating piezoelectric devices.
However, the college did not ask for that.
References
Question 19 - 2011, Paper 1
With regard to the EEG:
a) List three indications for the use of the EEG in a critically ill patient
b) What are the clinical implications of non-convulsive status epilepticus (NCSE) in the critically ill patient?
c) List two EEG patterns that may be seen after hypoxic brain injury thought to be associated with a poor prognosis.
College Answer
With regard to the EEG:
a) List three indications for the use of the EEG in a critically ill patient
• Detection of non convulsive seizures and characterization of spells in patients with altered mental status with: (A history of epilepsy, Fluctuating level of consciousness, Acute brain injury, Recent convulsive status epilepticus, Stereotyped activity such as paroxysmal movements, nystagmus, twitching, jerking, hippus, autonomic variability)
• Monitoring of ongoing therapy: Induced coma for elevated intracranial pressure or refractory status epilepticus, Assessing level of sedation
• Prognosis: Following cardiac arrest, acute brain injury
b) What are the clinical implications of non-convulsive status epilepticus (NCSE) in the critically ill patient?
An underdiagnosed entity.
In several studies, the presence of NCSE and delay to diagnosis and treatment were each associated with significantly more frequent mortality. Periodic epileptiform discharges (PED) have also been associated with a significant increase in death or severe disability at hospital discharge in particular in neurologic disease/injury. NCSE may also occur in those without primary brain injury e.g. sepsis and conveys the same prognosis. Aggressive treatment as for convulsive status epilepticus is recommended.
c) List two EEG patterns that may be seen after hypoxic brain injury thought to be associated with a poor prognosis.
Note: none of these patterns are specific for death or poor outcome and must be regarded along with clinical assessment.
• Generalised suppression/isoeletric
• Generalised burst suppression especially if accompanied by epileptiform activity
• Epileptiform and generalised periodic discharges, especially myoclonus
• Alpha pattern coma
Discussion
a) This answer comes from Box 49.2 in Oh's Manual (page 556).
- Confirmation of non-convulsive status epilepticus
- Continuous monitoring of general anaesthetic infusion for status epilepticus
- Confirmation of brain death or prognosis of hypoxic/ischaemic brain injury
b)
- Brain injury (excitotoxicity) could occur due to unrecognised seizures
- Cerebral metabolic rate may be higher, and cerebral metabolic demand may not be met if the NCSE is not recognised and treated, giving rise to ischaemia
- NCSE patients have a poorer prognosis than patients with a disorder of consciousness from other causes
- The underlying cause of NSCE is the most important prognostic factor
c) Again, the same box in Ohs Manual has the answers. Severe hypoxic encephalopathy is associated with the following EEG features:
- Presence of theta activity
- Diffuse slowing
- Burst suppression
- Alpha coma
References
Oh's Intensive Care manual: Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Question 25.2 - 2011, Paper 1
Examine the photograph shown below

This image is not from the college paper, but is reproduced without any permission whatsoever from this blog post by A. Lewis. Hang in there.
a) List three likely anatomical sites of lesions that can result in these eye signs
b) Give two associated clinical features that would help determine the site of the lesion?
College Answer
a) List three likely anatomical sites of lesions that can result in these eye signs
Any three anatomical sites of the lesion:
• Hemispheric lesion (hemispherectomy, massive hemispheric CVA, thalamic CVA)
• Brainstem lesion (brainstem infarct, multiple sclerosis, brainstem tumour or encephalitis)
• Central cord lesion (syringomyelia, glioma, ependymoma, traumatic)
• T1 root lesion (Pancoast tumour, cervical rib, brachial plexus avulsion, aortic or subclavian aneurysm
• Sympathetic chain (laryngeal, pharyngeal, thyroid or parathyroid surgery, carotid artery lesion, malignancy at base of skull)
b) Give two associated clinical features that would help determine the site of the lesion?
Any two of:
• distribution of loss of sweating
• distribution of loss of pain and temperature sensation
• motor deficit
• signs of central cord syndrome
• wasting of small muscles of hand and clubbing
• cervical LNs
• Signs of head / neck surgery/trauma
• Subclavian artery bruit
Discussion
This question is well revised from Table 10-12 of the most recent edition of Talley and O'Connor, which I have fancifully reinterpreted below:
|
In brief, one could answer the question in the following manner:
a) three likely anatomical sites of lesions:
- Cortical hemisphere (eg. stroke or tumour)
- Brainstem (eg. stroke or tumour)
- Brachial plexus (eg. pancoast tumour)
b) two associated clinical features that would help determine the site:
- Contralateral hemiparesis (cortical hemisphere or brainstem infarct)
- Brainstem nuclei signs (diplopia, vertigo, ataxia)
- Brachial plexus signs (eg. arm pain or weakness, small muscle wasting)
This could be really over-done. For example, in the cranial nerves section, there is a much longer list:
Causes of Horner's |
Associated clinical findings: |
| Cluster headache |
|
| Cortical stroke (hemispheric) |
|
| Brainstem stroke (lateral medullary syndrome) |
|
| Cavernous sinus pathology |
|
| Syringobulbia |
|
| Syringomyelia |
|
| Spinal injury or infarction |
|
| Malignancy in the apex of the lung |
|
| Thyroid cancer |
|
| Neck trauma or surgery |
|
| Lower trunk brachial plexus injuries |
|
| Carotid aneurysm or dissection |
|
References
Clinical Examination of the Critically Ill Patient, 3rd edition by L.I.G. Worthley - which can be ordered from our college here.
Clinical Examination: whatever edition, by Talley and O'Connor. Can be acquired any damn where.
Question 25.4 - 2011, Paper 1
The illustrations below illustrate a test being carried out in an unconscious patient.
The patient’s head is being moved from side to side.
This image is "borrowed" from Life In The Fast Lane, who appropriated it from Poser JB, et al. Plum and Posner’s Diagnosis of Stupor and Coma (4th edition), Oxford university Press, 2007. It has been lightly modified.
a) Name the neurological structures involved in the reflex being tested
b) What does the result shown in the illustrations suggest about the cause of unconsciousness?
College Answer
a) Name the neurological structures involved in the reflex being tested
• VIII nerve and vestibular nucleus
• III and VI nerves and nuclei
• Median longitudinal fasciculus
b) What does the result shown in the illustrations suggest about the cause of unconsciousness?
The cause is unlikely to be due to an anatomical lesion affecting the reticular activating system (Brain stem function is still present)
Discussion
The reflex arc for this physical sign can be found in Fetter's 2007 review article.
a) The vestibulocochlear nerve, the brainstem nuclei of the vestibulocochlear nerve, the fibers to the cerebellum, the fibers from the cerebellum, the medial longitudinal fasciculus (MLF) and the 3rd and 6th cranial nerves.
b) The cause of the unconsciousness in a patient with a negative oculocephalic reflex is some sort of destructive brainstem pathology or brain death.
A positive oculocephalic reflex is a good sign. In an intubated patient with comically huge eyeballs, it should look like this:

The pathways which command this reflex involve vestibular nuclei, lower pontine tegmentum, the upper pontine tegmentum, the midbrain paramedian tegmentum, and the medial longitudinal fasciculus. These are large, central brainstem regions, which overlap with the ascending arousal system. Thus, it would be highly unlikely that a structural lesion of some sort (like a stroke) has taken out the rest of the brainstem, leaving these regions intact.
In other words, if the oculocephalic reflex is intact, the coma is unlikely due to a structural brainstem lesion.
A more detailed overview of this reflex can be found at LITFL's page on the examination of the unconscious patient. Plum and Posner, on page 66 of their famous textbook (4th edition), include a well known diagram of lesions at different levels and their associated findings on oculocephalic and caloric testing, and the image from the college question has been ..borrowed ... from there.

References
Nathanson, Morton, Philip S. Bergman, and Paul J. Anderson. "Significance of oculocephalic and caloric responses in the unconscious patient." Neurology7.12 (1957): 829-829.
Fetter, Michael. "Vestibulo-ocular reflex." (2007): in: Developments in Ophthalmology, Vol.40 (ed: A.Straube and U.Buttner), Karger 35-51.
Clinical Examination of the Critically Ill Patient, 3rd edition by L.I.G. Worthley - which can be ordered from our college here.
Clinical Examination: whatever edition, by Talley and O'Connor. Can be acquired any damn where.
Question 13 - 2011, Paper 2
You are asked to admit a 46-year-old man who has just been intubated in the Emergency Department after collapsing from what appears clinically to be a brain stem stroke. His Glasgow Coma Score prior to intubation was 6.
Outline your management strategy for him for the first 24 hours.
College Answer
Activate the stroke team if available in this hospital as urgent intervention is needed for the best
potential outcome – involves neurologist and interventional neuroradiologist.
Attention to ABC (confirm tube position, adequacy of ventilation, control hypertension and treat
hypotension to ensure adequate CPP)
Investigations / Interventions
• CT scan to exclude bleed and confirm diagnosis – can miss post fossa and brainstem lesions
in the early stages so MRA may be indicated
• Interventional cerebral angiography and thrombectomy if within time window and facilities and
resources available.
• Thrombolysis with tPA within 4.5 hours of event if intervention unavailable or unsuccessful
• Heparin infusion
• Aspirin
Physiological monitoring and maintenance of normal parameters (BP, Na, BSL etc)
Role of EVD if hydrocephalus is present
Ongoing neurological assessment – at risk of progressing to locked in syndrome
Supportive care of the intubated ventilated critically ill patient
Discussion with family re therapy and outlook plus risk factors for poor outcome
Discussion
This question does not seem to stem from any specific guidelines.The college is asking what one might do with a brainstem stroke; in order to pass the candidate needs to
- demonstrate that they understand the importance of early thrombolysis
- know about the role of interventional neuroradiology in stroke
- appreciate the need to exclude intracranial haemorrhage, and the limitations of CT in posterior fossa lesions
- know how to manage stroke if neither thrombolysis nor clot retrieval is possible
- appreciate the possibility of hydrocephalus developing with posterior fossa strokes
- appreciate the prognosis of such a stroke, and the need to manage family expectations.
A detailed discussion of the definitive management options in acute stroke is available elsewhere.
Supportive management of acute stroke is also covered in a summary article.
If one were to summarise in brief the approach to management here, it would resemble this:
Definitive management option:
- Intravenous thrombolysis
- Intraarterial thrombolysis
- Endovascular embolectomy
- Conservative management and subsequent antiplatelet therapy
Supportive management:
- Airway: intubation, for the protection thereof (being mindful that it may be futile)
- Ventilation: aiming for normocapnea
- Circulatory support: to keep BP normal, and below 220 mmHg systolic
- Sedation: as needed to tolerate ICU management in comfort
- Electrolyte and endocrine control: ensuring normoglycaemia and normothermia
- Fluid balance management to ensure protection of renal function following contrast
- Enteric nutrition may commence by the nasogastric route
- Heparin is not indicated given the risk of haemorrhagic transformation*
- Antibiotic therapy if contaminated aspiration is suspected
* It should be pointed out that though the college (writing in 2011) suggest the use of a heparin infusion, this strategy has already fallen out of favour by this stage, given that it seems to kill people. Certainly, the 2007 AHA guidelines were not in favour of its use.
References
Regarding early thrombolysis:
Wardlaw JM, Zoppo G, Yamaguchi T, Berge E. Thrombolysis for acute ischaemic stroke. Cochrane Database Syst Rev. 2003;(3):CD000213.
The Stroke Foundation guidelines for management of acute stroke
Regarding early cerebral angiography and thrombectomy:
The Stroke Foundation guidelines dont actually recommend mechanical clot retrieval ("insufficient evidence", they say) but they do recommend intra-arterial thrombolysis, and the reference they give is the 2009 update of the Wardlaw meta-analysis mentioned above.
Regarding the need to exclude intracranial haemorrhage:
The need itself does not require references - it is common sense. CT or MRI? Here is a Cochrane review; diffusion-weighted imaging seems to be more sensitive in detecting ischaemic stroke.
Brazzelli M, Sandercock PA, Chappell FM, Celani MG, Righetti E, Arestis N, Wardlaw JM, Deeks JJ. Magnetic resonance imaging versus computed tomography for detection of acute vascular lesions in patients presenting with stroke symptoms. Cochrane Database Syst Rev. 2009 Oct 7;(4):CD007424. doi: 10.1002/14651858.CD007424.pub2.
Regarding antiplatelet agents and anticoagulation:
Again, the Stroke Foundation guidelines for management of acute stroke recommend aspirin and hemaprin in patients who definitely have no haemorrhage.
Regarding the possibility of hydrocephalus
I have not found any literature about the actual risk of this happening with undifferentiated posterior fossa lesions, but cerebellar infarction stands out as the leading culprit:
Hornig CR, Rust DS, Busse O, Jauss M, Laun A. Space-occupying cerebellar infarction. Clinical course and prognosis. Stroke. 1994 Feb;25(2):372-4.
Regarding the prognosis of brainstem stroke:
There is a good (though dated) article regarding the prognosis of stoke in the ICU. Sensibly, it seems older patients and those in a coma on admission have the poorest prognosis.
Steiner T, Mendoza G, De Georgia M, Schellinger P, Holle R, Hacke W.Prognosis of stroke patients requiring mechanical ventilation in a neurological critical care unit. Stroke. 1997 Apr;28(4):711-5.
Regarding the danger of heparin infusion:
Adams, Harold P., et al. "Guidelines for the Early Management of Adults With Ischemic Stroke " Circulation 115.20 (2007): e478-e534.
Question 22.1 - 2011, Paper 2
A 20-year-old female mechanically ventilated, paralysed and sedated in ICU following a diffuse axonal head injury, develops a severe exacerbation of intracranial hypertension on day 3. Investigations taken during a subsequent episode of polyuria are as follows:
|
Parameter |
Patient Value |
Normal Range |
|
pH |
7.5* |
7.35 – 7.45 |
|
PaCO2 |
28* mmHg (3.7 kPa) |
35 – 45 (4.6 – 6.0) |
|
HCO3 |
21* mmol/l |
22 – 27 |
|
Standard base excess |
-1.5 mmol/l |
-2 – +2 |
|
Sodium |
147 mmol/l |
135 – 145 |
|
Potassium |
3.2 mmol/l |
3.2 – 4.5 |
|
Chloride |
110 mmol/l |
100 – 110 |
|
Urea |
3.0 mmol/l |
3.0 – 8.0 |
|
Creatinine |
65 µmol/l |
50 – 100 |
|
Glucose |
4.0 mmol/l |
3.0 – 6.0 |
|
Measured plasma osmolality |
333* mOsm/kg |
275 – 295 mOsm/kg |
|
Urine osmolality |
410 mmol/l |
300 – 1300 mOsm/kg |
a) What is the most likely explanation for the polyuria?
b) Give your reasoning.
College Answer
a) What is the most likely explanation for the polyuria?
Mannitol therapy
b) Give your reasoning.
Increased measured plasma osmolality with an elevated osmolar gap - 32 mOsm/kg with formula (2xNa + glucose + urea) or 44 mOsm/kg with 1.86 x (Na+K) + urea + glucose. High urinary osmolality rules out diabetes insipidus. History supports osmotherapy to treat episode of raised ICP
Discussion
This question is identical to Question 3.1 from the second paper of 2010, and Question 3 from the second paper of 2007 (which contains an answer with a more complete interpretation of this issue).
References
Question 26.1 - 2011, Paper 2
List 4 clinical signs which may be noticeable on examination of the head in a patient with cerebellar disease.
College Answer
- Nystagmus
- Titubation
- Staccato speech
- Skew deviation of the eyes
- Impairment of finger-nose test
Discussion
This question interrogates one's knowledge of the highly regarded Talley and O'Connor manual of physical examination.
Talley and O'Connor visits the cerebellum twice, once in the chapter on the neurological examination of the head, and once in the discussion of "Correlation of physical signs and neurological disease". Neither time is there discussion of what specifically to look for in the patient's head. Its just not that specific.
Similarly, L.I.G Wortheley in the 3rd edition of CECIP (Clinical Examination of the Critically Ill Patient) makes mention of the cerebellum, but does not actually go through it in quite such a fashion.
So, where does one go for a thorough summary of what one can expect from a cerebellum-damaged head?
It seems, nowhere.*
Thankfully, from our medical school days, it seems about 84% of us can remember at least a few of the cerebellar signs. But, in searching for the specific signs mentioned by the college, I came across something. A website by the Coopers. ** These seem to be a couple who have moved from Australia to Ohio. This, in a deliciously unexplained twist, is completely irrelevant to the extravagant and all-encompassing mass of neurological examination material which abounds on their site. I have taken the liberty of linking to some of the documents they host.
Bob and Christina Cooper, I salute you.
* Several years after writing this rant, I have discovered a venerable document from 1990, available for free for all to read, which conveniently divides the cerebellar examination into body regions. This resource has subsequently given rise to a locally available summary of cerebellar physical signs and examination technique. The obsolete rant still remains in situ for structural reasons. - AY.(2015)
** That Coopers website is now down. http://www.hy-q.com/ now sends you to something completely unlike the cranial nerves. I believe it now belong to the manufacturer of industrial sensors. At this stage, the whereabouts of the Coopers are unknown. Their site can still be seen by accessing the archived copy on the Wayback Machine Internet Archive, where some of the PDF documents are still preserved. - AY.(2018)
References
Schmahmann JD (2004). "Disorders of the cerebellum: ataxia, dysmetria of thought, and the cerebellar cognitive affective syndrome". J Neuropsychiatry Clin Neurosci 16 (3): 367–78
Clinical Examination of the Critically Ill Patient, 3rd edition by L.I.G. Worthley - which can be ordered from our college here.
Clinical Examination: whatever edition, by Talley and O'Connor. Can be acquired any damn where.
My own gibberish notes from medical school.
Walker, H. Kenneth, W. Dallas Hall, and J. Willis Hurst. "The Neurologic System." (1990). Specifically: Chapter 69, "The Cerebellum"
Question 26.2 - 2011, Paper 2
A patient presented with sudden onset of weakness involving his left upper and lower limb. On examination, he was conscious, with a dilated non-reactive right pupil, normal power in the right upper and lower limbs, and a left hemiparesis. What is the likely site of lesion? Outline your reasoning.
College Answer
Right side of the midbrain. It is a crossed hemiplegia suggesting a brainstem stroke and the 3rd nerve nucleus is located in the midbrain.
Discussion
This question interrogates one's knowledge of the highly regarded Talley and O'Connor manual of physical examination.
Let us reason through this. A left hemiparesis suggests right sided cerebral pathology.
A right sided unreactive pupil suggests that the third nerve is somehow involved, and the nucleus for it is in the midbrain. Ergo, the right midbrain has infarcted. The hemiparesis reflects damage to the right-sided motor tracts above the level of the decussation (which is at the medulla).
References
The Internet Stroke Centre has an excellent summary of stroke syndromes.
Clinical Examination of the Critically Ill Patient, 3rd edition by L.I.G. Worthley - which can be ordered from our college here.
Clinical Examination: whatever edition, by Talley and O'Connor. Can be acquired wherever good books are sold or stolen.
Question 28 - 2011, Paper 2
A 27-year-old male presents with a severe head injury (GCS 4 at the scene), sustained in a high-speed motor vehicle collision. His initial CT scan in the emergency department shows a 2x3x2.5cm frontal haemorrhagic contusion and diffuse oedema. He is taken directly to the operating theatre where an external ventricular drain (EVD) is inserted. The patient is settled into the ICU and his secondary survey does not reveal any other significant injuries. The initial ICP is 32 mmHg after the EVD is connected.
a) If the ICP is refractory to your initial management of sedation, paralysis and correct positioning, what further measures will you consider and why?
b) What are the risk factors for post-traumatic seizures in patients with traumatic brain injury?
College Answer
a) If the ICP is refractory to your initial management of sedation, paralysis and correct
positioning, what further measures will you consider and why?
- Ensure EVD patent and CSF draining (reduce CSF component of ICP)
- Measures to maintain CPP > 60 mmHg
- Fluids (avoid albumin – SAFE TBI)
- Vasopressors
- Repeat CT scan to exclude a new mass lesion
- Osmotherapy (hypertonic saline or mannitol)
- Goal Na+ 150, Osm 300-320
- Consider barbiturates or propofol (decrease CMRO2)
- Consider continuous paralysis (decrease CMRO2)
- Consider moderate hypothermia (decrease CMRO2 and potentially neuroprotective)
- Adverse outcome in paediatric TBI RCT from CCCTG
- McIntyre MA suggesting titrated to ICP and prolonged duration may be beneficial
- Ongoing trials including POLAR in ANZ
- Decompressive craniotomy is contentious
- DECRA showed decreased ICP and reduced ICU length of stay but no mortality benefit and a greater number of patients with an unfavourable neurological outcome in those who received decompressive craniectomy.
- Patients with mass lesions (unless too small to require surgery) were excluded so this patient may not have been included in the study.
- Only a single surgical intervention was used.
b) What are the risk factors for post-traumatic seizures in patients with traumatic brain injury?
- GCS < 10
- Cortical contusion
- Depressed skull fracture
- Subdural, epidural or intracerebral haematoma
- Penetrating head wound
- Seizure within 24 hours of injury
Discussion
This question interrogates the candidate's familiarity with the more outré methods of decreasing a person's intracranial pressure.
Lets face it, anybody can sedate, paralyse and position the patient. Those measures are basic.
a)What further measures will you consider and why?
The Brain Trauma Organisation Guidelines for Management Traumatic Brain Injury contain a set of guidelines, which I have mindlessly parroted here.
Ultimately, there is an escalating series of management strategies which are standard for this scenario.
Control ICP by immediate measures:
- Open EVD to drain CSF
- Osmotherapy
- Hypertonic saline to keep Na+ around 150
- Consider intermittent mannitol
- Consider paralysis
Exclude new intracranial pathology:
- CT brain
Maintain cerebral oxygen supply:
- Normoxia
- Normotension (CPP >60mmHg) - maintained with fluids or vasopressors
- Monitor cerebral oxygenation, keep the SjO2 >50%
Decrease cerebral oxygen demand:
- Sedate with propofol
- Ensure adequate analgesia
- Consider barbiturate coma
- Consider hypothermia
Discuss a decompressive craniotomy with the neurosurgeon.
b) The risk factors for post-traumatic seizures
This answer was taken directly from the Brain Trauma Organisation Guidelines for Management Traumatic Brain Injury. Word for word, in fact; copy and paste. See it here.
I will reproduce them here for ease of reference;
- Glasgow Coma Scale (GCS) Score < 10
- Cortical contusion
- Depressed skull fracture
- Subdural hematoma
- Epidural hematoma
- Intracerebral hematoma
- Penetrating head wound
- Seizure within 24 h of injury
I should probably also digress for a moment to discuss the duration of seizure prophylaxis (the Brain Trauma Foundation recommends no more than 1 week). Post-traumatic seizure management is well covered elsewhere.
References
Chapter 43 (pp. 563) Cerebral protection by Victoria Heaviside and Michelle Hayes, and
Chapter 67 (pp. 765) Severe head injury by John A Myburgh.
Brain Trauma Organisation Guidelines for Management Traumatic Brain Injury is the definitive source.
Question 22 - 2012, Paper 1
Discuss the use of the Glasgow Coma Scale (GCS) in patients with traumatic brain injury in your practice and outline its limitations.
(There is no need to document the components of the GCS)
College Answer
General introduction
The GCS is a neurological scoring system used to assess conscious level after head injury. It is now usually scored out of 15 and is comprised of 3 categories, best eye response, best vocal response and best motor response. It has recently been used to categorise traumatic brain injury into mild, moderate and severe.
Advantages
It is the most widely recognised of all conscious level scoring systems in the world. It is quick and reproducible. It is skewed towards motor score, which is good since this is the most reliable measure of short-term prognosis in TBI. The distinction between a motor score of 2, 3 and 4 is a very useful clinical indicator of the severity of TBI, and the area of brain function that has been affected.
Disadvantages
- It fails to incorporate brain-stem reflexes
- It is unreliable in patients in the middle range of 9-12
- There is poor inter-observer reliability
- It is difficult for untrained staff to apply properly, especially distinguishing between M= 3,4,5
- Variation in scoring V in intubated patients
- M score does not factor in unilateral pathology
Controversy in the literature
- There is little evidence demonstrating validity and reliability of the GCS
- There are numerous other neurological scoring systems that have demonstrated greater validity and reliability e.g. the FOUR score
- Debates within the literature as to when GCS can be first applied after TBI, i.e when is the first post-resuscitation GCS applicable
How I use GCS in my practice.
- A statement of when and how GCS is used in TBI
- An appreciation of the need for all staff on the intensive Care Unit to be aware of the same criteria for its use and application
- An appreciation that on-going education is needed to make sure that it is used correctly
Discussion
The college answer is fairly comprehensive.
A thorough discussion of the advantages and disadvantages of the GCS can be found elsewhere.
It forms a part of the greater topic, the Assessment of the Unconscious Patient.
In brief, the major disadvantages are:
- It was never meant as an assessment tool for trauma.
- It is unreliable in patients in the middle range of 9-12
- People dont know how to use it correctly.
- It has high inter-observer variability
- It is inadequate to assess higher cortical functions.
- It is inadequate to assess brainstem reflexes.
- Therefore, it cannot be used as a trigger for intubation (GCS of 8)
- The eye score is unreliable if the eyes are damaged.
- The eye score may be meaningless (it is possible to score an E4 even if one is braindead)
- The total score is meaningless:
- The components are more important individually
- Depending on the individual component score, the prognosis may be very different for patients with the same total score.
- It is affected by drugs and alcohol.
- However, it is still used in assessing drug overdose patients.
- It is affected by language barriers
- Intubation makes a mockery of its verbal conponent
- It needs to be modified for use in young children.
The article by Green (2011) is the definitive resource on this topic, as it is a comprehensive review, in spite of being one person's opinion.
References
Green, Steven M. "Cheerio, laddie! Bidding farewell to the Glasgow Coma Scale." Annals of emergency medicine 58.5 (2011): 427-430.
Gill, Michelle R., David G. Reiley, and Steven M. Green. "Interrater reliability of Glasgow Coma Scale scores in the emergency department." Annals of emergency medicine 43.2 (2004): 215-223.
Riechers, Ronald G., et al. "Physician knowledge of the glasgow coma scale."Journal of neurotrauma 22.11 (2005): 1327-1334.
Question 25 - 2012, Paper 1
A 69-year-old man has been ventilated for an infective exacerbation of chronic obstructive pulmonary disease (COPD). Therapy has included steroids and an aminoglycoside antibiotic. His ICU course has been complicated by septic shock and acute kidney injury.
Twelve days later neurological examination off sedation reveals moderate to severe weakness of his limbs with intact sensation, normal cognition and normal cranial nerves
- List the differential diagnoses for his weakness.
- Outline how you would determine the diagnosis.
- List of differential diagnoses for his weakness
College Answer
a) List of differential diagnoses for his weakness
-
- Critical illness myopathy / Acute quadriplegic myopathy* (high dose steroids, with or without nondepolarising paralyzing agent use, Beta agonists)
- Critical Illness polyneuropathy/myopathy* (SIRS, sepsis, MODS)
- *Residual sedation and other drug influences (Renal [&/or liver] impairment contributing, aminoglycoside with NMJ effect)
- *Electrolyte abnormalities (PO4, Ca++, K+)
- Deconditioning with weakness exacerbated by subclinical sepsis
- Underlying polyneuropathy/myopathy exacerbated by critical illness Alcohol, B12 deficiency, paraneoplastic, consider diabetic
- GBS
- Rhabdomyolysis (drugs (e.g. statins), infections) should be thought of given renal failure
- acute myelitis or watershed infarction (acute upper motor neuron lesions may not yet have developed hypertonia and hyper-reflexia)
- Autoimmune neuropathy or myopathy (rare)
b) Diagnosis
Any relevant history.
Clinical examination:
-
- Normal higher functions and cranial nerves favour a critical illness neuromyopathy (CINM) or a purely peripheral nervous system. Spinal lesion possible although less likely + normal sensory examination
- Symmetrical features on peripheral neurological exam also favours CINM. Cerebral watershed infarction is possible but less likely given distal power is usually relatively spared.
- Critical illness myopathy often affects the diaphragm
- Tendon reflexes are absent or profoundly decreased in neuropathies and decreased in myopathies. They should be essentially normal in de-conditioning or with residual sedative effect.
- Plantars are unhelpful as they are equivocal
- Lack of focal neurology or relative sparing of distal motor power (watershed infarction) tends to exclude central causes (eg CVA) or mononeuropathies.]
- Distribution of weakness is symmetrical in all other causes and tends to be more profound proximally in myopathies, facial involvement tends to occur more in myopathies than in neuropathies (rare exception Miller-Fisher GBS variant).
- Muscle wasting may be present with myopathies and when there exists a pre-existing myopathy or neuropathy. Muscle fasciculation is uncommon but if present supports a lower motor neuron lesion, severe neuropathy or myopathy.
Investigations:
-
- Check biochem and ABGs (U&E’s, LFT’s – espy K, PO4, Ca, Mg, pH, PaCO2), FBE and inflammatory markers, Vit D and Gentamicin level
- Review cultures and sensitivities and abx used to determine the possibility of ongoing or resistant infection.
- CK – timing of test to be considered (Best done in first 7 days of illness – if not performed add test to previous blood samples - Elevated in myopathies
- Nerve conduction studies and Electromyographic studies help support diagnoses of neuropathy and myopathy (vs severe deconditioning or central causes)
- CSF analysis (GBS), may be required .
- Muscle Biopsy may be required.
- MRI if central cause suspected or NCS and EMG don’t support CINM
Discussion
The college answer is extensive and covers the territory well.
For revision purposes, several chapters exist locally:
- Ch.5.5.1 - Approach to the ICU patient with generalised weakness
- Ch.5.5.2 - Features that distinguish myopathy from neuropathy
- Ch.5.5.3 - Intensive Care for Guillain-Barre Syndrome
- Ch.5.5.4 - Critical illness polyneuromyopathy
- Ch.5.5.5 - Features that distinguish Guillain-Barre syndrome from critical illness polyneuromyopathy
From the above resources (specifically, from the table in chapter 5.5.1) I will pick some relevant conditions and put them in a sensible pattern to assist their recollection:
Differential diagnosis for weakness:
- Central:
- Spinal or brainstem ischaemia (unlikely)
- Peripheral nerve:
- Autoimmune polyneuropathy, eg. Guillain-Barre syndrome
- Criticial illness neuromyopathy
- Nutritional polyneuropathy, eg. B12 deficiency
- Neuromuscular junction
- Myasthenia gravis (unlikely)
- Aminoglycoside-induced weakness (in association with neuromuscular junction blockers)
- Muscle
- Atophy due to prolonged ICU stay, hypercatabolic state and malnutrition
- Criticial illness neuromyopathy
- Steroid myopathy
- Electrolyte derangement, eg. hypophosphataemia, hypocalcemia, hypermagnesemia or hypokalemia
Clinical examination
- GCS (brainstem-damaged or "locked in" syndrome)
- Gross bilateral power (looking for symmetry, distal sparing, lateralising motor feature)
- Cranial nerve examination (Normal cranial nerves suggest a purely peripheral problem)
- Tendon reflexes (absent in neuropathies, decreased in myopathies)
- Fatiguability (Myasthenia gravis vs. "reverse" fatiguability with Lambert-Eaton syndrome)
A panel of investigations:
- Electrolyte levels
- CK level
- B12 level
- Inflammatory markers
- Lumbar puncture
- Nerve conduction studies
- Electromyography
- MRI of the brainstem and spine
- Muscle biopsy if no satisfactory explanation is found.
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Jani, Charu. "Critical Illness Neuropathy." Medicine (2011): 237.
Young, G. Bryan, and Robert R. Hammond. "A stronger approach to weakness in the intensive care unit." Critical care 8.6 (2004): 416.
Question 15.3 - 2012, Paper 2
List the main feature(s) of these fundoscopy images a), b) and c) and name the conditions associated with them.
The images below are not from the college paper, but rather harvested from Google Images, labelled for non-commerical reuse.
a)

b)

c)

College Answer
- a) Retinal Haemorrhage (Coagulopathy, thrombocytopenia)
- b) Papilloedema (Raised intracranial pressure)
- c) Optic disc swelling, retinal haemorrhages and infarcts or cotton wool spots. (Malignant Hypertension)
Discussion
This is a bog-standard pattern recognition question.
I need to point out that the image in a) is one of branch retinal vein occlusion - it just so happens that it also features retinal haemorrhage.
Common fundoscopy findings are discussed with (slightly) more detail in the relevant Required Reading section.
References
The Stanford School of Medicine has an excellent resource on fundoscopy.
So does Walker's Clinical Methods (3rd ed, 1990) - the chapter on fundoscopy is particularly good for pathophysiological correlations.
Question 20 - 2012, Paper 2
With respect to non-convulsive status epilepticus (NCSE) in the critically ill:
- Give a definition for NCSE
- Outline the difficulties in making the diagnosis
- List the risk factors for NCSE
- Outline your approach to the management of a patient with suspected NCSE
College Answer
Definition:
Change in behaviour and or mental processes from baseline associated with continuous epileptiform EEG changes but without major motor signs. NCSE comprises a group of syndromes with a wide range of response to anti-convulsants from virtually self-limiting forms to refractory forms. No universally accepted definition yet exists
Difficulties in Diagnosis:
Little agreement on diagnostic criteria, clinical forms, consequences and treatment Difficulty telling when coma is due to ictal symptomatology and differentiating it from non ictal symptoms associated with underlying pathology such as posthypoxic, metabolic or septic encephalopathies and effects of sedative drugs.
On EEG there are cross over features between epilepsy and encephalopathies which are being still standardized and the diagnosis of NCSE should not be on EEG changes alone.
Early recognition and treatment are essential to optimize response to treatment and to prevent neurological and systemic sequelae. However overdiagnosis and aggressive use of anticonvulsants may also contribute to morbidity and mortality.
Risk factors:
- Systemic infection in patient with pre-existing epilepsy
- Stroke including intracerebral & subarachnoid haemorrhages
- Dementia
- Neoplasia
- Previous neurosurgery
- Patients with pre-existing epilepsy have a lower mortality (3%) than where NCSE is due to acute medical disorders (27%).
Management:
- Difficulties in diagnosis as outlined above
- Index of suspicion in patients with risk factors and suggestive clinical features
Investigations
- Blood tests to exclude electrolyte abnormalities (low Ca, low Mg), liver and renal dysfunction, haematological causes (e.g TTP)
- Lumbar puncture: looking for CNS infection
- EEG and response on EEG and clinically to Benzodiazepines
- MRI to exclude structural cause not evident on CT
Treatment
- Treatment of underlying cause Benzodiazepines: Diazepam or Lorazepam
- Valproate: if failure to respond to benzodiazepines
- Keppra increasingly used
- Reversal of factors that lower seizure threshold eg drugs such as cefepime, fever, hypoxia, hypoglycaemia, hyponatraemia
Discussion
Non-convulsive status epilepticus comes up often enough to merit its own little summary page.
a)
The diagnosis of non-convulsive status epilepticus requires the following:
- A change in behaviour or responsiveness
- A duration of change for longer than 30 minutes
- No obvious seizure activity
- Epileptiform discharges on EEG
b)
The difficulty in making the diagnosis is the protean nature of its manifestations, which range from confusion and delirium to unconsciousness. As there are numerous pathologies which are more common and which can present in this way, the diagnosis (by EEG confirmation) is frequently delayed.
c)
Risk factors for non-convulsive status epilepticus are similar to the risk factors for epilepsy in general, and include:
- Structural brain disease:
- Stroke
- Space occupying lesion (blood, pus or tumour)
- Gliosis due to previous stroke, brain injury or neurosurgery
- Dementia
- Metabolic
- Sepsis in a patient with known epilepsy
d) Approach to management:
- Attention to the ABCS, with management of life-threatening problems simultanous with a rapid focused examination and a brief history
- Supportive management
- Assessment of the airway, and airway control if appropriate
- Ventilation support, or supplemental O2 in the spontaneously breathing patient
- Circulatory support to ensure normotension
- Endocrine and metabolic support to ensure correction of electrolyte derangement and control of blood glucose
- Specific management
- Benzodiazepines: midazolam or lorazepam
- Anticonvulsants: phenytoin, valproate or levitiracetam
References
Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Chapter 50 (pp. 560) Status epilepticus by Helen I Opdam
Fountain, Nathan B. "Status epilepticus: risk factors and complications."Epilepsia 41.s2 (2000): S23-S30.
Meierkord, Hartmut, and Martin Holtkamp. "Non-convulsive status epilepticus in adults: clinical forms and treatment." The Lancet Neurology 6.4 (2007): 329-339.
Question 22 - 2013, Paper 1
A 60-year-old male presents 2 hours after the onset of vertigo and loss of consciousness. CT brain is performed and shows right basilar and vertebral occlusion with no evidence of infarction.
Discuss two possible definitive treatment strategies for this condition, including the indications and contra-indications of each.
College Answer
TWO of the following:
Intravenous thrombolysis
The patient is within the suggested time window for thrombolysis and by current guidelines should receive intravenous rtPA. Overall this treatment reduces deaths and dependency but is associated with a risk of potentially fatal intracranial haemorrhage.
Indications include patients with acute ischaemic stroke presenting within the appropriate time window (note to examiners – while initial guidelines suggested a time window of three hours there is data suggesting use up to 4.5 hours may be beneficial)
Contraindications include:
- Stroke or head trauma in previous 3 months
- Intracranial haemorrhage: past or present
- Major surgery in previous 14 days
- GI or urinary tract bleeding in previous 21 days
- MI in previous 3 months
- Non-compressible arterial puncture in previous 7 days
- Persistent severe hypertension
- Active bleeding or acute trauma
- Thrombocytopaenia
Intra-arterial thrombolysis
Although intra-arterial thrombolysis results in higher rates of re-cannulation there is no evidence that it reduces mortality or morbidity. However in patients who have undergone recent surgery (and therefore have a contra-indication to intravenous thrombolysis) or exceed the 6 hour time window for intravenous thrombolysis intra-arterial thrombolysis may be useful
Endovascular Thrombectomy
This technique may be used in large vessel thrombus,especially if recanalisation has not occurred with intravenous thrombolysis, or the patient is outside the time window . It requires specialist expertise that may not be generally available, and carries the risk of vascular damage or dissection with potential worsening of symptoms.
Indications would include ischaemic stroke in a large vessel in patients who have either failed thrombolysis or have a contraindication to it.
Contraindications include:
- Tortuous vessels precluding angiographic access
- Pre exisiting coagulopathy
- Established infarct on imaging
- Contrast allergy
Discussion
In essence, a stroke patient presents well within the timeframe for reperfusion therapy.
Let us tabulate this answer.
| Strategy | Indications | Contraindications |
| Intravenous Thrombolysis |
|
|
| Intraarterial thrombolysis |
|
|
| Endovascular embolectomy |
|
|
The window for thrombolysis seems to be three hours according to the college answer, though "there is data suggesting use up to 4.5 hours may be beneficial". That probably refers to Hacke et al (ECLASS III, 2008) who went as late as 4.5 hours post stroke. Modern Australian Stroke Foundation guidelines recommend 4.5 hours as the cut-off on the basis of the meta-analysis articles by Wardlaw et al (2014) and Emerson et al (2014). The MERCI trial investigators managed to get good outcomes even 8 hours post infarct, which is encouraging. However, these outcomes were still poorer than historical controls.
The issue of acute stroke management is discussed in brief summary elsewhere.
References
Oh's Intensive Care manual: Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer.
Smith, Wade S., et al. "Safety and efficacy of mechanical embolectomy in acute ischemic stroke results of the MERCI trial." Stroke 36.7 (2005): 1432-1438.
Nogueira, R. G., et al. "Endovascular approaches to acute stroke, part 2: a comprehensive review of studies and trials." American Journal of Neuroradiology30.5 (2009): 859-875.
Brinjikji, Waleed, et al. "Patient outcomes with endovascular embolectomy therapy for acute ischemic stroke a study of the national inpatient sample: 2006 to 2008." Stroke 42.6 (2011): 1648-1652.
Kidwell, Chelsea S., et al. "Design and rationale of the mechanical retrieval and recanalization of stroke clots using embolectomy (mr rescue) trial."International Journal of Stroke 9.1 (2014): 110-116.
Jansen, Olav, et al. "Neurothrombectomy for the treatment of acute ischemic stroke: results from the TREVO study." Cerebrovascular Diseases 36.3 (2013): 218-225.
Furlan, Anthony, et al. "Intra-arterial prourokinase for acute ischemic stroke: the PROACT II study: a randomized controlled trial." Jama 282.21 (1999): 2003-2011.
Sacks, David, et al. "Multisociety consensus quality improvement guidelines for intraarterial catheter‐directed treatment of acute ischemic stroke, from the American Society of Neuroradiology, Canadian Interventional Radiology Association, Cardiovascular and Interventional Radiological Society of Europe, Society for Cardiovascular Angiography and Interventions, Society of Interventional Radiology, Society of NeuroInterventional Surgery, European Society of Minimally Invasive Neurological Therapy, and Society of Vascular and ...." Catheterization and Cardiovascular Interventions 82.2 (2013): E52-E68.
Ogawa, Akira, et al. "Randomized trial of intraarterial infusion of urokinase within 6 hours of middle cerebral artery stroke The Middle Cerebral Artery Embolism Local Fibrinolytic Intervention Trial (MELT) Japan." Stroke 38.10 (2007): 2633-2639.
Hacke, Werner, et al. "Thrombolysis with alteplase 3 to 4.5 hours after acute ischemic stroke." New England Journal of Medicine 359.13 (2008): 1317-1329.
Wardlaw, Joanna M., et al. "Thrombolysis for acute ischaemic stroke." The Cochrane database of systematic reviews 7 (2014): CD000213.
Emberson, Jonathan, et al. "Effect of treatment delay, age, and stroke severity on the effects of intravenous thrombolysis with alteplase for acute ischaemic stroke: a meta-analysis of individual patient data from randomised trials." The Lancet384.9958 (2014): 1929-1935.
Question 5 - 2013, Paper 1
One of the serious complications of aneurysmal sub-arachnoid haemorrhage (SAH) is Delayed Cerebral Ischaemia (DCI).
Briefly discuss DCI, including in your answer its assessment and management with reference to accepted and postulated strategies.
College Answer
DCI is a common (occurring in about 30%) and serious complication following SAH. Defined as any neurological deterioration presumed related to ischaemia that persists for more than an hour and cannot be explained by any other physiological abnormalities. It is mostly caused by vasospasm.
May be reversible but may develop into cerebral infarction. Its highest risk of occurrence is from day 3 to 14 after presentation.
Aetiology still poorly understood
Assessment of DCI
Whilst up to 20% of patients can have a cerebral infarct despite being entirely asymptomatic, the mainstay of clinical monitoring is repeated clinical neurological examination.
DSA is the gold standard for vasospasm but as a screening test, multimodal CT imaging with CT perfusion is accurate and less invasive.
Transcranial Doppler has a high specificity but only moderate sensitivity. The other physiological modalities including EEG, brain tissue oxygen monitoring, cerebral microdialysis are less well established as monitoring modalities
Management of DCI
Aim is to prevent or minimise secondary injuries by haemodynamic management, drugs and endovascular procedures.
Haemodynamic strategies
Avoid hypotension.
Triple H therapy:
- Induced hypertension improves CBF independent of blood volume. The most common agents used being Norad and phenylepherine. Secure aneurysm first.
- Hypervolaemia does not offer any benefit over euvolaemia, however it is important to avoid hypovolaemia.
- There is no place for haemodilution except for people with polycythaemia. Milrinone infusion has been used as alternative to Triple H.
Pharmacological management · Calcium-channel blockers
The main intervention shown to be beneficial is the use of Nimodipine.
Other CCBs have been shown to reduce vasospasm with beneficial effects on DCI but RCTs still needed.
· Intra-cisternal thrombolytics
Used in some centres on selected patients · Statins
Evidence is conflicting. Awaiting results of STASH · Magnesium sulphate
MASH-II did not show a benefit compared with placebo · Endothelin-1 antagonists
Recent published studies evaluating clazosentan have shown no clinical benefit
Other agents
E.g. NO donors, EPO, enoxaparin, rho-kinase inhibitor either shown not to be beneficial or still being studied
Endovascular procedures
Angioplasty and/or Intra-arterial vasodilators may be used in addition to nimodipine and haemodynamic management if indicated and expertise available.
Overall optimal triggers for escalating and de-escalating therapy not well defined
Discussion
The discussion of DCI in the college answer is a complete and satisfying summary of the topic.
To make it easier to remember, one can trim some fat.
DCI description:
- Any new neurological deficit
- Occurs on days 3-14
- Can progress to stroke
DCI diagnosis
- Repeat examination is a screening tool with poor sensitivity but little cost.
- DSA is gold standard
- CTA is next best option
- Transcranial Doppler is another option with poor sensitivity
DCI management
- Nimodipine infusion
- Triple H therapy - remains debated;
- hypertension may not be helpful; at least maintain normotension
- hypervolemia may not be helpful; at least maintain normovolemia
- hemodilution is not helpful. Fullstop.
- Intra-arterial vasodilators such as papaverine and verapamil are a good option.
A LITFL review of vasospasm and DCI is a treatment with satisfying levels of detail.
Apocryphal notes on the diagnosis and management of SAH are also available:
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Question 10 - 2013, Paper 1
With respect to the Guillain Barre Syndrome (GBS):
- Outline how you would distinguish between GBS and Critical Illness Polymyoneuropathy (CIP).
- What are the current treatment options in GBS? Briefly outline the supporting evidence
- What is the prognosis of GBS and what factors are associated with a worse outcome?
College Answer
|
GBS |
CIP |
||||||
|
History and |
Recent GI or resp illness. |
Always occurs in association with a critical illness in |
|||||
|
Investigations |
Albuminocytologic dissociation in CSF. |
Elevated CK which may be |
|||||
|
Nerve |
When demyelinating form is |
A axonal neuropathy resulting in a decreased |
|||||
b)
- Plasma exchange and IVIG are both better than no therapy in hastening recovery from an episode and are equally effective. No value in both being given routinely.
c)
- - 5% mortality from medical complications in hospital.
-
-
- Up to 20% of patients are still significantly disabled at 6 months and 15% still have significant functional disability at 1 year.
-
-
- Recurrence rate is 7% with the mean interval between recurrences being 7 years.
- Poor prognosis associated with:
-
- Older age
-
- Rapid onset (<7days) prior to presentation
-
- Severe muscle weakness at presentation
-
- Need for mechanical ventilation
-
- EMG showing average distal motor response amplitude <20% normal
-
- Preceding diarrhoeal illness (proven Campylobacter)
Discussion
The distinctions between GBS and CIPN:
- CIPN is associated with a severe illness, whereas GBS is associated with a mild one.
- CIPN does not have autonomic dysfunction, whereas GBS does.
- CIPN will not have any specific CSF findings, whereas GBS will have raised CSF protein and perhaps even a monocytosis
- CIPN nerve conduction studies will not show any decrease in conduction velocity, whereas in GBS the cardinal feature is decreased conduction velocity.
As for management, Oh's Manual recommends either plasma exchanges or IV immunoglobulin, but there is no benefit in giving both together.
A discussion of the approach to the ICU patient with generalised weakness is available elsewhere.
A generic exam-oriented approach to Guillain Barre syndrome is presented in the "Required Reading" section.
An even better table than the CICM college answer is available in this 2006 article fom Respiratory Care; it is reproduced below.
Critical illness polyneuropathy |
Guillain-Barre |
Critical Illness Myopathy |
|
| Clinical setting |
Sepsis Septic encephalopathy |
Antecedent viral illness Surgery Campylobacter jejuni HIV |
Neuromuscular blocking drugs Corticosteroids Asthma Organ transplant |
| Motor weakness |
Generalised and distal |
Generalised and ascending |
Generalised and proximal |
| Reflexes |
Diminished |
Absent |
Preserved but weak |
| Cranial nerve palsy |
Rare |
Common |
Absent |
| Dysautonomia |
Normal autonomic function |
Frequent dysautonomia |
Normal autonomic function |
| Sensory deficit |
Distal |
Normal sensation, or slightly altered |
Normal sensation |
| CK level |
Normal |
Normal |
Elevated |
| Nerve conduction |
Reduced CMAP and SNAP amplitude (compound muscle action potentials and sensory nerve action potentials) |
Marked slowing, conduction block |
Reduced CMAP amplitude |
| Needle EMG |
Abnormal spontaneous activity Reduced recruitment Large polyphasic motor unit potentials (MUPs) |
Abnormal spontaneous activity Reduced recruitment Normal MUPs (early in disease) |
Minimal spontaneous activity Early recruitment Small polyphasic MUPs; |
| Direct muscle stimulation |
Normal |
Normal |
Absent or reduced |
| Muscle biopsy |
Neuropathic changes |
Neuropathic changes |
Myopathic changes Thick myosin filament loss Muscle fiber necrosis |
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Jani, Charu. "Critical Illness Neuropathy." Medicine (2011): 237.
Dhand, Upinder K. "Clinical approach to the weak patient in the intensive care unit." Respiratory care 51.9 (2006): 1024-1041.
Question 14.1 - 2013, Paper 1
In each part of this question, list clinical examination findings for each of the two underlined conditions that would help you to distinguish between them:
- A myopathy or a neuropathy as being the cause of weakness in all limbs of a patient
College Answer
Myopathy
- Wasting is late sign
- Usually proximal weakness
- Reflexes preserved until late
- Normal sensory exam
- May be muscle tenderness
Neuropathy
- Wasting earlier
- May be fasciculations
- Often peripheral distribution
- Loss of reflexes
- May be abnormal sensory exam
Discussion
This comes down to basic common sense.
If the nerves are healthy, and the muscles are to blame,
- The sensory supply should be preserved
- The reflexes should be preserved
- Weakness should be proximal - that is where the bigger muscles are, and the weakness there will be more obvious.
- There should be no fasciculations
Also...
- There may be myocardial involvement (skeletal myopathies tend to be associated with cadiomyopathy)
- The muscles involved may be painful and tender(as in myositis)
This question has been repeated. Its doppelganger, Question 3.1 from the first paper of 2010, has a much better-organised college answer.
References
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
UpToDate: An approach to the patient with muscle weakness
Young, G. Bryan, and Robert R. Hammond. "A stronger approach to weakness in the intensive care unit." Critical care 8.6 (2004): 416.
Dhand, Upinder K. "Clinical approach to the weak patient in the intensive care unit." Respiratory care 51.9 (2006): 1024-1041.
Question 14.3 - 2013, Paper 1
In each part of this question, list clinical examination findings for each of the two underlined conditions that would help you to distinguish between them:
- Ulnar nerve or lower brachial plexus (C8/T1) injury as the cause of a patient’s hand weakness following prolonged cardiothoracic surgery two days previously.
College Answer
Ulnar nerve injury
- Look for evidence of local trauma
- Weak finger abduction and adduction, and thumb adduction
- Sensory loss over little finger and medial half of ring finger
Lower brachial plexus
- All intrinsic muscles of hand weak (incl. LOAF muscles)
- Sensory loss over little and ring finger, extending above the wrist, and up medial aspect of arm
- Horner’s syndrome
Discussion
This forces the recall of medical school level neuroanatomy.
Particularly, the supply distribution of the brachial plexus
Thus:
Ulnar nerve palsy would be associated with weakness of only the small muscles of the hand, and of sensory loss over the area supplied by its palmar sensory branch (essentially one-and-a-half fingers worth, over the palm).
A brachial plexus C8-T1 injury - also known as Klumpke's paralysis - would result in a "claw hand", with a supinated foream and flexed fingers. The sensory loss would include the whole ulnar nerve distribution - but also the medial cutaneous nerve of the foream.
Lastly, damage to the nerve roots at C8-T1 will also result in a Horners Syndrome, as the ascending sympathetic supply will be interrupted.
References
For a reference, I direct the time-rich reader to Sir Sydney Sunderland's "Nerves and Nerve Injuries", from 1968. (Not available as full text in Google, unfortunately.)
For brachial plexus injuries, I recommend Alain Gilbert's book.
For peripheral nerves, there is Haymaker, Webb, and Barnes Woodhall. Peripheral nerve injuries: principles of diagnosis. Thieme, 1998.
Question 15 - 2013, Paper 1
The following information relates to a patient being cared for in your ICU with an isolated severe traumatic brain injury. The patient is heavily sedated and unresponsive.
A photograph of the patient bed-space and monitor, as well as the ventilator settings, arterial blood gas analysis, and plasma biochemistry results are provided.
Based on these data, what therapeutic interventions would you perform in this patient?
Give your reasons.
Photographs of bed space and monitor omitted.
...From cheating and looking at the answer, one can establish that the photograph depicts a trauma patient lying flat in bed, with a cervical collar on, an ETT fixed with ties, and an EVD drainage bag hanging well above their head.
The monitor displays the following values:
- CPP = 45mmHg
- ICP = 35mmHg
- Temperature = 38.1°
Ventilator Settings:
- SIMV mode
- FiO2 0.3
- Tidal Volume 450ml
- RR 18
- PEEP 5
|
Parameter |
Result |
Normal Adult Range |
|
Barometric pressure |
760 mmHg (100 kPa) |
|
|
pH |
7.38 |
7.35– 7.45 |
|
PCO2 |
45 mmHg (10.5 kPa) |
35–45 (4.6 – 6.0) |
|
PO2 |
100 mmHg (5.0 kPa) |
|
|
Bicarbonate |
26 mmol/L |
22 –27 |
|
Sodium* |
150 mmol/L |
134 – 146 |
|
Potassium |
4.0 mmol/L |
3.4 – 5.0 |
|
Chloride* |
114 mmol/L |
100 – 110 |
|
Urea* |
10.1 mmol/L |
3.0 – 8.0 |
|
Creatinine |
104 µmol/L |
50–120 |
|
Glucose* |
15 mmol/L |
3.0 – 7.0 |
|
Measured osmolality* |
330 mOsm/Kg |
280 – 300 |
College Answer
- Head up – bed currently flat. Elevation to 15-30 degrees may be beneficial for ICP control.
- Remove cervical collar – jugular venous compression may elevate ICP
- Assess ETT ties and if tight replace with alternative fixation method –same rationale
- External ventricular drain is too high – should be lowered
- Drainage of CSF given ICP of 35
- CPP is currently 45. Increase CPP (either by reducing ICP or increasing MAP)
- Consider paralysis; paralysis indicated if patient coughing or posturing and to prevent shivering with temperature control techniques.
- Increase respiratory rate; CO2 is 45 – aim for 35-40mmHg
- Control glucose – hyperglycaemia associated with worse outcome in head injury.
- Temperature is 38.1 – fever associated with elevated ICP; Cool to normothermia initially.
- Consider osmotherapy with hypertonic saline targeting Na+ to 155
Discussion
This question really asks, "how well do you know the Brain Trauma Organisation Guidelines for Management of Traumatic Brain Injury?" This is discussed in detail elsewhere.
It is difficult to make up a specific answer for this without the monitor photograph. From the college answer, one can predict what the picture would have contained.
In any case, whatever the stimulus photograph, the principles are are all the same:
Maintaining cerebral oxygen supply:
- Normoxia: keep the PaO2 above 60 mmHg
- Normotension: measure the MAP, and keep the systolic above 90mmHg
- Intracranial Pressure monitoring: keep it under 20mmHg
- Cerebral perfusion pressure: keep it 50-70mmHg
- Cerebral oxygenation monitoring:keep the SjO2 >50%, and PbrO2 >55mmHg
- Managing increased intracranial pressure for which there is a variety of strategies:
- Draining the EVD ( about 20ml/hr, max)
- Positioning the head straight
- Removing the C-spine collar
- Sedation :
- Propofol sedation to decrease distress and thus decrease ICP
- Barbiturate coma if other methods of lowering ICP have failed
- Analgesia to prevent increased ICP in response to suctioning and routine care
- Paralysis
- Osmotherapy
- Controversial measures
- Decompressive craniectomy
- Hypothermia
- Dexamethasone
Decreasing cerebral oxygen demand:
- Sedation
- Propofol sedation to decrease distress and thus decrease ICP
- Barbiturate coma if medical and surgical methods of lowering ICP have failed
- Analgesia - opioid selection is irrelevant, but opiate boluses increase ICP
- Seizure prophylaxis is infrequently indicated, and the course is 7 days only
Controversial measures:
- Decompressive Craniectomy
- Hypothermia
References
Our beloved Oh's Intensive Care manual has two excellent chapters to dedicate to this topic:
Chapter 43 (pp. 563) Cerebral protection by Victoria Heaviside and Michelle Hayes, and
Chapter 67 (pp. 765) Severe head injury by John A Myburgh.
There are also the Brain Trauma Organisation Guidelines for Management Traumatic Brain Injury, which one might describe as a definitive reference.
It is debatable as to which of these sources is more out of date. At the time of writing, the BTF guidelines have not been updated since 2007. Oh's Manual has undergone a more recent revision, but is not exactly a well-accepted source of guidelines.
Question 2 - 2013, paper 2
Outline the advantages and disadvantages of the various techniques used in the diagnosis and monitoring of vasospasm secondary to aneurysmal subarachnoid haemorrhage.
College Answer
Techniques that have proven or demonstrated potential in the diagnosis and monitoring of
vasospasm include:
Clinical:
In the conscious patient, may be detected clinically by new focal neurology or a drop in GCS. Advantages: No additional costs and readily available, can be repeated easily, non-invasive (usually), has to be performed at the bedside. Major disadvantage is lack of specificity often necessitating CT/angiography. Also lacks sensitivity, vasospasm can occur without a clinical correlate, early in the disease. Operator dependent.
Conventional 4 vessel DSA angiography:
Remains the gold standard for diagnosis of vasospasm.
May allow therapeutic intervention (angioplasty) at the time.
Disadvantages: invasive, risks of bleeding, embolism, radiation/contrast exposure and transport. Requires skilled interventional radiology, and therefore resource heavy. Risk of stroke (quoted about 1%, but probably a little lower) just from the angio, plus the dissections etc. that occur as well.
Detects vessel narrowing, not necessarily poor flow to distal tissue in all cases (either increased flow rate through narrow vessel or collateral supply. May lead to over treatment.
Transcranial Doppler (TCD):
It is low risk, performed at the bedside, non-invasive and able to be repeated daily enabling trend analysis.
Disadvantages:
- The technique is however operator dependent and there is high inter- observer variability.
- Debate exists regarding correlation of flow velocity and vasospasm and although high velocities (> 200cm/sec) are predictive, lower velocity may not be as good.
- The technique may be more accurate when MCA velocity is indexed to the ipsilateral extracranial carotid artery (Lindegaard index, >3 strongly predictive).
- Colour coded TCD may offer greater accuracy than plain TCD alone.
CTA/MRI:
- May be combined with perfusion allowing characterisation of both vascular anatomy and associated perfusion abnormalities.
- MR diffusion weighted imaging accurately identifies brain tissue at high risk of infarction; perfusion weighted imaging reveals asymmetries in regional perfusion.
- Both methods show correlation with delayed ischaemic neurological deficit (DIND).
- Disadvantages:
- Image clarity will be affected by clip/coil and contrast related issues need consideration. The overall diagnostic capability of this modality however remains unclear until further prospective studies are performed. Similar disadvantages as per angiography with respect to transport, radiation (for CT), contrast exposure, interpretation by experts.
- Image clarity will be affected by clip/coil and contrast related issues need consideration. The overall diagnostic capability of this modality however remains unclear until further prospective studies are performed. Similar disadvantages as per angiography with respect to transport, radiation (for CT), contrast exposure, interpretation by experts.
SPECT/PET
- Can be used to obtain a picture of brain perfusion and metabolism and have
shown variable correlation with vasospasm as assessed by more conventional
methods. - Disadvantages: They are resource heavy not easily available, radiation exposure, patient
transport are issues.
EEG:
- May provide prognostic information, focal areas of slowing correlate with angiographic vasospasm and a decrease in alpha to delta ratio strongly correlates with ischaemia. Sensitivity and specificity for detecting vasospasm is high.
Disadvantage: Not readily available however and their may be issues with interpretation.
Tissue sensors:
- The use of measures of tissue oxygenation using parenchymal sensors and microdialysis for
monitoring biochemical indices of ischaemia are largely research tools.
Salient points
- Clinical examination
- DSA
- CTA
- EEG
- Transcranial doppler
- Parenchymal sensors
- SPECT
Discussion
This answer lends itself well to a table format.
| Technique | Advantages | Disadvantages |
| Clinical examination |
|
|
| DSA |
|
|
| CTA |
|
|
|
Transcranial Doppler |
|
|
| EEG |
|
|
| SPECT |
|
|
Apocryphal notes on the diagnosis and management of SAH are also available.
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
Marshall, Scott A., Paul Nyquist, and Wendy C. Ziai. "The role of transcranial Doppler ultrasonography in the diagnosis and management of vasospasm after aneurysmal subarachnoid hemorrhage." Neurosurgery Clinics of North America21.2 (2010): 291-303.
Greenberg, E. D., et al. "Diagnostic accuracy of CT angiography and CT perfusion for cerebral vasospasm: a meta-analysis." American Journal of Neuroradiology 31.10 (2010): 1853-1860.
Sloan, M. A., et al. "Sensitivity and specificity of transcranial Doppler ultrasonography in the diagnosis of vasospasm following subarachnoid hemorrhage." Neurology 39.11 (1989): 1514-1514.
Rivierez, M., et al. "Value of electroencephalogram in prediction and diagnosis of vasospasm after intracranial aneurysm rupture." Acta neurochirurgica 110.1-2 (1991): 17-23.
Question 3.2 - 2013, paper 2
A 64-year-old male has been an in-patient in your Intensive Care Unit for one week following a subarachnoid haemorrhage.
The following data were obtained from a CSF sample taken from the external ventricular drain:
|
Parameter |
Patient Value |
Normal Adult Range |
|
Glucose |
3.8 mmol/L |
2.2 – 3.9 |
|
Protein |
0.46 G/L |
0.15 – 0.5 |
|
White Cell Count |
20x106 /L* |
< 5 |
|
Red Cell Count |
10 000x106 /L* |
< 5 |
Interpret these results.
College Answer
The WCC is elevated but the WCC:RCC ratio is normal (1:500) and represents normal findings after sub-arachnoid haemorrhage but does not exclude infection.
Discussion
This is a faily straightforward data interpretation question. 10,000 / 20 = 500; which is the perfect ratio. This CSF is not infected, it just has blood in it.
Of course, in order to make a more accurate analysis, it would be good to also know the serum WCC, so that one may calculate the proper ratio.
A more detailed discussion of CSF analysis is available elsewhere.
References
Question 6 - 2013, paper 2
Define delirium and describe your management approach to this problem in the ICU.
College Answer
Definition:
The acute onset of a disturbance of consciousness with inattention, changes in cognition and/orperception, that fluctuates over time, occurs as a consequence of a general medical condition and isnot better accounted for by a pre-existing, established or evolving dementia.
Management:
- Early recognition of delirium.
- Stabilise and ensure safety of the patient:
-
- Attend to airway, breathing and circulation issues as required.
- Consider and rule out any potentially life-threatening causes of delirium (comprehensive history and physical examination will provide clues):
-
- Hypoxia
- Hypoglycaemia
- Intra-cerebral haemorrhage
- Meningitis/Encephalitis
- Poisoning
- Wernicke’s Encephalopathy
- Infection: local (wound, anastomotic leaks etc.), UTI, lung etc.
- Withdrawal from drugs
- Hypertensive encephalopathy
- Metabolic derangements – sodium, renal, liver.
- Consider non-pharmacological strategies to control symptoms:
-
- Application of hearing aids, spectacles and dentures if worn.
- Continuous re-orientation of patient - verbal, visual with photographs etc.
- Enlist help of family members and/or interpreters.
-
- Ensure as close to normal as possible sleep/wake cycles in a quiet and calm environment.
- Treat pain, constipation, urinary retention if present.
-
- Check drug chart and beware/attend to poly-pharmacy and cessation of drugs associated with delirium.
- Mobilise early.
- Avoid physical restraints if safe to do so.
- Obtain pharmacological control of symptoms if necessary:
-
- Anti-psychotics are first line agents e.g. haloperidol, olanzepine, quetiapine.
-
- Haloperidol 1-5mg iv q30 PRN. Dose can be doubled and repeated. Beware long QTc.
-
- Benzodiazepines as first line agents for alcohol withdrawal only. Often used in combination with anti-psychotics in difficult to control symptoms in non-alcohol withdrawal delirium.
- Treat cause if found:
- O2, antibiotics, thiamine, glucose, electrolyte replacement, intra-venous fluids if dehydrated.
13
Investigations:
Directed by history, physical examination and differential diagnosis but include/consider;
Basic:
FBC, EUC, Glucose, LFT, ABG, CXR, ECG, Urinalysis + Dipstick, Septic screen, Urinary Drug Screen.
Advanced:
CT Brain, LP, TTE.
Discussion
Delirium is a favourite of the examiners. It is discussed in greater depth elsewhere ("Delirium in the ICU")
In order to simplify revision, I reproduce the salient points here:
The DSM -V diagnostic criteria for delirium:
- Disturbance in attention and awareness.
- Change in cognition
- The disturbance develops over a short period and tends to fluctuate
- There is evidence from the history, physical examination, or laboratory findings that the disturbance is caused by a direct physiologic consequence of a general medical condition, an intoxicating substance, medication use, or more than one cause.
A systematic approach to this question would resemble the following:
Urgently exclude and manage any lifethreatening aetiologies of delirium:
A) - Look for airway compromise due to decreased level of consciousness
B) - Assess for hypoxia and hypercapnea
C) - Assess for hypotension (thus cortial hypoperfusion) or hypertension (thus, hypertensive encephalopathy)
D) - Exclude hypoglycaemia and intoxication or poisoning; investigate for focal intracranial causes of delirium, such as intracranial haemorrhage or space-occupying lesion. Think about non-convulsive status epilepticus as the cause of delirium. Also consider withdrawal from alcohol and other drugs.
E) - Evaluate electrolytess, looking for hyponatremia
F) - Assess renal function, looking for uremia and dehydration
G) - Assess hepatic function, suspecting hepatic encephalopathy. Don't forget Wernicke's.
H) - Assess bone marrow function - cytopenia may be a clue to a space-occupying metastatic lesion, whereas blood film findings such as macrocytosis may suggest a chronic nutritional deficiency associated with alcoholism or IV drug abuse.
I) - Assess temperature, inflammatory markers and features of sepsis, ranging from UTI to septic shock (thinking about septic encephalopathy). Consider neurosyphilis and think about meningitis or encephalitis.
Investigation of delirium:
Stemming from the abovementioned differentials,
- ABG
- Urinalysis
- EUC
- CMP
- FBC
- Blood film
- Inflammatory markers
- CT brain
- EEG
- Lumbar puncture
Management of delirium
Non-pharmacological:
-
- Good analgesia
- Clear and firm communication with the patient
- Frequent re-orientation
- Family presence
- Low-noise environment
- Restoration of hearing aids and spectacles
- Avoidance of sleep disturbance, promotion of normal sleep–wake cycle.
- Avoidance of physical restraints
- Early removal of IV lines and IDCs
Pharmacological:
-
- Dexmedetomidine
- Atypical antipsychotics
- Classical antipsychotics
- Benzodiazepines (if withdrawing from alcohol or benzodiazepines)
References
Oh's Intensive Care manual: Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Girard, Timothy D., Pratik P. Pandharipande, and E. Wesley Ely. "Delirium in the intensive care unit." Critical Care 12.Suppl 3 (2008): S3.
Ely, E. Wesley, et al. "Evaluation of delirium in critically ill patients: validation of the Confusion Assessment Method for the Intensive Care Unit (CAM-ICU)."Critical care medicine 29.7 (2001): 1370-1379.
O'Keeffe, SHAUN T., and JOHN N. Lavan. "Clinical significance of delirium subtypes in older people." Age and ageing 28.2 (1999): 115-119.
Barr, Juliana, et al. "Clinical practice guidelines for the management of pain, agitation, and delirium in adult patients in the intensive care unit." Critical care medicine 41.1 (2013): 263-306.
Ouimet, Sébastien, et al. "Incidence, risk factors and consequences of ICU delirium." Intensive care medicine 33.1 (2007): 66-73.
Girard, Timothy D., et al. "Delirium as a predictor of long-term cognitive impairment in survivors of critical illness." Critical care medicine 38.7 (2010): 1513.
Hopkins, Ramona O., and James C. Jackson. "Long-term neurocognitive function after critical illness." CHEST Journal 130.3 (2006): 869-878.
van den Boogaard, Mark, et al. "Incidence and short-term consequences of delirium in critically ill patients: a prospective observational cohort study."International journal of nursing studies 49.7 (2012): 775-783.
Stevens, Robert D., Karin J. Neufeld, and Tarek Sharshar. "Delirium in the ICU: time to probe the hard questions." Crit Care 15.1 (2011): 118.
van Boogaard, M., et al. "Development and validation of PRE-DELIRIC (PREdiction of DELIRium in ICu patients) delirium prediction model for intensive care patients: observational multicentre study." BMJ: British Medical Journal344 (2012).
Van Rompaey, Bart, et al. "Risk factors for intensive care delirium: a systematic review." Intensive and Critical Care Nursing 24.2 (2008): 98-107.
Schweickert, William D., et al. "Early physical and occupational therapy in mechanically ventilated, critically ill patients: a randomised controlled trial."Lancet (London, England) 373.9678 (2009): 1874-1882.
Skrobik, YoannaK, et al. "Olanzapine vs haloperidol: treating delirium in a critical care setting." Intensive care medicine 30.3 (2004): 444-449.
Milbrandt, Eric B., et al. "Haloperidol use is associated with lower hospital mortality in mechanically ventilated patients*." Critical care medicine 33.1 (2005): 226-229.
Moots, R. J., et al. "Old drug, new tricks: haloperidol inhibits secretion of proinflammatory cytokines." Annals of the rheumatic diseases 58.9 (1999): 585-587.
Page, Valerie J., et al. "Effect of intravenous haloperidol on the duration of delirium and coma in critically ill patients (Hope-ICU): a randomised, double-blind, placebo-controlled trial." The Lancet Respiratory Medicine 1.7 (2013): 515-523.
Gilchrist, Neil A., Ifeoma Asoh, and Bruce Greenberg. "Atypical antipsychotics for the treatment of ICU delirium." Journal of intensive care medicine 27.6 (2012): 354-361.
Jasiak, Karalea D., et al. "Evaluation of discontinuation of atypical antipsychotics prescribed for ICU delirium." Journal of pharmacy practice 26.3 (2013): 253-256.
Inouye, Sharon K., et al. "A multicomponent intervention to prevent delirium in hospitalized older patients." New England journal of medicine 340.9 (1999): 669-676.
Girard, Timothy D., et al. "Efficacy and safety of a paired sedation and ventilator weaning protocol for mechanically ventilated patients in intensive care (Awakening and Breathing Controlled trial): a randomised controlled trial." The Lancet 371.9607 (2008): 126-134.
Mehta, Sangeeta, et al. "Daily sedation interruption in mechanically ventilated critically ill patients cared for with a sedation protocol: a randomized controlled trial." JAMA 308.19 (2012): 1985-1992.
Devlin, John W., et al. "Efficacy and safety of quetiapine in critically ill patients with delirium: A prospective, multicenter, randomized, double-blind, placebo-controlled pilot study*." Critical care medicine 38.2 (2010): 419-427.
Kim, Sung‐Wan, et al. "Risperidone versus olanzapine for the treatment of delirium." Human Psychopharmacology: Clinical and Experimental 25.4 (2010): 298-302.
Grover, Sandeep, Vineet Kumar, and Subho Chakrabarti. "Comparative efficacy study of haloperidol, olanzapine and risperidone in delirium." Journal of psychosomatic research 71.4 (2011): 277-281.
Yoon, Hyung-Jun, et al. "Efficacy and safety of haloperidol versus atypical antipsychotic medications in the treatment of delirium." BMC psychiatry 13.1 (2013): 1-11.
Question 10.1 - 2013, paper 2
a) What are the clinical features of Horner’s syndrome?
b) What additional features are associated with lateral medullary syndrome?
College Answer
a) Horner’s syndrome:
-
- Ptosis
- Miosis
- Anhidrosis
- Enophthalmos
b) Lateral Medullary Syndrome:
- Horner’s Syndrome as well as
- Nystagmus
- Ipsilateral V, IX and X cranial nerve lesions
- Ipsilateral cerebellar signs
- Contralateral pain and temperature (spinothalamic) loss over the trunk and limbs
Discussion
Horner's syndrome (the four features mentioned above) is not a problem to remember.
The lateral medullary syndrome, however, is somewhat more taxing on the neurons.
Thankfully, strokecentre.org has an excellent resource for identification (and explanation) of stroke syndrome features. This is their entry on the Lateral Medullary Syndrome (Wallenberg Syndrome)
The best way to memorise lateral medullary syndrome features would be to remember the ipsilateral Horners and the contralateral pain and temperature loss. The word "medullary" should dredge up one's recollection of medullary cranial nerve nuclei, of which nerves 5 9 and 10 are involved.
References
Question 21.1 - 2014, Paper 1
Name the dermatomes indicated by the letters A to H and L to R in the figure below.

College Answer
|
A = C4, B = C5, C = T3, D = T2, E = C6, F = T1, G = C7, H = C8, |
L = C4, M = T2, N = C5, O = T1, P = C6, Q = C8, R = C7 |
Discussion
Dermatome distribution seems something that one might expect to see as a part of the ACEM primary. Perhaps this is why the college examiners have decided to spring this on their candidates.
It is difficult to enter into an indepth discussion of such a question. For the purpose of reference, an excellent dermatome map can be found at www.apparelyzed.com.
For the time-poor candidate, a reference of dermatome and myotome maps has been stolen shamelessly from Wikipedia, and posted here at the Required Reading section.
References
For a more detailed look, one can see the textbook "Neurosurgical Classics".
Foerster, O. "The dermatomes in man." Neurosurgical Classics (1992): 129. Best viewed in this Googlebook.
Question 21.2 - 2014, Paper 1
For each of the following three clinical photographs, name the side of the lesion and the cranial nerve/s involved.

College Answer
(a) Left Glossopharyngeal (IX) cranial nerve.
(b) Right Hypoglossal (XII) cranial nerve.
(c) Left Facial (VII) and Left Abducens (VI) nerves.
Discussion
The college loves gaze palsies. And cranial nerve lesions in general.
a) demonstrates a deviated uvula. This results from palatine paralysis: the pharyngeal muscles on the affected side are weaker, and the tonic contraction of the muscles on the healthy side effects an unopposed pull on the uvula, causing it to deviate away from the lesion.The college has described this as a glossopharyngeal nerve palsy. However, as one of the more clever readers has pointed out, the motor innervation of the the palate muscles is in fact mainly supplied by the pharyngeal branches of the vagus nerve, specifically the branchial motor fibres (so called because their corresponding relatives in fish innervate the gill arches). These are the main muscles which elevate the palate when the patient says "Aaah". The only palatine muscle innervated by the glossopharyngeal nerve is the stylopharyngeus, which stretches between the styloid process and the pharynx and therefore may not have much of a role in moving the uvula. This correction of the college answer is offered with the caveat that even highly detailed explorations of these cranial nerves (eg. Clinical Anatomy of the Cranial Nerves by Paul Rea, p. 105-116) allow that both vagus and glossopharyngeal nerves are being tested by the "Aah" deviated uvula test, and that isolated lesions of one nerve without the other are virtually unknown. As such, here and elsewhere descriptions of CN IX and X lesions are grouped together.
| Cranial nerves | Lesions | |
CN IX and X:Glossopharyngeal and Vagus |
These two are usually tested (and described) together because isolated lesions of one but not the other are essentially unknown.
Obvious features
Subtle features
and, via the vagus...
|
|
|
Unilateral loss of the obvious features
|
Bilateral loss of the obvious features
|
|
b) demonstrates a tongue the right side of which has been affected by chronic muscle wasting, as occurs with denervation. Only a hypoglossal nerve lesion can give this appearance.
| Cranial nerves | Lesions | |
CN XII: Hypoglossal |
Expected features
The "central" supranuclear lesions tend to cause mild and transient weakness, because the hypoglossal nerve nuclei receive bilateral cortical input. Hemispheric lesions rarely cause a clinically important CN XII palsy. Nuclear lesions are frequently bilateral: there is little space in the medulla, and the nucli are close together. |
|
|
Supranuclear lesions
|
Nuclear and peripheral lesions
|
|
c) demonstrates an eye which cannot abduct past midline (an abducens nerve palsy). This is weird, because Question 21.3 (the very next question) goes on to ask about this in greater detail. To simplify revision, the abducens nerve table is reproduced below:
| Cranial nerves | Lesions | |
CN VI: Abducens |
Expected features

|
|
|
Unilateral lesion:
|
||
|
Bilateral lesion:Freakishly rare
|
||
Finally, the last picture presents a mouth apparently smiling with only the right side. This is characteristic of a seventh nerve palsy.
| Cranial nerves | Lesions | |
CN VII: Facial |
Obvious features
Subtle features

|
|
|
Unilateral lesion:
|
Central (forehead-sparing) lesions:
|
|
|
Bilateral lesion:Freakishly rare in isolation
Obviously, the facial nerve forms the efferent component of the corneal reflex, and a bilateral absence of the corneal reflex is to be expected in the context of braindeath. |
||
References
The LITFL summary of cranial nerve lesions is without peer in terms of useful information density.
Lapresle, J., and P. Lasjaunias. "CRANIAL NERVE ISCHAEMIC ARTERIAL SYNDROMES A REVIEW." Brain 109.1 (1986): 207-215.
Walker, H. Kenneth, W. Dallas Hall, and J. Willis Hurst. "Clinical methods." (1990).
Question 21.3 - 2014, Paper 1
This patient has been instructed to look to her left (image A) and then to her right (image B).

(a) Name the phenomenon observed.
(b) List two possible locations for the lesion associated with this observation.
(c) If this patient were also hemiplegic, which side would be paralysed?
College Answer
(a) Horizontal gaze palsy (right)
(b) Any two:
Frontal eye field
Posterior hemispheric lesion
Pre-pontine Reticular Formation (PPRF)
Abducens (VI) nerve nucleus
(c) Right sided paralysis.
Discussion
The college loves gaze palsies. And cranial nerve lesions in general.
To answer this specific question, I resorted to the free-ish copy of "Fundamentals of Neurology: An Illustrated Guide" by Mattle and Mumenthaler, available via Google Books. Horisontal gaze palsies are dealt with on page 188.
The specific disturbance is an abducens nerve palsy - the affected eye cannot abduct past midline. Judging by the college answer, the palsy is unilateral. Causes of a unilateral 6th nerve palsy include the following:
- Head injury (most common) with BOSF
- Raised intracranial pressure
- Localising lesion.... at any number of levels:
- Damage to the frontal eye field of the frontal lobe, which occupies some of the middle frontal gyrus
- Damage to the posterior hemispheres, which would be accompanied by a hemianopia
- Brainstem (tumour, stroke) - the paramedian prepontine reticular formation mentioned in this question, which receives information from higher cortical centres and transmits them to the abducens nucleus.
- Petrous portion of temporal bone (otitis media-associated osteomyelitis, mastoiditis)
- Clivus (intraforaminal extension of nasopharyngeal carcinoma or similar)
- Cavernous sinus (thrombosis)
- Superior orbital fissue (base of skull fracture)
- Any damn where (basal forms of meningitis, eg sarcoidosis, tuberculosis, cryptococcus)
The college then claims that the hemiplegic side is ipsilateral to the horisontal gaze palsy. This is weird. The damage to the brainstem should be at the level of the pons, and therefore the hemiplesia should be contralateral. An excellent 2013 article by Azarmina et al ("The Six Syndromes of the Sixth Cranial Nerve") discusses the various diffuse and focal ways in which the sixth nerve can be damaged. All the pyramidal signs are contralateral in these scenarios.
CN IV: Abducens |
Expected features
|
|
|
Unilateral lesion:
|
||
|
Bilateral lesion:Freakishly rare
|
||
The table below is a fragment of the greater Table of Conjugate Gaze Palsies. It may also be helpful in localising this lesion.
Disorder |
Clinical features |
Location of lesion |
Possible causes |
| Horisontal gaze palsies |
|
|
|
|
|
|
|
|
|
|
|
References
The LITFL summary of cranial nerve lesions is without peer in terms of useful information density.
Lapresle, J., and P. Lasjaunias. "CRANIAL NERVE ISCHAEMIC ARTERIAL SYNDROMES A REVIEW." Brain 109.1 (1986): 207-215.
Walker, H. Kenneth, W. Dallas Hall, and J. Willis Hurst. "Clinical methods." (1990).
Question 25 - 2014, Paper 1
Examine the single slice non-contrast CT image, depicted below, of a 58-year-old male who was brought to the Emergency Department with a headache. He was not on any medication.

a) Name the structures labelled A- E.
b) Describe lesion F as you would on the phone to a neurosurgical colleague.
c) Give three pathological causes for F.
A day after the CT scan the patient's Glasgow Coma Scale drops from 13 to 10.
d) Give three possible intracranial causes for this.
e) List five validated features affecting prognosis for patients with F.
College Answer
a)
A Left frontal cortex
B Caudate nucleus
C Top of quadrigeminal cistern (not 3rd or 4th ventricle)
D Septum pellucidum
E Posterior horn of left lateral ventricle
b)
'Acceptable' answer:
There is a hyperdensity in keeping with an intracerebral haematoma in the right frontoparietal region with midline shift and surrounding oedema.
c)
Hypertensive haemorrhage.
AV malformation.
Haemorrhagic transformation of ischaemic stroke.
Bleed into tumour.
(No evidence of subarachnoid haemorrhage).
d)
Expanding haematoma / Worsening oedema / mass effect.
Seizure (including non-convulsive).
Hypdrocephalus due to obstruction of ventricles.
e)
The features included in the intracerebral haemorrhage score are:
Age: < 80 or > 80
GCS: on transfer from the ED to definitive to care.
Location of bleed: supra vs infra tentorial.
Volume of Bleed: < 30 mL or > 30 mL.
Intraventricular extension of haemorrhage.
Discussion
The image above is not the gospel CICM image, but was stolen shamelessly from a 2009 article by Jae-Suk Park et al.
The answers to a), b), c) and d) should be a part of an ICU trainee's reptilian hindbrain activity.
If one's cross-sectional neuroanatomy was for some reason sub-optimal, one could pay a visit to the excellent wikiradiography Head CT page.
Differential explanations for "a hyperdensity in keeping with an intracerebral haematoma" are:
- Intracerebral haematoma, due to
- Hypertension
- Potentially associated with abuse of stimulants, eg.cocaine
- Amyloid angiopathy
- Arteriovenous malformation
- Intracranial aneurysm (though there is no subarachnoid blood)
- Cavernous angioma
- Venous angioma
- Dural venous sinus thrombosis
- Haemorrhage into the intracranial neoplasm
- Haemorrhage into an ischaemic stroke (haemorrhagic transformation)
- Vasculitis
- Hypertension
This list of differentials was retrieved from an excellent 2001 NEJM article by Adnan Qureshi.
The college then asks for five validated features which affect prognosis. Fortunately, an article titled"Development and validation of the Essen intracerebral haemorrhage score" can rescue us from wondering what hidden meaning the College had concealed within the remark I italicised. Presumably, the examiner behind it is also aware of, and perhaps is mildly annoyed by, several published prognostic features for ICH which are completely unvalidated.
The specific scoring system referred to in the official model answer was probably the modified Essen ICH score rather than the original ICH score. One can view the original system here and Essen scoring system here. Detailed familiarity with them is not essential; however one should recall that the following variables suggest a poor prognosis:
- Age over 80
- A high NIH-SS score (National Institutes of Health stroke scale)
- GCS (3-4)
- Volume of blood exceeding 30ml (30cm2)
- Infratentorial origin
- Intraventricular extension of haemorrhage
References
Park, Jae-Suk, et al. "Remote cerebellar hemorrhage complicated after supratentorial surgery: retrospective study with review of articles." Journal of Korean Neurosurgical Society 46.2 (2009): 136-143.
Qureshi, Adnan I., et al. "Spontaneous intracerebral hemorrhage." New England Journal of Medicine 344.19 (2001): 1450-1460.
Hemphill, J. Claude, et al. "The ICH score a simple, reliable grading scale for intracerebral hemorrhage." Stroke 32.4 (2001): 891-897.
Weimar, Christian, Jens Benemann, and H. C. Diener. "Development and validation of the Essen intracerebral haemorrhage score." Journal of Neurology, Neurosurgery & Psychiatry 77.5 (2006): 601-605.
Rost, Natalia S., et al. "Prediction of Functional Outcome in Patients With Primary Intracerebral Hemorrhage The FUNC Score." Stroke 39.8 (2008): 2304-2309.
Garrett, John S., et al. "Validation of Clinical Prediction Scores in Patients with Primary Intracerebral Hemorrhage." Neurocritical care 19.3 (2013): 329-335.
Question 27 - 2014, Paper 1
A 59-year-old male is admitted to the ICU following a severe traumatic brain injury
sedated, intubated and ventilated.
a) List the arguments for and against intracranial pressure (ICP) monitoring in this
patient.
b) Explain the term "secondary brain injury" and list the steps to avoid this.
College Answer
a)
For:
- This patient has about a 50 – 60% chance of developing raised ICP.
- It is critical that CPP is maintained and to know the CPP need to know the ICP.
- ICP is a strong predictor of outcome after severe TBI.
- Several studies have shown substantial lowering of mortality after ICP monitoring and
control was introduced.
- Numerous studies have also shown that patients who respond to ICP-lowering therapies
have a lower mortality compared to those who don't, allowing some prognostication.
- Internationally accepted BTF Guidelines advise ICP monitoring in patients with severe
TBI (GCS < 9) and an abnormal CT scan.
- Doesn't lead to greater intensity of treatment or ICU LOS compared to no ICP
- If EVD allows CSF drainage and analysis.
- Early diagnosis of secondary surgically correctable lesion e.g.: delayed subdural
haematoma.
Against:
- Risks associated with brain injury associated coagulopathy.
- Other risks – infection, false readings and risks of avoidable interventions (osmotherapy,
falsely elevating CPP, deep sedation).
- BEST TRIPPS study showing no difference in outcome.
- May require transfer to OT for insertion.
b)
- Secondary injury occurs at any time after the primary injury, and thus should theoretically
be preventable and is caused primarily by:
o Hypoxia
Ensure a PaO2 > 80 and/or SpO2 > 92%
o Hyper/hypocarbia
PaCO2 35 - 40mmHg
o Hypotension
SBP > 90 mmHg and/MAP > 70 mmHg / CPP > 50 mmHg
o Metabolic disturbance (Na, glucose, osmo)
Na+ of 140 – 150 mmol/L, glucose 6 – 10, Serum osmo 320 mOsm/L
o Fever
Normothermia
o Seizures
Phenytoin x 72hrs
o Raised ICP
ICP lowering therapy (head up 30o, neck neutral alignment, sedation and
paralysis, osmotherapy, drain CSF, surgical decompression)
o Secondary surgical lesion (delayed subdural/parenchymal haemorhage)
Repeat CT, surgical therapy
Discussion
a) is a list of arguments for and against ICP monitoring. The debate about indications for intracranial pressure monitoring (strictly, whether there are any) is discussed in the Required Reading section.
To simplify revision, and because the author has succumbed to sloth, large greyish boxes have been lifted from that section and planted here with zero modification.
|
|
A precise definition of "secondary brain injury" is remarkably difficult to find, as occurs often with frequently used terminology of which everybody has some assumed intuitive understanding. Go on everyone, define "injury" in general. The college, in its model answer, does not define the term, but rather frames it in terms of problems and solutions.
Prevention of secondary brain injury - colloquially referred to as "neurprotective measures" - is discussed elsewhere, both as a brief summary and as a rambling dialogue. Salient points from the brief summary are lazily pasted below.
Goals of management, in summary:
Maintaining cerebral oxygen supply:
- Normoxia: keep the PaO2 above 60 mmHg
- Normotension: measure the MAP, and keep the systolic above 90mmHg
- Intracranial Pressure monitoring: keep it under 20mmHg
- Cerebral perfusion pressure: keep it 50-70mmHg
- Cerebral oxygenation monitoring:keep the SjO2 >50%, and PbrO2 >55mmHg
- Managing increased intracranial pressure for which there is a variety of strategies:
- Draining the EVD ( about 20ml/hr, max)
- Positioning the head straight
- Removing the C-spine collar
- Sedation :
- Propofol sedation to decrease distress and thus decrease ICP
- Barbiturate coma if other methods of lowering ICP have failed
- Analgesia to prevent increased ICP in response to suctioning and routine care
- Paralysis
- Osmotherapy
- Controversial measures
- Decompressive craniectomy
- Hypothermia
- Dexamethasone
Decreasing cerebral oxygen demand:
- Sedation
- Propofol sedation to decrease distress and thus decrease ICP
- Barbiturate coma if medical and surgical methods of lowering ICP have failed
- Analgesia - opioid selection is irrelevant, but opiate boluses increase ICP
- Seizure prophylaxis is infrequently indicated, and the course is 7 days only
Controversial measures:
- Decompressive Craniectomy
- Hypothermia
References
Our beloved Oh's Intensive Care manual has two excellent chapters to dedicate to this topic:
Chapter 43 (pp. 563) Cerebral protection by Victoria Heaviside and Michelle Hayes, and
Chapter 67 (pp. 765) Severe head injury by John A Myburgh.
However, the discerning reader will recognise this book as an antique, and look instead to the frequently updated Brain Trauma Organisation Guidelines for Management of Traumatic Brain Injury.
Narayan, Raj K., et al. "Intracranial pressure: to monitor or not to monitor? A review of our experience with severe head injury." Journal of neurosurgery 56.5 (1982): 650-659.
Forsyth, Rob J., Susanne Wolny, and Beryl Rodrigues. "Routine intracranial pressure monitoring in acute coma." Cochrane Database Syst Rev 2 (2010).
Badri, Shide, et al. "Mortality and long-term functional outcome associated with intracranial pressure after traumatic brain injury." Intensive care medicine 38.11 (2012): 1800-1809.
Farahvar, Arash, et al. "Increased mortality in patients with severe traumatic brain injury treated without intracranial pressure monitoring: Clinical article."Journal of neurosurgery 117.4 (2012): 729-734.
Chesnut, Randall M., et al. "A trial of intracranial-pressure monitoring in traumatic brain injury." New England Journal of Medicine 367.26 (2012): 2471-2481.
Farahvar, Arash, et al. "Response to intracranial hypertension treatment as a predictor of death in patients with severe traumatic brain injury: Clinical article."Journal of neurosurgery 114.5 (2011): 1471-1478.
Meythaler, Jay M., et al. "Current concepts: Diffuse axonal injury - associated traumatic brain injury." Archives of physical medicine and rehabilitation 82.10 (2001): 1461-1471.
Tasker, R. C., et al. "Monitoring in non-traumatic coma. Part I: Invasive intracranial measurements." Archives of disease in childhood 63.8 (1988): 888-894.
Cremer, Olaf L., et al. "Effect of intracranial pressure monitoring and targeted intensive care on functional outcome after severe head injury*." Critical care medicine 33.10 (2005): 2207-2213.
Question 2 - 2014, paper 2
A 42-year-old male presented with a stroke. He was admitted to a general ward with a right sided hemiplegia, neglect and speech deficits. The day following admission, you are called to the ward because the patient has just become drowsy, and is no longer following commands. The team has performed a CT scan of the head and this shows extensive left middle cerebral artery territory infarction, with no haemorrhage, and early evidence of raised intracranial pressure.
a) Outline your initial plan of management. The family asks if there is any surgical option to “save” the patient.
b) What is the evidence for surgery in this situation, and how would you advise the family?
College Answer
a) The patient should be admitted to an intensive care or stroke unit for close monitoring and comprehensive treatment.
Transfer to a higher level centre is reasonable if comprehensive care and timely neurosurgical intervention is not available locally.
Maintain SpO2 >95% - any safe comments or values.
Intubate if usual concerns regarding airway protection in neurologically impaired patient.
“Safe” blood pressure (Extreme hypertension associated with haemorrhagic transformation.
Concerned about malignant brain swelling with possible temporal herniation and the need to reduce the space occupying effects of that swelling.
a) Elevate the head of the bed to 30°.
b) Do not hyperventilate PaCO2 35-40 mmHg
c) Increase levels of sedation +/- paralysis:
d) Barbiturate infusion – option, but not advocated in guidelines.
e) Osmotic therapy:
a. 3% Saline 100-200mL aliquots; Na+ ≤155mmol/L
b. Mannitol 0.5-1.0g/kg
c. Aim for serum Osm 300-320mOsm/L
f) Target normoglycaemia
g) Hypothermia- temperature 35-36.5oC
a. Prospective randomized studies are currently underway to further evaluate therapeutic hypothermia in patients with cerebral infarcts.
b) Evidence
a. Three prospective, randomized trials (i.e. DESTINY, DECIMAL and HAMLET)
- Supratentorial infarctions treated with decompressive craniectomy, usually within 48
hours of stroke onset. Age <60. Older populations being currently studied. - With hemicraniectomy compared with medical management:
- Reduced mortality (22% versus 71% - pooled analysis)
- No individual study showed an improvement in the percentage of survivors with good outcomes (mRS score, 0–3),
- Only shown in a pooled analysis (43% versus 21%).
- Only 14% of surgical survivors could look after their own affairs without assistance (mRS score, 2)
Note:
Names / excessive detail of studies not expected
Advice
I. The patient’s age <60 fits the studies’ inclusion criteria
II. Decompressive craniectomy for supratentorial infarction with swelling results in a
reproducible large reduction in mortality.
- But mortality after large ischaemic strokes with cerebral oedema remains between 20% & 30% despite medical and surgical interventions.
- Nearly all post-surgery survivors suffer residual permanent disabilities:
- One half are severely disabled
- A third are fully dependent on care
- 50% will suffer from depression
III. There may be a discrepancy between physical disability and quality of life, with many patients and families rating a good quality of life despite severe functional handicap. Ultimate advice and decisions will be based on a balance between survival and level of disability.
Additional Examiners’ Comments:
Candidates did not accurately read the question. Answers re advice to the family were not at the required level of sophistication.
Discussion
A systematic approach is called for.
a) is a question regarding the generic management of raised intracranial pressure, as well as the general supportive management of acute stroke, which are topics well discussed elsewhere.
The brief point-form summary of management recommendations offered below is based completly on the 2014 AHA/ASA guidelines - "Recommendations for the Management of Cerebral and Cerebellar Infarction With Swelling".
Admin) - The availability of a specialist acute stroke unit improves mortality and outcome; admission to ICU does not (perhaps the opposite)
A) - intubate them to protect from aspiration (though it does not improve outcome)
B) - Ventilate aiming for a CO2 ~35mmHg (no evidence for or against hyperventilation, but the guidelines statements tend to recommend a normal CO2)
C) - Tolerate a systolic blood pressure under 220mmHg systolic, or 120mmHg diastolic. (the evidence for this is also not very robust)
D) - There does not seem to be any point in monitoring the ICP. Rarely is the intracranial pressure raised. If it were truly raised, the usual armamentarium of methods can be deployed.
E) Control hypeglycaemia, but not aggressively - tolerate borderline-high normoglycaemia.
F) Ensure normovolaemia and good hydration.
G) Ensure adequate nutrition, preferably by the enteric route.
H) No evidence to support the use of heparin infusion.
I) no strong evidence to support the use of therapeutic hypothermia.
b) The evidence for surgery (i.e. decompressive craniectomy in malignant MCA syndrome) is discussed in detail elsewhere. In brief, the college model answer refer to three landmark studies:
- A fourth could be mentioned: DESTINY II Trial (2014)
A pooled analysis of the first three studies is available, including 93 patient cases.
"...after decompressive surgery the probability of survival increases from 28% to nearly 80% and the probability of survival with an mRS of ≤3 doubles."
(mRS of 3 here being the score of the modified Rankin scale, equating to a disability where one requires some help, some of the time, with some things - but is otherwise able to walk unassisted).
For advice to the family, the college quotes the AHA/ASA guidelines verbatim (see page 10):
- "Decompressive craniectomy ... results in a reproducible large reduction in mortality, but nearly all survivors suffer residual permanent disabilities."
- "No individual study showed an improvement in the percentage of survivors with good outcomes"
- "Only 14% of surgical survivors could look after their own affairs without assistance"
References
Oh's Intensive Care manual : Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer.
Torbey, Michel T., et al. "Evidence-Based Guidelines for the Management of Large Hemispheric Infarction." Neurocritical care (2015): 1-19.
Wartenberg, Katja E. "Malignant middle cerebral artery infarction." Current opinion in critical care 18.2 (2012): 152-163.
Yang, Ming-Hao, et al. "Decompressive hemicraniectomy in patients with malignant middle cerebral artery infarction: A systematic review and meta-analysis." The Surgeon (2015).
Jüttler, Eric, et al. "Decompressive surgery for the treatment of malignant infarction of the middle cerebral artery (DESTINY) a randomized, controlled trial." Stroke 38.9 (2007): 2518-2525.
Jüttler, Eric, et al. "DESTINY II: DEcompressive Surgery for the Treatment of malignant INfarction of the middle cerebral arterY II." International Journal of Stroke 6.1 (2011): 79-86.
Vahedi, Katayoun, et al. "Sequential-design, multicenter, randomized, controlled trial of early decompressive craniectomy in malignant middle cerebral artery infarction (DECIMAL Trial)." Stroke 38.9 (2007): 2506-2517.
Hofmeijer, Jeannette, et al. "Surgical decompression for space-occupying cerebral infarction (the Hemicraniectomy After Middle Cerebral Artery infarction with Life-threatening Edema Trial [HAMLET]): a multicentre, open, randomised trial." The Lancet Neurology 8.4 (2009): 326-333.
Vahedi, Katayoun, et al. "Early decompressive surgery in malignant infarction of the middle cerebral artery: a pooled analysis of three randomised controlled trials." The Lancet Neurology 6.3 (2007): 215-222.
Slotty, Philipp Jörg, et al. "The influence of decompressive craniectomy for major stroke on early cerebral perfusion." Journal of neurosurgery (2015): 1-6.
Barroso, Bruno. "Decompressive craniectomy for stroke after intravenous thrombolytic therapy." International Journal of Stroke 9.8 (2014): E40-E40.
Wijdicks, Eelco FM, et al. "Recommendations for the Management of Cerebral and Cerebellar Infarction With Swelling A Statement for Healthcare Professionals From the American Heart Association/American Stroke Association." Stroke 45.4 (2014): 1222-1238.
Jüttler, Eric, et al. "Hemicraniectomy in older patients with extensive middle-cerebral-artery stroke." New England Journal of Medicine 370.12 (2014): 1091-1100.
Question 16 - 2014, paper 2
A 53-year-old male presents to the Emergency Department with headache and vomiting. He has a left hemiparesis and has a Glasgow Coma Scale score of 5. Soon after presentation he is seen to have a tonic clonic seizure.
a) Outline your priorities for the management of this seizure. Include approximate dosing for any drugs you might use.
After 30 minutes the seizure is terminated and the patient is intubated and paralysed and sent for CT brain that confirms high-grade sub-arachnoid haemorrhage. On return to ICU the neurosurgeon asks you to “lighten” the patient for assessment. On reducing sedation, further seizure activity is noticed. This happens on 3 occasions.
b) Describe your approach to this problem.
c) Describe when and how you would cease sedation in this patient.
d) Using the information given above, give an assessment of this patient’s prognosis.
College Answer
a)
1. ABC+monitoring; BSL; Thiamine;
2. Cease the seizure
i. Clonazepam 0.01–0.02 mg/kg
ii. Midazolam 0.1 mg/kg or 2-5 mg boluses
iii. Or similar/reasonable alternative
3. Prevent further seizures
iv. Phenytoin 20 mg/kg @ max 50 mg/min
v. Valproate: 15–20 mg/kg IV
vi. Levetiracetam: 500–2000 mg depending on renal function
vii. Or other reasonable choice
b)
Should recognize this is status epilepticus: defined as a continuous state of seizures, or multiple
seizures, without return to baseline, resulting in observable or even subjectively perceived sensory,
motor, and/or cognitive dysfunction for at least 30 minutes. Other definitions exist so whatever is
reasonable.
Involvement with neurosurgeons for reversible factors.
Further benzodiazepine or similar → infusion
Propofol IV: loading dose: 1–5 mg/kg; infusion rate: 1–15 mg/kg/hr
Other agents – e.g. barbiturates if available
Early EEG monitoring to clarify seizure and confirm cessation (i.e. that a non-convulsive state is not
present).
Avoid muscle relaxants.
c)
Reduction of sedative medication needs to be discussed as a potentially difficult situation.
Balance of determining neurological function against the return of a convulsive or non-convulsive
state.
Continuous EEG monitoring should be discussed in this patient due to the prolonged, difficult to
control and recurrent seizures.
Timings and how medications are reduced needs to be logically explained and must be gradual.
Therapeutic drug monitoring to confirm phenytoin levels are in the therapeutic range
d)
Outcome after status epilepticus is determined primarily by the aetiology.
Relating to the Sub-arachnoid haemorrhage: High grade sub-arachnoid haemorrhage based on
Hunt & Hess; World federation of neurosurgeons & Fisher grading scales.
Relating to the fitting: status epilepticus secondary to the SAH infers a poorer prognosis. Various
series quote 20-35% “all comers” in this age group. A discussion should include the contribution and guarded prognosis from the SAH and coupled with this the status epilepticus prognosis.
Discussion
This question on status epilepticus differs from the others by its request for some information about prognosis. Status epilepticus is discussed elsewhere, both as a brief summary and as an extensive digression. From those chapters, the tabulated summary of management can be cut-and-pasted:
First line therapy |
|
Second line therapy |
|
Refractory status |
|
The college expects the trainees to recognise that this is status epilepticus; the definition they offer is slightly different to the recent Neurocritical Care Society Guidelines definition
("5 minutes or more of continuous seizure activity, or two seizures with no intervening recovery of consciousness").
But they do allow "whatever's reasonable", so that is ok.
Weaning sedation in status epilepticus
The reduction in sedation (presumably a sedating infusion) in this patient will be coming on the coat-tails of three previous such attempts, which were unsuccessful. Thinking seriously about this, one would have to come to the conclusion that there is some sort of decreased seizure threshold here, which the patient crosses in the course of surfacing from anaesthesia. The solution to this could include the following measures:
- Continuous EEG monitoring to commence while still sedated.
- Confirmation of appropriate therapeutic drug levels
- Confirmation of unchanged CT appearance (is there some sort of new pathology?)
- Consultation with neurology specialist, and commencement of synergistic antiepileptics
- Then, when everything is ready, a gradual decrease of sedation can be commenced.
- With continuous EEG monitoring, antiepileptic therapy and sedation can be cross-titrated until the patient is only on anti-epileptics, and all the sedation is ceased.
Outcomes of status epilepticus
As the college politely point out, the outcome is strongly related to the aetiological cause. For instance, the glioblastoma multiforme has a very diffent prognosis to the viral meningoencephalitis. That said, status epilepticus has a certain pathophysiological influence on the outcome, as it too is associated with some neurological damage.
The following table is an abridgement of the far better table available in the 2012 Guidelines for Management of Status Epilepticus.
Status Epilepticus |
Mortality:
|
|
Non-convulsive status |
Mortality:
Time-critical diagnosis:
|
Features associated with poor outcome:
|
Refractory status |
Mortality:
|
Features associated with poor outcome:
|
References
Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Chapter 50 (pp. 560) Status epilepticus by Helen I Opdam
Tan, R. Y. L., A. Neligan, and S. D. Shorvon. "The uncommon causes of status epilepticus: a systematic review." Epilepsy research 91.2 (2010): 111-122.
Brophy, Gretchen M., et al. "Guidelines for the evaluation and management of status epilepticus." Neurocritical care 17.1 (2012): 3-23.
Chen, James WY, and Claude G. Wasterlain. "Status epilepticus: pathophysiology and management in adults." The Lancet Neurology 5.3 (2006): 246-256.
Treiman, David M., et al. "A comparison of four treatments for generalized convulsive status epilepticus." New England Journal of Medicine 339.12 (1998): 792-798.
Meierkord, Hartmut, and Martin Holtkamp. "Non-convulsive status epilepticus in adults: clinical forms and treatment." The Lancet Neurology 6.4 (2007): 329-339.
Corry, Jesse J., et al. "Hypothermia for refractory status epilepticus."Neurocritical care 9.2 (2008): 189-197.
Brophy, Gretchen M., et al. "Guidelines for the evaluation and management of status epilepticus." Neurocritical care 17.1 (2012): 3-23.
Question 21.1 - 2015, Paper 1
List three causes of coma with bilateral miosis. (15% marks)
College Answer
- Pontine lesions
- Thalamic haemorrhage
- Metabolic encephalopathy
- Organophosphate
- Other cholinergic agents (e.g. donezepil for Alzheimers)
- Opioids, barbituates, GHB, clonidine
- Mushroom intoxication (cholinergic effect)
Discussion
Chris Nickson has done an awesome thing about this at LITFL. I have shamelessly ripped him off, because I have no access to Bhidayasiri's "Neurological differential diagnosis: a prioritized approach" which is given as his main reference.
Anyway. The more specific answer should mention that among focal neurological causes, bilateral lesions are required to cause bilateral miosis.
Thus, the corrected list of causes would resemble the following:
- Bilateral pontine lesions
- Bilateral thalamic lesions
- Metabolic encephalopathy
- Cholinergic drugs
- Organophosphates
- Myasthenia gravis drugs (the 'stigmines, eg. pyridostigmine)
- Alzheimers nootropics (the 'pezils, eg. donepezil)
- Sarin gas
- Non-cholinergic drugs:
- Opiates
- Barbiturates
- GHB
- Clonidine
- GHB
- Chloral hydrate
- Valproate
- Atypical antipsychotics
- Phenothiazines
Causes of bilaterally small pupils which do not produce coma:
- Neurosyphilis (bilateral Argyll-Robertson pupils)
- Diabetic neuropathy
- Late Holmes-Adie pupils (initially, they are dilated)
- Bilateral Horner's Syndrome, due to:
- Bilateral carotid dissection
- Bilateral neck trauma
- Cluster headache
- Or, massive thalamic or pontine damage
The whole "metabolic encephalopathy" thing is somewhat vague, and is included here because it is technically accurate. Metabolic encephalopathy can describe many things, and produce many signs.
A reader of LITFL had also pointed out that phenothiazines should be expected to cause mydriasis, by virtue of their anticholinergic effect. This is not the case. A 1973 article from California Medicine reports 48 cases of phenothiazine poisoning, in which the pupils were almost invariably small. This can be attributed to the alpha-antagonist effects of these drugs, which override the anticholinergic effects.
References
The LITFL summary of cranial nerve lesions is without peer in terms of useful information density.
Specifically, the reader is directed to Coma and Small Pupils, aka Neurological Mind-boggler 002
Walker, H. Kenneth, W. Dallas Hall, and J. Willis Hurst. "Clinical methods." 3rd edition.(1990).Chapter 58 The Pupils - by Robert H. Spector.
Barry, Daniel, Frank L. Meyskens Jr, and Charles E. Becker. "Phenothiazine Poisoning A Review of 48 Cases." California medicine 118.1 (1973): 1.
Question 6 - 2015, Paper 2
You are called to review a 55-year-old female following difficult, prolonged surgery for clipping of a left middle cerebral artery aneurysm. She returned to the ICU intubated, ventilated and with an external ventricular drain (EVD) in situ three hours earlier.
She now has frank blood in the EVD. Her blood pressure is 180/100 mmHg, and her intracranial pressure has increased to 57 mm Hg.
Outline your approach to her initial management
College Answer
Overview
- This is a very urgent situation
- Likely diagnosis is a surgical catastrophe
- Priorities
- Resuscitate
- Will need urgent CT +/- angiogram
- Contact surgical team
- Control ICP and defend CPP
- Prepare for OT
- Contact family once urgent situation settled
Resuscitate
- PaO2 >90 mmHg, O2 sats >95%
- CO2 32 – 38 mmHg
- Check ETT ties
- Check BP for accuracy, probably allow BP to be a bit on the high side initially (SBP 150 – 170) but not excessively. Avoid hypotension. Treat hypotension carefully (probably noradrenaline rather than metaraminol boluses) to prevent large swings in BP
Urgent CT +/- Angiogram
- Get junior to call CT
- Start packing, obtaining equipment, medications
Contact Surgical Team
Control ICP
- Check reading; level, zero, draining
- ETT ties not tight
- Head up 45 degrees
- Mild hyperventilation (CO2 34 – 38 mmHg)
- Sedation
- Thiopentone bolus 2 – 5 mg/kg
- Opiate/benzodiazepine/propofol
- Paralysis
- Lower drain (5 – 10 cm above foramen magnum) and drain CSF
- Consider osmolar therapy
- Mannitol (100 mL 20%)
- Hypertonic saline (dose)
- Target osm 320
- Maintain CPP if able
- Probably target CPP of 50-60
- Prepare for OT
- Check G+H
- Check coags
- Contact anesthestic/OT co-ordinator
- Cease feeds
Additional Examiners’ Comments:
Some candidates failed to recognise this as an emergency situation and treat appropriately in collaboration with the neurosurgeon.
Discussion
This college model answer is an interesting exercise, which offers a glimpse into the mind of the examiner. The candidates would be forgiven for thinking that writing something like "this is a very urgent situation" would be a useless motherhood statement in an ICU final. We are all critical care staff here. Upon seeing an ICP of 57 and an EVD full of blood, none of us would say "This is a non-urgent benign situation, and I will have a cup of tea". However, the apparent failure of some of the candidates to write such a statement has led the examiners to conclude that they failed to recognise this hideous situation as an emergency.

The rest of the college answer is also interesting, as it introduces some weird micromanagement of intra-hospital logistics (eg. "Contact anesthestic/OT co-ordinator" and "Get junior to call CT"). One might conclude on the basis of this that the marking breakdown included such minutae.
If all the "pack the patient, wipe their bottom, fold the sheets" bullshit is trimmed away one recognises that the meat of this question is in the management of ICP. The stereotypical approach to ICP management is described elsewhere, and is repeated here to simplify revision:
Stereotypical steps in ICP management:
- Position the head (45 °head up, facing straight)
- Loosen the ETT ties
- Remove the C-spine collar
- Decrease PEEP as much as possible
- Increase sedation
- Propofol sedation to decrease distress and thus decrease ICP
- Benzodiazepines may be of use (but they do not decrease the CMRO2 as much as propofol)
- Drain some CSF from the EVD
- Paralysis with neuromuscular junction blocker
- Osmotherapy
- Mannitol 20%
- Hypertonic saline
- Super-refractory ICP
- Hypothermia
- THAM
- Dihydroergotamine
- Controversial measures
- Barbiturate coma if other methods of lowering ICP have failed
- Decompressive craniectomy
Interestingly, the college recommends defending the CPP, which sounds unusual, because one will inevitably end up pushing more blood out of the EVD, with the MCA clip lost and the artery hosing away. This is actually the least stupid move of the possible moves you could make here, but it is a valid point that blood loss would likely be suibstantial, if not immediately then in theatre. According to this MRI study of cerebral blood flow by Enzmann et al (1994), the MCA blood flow at rest is about 127 ml/min. Let's say that the entire MCA output is being pushed out of the EVD. At that rate, one would lose 1L of blood every 8 minutes or so. As such, to organise a massive transfusion protocol might appear as a reasonable. Of course, one would not practice permissive hypotesion here to limit the blood loss, because that would produce brain hypoperfusion.
References
Enzmann, Dieter R., et al. "Blood flow in major cerebral arteries measured by phase-contrast cine MR." American journal of neuroradiology 15.1 (1994): 123-129.
Question 26 - 2015, Paper 2
A 27-year-old female presents to the Emergency Department after a collapse at work that was followed by a brief tonic-clonic seizure. She is 30 weeks pregnant with no previous pregnancies or other significant medical history. She currently localises bilaterally to painful stimulus but does not open her eyes or vocalise.
Her blood pressure is 170/50 mmHg, her urine analysis is unremarkable, and the cardiotocogram (CTG) is ‘reassuring’. A CT brain scan shows a sigmoid and transverse venous sinus thrombosis, with some temporal lobe parenchymal haemorrhage.
a) List the major risk factors, other than pregnancy, for this condition. (30% marks)
b) Briefly outline the management priorities for this patient? (70% marks)
College Answer
a)
Prothrombotic conditions – genetic or acquired Oral contraceptive
Malignancy
Parameningeal Infection e.g. ear, sinus
Head trauma
Surgery
Mechanical precipitant
Autoimmune disease e.g. SLE, antiphospholipid
Other drugs e.g. androgens
b)
Resuscitation:
o Consider intubation
o Check gas exchange (expect slight respiratory alkalosis)
o BP currently a bit on the high side, maybe careful hydralazine to SBP 140-160?
Specific therapy for cerebral venous sinus thrombosis
o Therapeutic anticoagulation
o Can use LMWH or UFH
o Intracranial haemorrhage with CVT is not a contraindication to anticoagulation
o Continued for remainder of pregnancy and usually for further 6-12 weeks postpartum
o Aspirin – no evidence of benefit. Occasionally used as alternative if firm CI to therapeutic anticoagulation
o Potential therapies include thrombolysis (systemic or catheter-directed), mechanical clot extraction, decompressive craniectomy
o Assess for underlying cause that may require specific therapy e.g.,
- Antiphosphoplipid syndrome
- Sinus or parameningeal infection
o May need an anticonvulsant; consider neurology input
Pregnancy related:
o Involvement of obstetric service, regular CTG, ultrasound
o ? steroids to allow for early delivery if needed
o Shielding for X-ray and CT limit as able
o Blood conservation given physiological anaemia of pregnancy
o Need to keep family up to date
Discussion
a)
The following lisk of risk factors was compiled using UpToDate and Ferro et al (2004). The latter was a multinational multicentre observational study which identified 624 patients with confirmed CVT. Of this group, the following risk factors were observed:
- Genetic thrombophilia (22.4% of cases)
- Pregnancy during peripartum period or puerperium (13.8%)
- Infection, be it CNS or ENT (12.3%)
- Drugs (7.5%)
- Malignancy (7.4%)
- Pregnancy at any stage (6.3%)
- Antiphospholipid syndrome (5.9%)
- Trauma, neurosrugery or lumbar puncture (4.5%)
- Vasculitis (3%)
- Polycythaemia or thrombocytosis (2.8%)
- Surgery (2.7%)
- Vascular anomaly in the CNS like dural fistula, AVM, etc (1.9%)
- Dehydration (1.9%)
b)
The major approaches to fixing this problem are anticoagulation, thrombolysis, endovascular thrombectomy and open clot retrieval.
- Anticoagulation has been the mainstay of treatment. Coutinho et al (2012) performed a systematic review of the practice and found it to be very helpful, with risk of death reduced by two thirds (ARR of 13%) and substantially improved neurological outcomes. As the patients usually have some sort of procoagulant state, you're going to end up anticoagulating them anyway.
- Thrombolysis for CVT is a logical extension of the use of thrombolysis for ischaemic stroke (i.e. "if its good enough for arterial clots, why not try it with venous clots"). This is the topic of the TO-ACT trial (Coutinho et al, 2013) which appears to still be recruiting. Apart from this undertaking, evidence for the use of thrombolysis in CVT consists of case series only (Ciccone et al, 2004, and Canhão et al, 2003, with about 200 patients in total). Discouraging features included a high rate of extracranial (21%) and intracranial (17%) haemorrhage, which occured in spite of the fact that in the majority of cases (88%) the thrombolytic agent was administered directly into the thrombosed sinus.
- Endovascular clot retrieval is typically reserved for situations where there is significant thrombus burden, contraindication to anticoagulation or a lack of clinical improvement or worsening of symptoms despite systemic heparin. It is the new exciting thing on this scene, and also only known from case series. As a representative example, Mokin et al (2015) report on the American experience. Thirteen patients were identified, of whom five had a favorable clinical outcome (defined as modified Rankin Scale score of 0–2) and three died. A systematic review of such case series (Siddiqui et al, 2015) found a good outcome in 84% and a mortality of 12% among a total of 185 patients, even though they represented the more severe end of the CVT spectrum (60% were in a coma).
- Open clot retrieval seems to be an end-of-the-line manoeuvre. It is known only from heroic case reports (eg. Persson et al, 1990 and Ekseth et al, 1998). In each case, the surgeons followed thrombectomy by an infusion of a thrombolytic agent.
- Decompressive craniectomy for this condition is discussed elsewhere. In brief, the results have been encouraging and full systemic anticoagulation within 24 hours of surgery seems to be safe. A 2009 review from Stroke courageously asserted that the therapy is "lifesaving" and that the outcome can be "excellent", on the basis of three cases. The AHA/ASA gudelines recommend this as a viable option.
References
Roberts, Jonathan C., and Christopher M. Fischer. "Cerebral venous sinus thrombosis." Vascular Emergencies: Expert Management for the Emergency Physician (2013): 1.
Rothwell, P. M., et al. "Risk factors for cerebral venous thrombosis." Oxford Textbook of Stroke and Cerebrovascular Disease (2014): 14.
Bhogal, P., et al. "Cerebral Venous Sinus Thrombosis." Clinical Neuroradiology (2016): 1-6.
Ferro, José M., et al. "Prognosis of cerebral vein and dural sinus thrombosis results of the international study on cerebral vein and dural sinus thrombosis (ISCVT)." Stroke 35.3 (2004): 664-670.
Lee, Emil JY. "The Empty Delta Sign 1." Radiology 224.3 (2002): 788-789.Virapongse, Chat, et al. "The empty delta sign: frequency and significance in 76 cases of dural sinus thrombosis." Radiology 162.3 (1987): 779-785.
Virapongse, Chat, et al. "The empty delta sign: frequency and significance in 76 cases of dural sinus thrombosis." Radiology 162.3 (1987): 779-785.
Saposnik, Gustavo, et al. "Diagnosis and management of cerebral venous thrombosis a statement for healthcare professionals from the American Heart Association/American Stroke Association." Stroke 42.4 (2011): 1158-1192.
Coutinho, Jonathan M., Sebastiaan FTM de Bruijn, and Jan Stam. "Anticoagulation for cerebral venous sinus thrombosis." Stroke 43.4 (2012): e41-e42.
Coutinho, Jonathan M., et al. "Thrombolysis or anticoagulation for cerebral venous thrombosis: rationale and design of the TO‐ACT trial." International Journal of Stroke 8.2 (2013): 135-140.
Canhão, Patricia, Filipa Falcão, and José M. Ferro. "Thrombolytics for cerebral sinus thrombosis." Cerebrovascular diseases 15.3 (2003): 159-166.
Ciccone, Alfonso, et al. "Thrombolysis for cerebral vein and dural sinus thrombosis." The Cochrane Library (2004).
Mokin, Maxim, et al. "Endovascular treatment of cerebral venous thrombosis: Contemporary multicenter experience." Interventional Neuroradiology (2015): 1591019915583015.
Siddiqui, Fazeel M., et al. "Mechanical Thrombectomy in Cerebral Venous Thrombosis Systematic Review of 185 Cases." Stroke 46.5 (2015): 1263-1268.
Persson, Lennart, and Anders Lilja. "Extensive dural sinus thrombosis treated by surgical removal and local streptokinase infusion." Neurosurgery 26.1 (1990): 117-121.
Ekseth, Kåre, Sverre Boström, and Magnus Vegfors. "Reversibility of severe sagittal sinus thrombosis with open surgical thrombectomy combined with local infusion of tissue plasminogen activator: technical case report." Neurosurgery 43.4 (1998): 960-964.
Question 14.1 - 2016, Paper 1
A 28-year-old female with ulcerative colitis on azathioprine and prednisolone was commenced on intravenous infliximab for the worsening of symptoms. Two weeks after the second cycle, she presented with headache, confusion and blurred vision followed by a generalised tonic-clonic seizure.
Cerebrospinal fluid analysis is unremarkable.
Slices from T2 weighted MRI scan of the brain are depicted below (Figure 1):

a) What is the most likely diagnosis?
b) List four risk factors for this condition.
College Answer
a)
- Posterior Reversible Leukoencephalopathy Syndrome
b)
- Hypertension
- Eclampsia / Pre-eclampsia
- Immunosuppressive therapy
- Auto-immune diseases
- Porphyria
- Acute or chronic renal diseases
- TTP / HUS
- Infection / sepsis / septic shock
Discussion
a)
This is PRES, the posterior reversible leukoencephalopathy syndrome. The images above were ripped off from the 2012 article by Swarnalatha et al. It has been associated with infliximab therapy, and is known in this context from a growing number of case reports (eg. Zamvar et al, 2009). It is also associated with sirolimus, thalidomide, gemcitabine, paclitaxel, carboplatin, sorafenib and the list goes on. According to Radiopedia, it can be recognised by the following MRI image features:
- Posterior distribution (but this is not essential)
- T1: hypointense in affected regions
- T1 C+ (Gd): patchy variable enhancement. It can be seen in ~35% of patients, whether leptomeningeal or cortical pattern.
- T2: hyperintense in affected regions
- DWI: usually normal
- ADC: signal increased in affected regions due to increased diffusion
- GRE: may show hypointense signal in cases of haemorrhage
- SWI: may show microhemorrhages in up to 50%
b)
Risk factors for PRES could include:
- Autoimmune disease
- Immunosuppressive therapy
- Eclampsia and pre-eclampsia
- Hypertension
PRES is almost exclusive to significant systemic conditions. . Classical associations include the following list (borrowed from Bartynski's Table 1):
- Solid organ transplant
- Bone marrow transplant
- Graft vs. host disease following allogenic BMT
- Immunosuppressant therapy
- Pregnancy (particularly, pre-eclampsia)
- Cancer chemotherapy
- Autoimmune disease, particularly scleroderma, SLE and Wegener's granulomatosis
- Sepsis and septic shock
The UpToDate article gives an even larger list of "associated conditions", which adds the following:
- TTP / HUS
- Cryoglobulinaemia
- Chronic kidney diseases
- Porphyria
- Blood transfusion
- Contrast media exposure
References
G Swarnalatha, R Ram, B. H. S. Pai, KV Dakshinamurty "Posterior reversible encephalopathy syndrome in minimal change disease" Indian Journal of Nephrology, Vol. 22, No. 2, March-April, 2012, pp. 153-154
Zamvar, Veena, et al. "Posterior reversible encephalopathy syndrome following infliximab infusion." Journal of pediatric gastroenterology and nutrition 48.1 (2009): 102-105.
Fugate, Jennifer E., et al. "Posterior reversible encephalopathy syndrome: associated clinical and radiologic findings." Mayo Clinic Proceedings. Vol. 85. No. 5. Elsevier, 2010.
Staykov, Dimitre, and Stefan Schwab. "Posterior reversible encephalopathy syndrome." Journal of Intensive Care Medicine 27.1 (2012): 11-24.
Bartynski, W. S. "Posterior reversible encephalopathy syndrome, part 1: fundamental imaging and clinical features." American Journal of Neuroradiology 29.6 (2008): 1036-1042.
Bartynski, W. S. "Posterior reversible encephalopathy syndrome, part 2: controversies surrounding pathophysiology of vasogenic edema." American Journal of Neuroradiology 29.6 (2008): 1043-1049.
Grioni, Daniele, et al. "The diagnosis of posterior reversible encephalopathy syndrome." The Lancet Neurology 14.11 (2015): 1073-1074.
Fugate, Jennifer E., and Alejandro A. Rabinstein. "Posterior reversible encephalopathy syndrome: clinical and radiological manifestations, pathophysiology, and outstanding questions." The Lancet Neurology 14.9 (2015): 914-925.
MacKenzie, ERIC T., et al. "Effects of acutely induced hypertension in cats on pial arteriolar caliber, local cerebral blood flow, and the blood-brain barrier." Circulation research 39.1 (1976): 33-41.
Question 20 - 2016, Paper 1
With respect to Guillain Barre Syndrome and Myasthenia Gravis, compare and contrast the respective:
a) Clinical features. (30% marks)
b) Investigations needed to make the diagnosis. (30% marks)
c) Specific treatment strategies with the relevant evidence/recommendations for the strategies listed (40% marks)
College Answer
|
Condition |
Clinical Features |
Investigations |
Treatment Strategies |
|
Guillain-Barre Syndrome |
Diarrhoeal prodrome Autonomic instability Symmetrical, progressive ascending weakness with associated areflexia. Ventilatory failure May be cranial nerve involvement. Sensory loss usually mild or absent. |
Nerve conduction studies show demyelination (reduction in conduction velocities) CSF analysis: high protein and normal WCC |
IVIG Plasmapheresis The use of plasma exchange or IVIG depends on the institution or whether the patient has a contraindication to IG such as IgA deficiency. Both have been shown to be equally efficacious. One Cochrane review suggested that IVIG given within 2 weeks of the onset was as efficacious as plasma exchange, and more likely to be completed than plasma exchange. Their combination is not supported. |
|
Myasthenia Gravis |
Fluctuating, often fatiguable, weakness and possible progression to ventilator failure but reflexes intact. Ptosis with associated diplopia. |
Auto-antibodies against nicotinic Ach receptors and MuSK Antibodies EMG and NCS studies |
Anticholinesterases e.g. Pyridostigmine – symptomatic treatment more effective in antiAChR than MuSK Rapid Immunotherapy (IVIG and PLEX) – recommended for myasthenic crises Chronic Immunotherpay (Steroids and immunosuppressants) – majority require this with antiAChase Thymectomy – not recommended routinely for age>60 unless thymoma present |
Discussion
a)
| Features | Guillain-Barre | Myasthenia Gravis |
| Clinical setting |
|
|
| Motor weakness |
|
|
| Sensory loss |
|
|
| Reflexes |
|
|
| Cranial nerve involvement |
|
|
| Dysautonomia |
|
|
b)
| Guillain Barre Syndrome |
|
| Myasthenia Gravis |
|
c)
| Guillain Barre Syndrome |
|
| Myasthenia Gravis |
|
References
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
van den Berg, Bianca, et al. "Guillain-Barre syndrome: pathogenesis, diagnosis, treatment and prognosis." Nature Reviews Neurology 10.8 (2014): 469-482.
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Raphael, J. C., et al. "Plasma exchange for Guillain-Barré syndrome." Cochrane Database Syst Rev 2.2 (2002).
Venkata Umakant, K., B. Seshulakshmi, and B. Srinivasa Rao. "Miller Fisher Syndrome–An Atypical Clinical Presentation." Intern Med 3.119 (2013): 2.
Berlit, Peter, and Josef Rakicky. "The Miller Fisher syndrome: review of the literature." Journal of Neuro-Ophthalmology 12.1 (1992): 57-63.
Odaka, M., N. Yuki, and K. Hirata. "Anti-GQ1b IgG antibody syndrome: clinical and immunological range." Journal of Neurology, Neurosurgery & Psychiatry70.1 (2001): 50-55.
Alkan, Ozlem, et al. "Spinal MRI findings of guillain-barre syndrome." Journal of radiology case reports 3.3 (2009): 25.
Cabrera Serrano, M., and A. A. Rabinstein. "Usefulness of pulmonary function tests and blood gases in acute neuromuscular respiratory failure." European Journal of Neurology 19.3 (2012): 452-456.
Farrero, Eva, et al. "Guidelines for the Management of Respiratory Complications in Patients With Neuromuscular Disease." Archivos de Bronconeumología (English Edition) 49.7 (2013): 306-313.
Hughes, Richard AC, et al. "Supportive care for patients with Guillain-Barré syndrome." Archives of neurology 62.8 (2005): 1194-1198.
Massam, M., and R. S. Jones. "Ventilatory failure in the Guillain-Barré syndrome." Thorax 35.7 (1980): 557-558.
González-Suárez, Inés, et al. "Guillain-Barré Syndrome: Natural history and prognostic factors: a retrospective review of 106 cases." BMC neurology 13.1 (2013): 95.
Dhand, Upinder K. "Clinical approach to the weak patient in the intensive care unit." Respiratory care 51.9 (2006): 1024-1041.
Sanders, Donald B., and Janice M. Massey. "Clinical features of myasthenia gravis." Handbook of clinical neurology 91 (2008): 229-252.
Bird, Shawn J. "Clinical manifestations of myasthenia gravis." Up-to-date 16.1 (2008): 1-8.
Gronseth, Gary S., and Richard J. Barohn. "Practice parameter: Thymectomy for autoimmune myasthenia gravis (an evidence-based review) Report of the Quality Standards Subcommittee of the American Academy of Neurology." Neurology 55.1 (2000): 7-15.
Gajdos, Philippe, Sylvie Chevret, and Klaus V. Toyka. "Plasma exchange for generalised myasthenia gravis." The Cochrane Library (2002).
Gajdos, Philippe, et al. "Treatment of myasthenia gravis exacerbation with intravenous immunoglobulin: a randomized double-blind clinical trial." Archives of neurology 62.11 (2005): 1689-1693.
Hughes, Richard AC, Anthony V. Swan, and Pieter A. van Doorn. "Intravenous immunoglobulin for Guillain‐Barré syndrome." The Cochrane Library (2014).
Sussman, Jon, et al. "Myasthenia gravis: association of British Neurologists’ management guidelines." Practical neurology 15.3 (2015): 199-206.
Question 27 - 2016, Paper 1
Outline the strategies, with the rationale, to reduce the likelihood of secondary neurological injury after brain trauma. Give the specific parameters/targets where appropriate.
College Answer
|
Strategy |
Rationale |
|
Endotracheal intubation |
Prevention of hypoxaemia by preventing airway obstruction and/or aspiration, facilitates mechanical ventilation |
|
Controlled mechanical ventilation O2 saturation >95% PaCO2 32 – 38 mmHg (4.2 – 5.0 kPa) |
Avoidance of hypoxaemia, Avoidance of hypercarbia which can lead to cerebral vasodilation and increased ICP Avoidance of hypocarbia with consequent cerebral vasoconstriction and relative ischaemia |
|
Cervical spine immobilisation |
Cervical spine injury is commonly associated with traumatic brain injury |
|
Maintain an adequate blood pressure Systolic BP >110 MAP 80-120 if CPP measured and ICP>20 |
Hypotension is associated with poorer neurological outcome Hypovolaemia is common in trauma patients due to associated injuries |
|
Avoid the use of albumin for fluid resuscitation |
Albumin is associated with poorer outcomes in patients with TBI |
|
Avoid cerebral venous hypertension Care with ETT tapes C-spine collars Elevate head of bed 30-45o |
Obstructed venous drainage can contribute to intracranial hypertension |
|
Maintain normothermia Temperature 36-37o |
Elevated temperature increases cerebral metabolic demand Hypothermia has not yet been shown to be associated with improved outcomes |
|
Maintain normoglycaemia BSL 6-10 mMol/L |
Hypoglycaemia exacerbates cerebral injury |
|
Avoid hyponatraemia Na 140-145 mMol/L |
Hyponatraemia can contribute to cerebral oedema and raised intracranial pressure |
|
Early detection of surgically correctable secondary lesion ICP monitoring Low threshold for repeat CT scan if deterioration in clinical neurological state |
Early identification of a surgically correctable lesion Reaccumulation of extra-axial collection Hydrocephalus New intraparenchymal haemorrhage Surgical intervention may prevent further neurological damage |
|
Monitoring of and treatment for intracranial hypertension ICP <20 |
Strategies to treat intracranial hypertension (in addition to those mentioned above) Sedation Neuromuscular paralysis Induction of mild hyperosmolar state |
|
Detect and treat seizures |
Convulsive and non-convulsive epileptic seizures, increase cerebral metabolic demand |
Discussion
Neuroprotective measures in traumatic brain injury are discussed in great detail elsewhere.
Other chapters of interest would have to include
- Methods of intracranial pressure monitoring
- Indications for intracranial pressure monitoring
- Management of raised intracranial pressure
In brief:
Maintaining cerebral oxygen supply:
- Normoxia: keep the PaO2 above 60 mmHg
- Normotension: measure the MAP, and keep the systolic above 90mmHg
- Intracranial Pressure monitoring: keep it under 20mmHg
- Cerebral perfusion pressure: keep it 50-70mmHg
- Cerebral oxygenation monitoring:keep the SjO2 >50%, and PbrO2 >55mmHg
- Managing increased intracranial pressure for which there is a variety of strategies:
- Draining the EVD ( about 20ml/hr, max)
- Positioning the head straight
- Removing the C-spine collar
- Sedation :
- Propofol sedation to decrease distress and thus decrease ICP
- Barbiturate coma if other methods of lowering ICP have failed
- Analgesia to prevent increased ICP in response to suctioning and routine care
- Paralysis
- Osmotherapy
- Controversial measures
- Decompressive craniectomy
- Hypothermia
- Dexamethasone
Decreasing cerebral oxygen demand:
- Sedation
- Propofol sedation to decrease distress and thus decrease ICP
- Barbiturate coma if medical and surgical methods of lowering ICP have failed
- Analgesia - opioid selection is irrelevant, but opiate boluses increase ICP
- Seizure prophylaxis is infrequently indicated, and the course is 7 days only
Controversial measures:
- Decompressive Craniectomy
- Hypothermia
References
Question 12 - 2016, Paper 2
With respect to delirium in critically ill patients:
a) Define delirium. (20% marks)
b) List the causes and predisposing factors. (30% marks)
c) Briefly outline its assessment and treatment. (50% marks)
College answer
a) Definition:
The acute onset of a disturbance of consciousness with inattention, changes in cognition and/or perception, that fluctuates over time, occurs as a consequence of a general medical condition and is not better accounted for by a pre-existing, established or evolving dementia.
b) Causes / Predisposing factors:
- Age >80
- Pre-existing cognitive impairment
- Severity of illness
- Visual impairment
- Dehydration
- Infection/Fever/Hypothermia
- Hypoxia
- Drugs/Polypharmacy o Esp Psychoactive drugs o Anticholinergics, o Narcotics o Steroids
- Drug withdrawal o Etoh, Benzos, SSRI
- Metabolic shifts- [Na], renal failure, BSL, Wernickes
- Cardiorespiratory disease
- Sensory deprivation, overstimulation
- Trauma/Post op o Esp – Cardiac sx, Cataract sx, Orthopedics and TURP
c) Assessment:
- DSM V
- CAM, CAM ICU
- Memorial delirium assessment scale
d) Treatment
- High-level supportive care
- Sleep hygiene
- Hydration
- nutrition- thiamine
- Early mobilization
- Avoid physical restraints
- Visual and hearing aids
- Minimize staff changes and utilize family members
- Frequent reorientation
- Do not directly engage or oppose hallucinations/ paranoid behaviours
- Treat underlying cause and precipitant
- Treat psychotic phenomenology
- Haloperidol
- Risperidone
- Olanzapine
- Dexmetomidine
Additional Examiners Comments
In general, well answered.
Discussion
This question closely resembles Question 29 from the second paper of 2009. It also features a positive comment from the examiners, which is unprecedented.
a) Definition of delirium (the DSM V definition)
- Disturbance in attention (ie, reduced ability to direct, focus, sustain, and shift attention) and awareness.
- Change in cognition (eg, memory deficit, disorientation, language disturbance, perceptual disturbance) that is not better accounted for by a preexisting, established, or evolving dementia.
- The disturbance develops over a short period (usually hours to days) and tends to fluctuate during the course of the day.
- There is evidence from the history, physical examination, or laboratory findings that the disturbance is caused by a direct physiologic consequence of a general medical condition, an intoxicating substance, medication use, or more than one cause.
b) Risk factors:
Significant risk factors:
Preventable risk factors
|
Associated factors |
|
Uncontrollable risk factors
|
Modifiable risk factors
|
|
c) Management of delirium
Non-pharmacological:
- Good analgesia
- Clear and firm communication with the patient
- Frequent re-orientation
- Family presence
- Low-noise environment
- Restoration of hearing aids and spectacles
- Avoidance of sleep disturbance, promotion of normal sleep–wake cycle.
- Avoidance of physical restraints
- Early removal of IV lines and IDC
- Early mobilisation
- Adequate hydration
- Adequate (oral) nutrition
- Use of thiamine
Pharmacological:
- Dexmedetomidine
- Atypical antipsychotics
- Classical antipsychotics
- Benzodiazepines (if withdrawing from alcohol or benzodiazepines)
References
Oh's Intensive Care manual: Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Girard, Timothy D., Pratik P. Pandharipande, and E. Wesley Ely. "Delirium in the intensive care unit." Critical Care 12.Suppl 3 (2008): S3.
Barr, Juliana, et al. "Clinical practice guidelines for the management of pain, agitation, and delirium in adult patients in the intensive care unit." Critical care medicine 41.1 (2013): 263-306.
Ouimet, Sébastien, et al. "Incidence, risk factors and consequences of ICU delirium." Intensive care medicine 33.1 (2007): 66-73.
Van Rompaey, Bart, et al. "Risk factors for intensive care delirium: a systematic review." Intensive and Critical Care Nursing 24.2 (2008): 98-107.
Schweickert, William D., et al. "Early physical and occupational therapy in mechanically ventilated, critically ill patients: a randomised controlled trial."Lancet (London, England) 373.9678 (2009): 1874-1882.
Inouye, Sharon K., et al. "A multicomponent intervention to prevent delirium in hospitalized older patients." New England journal of medicine 340.9 (1999): 669-676.
Question 19 - 2016, Paper 2
Describe the various types of brain herniation, including their radiological and clinical features.
College answer
1. Subfalcine (cingulate or transfalcine)
• This occurs when the brain extends under the falx cerebri. Radiological features include
• a shift of the septum pellucidum,
• effacement of the anterior horn of the lateral ventricle. Clinical features may be mild or absent, including
• headache,
• drowsiness,
• contralateral leg weakness.
2. Uncal (or temporal transtentorial)
• The uncinate process or medial portion of the temporal lobe is displaced downwards onto the tentorium cerebelli and suprasellar cistern.
Radiological features
• Shift of brainstem and distortion of adjacent cisterns
• Dilation of contralateral temporal horn
• PCA territory infarct due to compression of posterior cerebral artery as it crosses tentorium
Clinical features include
• ipsilateral pupillary dilation and lack of reactivity to light and
• deviation of eye to “down and out position” due to pressure on the third cranial nerve.
• Compression of ipsilateral posterior cerebral artery results in ischaemia of ipsilateral visual cortex and contralateral visual field deficits in both eyes (contralateral homonymous hemianopia)
• There is also a decreased conscious level and
• There may be a contralateral hemiparesis due to the primary lesion causing the uncal herniation
• There may also be ipsilateral hemiparesis and leg extension (referenced to the side of herniation). This is referred to as a false localising sign due to compression of contralateral cerebral peduncle with corticospinal and some corticobulbar fibres
(Kernohan‟s notch)
• Progression will lead to decreased conscious state, bradycardia, decorticate posture, respiratory depression and death
3. Central
• Symmetrical downward movement of thalamus through tentorium cerebelli Radiological appearance:
• Peri-mesencephalic cistern effacement
• May be diffuse loss of grey-white matter differentiation
Clinically
• Loss of consciousness with small reactive pupils and
• Paralysis of upward eye movements („sunset eyes‟)
• May progress to decorticate posturing
• Diabetes insipidus may be present
4. Transcalvarial
Brain squeezes through a fracture or surgical site in the skull Clinical features relate to side and lobe involved
5. Infratentorial herniation
6. Cerebellar Tonsillar (downward cerebellar herniation, transforaminal herniation) Cerebellar tonsils move downwards through the foramen magnum.
Clinically causes
• cardiac and respiratory depression.
7. Upward transtentorial herniation or reverse coning
• Increased pressure in posterior fossa causing upward movement of cerebellum through tentorial notch with compression of midbrain, e.g. when CSF is abruptly drained above the level of the tentorium Clinical features
• Coma, respiratory depression, haemodynamic instability and death
Additional Examiners' Comments:
Many candidates had large knowledge gaps and were factually incorrect with their answers. Division between supratentorial and infratentorial herniation was fundamental to the question. Many candidates mixed uncal and cerebellar tonsil herniation and there was little mention of lateralising signs and general impact on conscious state.
Discussion
The discussion of brain herniation elsewhere has a lot more detail than this, including explanations.
| Herniation | Radiological features | Clinical features |
| Falcine |
|
|
| Midline shift |
|
|
| Uncal |
|
|
| Central tentorial |
|
|
| Tonsillar |
|
|
| Upward |
|
|
| Transcalvarial |
|
|
References
Hahn, F. J., and J. Gurney. "CT signs of central descending transtentorial herniation." American Journal of Neuroradiology 6.5 (1985): 844-845.
Brazis, P., J. Masdeu, and Jose Biller. "Localization in Clinical Neurology." 2007 Lippincott Williams & Wilkins
Cuneo, Richard A., et al. "Upward transtentorial herniation: seven cases and a literature review." Archives of neurology 36.10 (1979): 618-623.
Riveros Gilardi, Berta, et al. "Types of cerebral herniation and their imaging features." Radiographics 39.6 (2019): 1598-1610.
Question 21 - 2016, Paper 2
A 23-year-old female is admitted to your ICU following her first presentation with seizures. A collateral history suggested that she had been acting unusually for the previous few days before she was seen to collapse with a tonic-clonic seizure. She continued to fit during transfer to hospital.
On arrival to the Emergency Department she was given further doses of midazolam IV and loaded with levetiracetam IV. After 20 minutes she continued to have sporadic seizure activity with a best GCS of 6 and was intubated using propofol and rocuronium.
a) List six possible causes for her presentation. (30% marks)
On admission to ICU she is on a propofol infusion at 20 mg/hr, minimal ventilatory support and is haemodynamically stable. She continues to have intermittent seizures .
b) Briefly outline your specific management with respect to the seizures. (70% marks)
College answer
a)
Acute structural brain injury (stroke, HI, SAH)
Infection (encephalitis, meningitis, abscess)
Tumour (CNS, Paraneoplastic syndromes / autoantibodies to remote tumours)
Withdrawal (Alcohol, barbiturates, BDZ)
Metabolic (hypoglycaemia, HE, uraemia, hyponat, hypergly/Ca/Mg)
Drug OD
Eclampsia
Autoimmune encephalitis
Or any acceptable cause – PRES, CNS vasculitis etc.
b)
Look for and treat underlying cause of refractory status epilepticus (RSE)
Principles of treatment for RSE
• Look for and treat underlying cause
History including travel, examination, CT, LP, BSL, U&E, metabolic screen, drug screen, auto-immune screen, beta-HCG, paraneoplastic markers, MRI
• Additional agents (one to three or more) to prevent emergence seizures, e.g. Phenytoin, Fosphenytoin, Levetiraetam, Valporate, Phenobarbitone BDZ – clonazepam / diazepam / lorazepam
• General Anaesthesia with EEG monitoring
Propofol / thiopentone / inhalational anaesthetics
• EEG to burst suppression OR seizure suppression only (controversial)
• No guidelines for duration of therapy - initially 24 to 48 hours (controversial)
• If emergence seizures develop treat for longer or deeper or both (controversial)
• Try to avoid rapid switches or changes in agent dosing (as per conventional seizure Mx)
• Avoid NMBs unless continuous EEG monitoring
• Avoid hyperthermia and consider hypothermia
Additional Examiners' Comments:
Almost all the candidates were able to answer the first part. Although all the candidates wrote something about the management of the case, it tended to be limited and largely disorganised. There was a lot of generic information not related to the "specific management with respect to the seizures", e.g. „FAST HUG‟ that did not score the candidate any marks.
Discussion
a)
The most common causes of status epilepticus are failure to take one’s own epilepsy tablets. For the weird causes, there is a good article which lists a massive spectrum of toxins, genetic diseases, rare autoimmune conditions and what have you.
- Vascular causes:
- Stroke
- Decreased cerebral blood flow: ischaemic encephalopathy
- Increased cerebral blood flow: hypertensive encephalopathy
- Eclampsia
- Intracranial haemorrhage
- Infectious causes:
- Encephalitis
- Meningitis
- Brain abscess
- Neoplastic lesions:
- Space-occupying tumour
- Drug-induced status epilepticus
- Cocaine
- Methamphetamine
- Phenothiazines
- Tricyclics
- Isoniazid
- Drug withdrawal
- Alcohol
- Benzodiazepines
- Idiopathic neurological causes:
- By this, I mean poorly controlled epilepsy. It is possible to be fully compliant with your medications and still find them totally ineffective. Non-convulsive status could account for the unusual behaviour seen in the "previous few days".
- Congenital causes:
- congenital disorder of metabolism
- structural; congenital abnormality, such as cerebral palsy.
- Autoimmune causes:
- Cerebral vasculitis
- Limbic (NMDA receptor antibody) encephalitis - the presentation of this is pretty classical; the patient has a prodrome of weird behaviour, progressively becoming more confused and ultimately presenting with stupor, coma or relentless seizures. Classically, it is also very difficult to control and these are the people that end up on fourth and fifth line therapies to manage their first-ever episode of epileptic activity.
- Traumatic causes
- penetrating head injury
- neurosurgery
- Endocrine and metabolic causes
- hyponatremia
- hypokalemia
- hypomagnesemia
- hypocalcemia
- an extremely low or extremely high BSL
- uremic encephalopathy
- hepatic encephalopathy
b)
Management of status epilepticus is discussed in greater detail elsewhere. To borrow from that chapter, here is a list of specific therapies for status epilepticus:
First line agents
- Benzodiazepines: boluses every 2-5 minutes
- Phenytoin: 20mg/kg loading dose
- Phenytoin on its own is useless. Or rather, it is inferior to benzodiazepines as a solitary agent. Always, both must be used simultaneously.
Second line agents
- Midazolam infusion
- Phenytoin (well, rather, the American study recommends fosphenytoin)
- Phenobarbital and levetiracetam are also in this second line of attack
Third line agents: for refractory status epilepticus
- Propofol infusion, or midazolam infusion, or thiopentone infusion.
- At this stage, continuous EEG monitoring becomes mandatory
- It does not matter which "general anaesthetic agent" you start an infusion of in refractory status epilepticus. However, one would be well advised to mention in their CICM fellowship answer that the patient has been intubated a long time ago, and that continuous EEG monitoring is now in progress.
- The role of traditional antiepileptic drugs is also exhausted at this stage, as there will probably be no benefit from adding them into a situation where a constantly observed burst suppression is already achieved by high dose anaesthetic infusion.
Fourth line agents: for these, there is little evidence.
Fifth line therapies: for these, the evidence borders on the veterinarian
- Hypothermia
- Ketogenic diet
- Deep brain stimulation
- Surgical management - this could mean callosotomy, which might give rise to its own series of terrible side effects. One might wish for one's epilepsy back.
References
Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Chapter 50 (pp. 560) Status epilepticus by Helen I Opdam
Tan, R. Y. L., A. Neligan, and S. D. Shorvon. "The uncommon causes of status epilepticus: a systematic review." Epilepsy research 91.2 (2010): 111-122.
Johnson, Nicholas, et al. "Anti-NMDA receptor encephalitis causing prolonged nonconvulsive status epilepticus." Neurology 75.16 (2010): 1480-1482.
Chen, James WY, and Claude G. Wasterlain. "Status epilepticus: pathophysiology and management in adults." The Lancet Neurology 5.3 (2006): 246-256.
Treiman, David M., et al. "A comparison of four treatments for generalized convulsive status epilepticus." New England Journal of Medicine 339.12 (1998): 792-798.
Meierkord, Hartmut, and Martin Holtkamp. "Non-convulsive status epilepticus in adults: clinical forms and treatment." The Lancet Neurology 6.4 (2007): 329-339.
Borris, Douglas J., Edward H. Bertram, and Jaideep Kapur. "Ketamine controls prolonged status epilepticus." Epilepsy research 42.2 (2000): 117-122.
Slovis, Corey M. "Lidocaine in the treatment of status epilepticus." Academic emergency medicine 4.9 (1997): 918-925.
Storchheim, Frederic. "Status epilepticus treated by magnesium sulphate, injected intravenously." Journal of the American Medical Association 101.17 (1933): 1313-1314.
Kluger, G., et al. "Pyridoxine-dependent epilepsy: normal outcome in a patient with late diagnosis after prolonged status epilepticus causing cortical blindness." Neuropediatrics 39.5 (2008): 276-279.
Mirsattari, Seyed M., Michael D. Sharpe, and G. Bryan Young. "Treatment of refractory status epilepticus with inhalational anesthetic agents isoflurane and desflurane." Archives of neurology 61.8 (2004): 1254-1259.
Hamani, Clement, et al. "Deep brain stimulation of the anterior nucleus of the thalamus: effects of electrical stimulation on pilocarpine-induced seizures and status epilepticus." Epilepsy research 78.2 (2008): 117-123.
Cervenka, Mackenzie C., et al. "The ketogenic diet for medically and surgically refractory status epilepticus in the neurocritical care unit." Neurocritical care15.3 (2011): 519-524.
Corry, Jesse J., et al. "Hypothermia for refractory status epilepticus."Neurocritical care 9.2 (2008): 189-197.
Question 8 - 2017, Paper 1
You are asked to admit a 46-year-old male who has just been intubated in the Emergency Department (ED) after collapsing from a brain stem stroke, two hours earlier. His Glasgow Coma Scale (GCS) prior to intubation was 6.
Outline your management strategy for him for the first 24 hours.
College answer
Resuscitation, definitive and supportive treatment. Activate the stroke team if available in this hospital as urgent intervention is needed for the best potential outcome – involves neurologist and interventional neuroradiologist. Attention to ABC (confirm tube position, adequacy of ventilation, control hypertension and treat hypotension to ensure adequate CPP).
Investigations / Interventions
- Interventional cerebral angiography if facilities and resources available or transfer to specialist centre if within acceptable time window
Note: Acceptable time window varies between centres but may be up to 12hrs or longer if CT perfusion scan shows salvageable brain.
Although recent trials have shown benefit for acute thrombectomy in acute stroke, brain stem stroke was not well represented in the study population. However, it is so potentially devastating that thrombectomy is advocated - Some centres may combine with IA fibrinolysis (recent papers including one from RMH showing some good outcomes with IA fibrinolysis up to 24-48 hours post stroke)
- Systemic thrombolysis if specialist neuroradiological intervention not available
- Heparin infusion
- Aspirin
Physiological monitoring and maintenance of normal parameters (BP, Na, BSL etc.)
Role of EVD if hydrocephalus is present.
Ongoing neurological assessment – at risk of progressing to locked in syndrome.
Supportive care of the intubated ventilated critically ill patient.
Discussion with family re therapy and outlook plus risk factors for poor outcome.
Investigation for underlying cause / risk factors and treatment as appropriate.
Discussion
This question is virtually identical to Question 13 from the second paper of 2011, with the exception of the college this time specifying that the collapse occurred two hours ago. The answer to Question 13 is therefore reproduced below with minimal modification.
The college is asking what one might do with a brainstem stroke; in order to pass the candidate needs to
- demonstrate that they understand the importance of early thrombolysis
- know about the role of interventional neuroradiology in stroke
- appreciate the need to exclude intracranial haemorrhage, and the limitations of CT in posterior fossa lesions
- know how to manage stroke if neither thrombolysis nor clot retrieval is possible
- appreciate the possibility of hydrocephalus developing with posterior fossa strokes
- appreciate the prognosis of such a stroke, and the need to manage family expectations.
A detailed discussion of the definitive management options in acute stroke is available elsewhere.
Supportive management of acute stroke is also covered in a summary article.
If one were to summarise in brief the approach to management here, it would resemble this:
Definitive management option:
- Intravenous thrombolysis
- Intraarterial thrombolysis
- Endovascular embolectomy
- Conservative management and subsequent antiplatelet therapy
Supportive management:
- Airway: intubation, for the protection thereof (being mindful that it may be futile)
- Ventilation: aiming for normocapnea
- Circulatory support: to keep BP normal, and below 220 mmHg systolic
- Sedation: as needed to tolerate ICU management in comfort
- Electrolyte and endocrine control: ensuring normoglycaemia and normothermia
- Fluid balance management to ensure protection of renal function following contrast
- Enteric nutrition may commence by the nasogastric route
- Heparin is not indicated given the risk of haemorrhagic transformation*
- Antibiotic therapy if contaminated aspiration is suspected
*It should be pointed out that in a previous incarnation of this question (2011), the college suggested the use of a heparin infusion. This strategy has now fallen out of favour, given that it seems to kill people. Certainly, the 2007 AHA guidelines were not in favour of its use. In spite of this, the heparin anachronism has also been repeated in the college answer to this question.
References
Oh's Intensive Care manual: Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer. This chapter of Oh's has the distinction of having very few tables in it - there are only two, for an extremely long block of text.
The Internet Stroke Centre has an excellent summary of stroke syndromes.
Kammersgaard, Lars Peter, et al. "Short-and long-term prognosis for very old stroke patients. The Copenhagen Stroke Study." Age and Ageing 33.2 (2004): 149-154.
National Collaborating Centre for Chronic Conditions (Great Britain). "Stroke: national clinical guideline for diagnosis and initial management of acute stroke and transient ischaemic attack (TIA)." Royal College of Physicians, 2008.
Friedman, Howard S., W. J. Koroshetz, and N. Qureshi. "Tissue plasminogen activator for acute ischemic stroke." N Engl J Med. 1995;333(24):1581.
Trialists’Collaboration, Stroke Unit. "Organised inpatient (stroke unit) care for stroke." Cochrane database of systematic reviews 4 (2013).
Foerch, C., et al. "Survival and quality of life outcome after mechanical ventilation in elderly stroke patients." Journal of Neurology, Neurosurgery & Psychiatry 75.7 (2004): 988-993.
Bath, Philip MW, Robert Iddenden, and Fiona J. Bath. "Low-molecular-weight heparins and heparinoids in acute ischemic stroke a meta-analysis of randomized controlled trials." Stroke 31.7 (2000): 1770-1778.
Sherman, David G., et al. "The efficacy and safety of enoxaparin versus unfractionated heparin for the prevention of venous thromboembolism after acute ischaemic stroke (PREVAIL Study): an open-label randomised comparison."The Lancet 369.9570 (2007): 1347-1355.
Wartenberg, Katja E. "Malignant middle cerebral artery infarction." Current opinion in critical care 18.2 (2012): 152-163.
Kasuya, Yusuke, et al. "Ventilator-associated pneumonia in critically ill stroke patients: frequency, risk factors, and outcomes." Journal of critical care 26.3 (2011): 273-279.
Nogueira, R. G., et al. "Endovascular approaches to acute stroke, part 2: a comprehensive review of studies and trials." American Journal of Neuroradiology30.5 (2009): 859-875.
Brinjikji, Waleed, et al. "Patient outcomes with endovascular embolectomy therapy for acute ischemic stroke a study of the national inpatient sample: 2006 to 2008." Stroke 42.6 (2011): 1648-1652.
Kidwell, Chelsea S., et al. "Design and rationale of the mechanical retrieval and recanalization of stroke clots using embolectomy (mr rescue) trial."International Journal of Stroke 9.1 (2014): 110-116.
Jansen, Olav, et al. "Neurothrombectomy for the treatment of acute ischemic stroke: results from the TREVO study." Cerebrovascular Diseases 36.3 (2013): 218-225.
Mayer, Stephan A., et al. "Cost and outcome of mechanical ventilation for life-threatening stroke." Stroke 31.10 (2000): 2346-2353.
Meyfroidt, Geert, Pierre-Edouard Bollaert, and Paul E. Marik. "Acute ischemic stroke in the ICU: to admit or not to admit?." Intensive care medicine 40.5 (2014): 749-751.
Golestanian, Ellie, Jinn-Ing Liou, and Maureen A. Smith. "Long-term survival in older critically ill patients with acute ischemic stroke." Critical care medicine37.12 (2009): 3107.
de Courten-Myers, Gabrielle M., et al. "Hemorrhagic infarct conversion in experimental stroke." Annals of emergency medicine 21.2 (1992): 120-126.
Rosso, Charlotte, et al. "Intensive Versus Subcutaneous Insulin in Patients With Hyperacute Stroke Results From the Randomized INSULINFARCT Trial."Stroke 43.9 (2012): 2343-2349.
Gilmore, Rachel M., and Latha G. Stedd. "The role of hyperglycemia in acute ischemic stroke." Neurocritical care 5.2 (2006): 153-158.
Wrotek, Sylwia E., et al. "Treatment of fever after stroke: conflicting evidence."Pharmacotherapy: The Journal of Human Pharmacology and Drug Therapy31.11 (2011): 1085-1091.
Poca, Maria Antonia, et al. "Monitoring intracranial pressure in patients with malignant middle cerebral artery infarction: is it useful? Clinical article." Journal of neurosurgery 112.3 (2010): 648-657.
Llinas, Rafael H. "Ischemic stroke and ICU care." Seminars in neurology. Vol. 28. No. 5. 2008.
Adams, Harold P., et al. "Guidelines for the Early Management of Adults With Ischemic Stroke " Circulation 115.20 (2007): e478-e534.
Wang, Xia, et al. "Magnitude of Blood Pressure Reduction and Clinical Outcomes in Acute Intracerebral Hemorrhage Intensive Blood Pressure Reduction in Acute Cerebral Hemorrhage Trial Study." Hypertension (2015): HYPERTENSIONAHA-114.
Arima, Hisatomi, et al. "Optimal achieved blood pressure in acute intracerebral hemorrhage INTERACT2." Neurology 84.5 (2015): 464-471.
Question 15.3 - 2017, Paper 1
This is the second part of a multi-part SAQ. The first part was as follows:
You are called to review a 48-year-old male in the post-operative recovery unit (PACIJ) who has just undergone resection of a TSH-secreting pituitary adenoma via a trans-sphenoidal approach. He is febrile (38.5'C) and is hypertensive (160/50 mmHg) with tachycardia (130 beats/min) and hyper-dynamic circulation, and is hyper-reflexic.
Give the likely diagnosis. (10% marks)
List your immediate pharmacological management. (30% marks)
The patient subsequently recovered and was discharged home. He re-presented two weeks later with increasing drowsiness, confusion, fevers, neck stiffness and a clear nasal discharge.
Give the likely diagnosis. (10% marks)
Briefly outline your immediate management. (30% marks)
Three days after re-admission, the same patient was the subject of a Rapid Response System (RRS) call for decreased consciousness.
Images 1 and 2 (both shown On page 12) are slices from the CT head scan taken at the time of this event.

What complication has occurred? (20% marks)
College answer
e) Tension pneumocephaly (Mount Fuji sign) secondary to malpositioned nasopharyngeal airway tube
Discussion
This image was stolen shamelessly from a 2015 paper by Dabdoub et al. The college image had a lot more air in the various inner spaces of the skull, and there was no conspicuous burrhole in the bony windows images.
Also, there was a malpositioned nasopharyngeal airway. Can you people guess how hard it is to find a CT with pneumoencephalus and an intracranial nasopharyngeal airway? One can hardly find examples of the latter, even though it appears to be frighteningly common; and when you do they look like this one from Muzzi et al (1991)

Anyway. After having their TSH-oma resection complicated by thyroid storm and basal meningitis, the poor patient now has tension pneumoencephalus. The characteristic feature of tension in this case is the lens-like curvature of the air pocket, suggesting that it is pushing on the brain tissue.
References
Dabdoub, Carlos B., et al. "Review of the management of pneumocephalus."Surgical neurology international 6 (2015).
Question 27 - 2017, Paper 1
Critically evaluate the role of induced hypothermia in the management of traumatic brain injury.
College answer
Induced hypothermia refers to the use of techniques to intentionally lower the core body temperature below a physiological level (i.e. <36 degrees), in this case, in a patient with a traumatic brain injury.
Rationale
• Reduction in metabolic rate
• Reduction in oedema
• Modification of the inflammatory response
Indications
Prophylactic (early)
Therapeutic (for the management of elevated intracranial pressure)
Advantages
• Reduction in core body temperature is associated with a reduction in cerebral metabolic
rate and reduction in cerebral blood flow
• Will be associated with a reduction in intracranial pressure
• Noted cerebral protective effect in animal models and in case reports of survival with good
neurological recovery in hypoxic ischaemic encephalopathy in patients with severe
accidental hypothermia
• Known that hyperthermia is associated with worse neurological outcomes
Adverse effects
• Requires sedation and neuromuscular blockade with the attendant adverse effects
• Lower temperature predisposes to infective complications, in particular pneumonia
• Coagulopathy
• Cardiac dysrhythmias
• Overshoot can expose patients to adverse effects of more severe hypothermia
o Dysrhythmia
o Diuresis and electrolyte disturbance
o Immune suppression
• Adverse effects of cooling devices (loss of skin integrity) and monitoring devices
(epistaxis)
• Cost of prolonged ICU stay and increased requirement for intervention and monitoring
Evidence
• Initial studies and meta-analysis showed promising results with regards to improved
neurological outcomes
• Subsequent studies are less positive
Cochrane Systematic Review 2009
No evidence of benefit.
Significant benefit shown in low quality trials with tendency to over-estimate the treatment effect
Prophylactic Hypothermia:
• Nine class I and II studies, and 3 Class III studies summarised in BTF.
• Since then two paediatric studies and a Japanese study have been published
Brain Trauma Foundation (2016):
“Level II B: Early (within 2.5 hours), short-term (48 hours post-injury) prophylactic hypothermia is not recommended to improve outcomes in patients with diffuse injury”.
Elevated ICP management:
• EUROTHERM-3235 study
o Induced hypothermia has an effect on reducing intracranial pressure, but the effect on
outcome is variable
o Little clinical evidence on the effect on other important aspects of cerebral physiology
e.g. cerebral blood flow or cellular metabolism
Summary
• It is important to avoid hyperthermia
• Routine use of induced hypothermia in all TBI patients is not warranted
• Careful reduction in core body temperature may help control ICP in selected severe TBI
patients who may otherwise be at risk of a decompressive craniectomy.
• Await results of high-quality RCTs
Discussion
Introduction:
- Induced hypothermia in traumatic brain injury is the therapeutic or prophylactic use of lower body temperature, to prevent secondary brain injury or to relieve refractory raised ICP.
Rationale:
- Decreased cellular injury
- Decreased neuronal apoptosis (Xu et al, 2002)
- Decreased production of oxygen free radicals (Globus et al, 1995)
- Reduced excitotoxicity (Busto et al, 1989)
- Suppression of epileptic activity also decreases the risk of excitotoxicity
- Decreased inflammatory response and oedema
- Impairment of neutrophil and macrophage function should decrease the size of the injury and mitigate the oedema (Siesjö et al, 1989)
- Decreased permeability of the blood-brain barrier, also decreasing the oedema (Fischer et al, 1999)
- Decreased cerebral metabolic rate, with many benefits:
- Decrease oxygen and glucose consumption by the oedematous brain tissue (by 6-10% per 1°C - Polderman, 2001 )
- Decreased intracranial pressure (thus, improved perfusion of the healthy brain)
Arguments against the use of hypothermia in TBI
- The studies exploring its benefits have been either human case series or animal data
- The technique is not without risk (i.e. even mild hypothermia has a rate of significant complications):
- Arrhythmias (AF, bradycardia)
- Diuresis, hypokalemia
- Need for paralysis and sedation
- Poor neutrophil function: the rate of infectious complications is relatively high, eg. pneumonia (POLAR, 2018 had 70% vs 57% in the normothermic group)
- Higher catecholamine reuqirements (POLAR, 2018): Catecholamine responsiveness is diminished at low temperature, making CPP more difficult to achieve with noradrenaline
- The deeper the hypothermia, the greater the risk of complications
- Haemodynamic instability in hypothermia may decrease CPP
- Decreased platelet function may lead to expansion of conservatively managed haemorrhages or contusions
Evidence for and against hypothermia in TBI
- Eurotherm 3235 trial (2015):
- Enrolled 387 patients;
- Hypothermia was used as a second-line therapy to reduce ICP.
- No survival benefit was observed.
- Recruitment was suspended early owing to safety concerns.
- ICP control was in fact better in the hypothermia group (they required rescue therapies less frequently) but this seems to have made no difference to mortality.
- "Cochrane Systematic Review 2009" probably refers to Sydenham et al (2009). A new update was published by Lewis et al in 2017. Neither meta-analysis found any benefit (the 2009 version recommended that hypothermia should be relegated to the realm of experimental trial interventions rather than established practice).
- POLAR (2018)
- Enrolled 511 patients
- Hypothermia was commenced early and sustained for at least 72 hours
- There was no difference in neurological outcome between the groups
- "These findings do not support the use of early prophylactic hypothermia in patients with severe traumatic brain injury", they concluded
"Own practice"
- Prophylactic hypothermia for severe TBI is not indicated in routine practice
- Therapeutic hypothermia for severe TBI with refractory raised ICP may reduce the ICP, and is an alternative or adjunct to decompressive craniectomy
If the college examiners had any investment in the process of writing these answers, they'd probably have offered their trainees some references beyond "two paediatric studies and a Japanese study". At least one of the "two paediatric studies" is Hutchison et al (2008), who concluded that prophylactic hypothermia "does not improve the neurologic outcome and may increase mortality". The other paediatric trial may be Li et al (2009), which came to totally opposite conclusions ( "moderate hypothermia provided neuronal protection for children with severe TBI, and maintaining the intracranial temperature at 34.5°C for 72 h was safe"). Looking at the list of trials undergoing meta-analysis in Lewis et al (2017), the "Japanese study" is probably Hifumi et al (2016), whose B-HYPO trial did not find any significant difference in mortality or neurological outcome among 135 adult patients.
References
Sedzimir, C. B. "Therapeutic Hypothermia in Cases of Head Injury*." Journal of neurosurgery 16.4 (1959): 407-414.
Rosomoff, Hubert L. "Experimental Brain Injury During Hypothermia*." Journal of neurosurgery 16.2 (1959): 177-187.
Lundberg, Nils, Kai C. Nielsen, and Eric Nilsson. "Deep Hypothermia in Intracranial Surgery*." Journal of neurosurgery 13.3 (1956): 235-247.
Jennett, B., et al. "Treatment for severe head injury." Journal of Neurology, Neurosurgery & Psychiatry 43.4 (1980): 289-295.
Drake, C. G., and T. A. Jory. "Hypothermia in the treatment of critical head injury." Canadian Medical Association journal 87.17 (1962): 887.
Marion, Donald W., et al. "Treatment of traumatic brain injury with moderate hypothermia." New England Journal of Medicine 336.8 (1997): 540-546.
Fay, T. "Observations on generalized refrigeration in cases of severe cerebral trauma." Assoc Res Nerv Ment Dis Proc. Vol. 24. 1945.
Polderman, Kees H. "Mechanisms of action, physiological effects, and complications of hypothermia." Critical care medicine 37.7 (2009): S186-S202.
Xu, Lijun, et al. "Mild hypothermia reduces apoptosis of mouse neurons in vitro early in the cascade." Journal of Cerebral Blood Flow & Metabolism 22.1 (2002): 21-28.
Globus, Mordecai Y‐T., et al. "Detection of free radical activity during transient global ischemia and recirculation: effects of intraischemic brain temperature modulation." Journal of neurochemistry 65.3 (1995): 1250-1256.
Busto, Raul, et al. "Effect of mild hypothermia on ischemia-induced release of neurotransmitters and free fatty acids in rat brain." Stroke 20.7 (1989): 904-910.
Siesjö, Bo K., et al. "Calcium, Excitotoxins, and Neuronal Death in the Brain." Annals of the New York Academy of Sciences 568.1 (1989): 234-251.
Fischer, Silvia, et al. "Hypothermia abolishes hypoxia-induced hyperpermeability in brain microvessel endothelial cells." Molecular brain research 74.1 (1999): 135-144.
Schmutzhard, Erich, et al. "Therapeutic hypothermia: The rationale." Critical Care 16.2 (2012): 1.
Andrews, Peter JD, et al. "Hypothermia for intracranial hypertension after traumatic brain injury." New England Journal of Medicine 373.25 (2015): 2403-2412.
Cooper, D. James, et al. "Effect of early sustained prophylactic hypothermia on neurologic outcomes among patients with severe traumatic brain injury: the POLAR randomized clinical trial." JAMA (2018) Published online October 24, 2018. doi:10.1001/jama.2018.17075
Hutchison, James S., et al. "Hypothermia therapy after traumatic brain injury in children." New England Journal of Medicine 358.23 (2008): 2447-2456.
Hifumi, Toru, et al. "Fever control management is preferable to mild therapeutic hypothermia in traumatic brain injury patients with abbreviated injury scale 3–4: a multi-center, randomized controlled trial." Journal of neurotrauma 33.11 (2016): 1047-1053.
Li, Hao, et al. "Protective effect of moderate hypothermia on severe traumatic brain injury in children." Journal of neurotrauma 26.11 (2009): 1905-1909.
Question 24 - 2017, Paper 2
With respect to the management of patients with aneursymal sub arachnoid haemorrhage (aSAH), briefly discuss the role of the following:
- Nimodipine.
- Hypertensive I hypervolaemic I haemodilution, (HHH) therapy.
- Magnesium.
- lnterventional radiology.
College answer
Nimodipine;
Level I evidence of improved neurological outcome. Calcium antagonist. Likely prevents neuronal damage by preventing influx of Ca more than by antagonising Sm muscle contraction and directly reducing incidence of vasospasm. May lead to hypotension.
Meta-analyses suggest oral efficacious
IV expensive; needs co-infusion
Recommended for all patients with aneurysmal SAH
Triple H therapy:
Haemodilution – no good evidence that works in isolation. Theoretically improved rheology => better perfusion
Hypervolaemia – no evidence that hypervolaemia is beneficial and fluid overload associated with worse outcomes. Hypovolaemia should be avoided as may exacerbate vasospasm. Volume loading often given to patients with clinical vasospasm to ensure euvolaemia
Hypertensive therapy: Unsecured aneurysm a relative CI to HT therapy. Demonstrated to improve cerebral blood flow. Not useful for prevention of vasospasm, but commonly used to treat cerebral ischaemia in the presence of vasospasm. May be titrated to clinical response. NA favoured agent. Sometimes high doses of pressor agents required to augment MAP. Risk of stress cardiomyopathy. Unless titrated to clear neurological signs the optimal MAP goals are unclear. Balance of risks vs benefits.
Interventional Radiology
Intra-arterial vasodilators: e.g. verapamil / papaverine / nicardipine. Clear angiographic benefit / used routinely for the treatment of vasospasm. Lacking high-level data on outcome benefit. Other angiographic interventions such as ballooning / stents are also utilised to good angiographic effect. Not routinely available in all centres. Caries the risks associated with angiography (transport, anaesthesia, contrast use, vascular injury, stroke)
Magnesium:
Several trials of MgSO4 – these have failed to show benefit. Not routinely indicated for the prevention of vasospasm although low magnesium may be associated with its development.
Discussion
The college question - though asking about therapeutic options which are mainly used to prevent or treat vasospasm - is actually not worded in a way which limits one's answer to only vasospasm. Therefore, some additional material could be added to the interventional radiology section, which deals more with its merits as a diagnostic modality.
Nimodipine
- The objective is to prevent symptomatic vasospasm, i.e. features of ischaemia and radiologically obvious strokes
- The BRANT trial: patients receiving nimodipine were 34% less likely to develop stroke. One ought to continue nimodipine for 21 days to get the optimal effect.
- Owing to the difficulty in identifying patients who will go on to develop vasospasm, nimodipine is given to all SAH patients.
"Triple H therapy"
- Largely discredited practice of forced hypervolemia, hypertension and haemodilution.
- A Cochrane review of this "circulatory volume expansion therapy" (2004) did not find any benefit. However, there was only one RCT and one "quasi-randomised" trial. The numbers were simply too small to make a recommendation.
- On purely theoretical physiological grounds, as well as from the standpoint of lacking evidence, this therapy was savagely shredded by Myburgh in an excellent review article (2005)
- Hypertension is the only component broadly supported by a consensus of neurosurgeons.
Magnesium infusion
- Divalent cation which acts as a physiological antagonist for calcium, i.e. it is analogous to using a calcium channel blocker.
- Should relax smooth muscle, and therefore either treat and/or prevent vasospasm.
- MASH-2 trial from 2012: a multi-center investigation of 64mmol of MgSO4 per day, randomised among 606 patients; no benefit: "intravenous magnesium sulphate does not improve clinical outcome after aneurysmal subarachnoid haemorrhage".
Conventional 4 vessel DSA (Digital Subtraction Angiography):
- DSA has several possible roles to play in the management of SAH:
- Diagnostic:
- It can be used to characterise the aneurysm (eg. to determine whether it can, or cannot be managed by coiling)
- It can discriminate aneurysmal bleeds from AVMs
- It can be used to look for an aneurysm in CT-negative SAH - in fact the AHA/ASA guidelines recommend this wherever there is no obvious aneurysm on the CT angiogram, according to https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5288992/Grasso et al (2017)
- Definitive therapeutic:
- On susceptible aneurysms, coiling could be attempted
- Diagnostic:
- This is the gold standard for both diagnosis and management of vasospasm. One can confirm that vasospasm is occurring by a CT angiogram- or, if one were to go straight to DSA one could progress to some sort of definitive treatment. Verapimil and papaverine are the two most commonly used intra-arterial vasodilators.
- However, this requires a skilled interventional radiologist. It exposes the patient to contrast and it it in vasive, with a (not insignificant - around 1%) risk of atheroma embolism or vessel dissection..
- There is a small chance that this technique will lead to over-treatment: vessel narrowing may be detected, but this decrease in diameter may not reflect a decrease in flow, and may not warrant an injection of vasodilator.
References
Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer
LITFL offer this reference as a follow-on to their chapter:
Dabus, Guilherme, and Raul G. Nogueira. "Current Options for the Management of Aneurysmal Subarachnoid Hemorrhage-Induced Cerebral Vasospasm: A Comprehensive Review of the Literature." Interventional Neurology 2.1 (2013): 30-51.
Frontera, Jennifer A., et al. "Defining Vasospasm After Subarachnoid Hemorrhage What Is the Most Clinically Relevant Definition?." Stroke 40.6 (2009): 1963-1968.
Vergouwen, Mervyn DI, et al. "Definition of Delayed Cerebral Ischemia After Aneurysmal Subarachnoid Hemorrhage as an Outcome Event in Clinical Trials and Observational Studies Proposal of a Multidisciplinary Research Group."Stroke 41.10 (2010): 2391-2395.
Etminan, Nima, et al. "Effect of pharmaceutical treatment on vasospasm, delayed cerebral ischemia, and clinical outcome in patients with aneurysmal subarachnoid hemorrhage: a systematic review and meta-analysis." Journal of Cerebral Blood Flow & Metabolism 31.6 (2011): 1443-1451.
Brathwaite, Shakira, and R. Loch Macdonald. "Current Management of Delayed Cerebral Ischemia: Update from Results of Recent Clinical Trials." Translational stroke research 5.2 (2014): 207-226.
Mir, D. I. A., et al. "CT Perfusion for detection of delayed cerebral ischemia in aneurysmal subarachnoid hemorrhage: a systematic review and meta-analysis." American Journal of Neuroradiology 35.5 (2014): 866-871.
Scheglov, Dmitry V., et al. "Endovascular Treatment of Vasospasm Related to Acute Subarachnoid Hemorrhage from Ruptured Aneurysms." Neurovascular Events After Subarachnoid Hemorrhage. Springer International Publishing, 2015. 223-229.
Serrone, Joseph C., et al. "Aneurysmal subarachnoid hemorrhage: pathobiology, current treatment and future directions." Expert review of neurotherapeutics 0 (2015): 1-14.
Rinkel, Gabriel JE, et al. "Circulatory volume expansion therapy for aneurysmal subarachnoid haemorrhage." The Cochrane Library (2004).
Connolly, E. Sander, et al. "Guidelines for the management of aneurysmal subarachnoid hemorrhage a guideline for healthcare professionals from the American heart association/American stroke association." Stroke 43.6 (2012): 1711-1737.
Macdonald, R. Loch, et al. "Clazosentan to overcome neurological ischemia and infarction occurring after subarachnoid hemorrhage (CONSCIOUS-1) randomized, double-blind, placebo-controlled Phase 2 dose-finding trial." Stroke39.11 (2008): 3015-3021.
Mees, Sanne M. Dorhout, et al. "Magnesium for aneurysmal subarachnoid haemorrhage (MASH-2): a randomised placebo-controlled trial." The Lancet380.9836 (2012): 44-49.
Zhang, Shihong, et al. "Tirilazad for aneurysmal subarachnoid haemorrhage."The Cochrane Library (2010).
Liu, Guang Jian, et al. "Systematic assessment and meta-analysis of the efficacy and safety of fasudil in the treatment of cerebral vasospasm in patients with subarachnoid hemorrhage." European journal of clinical pharmacology 68.2 (2012): 131-139.
Kirkpatrick, Peter J., et al. "Simvastatin in aneurysmal subarachnoid haemorrhage (STASH): a multicentre randomised phase 3 trial." The Lancet Neurology 13.7 (2014): 666-675.
Yoneda, Hiroshi, et al. "A prospective, multicenter, randomized study of the efficacy of eicosapentaenoic acid for cerebral vasospasm: the EVAS study."World neurosurgery 81.2 (2014): 309-315.
Teasdale, G. M., et al. "A universal subarachnoid hemorrhage scale: report of a committee of the World Federation of Neurosurgical Societies." Journal of neurology, neurosurgery, and psychiatry 51.11 (1988): 1457.
Connolly, E. Sander, et al. "Guidelines for the Management of Aneurysmal Subarachnoid Hemorrhage A Guideline for Healthcare Professionals From the American Heart Association/American Stroke Association." Stroke 43.6 (2012): 1711-1737.
Myburgh, J. A. "Triple h” therapy for aneurysmal subarachnoid haemorrhage: real therapy or chasing numbers." Crit Care Resusc 7.3 (2005): 206-212.
Bederson, Joshua B., et al. "Guidelines for the management of aneurysmal subarachnoid hemorrhage a statement for healthcare professionals from a special Writing Group of the Stroke Council, American Heart Association."Stroke 40.3 (2009): 994-1025.
Muizelaar, J. Paul, and Donald P. Becker. "Induced hypertension for the treatment of cerebral ischemia after subarachnoid hemorrhage. Direct effect on cerebral blood flow." Surgical neurology 25.4 (1986): 317-325.
Dhar, Rajat, et al. "Comparison of induced hypertension, fluid bolus, and blood transfusion to augment cerebral oxygen delivery after subarachnoid hemorrhage: Clinical article." Journal of neurosurgery 116.3 (2012): 648-656.
Pickard, J. D., et al. "Effect of oral nimodipine on cerebral infarction and outcome after subarachnoid haemorrhage: British aneurysm nimodipine trial."BMJ: British Medical Journal 298.6674 (1989): 636.
Origitano, Thomas C., et al. "Sustained increased cerebral blood flow with prophylactic hypertensive hypervolemic hemodilution (" triple-H" therapy) after subarachnoid hemorrhage." Neurosurgery 27.5 (1990): 729-740.
Marshall, Scott A., Paul Nyquist, and Wendy C. Ziai. "The role of transcranial Doppler ultrasonography in the diagnosis and management of vasospasm after aneurysmal subarachnoid hemorrhage." Neurosurgery Clinics of North America21.2 (2010): 291-303.
Greenberg, E. D., et al. "Diagnostic accuracy of CT angiography and CT perfusion for cerebral vasospasm: a meta-analysis." American Journal of Neuroradiology 31.10 (2010): 1853-1860.
Sloan, M. A., et al. "Sensitivity and specificity of transcranial Doppler ultrasonography in the diagnosis of vasospasm following subarachnoid hemorrhage." Neurology 39.11 (1989): 1514-1514.
Rivierez, M., et al. "Value of electroencephalogram in prediction and diagnosis of vasospasm after intracranial aneurysm rupture." Acta neurochirurgica 110.1-2 (1991): 17-23.
Kawamoto, Shunsuke, et al. "Effectiveness of the head-shaking method combined with cisternal irrigation with urokinase in preventing cerebral vasospasm after subarachnoid hemorrhage." Journal of neurosurgery 100.2 (2004): 236-243.
Vergouwen, Mervyn DI, et al. "Biologic effects of simvastatin in patients with aneurysmal subarachnoid hemorrhage: a double-blind, placebo-controlled randomized trial." Journal of Cerebral Blood Flow & Metabolism 29.8 (2009): 1444-1453.
Macdonald, R. Loch, et al. "Clazosentan to Overcome Neurological Ischemia and Infarction Occurring After Subarachnoid Hemorrhage (CONSCIOUS-1) Randomized, Double-Blind, Placebo-Controlled Phase 2 Dose-Finding Trial."Stroke 39.11 (2008): 3015-3021.
Bakker, Nicolaas A., et al. "International subarachnoid aneurysm trial 2009: endovascular coiling of ruptured intracranial aneurysms has no significant advantage over neurosurgical clipping." Neurosurgery 66.5 (2010): 961-962.
Fisher, C. M., J. P. Kistler, and J. M. Davis. "Relation of cerebral vasospasm to subarachnoid hemorrhage visualized by computerized tomographic scanning." Neurosurgery 6.1 (1980): 1-9.
Grasso, Giovanni, Concetta Alafaci, and R. Loch Macdonald. "Management of aneurysmal subarachnoid hemorrhage: State of the art and future perspectives." Surgical neurology international 8 (2017).
Question 3 - 2018, Paper 1
a) How are the World Federation of Neurosurgeons Score (WFNS) and the Fisher score calculated in the grading of aneurysmal subarachnoid haemorrhage (SAH)? (40% marks)
b) What are the limitations of using these scores in the first 24 hours after the onset of SAH to determine prognosis? (60% marks)
College answer
- WFNS (clinical grade)
- I – GCS 15, no motor deficit
- II – GCS 13-14, no motor deficit
- III – GCS 13-14 and motor deficit
- IV – GCS 7-12 +/- motor deficit
- V – GCS 3-6 +/- motor deficit
- Fisher (radiological grade, based on brain CT)
- I – no blood
- II – diffuse deposition of SAH without clots or layers of blood < 1mm
- III – localized clots and /or vertical layers of blood 1 mm or more in thickness
- IV – diffuse or no subarachnoid blood but intracerebral or intraventricular clots
WFNS is a clinically graded score – gives information on prognosis
WFNS 3+ worse outcome
Fisher gives information on vasospasm risk
Fisher 3+ higher risk of vasospasm
Limitations of grading systems:
Neither have high sensitivity or specificity for outcomes
The scores may alter depending on when they are calculated – initial presentation, on arrival to ED or on arrival ICU
Sedation or paralysis can confound the interpretation
Effects of hydrocephalus or seizure – may suggest an initially unfavourable outcome,
Effects of rebleed may confound an initial positive grade
Expert assessment is required for radiological interpretation WFNS uses GCS score which has poor inter-rater reliability
Examiners Comments:
Many candidates failed to address the specific limitations of the scores and instead described general issues effecting prognosis in subarachnoid haemorrhage. Several failed to mention both scoring systems. Overall there was poor knowledge of the scoring systems.
Discussion
For answering this questions, no single reference is better than the 2005 review article by David Rosen.
a) In answer to the question "how are scores calculated", one may discuss the philosophy underlying the scoring system, or - more realistically - list the values used to calculate the scores. For reference and to simplify revision, links to the original articles are offered below, together with the grading system.
- Grade 1: GCS 15, no motor deficit.
- Grade 2: GCS 13-14 without deficit
- Grade 3: GCS 13-14 with focal neurological deficit
- Grade 4: GCS 7-12, with or without deficit.
- Grade 5: GCS <7 , with or without deficit.
- Grade 1 - no haemorrhage
- Grade 2 - SAH less than 1mm thick, diffuse
- Grade 3 - SAH more than 1mm thick, with localised clots
- Grade 4 - intraventricular or parenchymal extension, with clots
b)
Limitations of the Fisher score
- It was developed when the imaging resolution was approximately 1\20th of what is currently available
- It may be difficult to apply for staff who are unfamiliar with CT imaging
- It was validated in a small series of patients (by Kistler et al, 1981)
- Grade 1 and 2 are very uncommon
- Clot density and clot clearance rate are important factors which infuence the development of vasospasm, but which are not included in the scale. The same score (4) is given to the patient with a tiny speck of blood in the ventricle, as well as to the patient whose ventricles are full of thick clot.
- Unlikelty clinical scoring systsems, it does not correlate very well with clinical outcome- only with vasospasm
Limitations of the WFNS system
- It relies on the accurate application of the GCS
- It does not incorporate imaging data
- It is unclear whether adding the additional focal neurodeficit dimension has any added benefit to the prognostic power of the scoring system (It may well be that admission GCS is the single best predictor of neurological outcome)
- the expert committee behind the WFNS did not explain the reasoning behind the specific GCS breakpoints used for their definition
- Grade 4, which represents a range of GCS scores between 7 and 12, includes a group of patients who may have widely different outcomes.
- There is a significant step in the likelihood of poor outcome between Grade 2 and Grade 3 (0.61 vs 1.78)
- There are very few Grade 3 patients in all studies of WFNS (usually, ~ 3%)
References
Drake, Charles G. "Report of World Federation of Neurological Surgeons Committee on a universal subarachnoid hemorrhage grading scale." J neurosurg 68 (1988): 985-986.
Fisher, C. M., J. P. Kistler, and J. M. Davis. "Relation of cerebral vasospasm to subarachnoid hemorrhage visualized by computerized tomographic scanning." Neurosurgery 6.1 (1980): 1-9.
Rosen, David S., and R. Loch Macdonald. "Subarachnoid hemorrhage grading scales." Neurocritical care 2.2 (2005): 110-118.
Question 17 - 2018, Paper 1
List the potential causes of polyuria during the immediate post-operative period in a patient who has undergone surgery for a pituitary tumour.
For each cause listed, outline the following:
i. Mechanism of action,
ii. Approach to diagnosis, and
iii. Management
College answer
Central Diabetes Insipidus-
Mechanism of action-
Anatomic injury to hypothalamus, pituitary stalk or posterior pituitary gland. Usually partial or total disruption of pituitary stalk-severs connections between cell bodies of ADH secreting neurons in hypothalamus and their nerve endings in posterior pituitary preventing ADH secretion.
ADH acts at the V2 receptor via cAMP and is responsible for the insertion and removal of water (aquaporin) channels into luminal membrane of renal tubules thereby altering permeability to water.
Approach to diagnosis-
Hypotonic polyuria- Urine output >300ml/hr x 3hrs OR >2.5ml/kg/hr OR >3L/day. Urine osmolality<200mOsm/kg (urine specific gravity <1.010), Hypernatraemia. Lab parameters may be affected if patient has access to free water.
Management-
DDAVP (Desmopressin) 1-4mcg SC or IM (OR short acting AVP analogue), monitor urine output, watch for hyponatraemia developing. Allow to drink to thirst if possible and monitor. Exclude other causes of polyuria (as below). Monitor urine and serum osmolality and electrolytes.
Hyperglycaemia-
Mechanism of action-
Osmotic diuresis from high blood glucose levels.
Approach to diagnosis-
Presence of high blood glucose levels in the context of glucocorticoid administration following pituitary tumour resection or from Cushing’s disease or GH-secreting tumour.
Management-
Correct BGLs with insulin. Correct volume deficit and monitor fluid balance, electrolytes.
High volume IV fluid administration-
Mechanism of action-
High volume IV fluid administration intra-operatively
Approach to diagnosis-
Evidence of high volume IV fluids, electrolytes measured may vary with fluid administered
Management-
Should be self-limiting. Monitor urine output/electrolytes.
Acute fall in Growth Hormone-
Mechanism of action-
Drop of blood levels of GH and IGF-1 that cause fluid retention when inappropriately high due to a GH-secreting tumour.
Approach to diagnosis-
Context of GH secreting tumour and acromegaly. Serum and urine electrolytes and osmolalities should be in reference range.
Management-
Should be self-limiting. Monitor urine output/electrolytes.
Mannitol administration-
Mechanism of action-
Osmotic diuresis
Approach to diagnosis-
Administration of mannitol due to large tumour/cerebral oedema (unusual). Osmolar gap may be seen.
Management-
Should be self-limiting. Monitor urine output/electrolytes
Examiner Comments:
Maximum score if Diabetes Insipidus not mentioned was 4 marks. Must have mentioned at least two causes to achieve passing mark.
Discussion
As a tabulated answer, this has the distinct disadvantage of requiring a level of detail which does not lend itself to elegant distribution into narrow columns. There is simply too much to write about. The table which follows represents distilled information from the excellent articles by Prete et al (2017) and Hensen et al (1999)
| Mechanism | Diagnosis | Management |
|
Central diabetes insipidus |
||
|
|
|
|
Cerebral salt wasting |
||
|
|
|
|
Perioperative IV fluids |
||
|
|
|
|
Osmotic diuresis |
||
|
|
|
|
|
|
| Acute fall in growth hormone (GH) levels | ||
|
|
|
References
Guerrero, R., et al. "Early hyponatraemia after pituitary surgery: cerebral salt-wasting syndrome." European journal of endocrinology 156.6 (2007): 611-616.
Hensen, Johannes, et al. "Prevalence, predictors and patterns of postoperative polyuria and hyponatraemia in the immediate course after transsphenoidal surgery for pituitary adenomas." Clinical endocrinology 50.4 (1999): 431-439.
Hans, Pol, Achille Stevenaert, and Adelin Albert. "Study of hypotonic polyuria after trans-sphenoidal pituitary adenomectomy." Intensive care medicine 12.2 (1986): 95-99.
Kamenický, Peter, et al. "Growth hormone, insulin-like growth factor-1, and the kidney: pathophysiological and clinical implications." Endocrine reviews 35.2 (2013): 234-281.
Question 23 - 2018, Paper 1
An 81 -year-old female with critical aortic stenosis has a valve replacement procedure. Post-operatively
she is diagnosed with an anterior spinal artery syndrome at the T6-T7 level on an MRI.
a) Describe the signs you would expect on sensory examination of her lower limbs. (20% marks)
b) What are the deep tendon reflexes likely to show? (20% marks)
c) What perioperative factors may contribute to this syndrome? (30% marks)
d) What therapies have been advocated to optimise spinal cord perfusion? (30% marks)
College answer
- Sensory neurological examination of the lower limbs would reveal loss of pain and temperature sensation with a sensory level of T6-T7 with relative sparing of proprioception and vibratory sense below this level.
- The acute stages are characterised by flaccidity and loss of deep tendon reflexes (with spasticity and hyperreflexia developing over ensuing days and weeks).
- Prolonged aortic cross clamp ,low perfusion pressure to the spinal cord as well as IABP, or ECMO are associated with spinal infarction
- Mean arterial pressure is increased in increments of 10mm Hg every five minutes (with volume and vasopressor agents) until symptoms resolve, bleeding complications ensue, or additional blood pressure augmentation would cause an unacceptably high risk of bleeding at the surgical bed.
If a lumbar drain is in place, it should be opened and set to drain at 8 to 12mm Hg. If not in place, a lumbar drain should be placed if there is no response to blood pressure augmentation within 10 to 20 minutes.
Discussion
a)
The sensory signs of an anterior spinal artery syndrome are:
- Preserved bilateral proproception and vibration
- Lost bilateral pain, temperature
- Usually, preserved light touch sensation (Triggs & Beric, 1992)
There would also be bilaterally absent motor control, and probably incontinence. The affected tracts are:
- Anterior spinothalamic tract (pain)
- Vestibulospinal tract (postural motor control)
- Tectospinal tract (reflexive postural head neck and eye movements)
- Anterior reticulospinal tract (postural motor control)
- Anterior corticospinal tract (gross motor control)
b)
Tendon reflex examination would reveal a flaccid loss of reflexes. "Flaccid motor paralysis and absent deep tendon reflexes may later progress to spasticity and hyperactive tendon reflexes", say Santamato et al (2013), but they do not say how long it will take. Spinal reflex arcs below the level of the injury will be intact, but they are facilitated by input from upper motor neurons and when this is interrupted the deep tendon reflexes are transiently lost.
c)
Perioperative factors in cardiothoracic or abdominal aortic surgery which promotes anterior spinal artery syndrome are
- Perioperative hypotension
- Prolonged aortic crossclamp time
- Other instrumentation of the atheromatous aorta (eg. angiography, IABP, VA ECMO)
- Inadequate heparinisation of the bypass circuit
- Air emboli
Apart from "perioperative factors", Djurberg & Haddad (1995) list "conditions affecting blood flow in the anterior spinal artery":
- Arteriosclerosis
- Vascular malformations (aortic aneurysms, haemangioma etc.)
- Tumour
- Infection (tuberculosis)
- Haematological disorders (polycythaemia, hypercoagulability)
- Trauma of the spine (fracture. haematoma, foreign body etc.)
- Chronic respiratory disease with polycythaemia
- Anatomical changes of the spine (kyphoscoliosis, spondyloarthrosis, disc herniation etc.)
d)
Management of an infarcted anterior cord involves maximising the perfusion of the cord via collaterals. The best information about this about this seems to come from Hnath et al (2007), who published a fairly successful protocol. This consisted of:
- Increasing perfusion pressure
- Hnath et al maintained the MAP at ≥90 mm Hg. In their answer, the college examiners recommend cranking the vasopressors until symptoms resolve or complications develop. This comes from the "Spinal Cord Infarction" UpToDate article by Mullen et al (2016).
- Decreasing spinal CSF pressure
- Hnath et al actively drained the CSF to maintain pressures <15 mm Hg. The college recommend simply draining to a positive pressure of no more than 8-12 mmHg, which is again from the same UpToDate source. The systematic review by Cina et al (2004) suggests that if you're going to do this, you should aim to decrease the CSF pressure to at least below 10 mmHg, for at least 48-60 hours. The rationale for this is that the lower CSF pressure minimise the resistance to afferent spinal cord blood flow, thereby increasing perfusion of at-risk regions (Strohm et al, 2017)
Hnath et al reported a 60% improvement, but their series had only 5 patients in the treatment arm, which somewhat dampens the enthusiasm of anybody following their footsteps. Chiesa et al (2005) list several other possible strategies:
- Distal aortic perfusion by bypass of the left heart (i.e. piping oxygenated blood into the distal aorta), which doesn't seem to work according to Coselli et al (2004)
- Deep hypothermic circulatory arrest which should theoretically protect the cord perioperatively (Safi et al, 1998)
- Regional cooling of the cord by infusing normal saline at 4° C into a thoracic epidural (Cambria et al, 1997)
- Protective pharmacological agents, used perioperatively (steroids, naloxone, barbiturates, papaverine, magnesium sulfate)
References
Djurberg, H., and M. Haddad. "Anterior spinal artery syndrome." Anaesthesia 50.4 (1995): 345-348.
Eltorai, Ibrahim M. "Anterior Spinal Artery Syndrome." Rare Diseases and Syndromes of the Spinal Cord. Springer, Cham, 2016. 437-440.
Foo, Dominic, and Alain B. Rossier. "Anterior spinal artery syndrome and its natural history." Spinal Cord 21.1 (1983): 1.
Zuber, William F., Max R. Gaspar, and Philip D. Rothschild. "The anterior spinal artery syndrome--a complication of abdominal aortic surgery: report of five cases and review of the literature." Annals of surgery 172.5 (1970): 909.
TRIGGS, WILLIAM J., and ALEKSANDAR BERIĆ. "Sensory abnormalities and dysaesthesias in the anterior spinal artery syndrome." Brain 115.1 (1992): 189-198.
Aydin, A. "Mechanisms and prevention of anterior spinal artery syndrome following abdominal aortic surgery." Angiologiia i sosudistaia khirurgiia= Angiology and vascular surgery 21.1 (2015): 155-164.
Santamato, Andrea, et al. "Paraplegia due to Anterior Spinal Artery Stroke: Rehabilitative Program on Lower Extremity Weakness and Locomotor Function." Int J Phys Med Rehabil1.118 (2013): 2.
Ullery, Brant W., et al. "Risk factors, outcomes, and clinical manifestations of spinal cord ischemia following thoracic endovascular aortic repair." Journal of vascular surgery 54.3 (2011): 677-684.
Cheshire, William P., et al. "Spinal cord infarction Etiology and outcome." Neurology 47.2 (1996): 321-330.
Gialdini, Gino, et al. "Retrospective analysis of Spinal Cord Infarction after Aortic Repair (P6. 300)." Neurology 88.16 Supplement (2017): P6-300.
Hnath, Jeffrey C., et al. "Strategies to improve spinal cord ischemia in endovascular thoracic aortic repair: outcomes of a prospective cerebrospinal fluid drainage protocol." Journal of vascular surgery 48.4 (2008): 836-840.
Chiesa, Roberto, et al. "Spinal cord ischemia after elective stent-graft repair of the thoracic aorta." Journal of vascular surgery 42.1 (2005): 11-17.
Strohm, Tamara, Seby John, and Muhammad Hussain. "Cerebrospinal Fluid Drainage for Acute Spinal Cord Infarction (P1. 301)." Neurology 88.16 Supplement (2017): P1-301.
Coselli, Joseph S., et al. "Left heart bypass during descending thoracic aortic aneurysm repair does not reduce the incidence of paraplegia." The Annals of thoracic surgery 77.4 (2004): 1298-1303.
Safi, Hazim J., et al. "Thoracic and thoracoabdominal aortic aneurysm repair using cardiopulmonary bypass, profound hypothermia, and circulatory arrest via left side of the chest incision." Journal of vascular surgery 28.4 (1998): 591-598.
Cambria, Richard P., et al. "Clinical experience with epidural cooling for spinal cord protection during thoracic and thoracoabdominal aneurysm repair." Journal of vascular surgery 25.2 (1997): 234-243.
Cinà, Claudio S., et al. "Cerebrospinal fluid drainage to prevent paraplegia during thoracic and thoracoabdominal aortic aneurysm surgery: a systematic review and meta-analysis." Journal of vascular surgery 40.1 (2004): 36-44.
Taira, Yutaka, and Martin Marsala. "Effect of proximal arterial perfusion pressure on function, spinal cord blood flow, and histopathologic changes after increasing intervals of aortic occlusion in the rat." Stroke 27.10 (1996): 1850-1858.
Mullen, Michael, et al. "Spinal cord infarction: Prognosis and treatment." UpToDate. Waltham MA.(Accessed on February, 2016).
Question 27 - 2018, Paper 1
A patient who was extubated 2 hours ago following a drug overdose, becomes very aggressive in the ICU. He has punched one staff member, head-butted another and has become very violent in close proximity to the other patients.
Describe how you would manage this situation. Include the advantages and disadvantages of the drugs that could be used.
College answer
Call for help: Hospital emergency response (Code Black or equivalent)
May be a medical illness (hypoxia, hypoglycaemia, metabolic disturbance), psychiatric disorder (acute psychosis, drug-induced psychosis, delusional state, mania or personality disorder) or drug intoxication or withdrawal causing the aggressive violence.
Sedation to gain control of the situation may be required to allow such an assessment.
Acute Management
De-escalation, containment and negotiation techniques if appropriate and most likely to work in a situation of low level threat (unlike this one).
Physical restraint – to allow delivery of drug therapy, need help / security team / police etc.
Chemical restraint:
i. Options:
- Benzodiazepines:
- Diazepam / Midazolam / Lorazepam
- Advantages of rapid action, good safety profile
- Concern: Sedation / Drowsiness / Respiratory depression / hypotension/short acting
- Anti-psychotics:
- Typical
- Haloperidol
- Droperidol (increasing profile for relatively safe emergency sedation)
- Atypical
- Olanzepine ii. Risperidone
- Typical
-
- Advantages – less respiratory depression, can be given im.
- Concerns: Extra-pyramidal side effects / QT prolongation / hypotension /slow onset, may require repeated administration
- NMDA-antagonist (Ketamine):
- Advantage: Can be given im, much less respiratory depression or hypotension, rapid onset
- Concern: Hallucinations / Hypertension, tachycardia /
- Intravenous anaesthetic agents (propofol, thiopentone)
- Advantage – very rapid action with guaranteed effect
- Concerns – apnoea, hypotension. May require intubation.
(B) Post-intervention considerations.
- Assessment and investigation for medical / psychiatric cause of severe agitation
- Adequate monitoring and support of vital signs
- Monitoring for adverse effects of medications used to control the individual
- Examination for injuries to the perpetrator
- Documentation
- Debrief – staff involved / perpetrator, when calm and rational other patients, perpetrator’s family
- Disposition – monitored environment
Examiner Comments:
Most candidates omitted thinking about or looking for causes of aggression (e.g. hypoxia) and did not mention any post-intervention considerations.
Discussion
This is far from uncommon, and the level of detail invested into the scenario suggests that some lightly bruised veteran of the ICU wrote the question in memory of a particularly extreme confrontation. Fortunately, there is a NSW Health directive to guide this area of practice.
Ensuring safety of the patient and staff
- Retreat to a safe place; remove staff to a safe area or to a safe distance, as much as possible
- Activate duress alarm
- Activate local emergency response (usually designated Code Black)
De-escalation technique
- An attempt to de-escalate the situation by engaging with the aggressive patient is one option, Some techniques have been suggested:
- Respecting personal space
- Appropriate body language using a non-confronting manner
- Establishing appropriate verbal contact to engage with the person
- Communicating in a clear and concise manner, avoiding repetition
- Listening and acknowledging the person’s concerns
- Identifying the person’s needs and feelings
- Setting clear limits and boundaries
- Being respectful
- etc etc
- Defusing the situation through conversation seems like an appropriate place to start.
- However this would probably not be a reasonable thing to include in the answer to Question 27. Specific offensive behaviours were quoted by the college, likely as a means of communicating to the trainees that they were not dealing with a reasonable person. If the patient is headbutting the staff, we are probably no longer in conversation territory.
Physical behavioural control measures
- The security team needs to nominate the team leader
- The team leader should assigns roles for each staff member
- One staff member should support or hold each limb
- One staff member should support or hold the head and continue to engage with the patient to "reassure and calm" them while they bite and spit.
With the patient physically restrained, it may now be possible to administer chemical restraints.
Chemical behavioural control measures
- In Question 27 from the first paper of 2018, the college wanted a list of drugs and their advantages/disadvantages. To quote several classes and to write "sedation/drowsiness/respiratory depression" as the disadvantage for all of them would probably win few marks. All these drugs have "rapid onset|" as an advantage and "sedation/drowsiness" as a disadvantage because you are using them to rapidly sedate somebody. Thus, the following list is offered with the intention of making these drug classes look so sufficiently different that the choice of which drug to give is not rendered meaningless.
- Benzodiazepines: Midazolam, diazepam, lorazepam, clonazepam
- Advantages:
- Rapid onset of effect
- Safe to give IM
- Disadvantages
- When given IM, unpredictable pharmacokinetics
- Prolonged duration of action and delayed peak effect may give rise to an inadvertent overdose ("he just won't stay down, give him more!")
- Some of these patients may be multi-drug resistant organisms and may be recreationally taking substantially more benzodiazepines than you would ever be willing to inject into them for behaviour control.
- Advantages:
- Classical antipsychotics: haloperidol, droperidol
- Advantages:
- Relatively short duration of action
- Significant experience with their use
- System-level support is strong- eg. many Australian health services have adopted droperidol as their drug of choice following the hilariously titled DORM trial (Isbister et al, 2010)
- Disadvantages:
- QT intervals will become prolonged with excess use
- Extrapyramidal side effects may produce motor problems which may extend to such unpleasantness as respiratory arrest due to muscle rigidity
- Most of these drugs are alpha-1 antagonists, which will cause hypotension
- Anticholinergic side efects cause urinary retention and may exacerbate delirium
- Advantages:
- Atypical antipsychotics
- Advantages:
- Generally viewed as safer than the classical agents
- Less anticholinergic and other side effects
- Longer duration of action for sustained effect
- Disadvantages:
- Many agents are not available in IV/IM formulations, which means you will be relying on some degree of cooperation, to swallow the tablet.
- Slow onset of antipsychotic effect; immediately useful effect is actually an antihistamine-like sedation which is probably no different to the classical agents in mechanism, except slower.
- Advantages:
- Dissociative anaesthetics
- Ketamine has been suggested as an agent for the "difficult to control" aggressive patients who have already had dangerous doses of other drugs. Data on this were publsihed by Isbister et al (2016), who gave their patients a median dose of 300mg (!) of ketamine to chase the 25mg of droperidol which they have already had.
- Advantages:
- Airway reflexes are preserved
- it is another class to use in a multimodal approach to behaviour control
- Disadvantages:
- Psychosis may get worse
- The patient may hallucinate
- Analgesic effect renders the patient immune to pain, which may result in self-harm
- Agitation associated with ketamine may be difficult to distinguish from the pre-existing agitation
- General anaesthetics
- The college answer to Question 27 recommends barbiturates or propofol, quoting rapid action and a "guaranteed" effect. One might also make the argument that 500mg of intramuscular suxamethonium might be similarly rapid in onset, and offer a similar certainty of behaviour control.
- Propofol has been used as an infusion in these cases (Chalwin et al, 2012)- apparently only 30-50mg/hr was required to sustain "conscious sedation, leading to satisfactory patient compliance with healthcare interventions".
- The natural tendency of these situations to lead to intubation needs to be mentioned.
- Benzodiazepines: Midazolam, diazepam, lorazepam, clonazepam
Investigations and post-sedation care
- Determine need for ongoing physical restraints
- Monitor vital signs
- Examine the patient for injuries
- Explore organic differentials (eg. meningitis, encephalitis, head trauma, hypoxia, pain, background of developmental delay, metabolic encephalopathy)
Post-event care of staff and family
- Debrief with staff
- Discussion with patient's family
- Escalation of incident to incident monitoring committee
- Institution-level interventions (eg. aggression management workshops and training in safe "take-down" techniques of physical restraint)
References
Yoon, Hyung-Jun, et al. "Efficacy and safety of haloperidol versus atypical antipsychotic medications in the treatment of delirium." BMC psychiatry 13.1 (2013): 1-11.
Arumugam, Suresh, et al. "Delirium in the intensive care unit." Journal of Emergencies, Trauma, and Shock 10.1 (2017): 37.
Kynoch, Kate, Chiung‐Jung Wu, and Anne M. Chang. "Interventions for preventing and managing aggressive patients admitted to an acute hospital setting: a systematic review." Worldviews on Evidence‐Based Nursing 8.2 (2011): 76-86.
Isbister, Geoffrey K., et al. "Randomized controlled trial of intramuscular droperidol versus midazolam for violence and acute behavioral disturbance: the DORM study." Annals of emergency medicine 56.4 (2010): 392-401.
Chalwin, Richard. "Propofol Infusion for the Retrieval of the Acutely Psychotic Patient." Air medical journal 31.1 (2012): 33-35.
Question 3 - 2018, Paper 2
Compare and contrast Guillian-Barré syndrome (GBS), and acute transverse myelitis (ATM) in terms of the relevant history, the clinical features, and the relevant investigation findings.
College answer
|
Guillian-Barré |
Acute Transverse Myelitis |
|
|
Relevant History |
Antecedent respiratory or diarrhoeal illness Campylobacter Jejuni Viral – EBV, HSV Mycoplasma Vaccination |
Antecedent respiratory, gastrointestinal, or systemic illness in 30-60%, can occur as part of the spectrum of multiple sclerosis, may be seen in patients with acute disseminated encephalomyelitis, other CNS infections or associated with a systemic autoimmune disease |
|
Motor Weakness |
Ascending, symmetrical motor weakness Parasthesia/pain Hypo/areflexia |
Pyramidal weakness below level of spinal cord lesion, bilateral signs |
|
Cranial Nerve Palsy |
Common Uni-/bilateral facial Bulbar |
Rare, may be associated with optic neuritis if part of MS spectrum |
|
Dysautonomia |
Yes |
May be present |
|
Sensory Deficit |
Absent or Mild, distal |
Clearly defined sensory level all modalities (spinothalamic and posterior columns) on the trunk at level of involvement |
|
CSF |
Elevated protein. No pleocytosis. |
Abnormal in 50%, moderate lymphocytosis (typically <100/mm3) and an elevated protein. Glucose levels are normal. Oligoclonal bands are usually not present in isolated TM, and when present suggest a higher risk of subsequent MS |
|
Neurophysiology |
Abnormal spontaneous activity |
Decreased/ unrecordable motor evoke potentials to lower limbs especially on |
|
Normal MUPs initially. Reduced recruitment. |
lumbar stimulation and evidence of denervation in leg muscles |
|
|
MRI |
Not diagnostic |
Gadolinium-enhancing signal abnormality (extending over one or more cord segments. Cord oedema at the level. |
Discussion
This is another question in a long series of neurology questions asking the trainees to compare Guillain-Barre with other spinal weakness syndromes. The official college answer to this SAQ was actually quite extensive, and likely represents an earnest effort from the examiners. It would be difficult to improve on such an answer. One can merely rearrange the categories and add some irrelevant tidbits here and there. The product appears below.
| Guillian-Barré | Acute Transverse Myelitis |
| Pathophysiology | |
|
Acute inflammatory demyelinating peripheral neuropathy associated with infection such as:
|
Autoimmune inflammation of the spinal cord; may be idiopathic or associated with other illnesses:
|
| Typical features of history | |
|
|
| Power | |
|
|
| Tone | |
|
|
| Reflexes | |
|
|
| Cranial nerves | |
|
|
| Autonomic features | |
|
|
| Sensory findings | |
|
|
| CSF features | |
|
|
| Nerve conduction studies | |
|
|
| Electromyography | |
|
|
| MRI | |
|
|
References
Chapter 57 (pp. 617) Neuromuscular diseases in intensive care by George Skowronski and Manoj K Saxena
van den Berg, Bianca, et al. "Guillain-Barre syndrome: pathogenesis, diagnosis, treatment and prognosis." Nature Reviews Neurology 10.8 (2014): 469-482.
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Raphael, J. C., et al. "Plasma exchange for Guillain-Barré syndrome." Cochrane Database Syst Rev 2.2 (2002).
Venkata Umakant, K., B. Seshulakshmi, and B. Srinivasa Rao. "Miller Fisher Syndrome–An Atypical Clinical Presentation." Intern Med 3.119 (2013): 2.
Berlit, Peter, and Josef Rakicky. "The Miller Fisher syndrome: review of the literature." Journal of Neuro-Ophthalmology 12.1 (1992): 57-63.
Odaka, M., N. Yuki, and K. Hirata. "Anti-GQ1b IgG antibody syndrome: clinical and immunological range." Journal of Neurology, Neurosurgery & Psychiatry70.1 (2001): 50-55.
Alkan, Ozlem, et al. "Spinal MRI findings of guillain-barre syndrome." Journal of radiology case reports 3.3 (2009): 25.
Cabrera Serrano, M., and A. A. Rabinstein. "Usefulness of pulmonary function tests and blood gases in acute neuromuscular respiratory failure." European Journal of Neurology 19.3 (2012): 452-456.
Farrero, Eva, et al. "Guidelines for the Management of Respiratory Complications in Patients With Neuromuscular Disease." Archivos de Bronconeumología (English Edition) 49.7 (2013): 306-313.
Hughes, Richard AC, et al. "Supportive care for patients with Guillain-Barré syndrome." Archives of neurology 62.8 (2005): 1194-1198.
Massam, M., and R. S. Jones. "Ventilatory failure in the Guillain-Barré syndrome." Thorax 35.7 (1980): 557-558.
González-Suárez, Inés, et al. "Guillain-Barré Syndrome: Natural history and prognostic factors: a retrospective review of 106 cases." BMC neurology 13.1 (2013): 95.
Dhand, Upinder K. "Clinical approach to the weak patient in the intensive care unit." Respiratory care 51.9 (2006): 1024-1041.
Sanders, Donald B., and Janice M. Massey. "Clinical features of myasthenia gravis." Handbook of clinical neurology 91 (2008): 229-252.
Bird, Shawn J. "Clinical manifestations of myasthenia gravis." Up-to-date 16.1 (2008): 1-8.
Gronseth, Gary S., and Richard J. Barohn. "Practice parameter: Thymectomy for autoimmune myasthenia gravis (an evidence-based review) Report of the Quality Standards Subcommittee of the American Academy of Neurology." Neurology 55.1 (2000): 7-15.
Gajdos, Philippe, Sylvie Chevret, and Klaus V. Toyka. "Plasma exchange for generalised myasthenia gravis." The Cochrane Library (2002).
Gajdos, Philippe, et al. "Treatment of myasthenia gravis exacerbation with intravenous immunoglobulin: a randomized double-blind clinical trial." Archives of neurology 62.11 (2005): 1689-1693.
Jacob, Anu, and Brian G. Weinshenker. "An approach to the diagnosis of acute transverse myelitis." Seminars in neurology. Vol. 28. No. 01. © Thieme Medical Publishers, 2008.
Garg, Nidhi, et al. "Differentiating lower motor neuron syndromes." J Neurol Neurosurg Psychiatry 88.6 (2017): 474-483.
West, Timothy W. "Transverse myelitis—a review of the presentation, diagnosis, and initial management." Discovery medicine 16.88 (2013): 167-177.
Harzheim, Michael, et al. "Discriminatory features of acute transverse myelitis: a retrospective analysis of 45 patients." Journal of the neurological sciences 217.2 (2004): 217-223.
Question 10 - 2018, Paper 2
With regard to posterior reversible leukoencephalopathy syndrome (PRES), outline the risk factors, clinical features, differential diagnoses, radiological findings and management.
College answer
Clinical features:
Onset acute – days/weeks
Headache
Encephalopathy -fluctuating conscious level to coma
Hypertension
Seizures
Visual deficits
Risk factors:
Hypertension
Cytotoxic therapy
Eclampsia
Renal disease
Autoimmune disorders
Transplantation
Differential diagnoses
CVA
Encephalitis
Migraine
Demyelinating conditions
Vasculitis
Radiological findings:
Vasogenic oedema in the posterior circulation territories on MRI
Management:
Aggressive blood pressure control
Cease any precipitating agents
Antiseizure medication
Discussion
This is the second time PRES has appeared in the written papers. Little can be done to improve the direct brevity of the college answer, other than to add references and change structure.
Risk factors
|
Classical associations
|
Other associated conditions
|
Clinical features (Fugate and Rabenstein, Lancet, 2015)
- Altered level of consciousness, ranging from confusion to coma
- Headache
- Seizures
- Visual symptoms (usually, blindness or hemianopia)
- Neuroradiology findings
- Exclusion of other pathology (eg. encephalitis or stroke)
- Acute onset, and reversibility over days or weeks
- Hypertension
Differential diagnosis (from UpToDate)
- Eclampsia
- Cerebral oedema due to hypertensive encephalopathy
- Reversible cerebral vasoconstriction syndrome
- Ischaemic stroke (posterior circulation)
- Cerebral venous thrombosis
- Encephalitis (infectious, paraneoplastic or autoimmune)
- CNS malignancy, eg. lymphoma
- Acute demyelinating encephalomyelitis (ADEM)
Radiological findings (Swarnalatha et al, 2012)
- Oedema is symmetric (bilateral)
- Posterior occipital or parietal distribution (but this is not essential): in fact three major anatomical patterns of distribution exist:
- holohemispheric
- superior frontal sulcal
- primary parietal-occipital
Management of PRES:
- Aggressively control the blood pressure.
- Give antiepileptics if seizures were a presenting problem.
- Stop the causative drug.
- Deliver the baby (in eclampsia).
- Protect the patient from the horrors of ICU stay by attentive FASTHUGish supportive care
References
Staykov, Dimitre, and Stefan Schwab. "Posterior reversible encephalopathy syndrome." Journal of Intensive Care Medicine 27.1 (2012): 11-24.
Bartynski, W. S. "Posterior reversible encephalopathy syndrome, part 1: fundamental imaging and clinical features." American Journal of Neuroradiology 29.6 (2008): 1036-1042.
Bartynski, W. S. "Posterior reversible encephalopathy syndrome, part 2: controversies surrounding pathophysiology of vasogenic edema." American Journal of Neuroradiology 29.6 (2008): 1043-1049.
Grioni, Daniele, et al. "The diagnosis of posterior reversible encephalopathy syndrome." The Lancet Neurology 14.11 (2015): 1073-1074.
Fugate, Jennifer E., and Alejandro A. Rabinstein. "Posterior reversible encephalopathy syndrome: clinical and radiological manifestations, pathophysiology, and outstanding questions." The Lancet Neurology 14.9 (2015): 914-925.
MacKenzie, ERIC T., et al. "Effects of acutely induced hypertension in cats on pial arteriolar caliber, local cerebral blood flow, and the blood-brain barrier." Circulation research 39.1 (1976): 33-41.
G Swarnalatha, R Ram, B. H. S. Pai, KV Dakshinamurty "Posterior reversible encephalopathy syndrome in minimal change disease" Indian Journal of Nephrology, Vol. 22, No. 2, March-April, 2012, pp. 153-154
Hobson, Esther V., Ian Craven, and S. Catrin Blank. "Posterior reversible encephalopathy syndrome: a truly treatable neurologic illness." Peritoneal Dialysis International 32.6 (2012): 590-594.
Question 25 - 2018, Paper 2
Critically evaluate the role of Decompressive Craniectomy (DC) following traumatic brain injury.
College answer
Introduction
The main role of DC in TBI is reduction of ICP and prevention of herniation, aggravated by haematoma and brain swelling. Use of this technique is controversial and its efficacy in TBI is uncertain despite recent trials. Two main techniques widely used for DC in TBI are unilateral frontotemporoparietal craniectomy and bifrontal craniectomy
Rationale
In a decompressive craniectomy, a substantial portion of the skull is removed in order to reduce increased ICP. This can be done in combination with an evacuation procedure or as a primary treatment for increased ICP. The rationale of DC is based in the Monro-Kellie Doctrine. The skull is a rigid unexpandable structure, opening the cranial vault by DC increases the volume available to the intracranial contents and reduces ICP. Current Brain Trauma Foundation guidelines suggested the ICP lower than 20 mmHg after TBI. Patients with well-controlled ICP under the threshold appear to have improved outcomes.
Evidence
DECRA
Published by Cooper et al. in 2011- 155 patients with TBI and either GCS score lower than 8 or CT demonstrating moderate diffuse brain injury were enrolled. Patients with refractory ICP (ICP>20 mmHg for 15 minutes) within a 1-hour period were randomized to one of two groups.
DC decreased ICP and the length of stay in the intensive care unit but was associated with more patients with unfavourable neurological outcomes.
Criticisms of DECRA:
Higher ICP threshold should be used before performing DC in TBI.
The period of medical management with high ICP was too short prior to randomisation.
More patients who had non-reactive pupil were enrolled in the DC group (27%) only 12% in medical therapy group.
The choice of surgical method- only bifrontal DC without falx sectioning allowed.
No standardised rehabilitation
Long enrolment period
Less emphasis on CPP.
RESCUEicp
Multicentre (48 centre, 19 countries) RCT
408 patients (age, 10-65 years) with TBI and refractory elevated ICP (>25 mmHg) were randomized to undergo DC or receive ongoing medical care.
The primary outcome was the Extended Glasgow Outcome Scale (GOS-E) at 6 months.
At 6 months patients in DC group resulted in lower mortality and higher rates of vegetative state, lower severe disability and upper severe disability than ongoing medical care group. The rates of moderate disability and good recovery were similar in the two groups.
Limitations
A relatively large proportion of patients in the medical group underwent DC
Pros
• Reduces ICP
• Increases survival
• Decreases ICU length of stay
Cons
ICP reduction may not necessarily result in better clinical outcomes
Potentially increased numbers of severely debilitated survivors
Surgical complications potentially include:
• Axonal stretch
• Aggravated brain oedema
• Haematoma expansion or bleeding
• Infection
• CSF leakage
• Syndrome of the trephined
Own practice
We utilise decompressive craniectomy in our unit in young patients with TBI, refractory intracranial hypertension and relatively early in their course prior to irreversible secondary injury
Clinicians and family members will need to be aware of the risks when potentially employing this strategy.
Probably useful if mass lesion (excluded in DECRA)
Summary
There is a growing body of literature with conflicting results.
Decompressive craniectomy decreases ICP and leads to improved survival. The quality of that survival is the issue, so careful procedure selection, patient population selection and overall situation appreciation are important
The level of detail of the studies given in the template was not required.
Examiners Comments:
Most candidates answered the question as asked, but several wasted efforts explaining other methods of controlling ICP or describing DC use in non-TBI situations. Candidates are reminded to read the stem carefully.
Discussion
This SAQ is entirely unlike Question 9 from the first paper of 2009, where the focus was more on indications complications and outcomes. This one required some additional depth of analysis, of which probably the most sophisticated area involved the interpretation and presentation of the results of two major trials in TBI management. In spite of the dyssynchronous-sounding "wasted efforts" mentioned by the college, clearly many of the trainees (at least 67.2% of them) have at least a workmanlike knowledge of these issues.
Rationale
- Raised intracranial pressure contributes to secondary brain injury and morbidity/mortality from TBI
- Intracranial pressure is governed by the Monro-Kellie Doctrine, where intracranial content is confined within a finite space and any expansion of one component produces increased pressure on other components
- Decompressive craniectomy increases the volume available to the intracranial contents
- The consequence should be decreased ICP and decreased secondary brain injury.
Evidence
- The DECRA trial:
- (n=155)
- No strong evidence for any mortality benefit (19% vs 18%).
- Worse functional outcomes in survivors
- However: methodologically flawed:
- Protocol resorted to surgery too early
- Patients with "mass lesions" were excluded
- The bifrontal procedure is suboptimal for controlling ICP (but anyway the ICP control was very good in the decompression group)
- The 155 patients for this trial took 8 years to enrol
- Prior to the randomisation, both groups had relatively normal-ish ICPs (upper limit of normal, approaching 20 mmHg).
- The RESCUEicp trial:
- n= 408 patients
- Higher threshold (sustained ICP of > 25mmHg, and sustained for longer, in spite of a good trial of Stage 2 therapies).
- Improved mortality (26.9% vs 48.9%)
- More survivors with severe disability
- Problems with methodology:
- Of the patients randomised to medical management, 37% underwent decompressive craniectomy anyway.
- As with DECRA, recruitment of all 408 patients took 10 years. Half the centres recruited only 3 patients, or fewer.
- Therapeutic hypothermia was one of the optional Stage 2 rescue therapies prior to reaching for the bone saw, which - we now realise- may confer a survival disadvantage.
Society guidelines
- new (2016) BTF Guidelines:
- Not recommended to improve outcomes
- Do a large bifrontal decompression (no less than 12 × 15 cm)
- (these do not incorporate RESCUEicp results)
Advantages of decompression in TBI include
- Maybe some sort of mortality benefit (cohort studies such as Sonuca et al, 2010; as well as RESCUIicp)
- Shorter ICU stay
- Less ICP-targeting interventions
- Lower ICP
Disadvantages include:
- Conflicting evidence for mortality benefit (19% vs 18% in the DECRA trial, versus 26.9% vs 48.9% in RESCUIicp)
- Worse neurological outcome in survivors
- Multiple complications associated with decompressive craniectomy:
- Herniation through the defect
- Delayed paradoxical herniation
- Subdural hygroma
- Infection
- Bleeding
- Post-traumatic hydrocephalus
- "Sinking Flap Syndrome"
- Bone resorption
Own practice
This section should probably be written delicately. Among the examiners, there is clearly substantial heterogeneity of beliefs regarding this intervention. The "own practice" answer should be sufficiently conservative to please the haters of decompressive craniectomy, while acknowledging that it is difficult to present improved survival as a bad thing. Thus, something like:
- My practice is to reserve decompressive craniectomy for carefully selected patients, who:
- have severe traumatic brain injury, with or without mass lesions
- have refractory ICP, difficult to control with Stage 1 and Stage 2 interventions (posture, sedation, paralysis, osmotherapy, cooling)
- are early in the course of TBI evolution (i.e. do not have well-established structural brain damage)
- My practice would be to discuss the options (decompressive craniectomy, thiopentone coma, conservative management) with the family, taking into account their values and expectations.
References
Cooper, D. James, et al. "Decompressive craniectomy in diffuse traumatic brain injury." New England Journal of Medicine 364.16 (2011): 1493-1502.
Hutchinson, Peter J., et al. "Trial of decompressive craniectomy for traumatic intracranial hypertension." New England Journal of Medicine 375.12 (2016): 1119-1130.
Vahedi, Katayoun, et al. "Sequential-design, multicenter, randomized, controlled trial of early decompressive craniectomy in malignant middle cerebral artery infarction (DECIMAL Trial)." Stroke 38.9 (2007): 2506-2517.
Hofmeijer, Jeannette, et al. "Surgical decompression for space-occupying cerebral infarction (the Hemicraniectomy After Middle Cerebral Artery infarction with Life-threatening Edema Trial [HAMLET]): a multicentre, open, randomised trial." The Lancet Neurology 8.4 (2009): 326-333.
Jüttler, Eric, et al. "Decompressive surgery for the treatment of malignant infarction of the middle cerebral artery (DESTINY) a randomized, controlled trial." Stroke 38.9 (2007): 2518-2525.
Lee, Kyeong Woo, et al. "Functional Outcomes of Patients with Severe MCA Infarction after Decompressive Craniectomy." Brain & Neurorehabilitation 7.1 (2014): 48-53.
Tuzgen, Saffet, et al. "Decompressive craniectomy in patients with cerebral
infarction due to malignant vasospasm after aneurysmal subarachnoid hemorrhage." Journal of neurosciences in rural practice 3.3 (2012): 251.
Murthy, J. M. K., et al. "Decompressive craniectomy with clot evacuation in large hemispheric hypertensive intracerebral hemorrhage." Neurocritical care 2.3 (2005): 258-262.
Güresir, Erdem, et al. "Decompressive craniectomy in subarachnoid hemorrhage." Neurosurgical focus 26.6 (2009): E4.
Keller, E., et al. "Decompressive craniectomy in severe cerebral venous and dural sinus thrombosis." New Trends of Surgery for Stroke and its Perioperative Management. Springer Vienna, 2005. 177-183.
Schirmer, Clemens M., Daniel A. Hoit, and Adel M. Malek. "Decompressive hemicraniectomy for the treatment of intractable intracranial hypertension after aneurysmal subarachnoid hemorrhage." Stroke 38.3 (2007): 987-992.
Adamo, Matthew A., and Eric M. Deshaies. "Emergency decompressive craniectomy for fulminating infectious encephalitis." (2008). Journal of Neurosurgery January 2008 / Vol. 108 / No. 1 / Pages 174-176
Hutchinson, Peter, Ivan Timofeev, and Peter Kirkpatrick. "Surgery for brain edema." Neurosurgical focus 22.5 (2007): 1-9.
Margules, Andrew, and Jack Jallo. "Complications of decompressive craniectomy." JHN Journal 5.1 (2010): 4.
Chu, Stacy Y., and Kevin N. Sheth. "Decompressive Craniectomy in Neurocritical Care." Current treatment options in neurology 17.2 (2015): 1-11.
Kolias, Angelos G., et al. "Primary decompressive craniectomy for acute subdural haematomas: results of an international survey." Acta neurochirurgica154.9 (2012): 1563-1565.
Li, Lucia M., et al. "Outcome following evacuation of acute subdural haematomas: a comparison of craniotomy with decompressive craniectomy."Acta neurochirurgica 154.9 (2012): 1555-1561.
Uozumi, Yoichi, et al. "Decompressive craniectomy in patients with aneurysmal subarachnoid hemorrhage: a single-center matched-pair analysis" Cerebrovasc Dis 37 (2014): 109-115.
Takeuchi, Satoru, et al. "Decompressive craniectomy for arteriovenous malformation-related intracerebral hemorrhage." Journal of clinical neuroscience: official journal of the Neurosurgical Society of Australasia (2015).
Takeuchi, Satoru, et al. "Decompressive craniectomy with hematoma evacuation for large hemispheric hypertensive intracerebral hemorrhage." Brain Edema XV. Springer Vienna, 2013. 277-279.
Coutinho, Jonathan M., et al. "Decompressive hemicraniectomy in cerebral sinus thrombosis consecutive case series and review of the literature." Stroke40.6 (2009): 2233-2235.
Raza, Emmon, et al. "Decompressive Surgery for Malignant Cerebral Venous Sinus Thrombosis: A Retrospective Case Series from Pakistan and Comparative Literature Review." Journal of Stroke and Cerebrovascular Diseases 23.1 (2014): e13-e22.
Sonuca, Dekompresif Kraniektominin. "Effect of early bilateral decompressive craniectomy on outcome for severe traumatic brain injury." Turkish neurosurgery 20.3 (2010): 382-389.
Crudele et al. "Decompressive Hemicraniectomy in Acute Neurological Diseases." Journal of Intensive Care Medicine 2016;31(9):587–596
Quinn, T. M., et al. "Decompressive craniectomy." Acta Neurologica Scandinavica 123.4 (2011): 239-244.
Torres, Roland. "DECRA… Where do we go from here?." Surgical neurology international 3 (2012).
Muñoz, Javier, et al. "Primary decompressive craniectomy in neurocritical patients. a meta-analysis of randomized controlled trials, cohort and case-control studies." Journal of Emergency and Critical Care Medicine 2.9 (2018).
Question 30.2 - 2018, Paper 2
List three causes of coma with bilateral miosis. (30% marks)
College answer
• Pontine lesions
• Thalamic haemorrhage
• Metabolic encephalopathy
• Organophosphate toxicity
• Other cholinergic agents (e.g. donezepil for Alzheimers) Opioids, barbituates, GHB, clonidine
• Mushroom intoxication (cholinergic effect)
Discussion
This question is virtually identical to Question 21.1 from the second paper of 2015, except this time the causes of coma are each worth 10% of the marks instead of 5%.
In summary, a list of causes would resemble the following:
- Bilateral pontine lesions
- Bilateral thalamic lesions
- Metabolic encephalopathy
- Cholinergic drugs
- Organophosphates
- Myasthenia gravis drugs (the 'stigmines, eg. pyridostigmine)
- Alzheimers nootropics (the 'pezils, eg. donepezil)
- Sarin gas
- Non-cholinergic drugs:
- Opiates
- Barbiturates
- GHB
- Clonidine
- GHB
- Chloral hydrate
- Valproate
- Atypical antipsychotics
- Phenothiazines
Causes of bilaterally small pupils which do not produce coma:
- Neurosyphilis (bilateral Argyll-Robertson pupils)
- Diabetic neuropathy
- Late Holmes-Adie pupils (initially, they are dilated)
- Bilateral Horner's Syndrome, due to:
- Bilateral carotid dissection
- Bilateral neck trauma
- Cluster headache
- Or, massive thalamic or pontine damage
The whole "metabolic encephalopathy" thing is somewhat vague, and is included here because it is technically accurate. Metabolic encephalopathy can describe many things, and produce many signs.
A reader of LITFL had also pointed out that phenothiazines should be expected to cause mydriasis, by virtue of their anticholinergic effect. This is not the case. A 1973 article from California Medicinereports 48 cases of phenothiazine poisoning, in which the pupils were almost invariably small. This can be attributed to the alpha-antagonist effects of these drugs, which override the anticholinergic effects.
References
The LITFL summary of cranial nerve lesions is without peer in terms of useful information density.
Specifically, the reader is directed to Coma and Small Pupils, aka Neurological Mind-boggler 002
Walker, H. Kenneth, W. Dallas Hall, and J. Willis Hurst. "Clinical methods." 3rd edition.(1990).Chapter 58 The Pupils - by Robert H. Spector.
Barry, Daniel, Frank L. Meyskens Jr, and Charles E. Becker. "Phenothiazine Poisoning A Review of 48 Cases." California medicine 118.1 (1973): 1.
Question 10 - 2019, Paper 1
In relation to diffuse cerebral oedema; discuss the pathophysiology, and the clinical and CT manifestations.
College answer
(30%- 30%- 40% marks)
Cerebral oedema is often classified based on 3 different mechanisms by which oedema results:
Cytotoxic oedema: failure of ionic pumps to maintain cellular homeostasis, accumulation of water and swelling of cells. Blood brain barrier (BBB) is intact. Metabolic derangements and ischaemia most common causes. E.g. CVA, post cardiac arrest, encephalopathy e.g. due to hepatic impairment.
Vasogenic oedema: breakdown of endothelial junctions of the BBB allowing intravascular proteins and fluid into extracellular space. Due to trauma, tumours, inflammation (e.g. infection), late stage of ischaemic insults, high altitude sickness. Mechanism relates to hydrostatic pressure in arterial HT, tumour released endothelial destructive factors (e.g. vascular endothelial growth factor - secretion reduced by Dexamethasone).
Osmotic oedema: Dilution of plasma leading to shift of water down the osmolarity gradient to the brain.
E.g. Excess H2O intake, SIADH, dialysis, rapid decrease in blood glucose when treated for a hyperosmolar hyperglycaemic state.
Cytotoxic and vasogenic oedema often coexist e.g. in setting of infarction or trauma.
Clinical manifestations
May be similar to and superimposed on manifestations of the underlying cause
Related mostly to elevated ICP or mass effect
Reduced consciousness
Headache
Photophobia
Agitation, delirium early
Hypertension, bradycardia (Cushing’s response)
Pupillary dilatation and decreased light reflex Papilledema
(Lateralising signs may be present with unilateral uncal/cerebellar herniation)
CT manifestations
Loss of sulci
Loss of grey-white differentiation
Basal cistern/lateral ventricle effacement
Uncal herniation
Herniation of cerebellar tonsils into foramen magnum.
Discussion
There are several agreed-upon mechanisms which can generate cerebral oedema:
- Cellular oedema
- Cytotoxic oedema (disturbance of cellular osmoregulation due to Na/K ATPase failure), due to interrupted energy supply eg. ischaemia hypoxia or trauma
- Metabolic storage (due to abnormal intracellular accumulation of molecular products), eg. in hyperammonaemia or inherited cell storage diseases suhc as Pompe's disease (glycogen), Hurler's disease (mucopolysaccharides), Gaucher's disease (glycosyl ceramide), etc.
- Extracellular oedema
- Vasogenic oedema (an increase in brain capillary permeability), eg. due to infection
- Osmotic oedema (due to an osmotic gradient between the plasma and the interstitial fluid, across an intact blood-brain barrier), eg. in the context of dialysis disequilibrium, or due to rapid loring of the blood glucose in a hyperglycaemic hyperosmolar state
- Hydrocephalic oedema (obstruction of CSF flow pathways), where CSF infiltrates periventricular white matter due to increased intraventricular pressure, through a damaged ependymal lining.
For the majority of the clinical features listed below, the main source was the UpToDate article on high altitude cerebral oedema, as that seemed like a cause of diffuse oedema which was sufficiently insidious in onset to produce symptoms instead of immediate coma.
Symptoms
- Headache
- Photophobia
- Neck stiffness
- "Lassitude"
Signs
- Irritability and confusion
- Ataxia
- Agitation, delirium
- Decreased level of consciousness
- Seizures
With raised ICP:
- Hypertension
- Bradycardia
- Mydriasis
- Loss of light reflex
- Papilledema on fundoscopy
Radiological features:
Vasogenic oedema
- Primarily affecting white matter
- Indentations of edema with frond-like projections into normal gray matter
- Enhancement following contrast
- Usually focal, i.e. due to some local lesion
Cytotoxic oedema
- Usually diffuse
- Does not enhance with contrast
- Involves subcortical nuclear gray matter structures (e.g., basal ganglia, thalamus).
Hydrocephalus-associated "interstitial" oedema
- Transependymal fluid: low attenuation periventricular changes around the lateral ventricles. These are usually most prominent surrounding frontal and occipital horns.
Oedema in general
- effacement of the sulci
- effacement of the ventricles
- loss of grey-white differentiation
References
Stokum, Jesse A., Volodymyr Gerzanich, and J. Marc Simard. "Molecular pathophysiology of cerebral edema." Journal of Cerebral Blood Flow & Metabolism 36.3 (2016): 513-538.
Mahajan, Shalvi, and Hemant Bhagat. "Cerebral oedema: Pathophysiological mechanisms and experimental therapies." Journal of Neuroanaesthesiology and Critical Care 3.04 (2016): S22-S28.
Iencean, S. M. "Brain edema–a new classification." Medical hypotheses 61.1 (2003): 106-109.
Milhorat, Thomas H. "Classification of the cerebral edemas with reference to hydrocephalus and pseudotumor cerebri." Child's Nervous System 8.6 (1992): 301-306.
Klatzo, Igor. "Evolution of brain edema concepts." Brain Edema IX. Springer, Vienna, 1994. 3-6.
Reichardt, M. "Zur Entstehung des Hirndrucks bei Hirngeschwülsten und anderen Hirnkrankheiten und über eine hei diesen zu beobachtende besondere Art der Hirnschwellung." Deutsche Zeitschrift für Nervenheilkunde28.2-4 (1905): 306-355.
Klatzo, Igor. "Neuropathological aspects of brain edema." Journal of Neuropathology & Experimental Neurology 26.1 (1967): 1-14.
Doggett, N. S., and P. S. J. Spencer. "Pharmacological properties of centrally administered ouabain and their modification by other drugs." British journal of pharmacology42.2 (1971): 242.
Gazendam, Jurjen, K. Gwan Go, and Annie K. Van Zanten. "The effect of intracerebral ouabain administration on the composition of edema fluid isolated from cats with cold-induced brain edema." Brain research 175.2 (1979): 279-290.
Betz, A. L., F. Iannotti, and J. T. Hoff. "Brain edema: a classification based on blood-brain barrier integrity." Cerebrovascular and brain metabolism reviews 1.2 (1989): 133-154.
Philippe, Geneviève, and Luc Angenot. "Recent developments in the field of arrow and dart poisons." Journal of ethnopharmacology 100.1-2 (2005): 85-91.
Walters, R. J. L., et al. "Haemodialysis and cerebral oedema." Nephron 87.2 (2001): 143-147.
Maccario, Micheline, and ChrystopoulosP Messis. "Cerebral oedema complicating treated non-ketotic hyperglycaemia." The Lancet 294.7616 (1969): 352-353.
Ligtenberg, J. JM, et al. "A lethal complication of psychogenic polydipsia: cerebral edema and herniation." Intensive care medicine 24.6 (1998): 644-645.
Milhorat, Thomas Herrick. Cerebrospinal fluid and the brain edemas. New York Society of Neurosurgery, New York (1987)
Gilbert, Joseph J., et al. "Cerebral edema associated with meningiomas." Neurosurgery 12.6 (1983): 599-605.
Milhorat, Thomas H., et al. "Structural, ultrastructural, and permeability changes in the ependyma and surrounding brain favoring equilibration in progressive hydrocephalus." Archives of Neurology 22.5 (1970): 397-407.
Weisberg, Leon, Jack Greenberg, and Antonio Stazio. "Computed tomographic findings in brain swelling." Computerized Medical Imaging and Graphics 14.4 (1990): 263-268.
Ho, Mai-Lan, Rafael Rojas, and Ronald L. Eisenberg. "Cerebral edema." American Journal of Roentgenology 199.3 (2012): W258-W273.
Question 27 - 2019, Paper 1
a) List five neurological signs associated with a lateral medullary infarction. (25% marks)
b) List four neurological signs of a third cranial nerve palsy. What clinical feature of the palsy would distinguish between an intracranial mass lesion or diabetic neuropathy as the cause? (20% marks)
c) List five neurological deficits associated with a bulbar palsy, along with the corresponding cranial nerves which are affected. (25% marks)
d) List six causes of dilated unreactive pupils not due to a primary intracranial lesion.
(30% marks)
College answer
-
a)
- Loss of contralateral pain and temperature in the trunk, and ipsilateral pain and temperature loss in the face.
- Difficulty in walking or sitting upright
- Nystagmus
- Limb ataxia/hypotonia
- Horner’s syndrome
- Bulbar muscle weakness
b)
- Ptosis (complete or partial).
- The affected eye deviates downwards and outwards (divergent strabismus). Intorsion (internal rotation of eye)
- The pupil MAY be dilated and fixed to light but may be normal.
- A mass lesion results in pupillary non-reactivity, in diabetes the pupil is spared.
c)
- Absent gag reflex (IX, X nerve lesions)
- Absent elevation of soft palate (IX, X, nerve lesions)
- Nasal speech (soft palate movement absent)
- Jaw jerk normal or absent (V lesion)
- Tongue weak and wasted and possibly fasciculating (XII lesion) Drooling saliva and difficulty swallowing (IX, X, XII lesions)
d)
- Drugs systemic: e.g. Barabiturate ,adrenaline, atropine, methanol (only one drug marked) Drugs topical – anticholinergics. Sympathomimetics (only one drug marked)
- Guillain Barre
- Trauma
- Prosthetic eye/lenses
- Envenomation (tetrodoxin, pufferfish)
- Chronic blindness
- Total spinal
- Hepatic encephalopathy
(any answer not on the list that the examiner considers plausible or can verify to attract a mark)
Discussion
a) List five neurological signs associated with a lateral medullary infarction. (25% marks)
All the classical stroke syndromes can be found listed and described here.
The latery medullural syndrome (Wallenberg syndrome) consists of the following classical findings:
- On the side of the lesion:
- Facial sensory loss
- Nystagmus
- Horner's syndrome
- Loss of gag reflex
- Ipsilateral ataxia with a tendency to fall to the ipsilateral side
- On the contralateral side:
- Pain and temperature sensory loss in the extremities
- Generally:
- Vertigo
- Nausea
- Dysphagia
b) List four neurological signs of a third cranial nerve palsy. What clinical feature of the palsy would distinguish between an intracranial mass lesion or diabetic neuropathy as the cause? (20% marks)
Lesions of the oculomotor nerve (CN III) include the following features:

- Ptosis
- Down-and-out pupil
- Mydriasis
- Failure of light reflex
(but consensual constriction of the opposite eye is intact) - Failure of accommodation
The college mention that "A mass lesion results in pupillary non-reactivity, in diabetes the pupil is spared". This is accurate: diabetes and other forms of microvascular disease cause a pupil-sparing oculomotor palsy. This is because the nerve's central core underoes ischemic infarction (authoritative source).
c) List five neurological deficits associated with a bulbar palsy, along with the corresponding cranial nerves which are affected. (25% marks)
This is an exercise in listing the bilateral lower motor lesions of nerves 9, 10, and 12. these data come from an article by
Absent gag reflex: due to bilateral lesions of CN IX and X
Soft palate paralysis which results in "imprecise consonants, hypernasality, and a decreased range of pitch and loudness" (because the weakness of the soft palate and pharyngeal muscules causes insufficient nasopharyngeal closure and reduced oral airflow). The resulting speech is breathy, quiet and the patient is generally unable to generate long phrases because they need to pause to take another breath. This is due to bilateral lesions of CN IX and X; a unilateral lesion of the same mechanism would cause a deviation of the uvula.
Paralysis of the laryngeal muscles: this causes a "soft, weak, low-pitched and
monotonous voice" which is the result of CN X paralysis. In bulbar palsy the volcal cords are hypoadducted, which promotes aspiration.
Tongue wasting and fasciculations due to CN XII paralysis; which also contributes to the inarticulate speech.
Dysphagia occurs because the process of swallwoing normally requires all the bulbar nerves to work in concert, and their weakness therefore results in an incoordinated swallow. Realistically, this is due to the dysfunction of nerves IX, X and XII, but also V and VII.
Drooling, because there is a loss of tone and strength in the muscles that control lip closure (CN VII). At the same time, due to decreased laryngeal sensitivity and motor function, there is progressive pooling of food and saliva in the vallecula and piriform recesses.
d) List six causes of dilated unreactive pupils not due to a primary intracranial lesion.
(30% marks)
Not due to an intracranial lesion would exclude all the usuals suspects:
- That is what the end of brainstem herniation looks like
- Bilateral midbrain lesion- eg. basilar artery infarct
- Bilateral 3rd nerve damage, eg. due to severe base of skull fracture
Thus, you are left with a list of differentials which could be massively broad:Fortunately, Critical Care and Resuscitation published a case report by a P.D. Thomas (2000) which fits this SAQ like a glove. Thomas' original classification is reproduced below, as well as a complimentary list which covers similar ground.

An alternative classification might follow a classical mnemonic for differential diagnosis, as this is what an exam candidate may fall back on when under stress.
- Vascular problems:
- Spinal infarction
- Severe global brain injury (eg. due to hypoxia)
- Infectious causes
- Botulism
- Syphilis (uveitis or neurosyphilis)
- Tetanus
- Neoplasms
- Drug-induced causes
- Anticholinergic drugs, topically or systemically
- Sympathomimetic drugs
- Serotonin syndrome
- Toxins from classican Strayan fauna: funnel web spider, taipan, blue-ring octopus, as well as tetrodotoxin
- Idiopathic causes
- Glaucoma
- Congenital causes
- Chronic blindness
- Autoimmune causes
- CNS vasculitis, eg. Bickerstaff brainstem encephalitis
- Optic neuritis due to MS
- Cranial nerve neuropathy due to Miller-Fisher variant of GBS
- Trauma
- Bilateral eye trauma
- Bilateral cataract repair
- Endocrine/metabolic pathology
- Phaeochromocytoma
- Hepatic encephalopathy
- Wernicke's encephalopathy
- Uraemic encephalpathy
In all honesty, one could not claim that bilateral prosthetic eyes are a valid member of a list of causes of bilaterally unreactive dilated pupils, because firstly why would anybody get a pair of prosthetic eyes with freakishly dilated pupils and secondly those aren't pupils.
References
Oh's Intensive Care manual: Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer. This chapter of Oh's has the distinction of having very few tables in it - there are only two, for an extremely long block of text.
Qureshi, Adnan I., et al. "Spontaneous intracerebral hemorrhage." New England Journal of Medicine 344.19 (2001): 1450-1460.
Caplan, L. R. "Basic Pathology, Anatomy, and Pathophysiology of Stroke." Caplan’s Stroke A Clinical Approach (2009): 23-4.
Walker, H. Kenneth, W. Dallas Hall, and J. Willis Hurst. "Clinical methods." 3rd edition.(1990). Chapter 63. Cranial Nerves IX and X: The Glossopharyngeal and Vagus Nerves- by Kenneth Walker
Rea, Paul. "Chapter 5: Hindbrain (Rhombencephalon)" Essential clinical anatomy of the nervous system. Academic Press, 2015.
Kühnlein, Peter, et al. "Diagnosis and treatment of bulbar symptoms in amyotrophic lateral sclerosis." Nature Reviews Neurology 4.7 (2008): 366.
Graham, P. J. "Congenital flaccid bulbar palsy." British medical journal 2.5400 (1964): 26.
Sang, Delia N., and Daniel M. Albert. "Retinoblastoma: clinical and histopathologic features." Human pathology 13.2 (1982): 133-147.
Sato, Hiromasa, Kosuke Naito, and Takao Hashimoto. "Acute isolated bilateral mydriasis: case reports and review of the literature." Case reports in neurology 6.1 (2014): 74-77.
Thomas, P. D. "The differential diagnosis of fixed dilated pupils: a case report and review." Critical Care and Resuscitation 2.1 (2000): 34.
Question 10 - 2019, Paper 2
Describe briefly the clinical features, differential diagnosis, initial diagnostic tests and treatments for a patient with suspected acute transverse myelitis.
College answer
Clinical Features: [3 marks]
Acute transverse myelitis is a clinical syndrome characterised clinically by rapid onset and progression of motor, sensory and autonomic dysfunction as a result of acute inflammation involving gray and white matter at one or adjacent levels in the spinal cord.
- History: recent vaccination, travel, recent infection (esp viral). History of motor, sensory or autonomic symptoms including pain, parathesiae.
- Clinical Findings:
- Motor weakness, paraparesis.
- Sensory level
- Autonomic signs – e.g. incontinence
Differentials (i.e. diagnoses other than those specifically associated with ATM);
[2 marks for any 4 of below]
- GBS
- Vascular event -Anterior spinal artery syndrome.
- Multiple sclerosis (similar but different immunopathogenesis – MS mediated through cell mediated immune aberration, ATM mediated through abnormal humoral immunity)
- Acute Compressive myelopathy due to bleed (e.g. AVM) or abscess
- Herpes zoster myelitis
- Post-polio syndrome (even in countries where polio has been eradicated)
- B12 deficiency (usually sub-acute)
Diagnostic work-up;
- CT spine to rule out compressive myelopathy, bleed
- MRI brain and spine with gadolinium contrast – MRI findings (T2 signal) may lag clinical findings
- CSF examination:
- variable cellular response dependent on sub-aetiology
- Culture and enterovirus PCR
- Oligoclonal bands and specific immunology (NMO, ADEM) [2 marks]
- Blood tests for anti-CNS and systemic auto-antibodies (don’t expect fine print, bonus marks for candidates knowing association of NMO with acquaporin-4 IgG antibodies)
- Blood for B12 levels
- ENMG (neurophysiology), if possibility of neuropathy remains.
Note: Must include imaging (either CT scan or MRI) and CSF examination in this section to score full marks.
Specific Treatments to be initiated; [3 marks]
– should be commenced awaiting definitive diagnosis
- Pulse corticosteroids for ADEM, NMO and ATM associated with auto-immune diseases are usual care; trials lacking
- Plasma exchange: for ADEM, NMO
- IVIG described
Discussion
This question is a welcome evolution of Question 3 from the second paper of 2018, where (again) the trainees were asked to compare Guillaine-Barre syndrome to another lower motor neuron disease.
Clinical features
- History and background:
- Usually occurs as a postinfectious complication
- Can fall within the spectrum of coexisting MS
- Can coexist with acute disseminated encephalomyelitis
- Autoimmune diseases are associated (eg. SLE, scleroderma, etc)
- Often, very rapidly progressing
- Weakness nadir is achieved within 4 hours in some cases (though some take as long as 21 days)
- Examination findings:
- Power
- Bilaterally decreased power
- Symmetrical
- Weakness remains at and below the level of the lesion
- "Pyramidal" preference: flexors of the legs and the extensors of the arms
- Tone
- Initially flaccid
- Later, hypertonic spasticity
- Reflexes
- Depressed initially
- Hyperreflexia subsequently
- Sensation
- Sensation is usually absent
- There is usually a distinct symmetrical sensory level
- Cranial nerves
- Usually, not involved
- When it forms a part of the MS spectrum, there may be optic neuritis
- Autonomic dysfunction
- Usually, no dysfunction, unless the level of the lesion is high
- High lesions may present with spinal shock
- Power
Differential diagnosis
- Vascular causes
- spinal cord infarction
- Infectious causes
- Polyomyelitis
- Epidural abscess
- Herpes zoster
- Neoplastic causes
- Spinal canal tumour
- Drug-related causes
- B12 deficiency
- Steroid-induced myopathy
- Hereditary distal neuropathies
- Spinobulbar muscular atrophy (Kennedy's disease)
- genetically heterogeneous distal hereditary motor neuropathies
- Autoimmune/ immune-mediated diseases
- Guillain-Barré syndrome
- multifocal motor neuropathy (MMN)
- Chronic inflammatory demyelinating polyneuropathy (CIDP)
- Multiple sclerosis
- Myasthenia gravis
- Eaton-Lambert syndrome
- Myositis and dermatomyositis
- Iatrogenic causes
- Critical illness polyneuromyopathy
Initial diagnostic tests
- Bloods
- B12 level
- Aquaporin-4 IgG antibodies
- Lumbar puncture:
- Expect to see raised protein and lymphocytosis
- Test for viruses (zoster and enterovirus)
- Also, need culture and gram stain if an infection is still a serious differential
- Nerve conduction studies
- Reduced amplitude sensory nerve action potential (SNAP)
- Pathological F-wave responses
- Decreased conduction velocity of motor and sensory nerves.
- Electromyography
- Reduced amplitude of motor (MUP) action potentials
- MRI
- Noncontrast MRI reveals cord oedema at the level of the lesion (but in 40%, looks totally normal)
- Gadolinium-enhancing signal abnormality extending over one or more cord segments.
- Lesions occupy most of the transverse diameter of the cord (2/3rds)
Management
- High dose steroids: though there are no clinical trials, generally people tend to recommend giving 1g/day of methylprednisolone for 3-7 days
- Plasmapheresis should be offered to those patients who do not respond to steroids: though this recommendation is also extrapolated form the fact that other demyelinating autoimmune diseases benefit from plasmapheresis. Beh et al (2013) recommended 1.5 plasma volumes for 5 treatments over 10 days (i.e. every second day). This should be offered early, within 15 days of diagnosis
- Cyclophosphamide is recommended occasionally
- Rituximab has been attempted
- IV immunoglobulin is not usually recommended, as there is insufficient evidence
References
Beh, Shin C., et al. "Transverse myelitis." Neurologic clinics 31.1 (2013): 79-138.
Waters, Patrick, et al. "Aquaporin-4 antibodies in neuromyelitis optica and longitudinally extensive transverse myelitis." Archives of neurology 65.7 (2008): 913-919.
Question 14.1 - 2019, Paper 2
A 68-year-old male presents with sudden onset of coma. On examination, he is obtunded and has midsized pupils. His reflexes are difficult to elicit but present, and he has clearly extensor plantar responses bilaterally. He is intubated, and initial CT brain scan without contrast is normal.
a) Excluding a toxidrome, what is the most likely dagnosis?(25% marks)
College answer
Midbrain infarct
Discussion
What we know:
- The coma is of sudden onset
- Pupils are mid-sized (presumably both)
- Intact reflexes
- Extensor (abnormal) plantars
- Normal CT brain
So: the main focal finding is bilateral mid-dilated pupils. There is actually quite a large list of possibilities as to what this could be. Here's a nice diagram from Critical Care and Resuscitation (case report by P.D. Thomas, 2000).

However, with all the toxic stuff excluded, the intracranial lesions causing this finding usually are:
- Severe diffuse hypoxic brain injury
- Bilateral midbrain lesion
- Bilateral 3rd nerve injury (eg. traumatic)
- Bilateral eye trauma
- Terminal stages of brainstem herniation
So the CT is normal, so we know the patient is not coning immediately, and presumably there is no intracranial explanation as to why their third nerves would suddenly be severed (nor would that give you upgoing plantars anyway). Diffuse hypoxic brain injury might also give you a relatively normal scan result, and presumably the examiners would have given you at least partial marks for this, but overall the midbrain lesion becomes more likely.
References
Plum, Fred, and Jerome B. Posner. The diagnosis of stupor and coma. Vol. 19. Oxford University Press, 1982. - warning! This link takes you to a download of the whole 9.0Mb file, which represents the entire volume of the 1980 second edition.
Bateman, David E. "Neurological assessment of coma." Journal of Neurology, Neurosurgery & Psychiatry 71.suppl 1 (2001): i13-i17.
Sato, Hiromasa, Kosuke Naito, and Takao Hashimoto. "Acute isolated bilateral mydriasis: case reports and review of the literature." Case reports in neurology 6.1 (2014): 74-77.
Thomas, P. D. "The differential diagnosis of fixed dilated pupils: a case report and review." Critical Care and Resuscitation 2.1 (2000): 34.
Question 14.3 - 2019, Paper 2
A 64-year-old male presented with vomiting, and was ventilated for two days after an acute aspiration episode. Two days after extubation, he is noted to freely aspirate oral fluids without a resultant cough. His left pupil is constricted, and he appears clumsy with his left hand. On further examination you find no weakness, but he has past pointing in the left arm. There is nystagmus on looking to the left.
a) Where is the likely neurologic lesion? (15% marks)
b) What is the most common pathology? (10% marks)
College answer
a) Lateral part of medulla (Lateral Medullary Syndrome acceptable)
b) Occlusion of PICA branch
Discussion
Important features here are:
- History of nausea
- Clearly some sort of serious swallowing dysfunction
- Left sided miosis
- Left sided incoordination (obviously cerebellar)
- Left sided nystagmus
So, to localise this, it is clear something must be going on at the level of the cerebellum. However, an isolated cerebellar lesion would not be producing that miosis. That would require a lesion which interrupts descending sympathetic fibres, leaving behind the parasympathetic stimulus from the midbrain. The combination of the two leads you to the lateral medulla.
In summary, the features of lateral medullary syndrome are:
- On the side of the lesion:
- Facial sensory loss
- Nystagmus
- Horner's syndrome
- Loss of gag reflex
- Ipsilateral ataxia with a tendency to fall to the ipsilateral side
- On the contralateral side:
- Pain and temperature sensory loss in the extremities
- Generally:
- Vertigo
- Nausea
- Dysphagia
The most likely culprit is the PICA, but a lateral medullary syndrome can also develop due to a large number of different lesions, likely accounting for the wide variation in individual brainstem vascularity. Anatomically, the damaged territory is supplied by the PICA, but PICA-specific occlusions are apparently in the minority; about 80% of lateral medullary strokes happen because the vertebral artery is occluded (Kim et al, 2016)
References
Oh's Intensive Care manual: Chapter 51 (pp. 568) Acute cerebrovascular complications by Bernard Riley and Thearina de Beer. This chapter of Oh's has the distinction of having very few tables in it - there are only two, for an extremely long block of text.
Qureshi, Adnan I., et al. "Spontaneous intracerebral hemorrhage." New England Journal of Medicine 344.19 (2001): 1450-1460.
Caplan, L. R. "Basic Pathology, Anatomy, and Pathophysiology of Stroke." Caplan’s Stroke A Clinical Approach (2009): 23-4.
Hong, Yuehui, et al. "Lesion Topography and Its Correlation With Etiology in Medullary Infarction: Analysis From a Multi-Center Stroke Study in China." Frontiers in neurology 9 (2018): 813.
Kim, Jong S., and Louis R. Caplan. "Clinical stroke syndromes." Intracranial Atherosclerosis: Pathophysiology, Diagnosis and Treatment. Vol. 40. Karger Publishers, 2016. 72-92.
Lui, Forshing, and Steve S. Bhimji. "Wallenberg syndrome." StatPearls [Internet]. StatPearls Publishing, 2018.
Question 21 - 2019, Paper 2
A 59-year-old female is transferred to your ICU febrile with a reduced level of consciousness. Her family have noted major behavioural change over the past three weeks.
MRI scan with contrast (two days ago) showed increased T2 and FLAIR signal in both frontal lobes, not conforming to a vascular pattern.
CSF Examination has shown the following:
|
Parameter |
Patient Value |
Adult Normal Range |
|
Opening pressure |
40 cm* |
15 – 25 |
|
Glucose |
4.8 mmol/L |
3.3 – 6.1 |
|
Protein |
2.24 g/L* |
0.10 – 0.50 |
|
Red Cell count |
50 cells/high power field* |
0 – 5 |
|
White Cell Count |
270 cells/high power field* |
0 – 5 |
|
Lymphocytes |
99% |
|
|
Gram stain |
Nil bacteria seen |
She has been receiving Ceftriaxone and Acyclovir at appropriate doses since admission. Please outline:
- The differential diagnosis for her presentation. (40% marks)
- The specific investigations you would order and the specific treatment for the differentials. (60% marks)
College answer
The differential diagnosis for her presentation
The clinical presentation is suggestive of Encephalitis with numerous possible aetiologies
Infective:
HSV still possible, but less likely with relatively normal MRI (no temporal involvement) VZV
Enterovirus HIV
Influenza
Cryptococcal disease (unlikely without leptomeningeal involvement) Lyssavirus, Hendravirus if bat exposure
Arthropod borne viruses
Murray Valley
Equine
Japanese encephalitis
many others up to and including rabies
Post infectious encephalitis (acute disseminated encephalomyelitis)
Auto-immune and para-neoplastic
anti-NMDA receptor encephalitis is the best studied, many other targets now described: association with ovarian cancer, endometrial cancer, small cell lung cancer; esp. anti-NMDA systemic auto-immune disease, e.g. SLE (limbic encephalitis)
Malignant
unlikely with minimal MRI findings lymphoma given lymphocyte predominance
Specific Investigations
CSF (existing sample or repeat) for viral PCR (HSV, VZV, enteroviruses) and serology for suspected pathogens, oligoclonal bands Anti-NMDA antibodies, other CNS antibodies, oligo-clonal bands, Cytology & flow cytometry
Auto-antibodies: ANA, anti-dsDNA etc. HIV testing
EEG
Imaging to look for systemic malignancy (ovarian, endometrial, breast, lung) Investigations to consider down the track
Brain biopsy
Repeat MRI to assess for evolution
Specific treatment
Specific treatment depends on underlying aetiology, which may be challenging to establish
Some comment on current antimicrobial therapy: would be reasonable to broaden current therapy given progression and ongoing fevers:
Viral encephalitis
No specific therapies for most viruses other than HSV
Could consider broadening anti-virals to ganciclovir (as guided by ID) Auto-immune encephalitis:
These disorders are highly responsive to immunomodulatory therapies and early initiation of treatment improves outcomes.
Once infectious cause ruled out, and there are no contraindications, commence immunotherapy in discussion with neurology/ID
no RCT, strong recommendations for pulse steroid, plasma exchange, IVIG other therapies for resistance incl. rituximab, pulse cyclophosphamide
Look for and treat underlying malignancy.
Discussion
First of all, this presentation clearly meets the (vague) internationally agreed-upon criteria for encephalitis. We have evidence of an altered level of consciousness, abnormal imaging and CSF pleocytosis with a very elevated protein. There is a million different potential causes for somtheing like this, but generally they tend to fall into "infectious" and "autoimmune" categories:
|
Aetiologies of encephalitis |
Mimics of encephalitis |
|
Infectious
Neoplastic /paraneoplastic
Inflammatory and idiopathic
Congenital
Autimmune
|
Vascular
Infectious
Neoplastic /paraneoplastic
Drug-induced
Inflammatory and idiopathic
Traumatic
Metabolic
|
Specific investigations: To borrow from the 2014 paper by Venkatesan, the following routine and "conditional" investigations are recommended for various specific pathologies:
Routine studies
- CSF: opening pressure, cell count with differential, protein, glucose
- Gram stain and bacterial culture
- HSV-1/2 PCR (if test available, consider HSV CSF IgG and IgM in addition)
- VZV PCR
- Enterovirus PCR
- Cryptococcal antigen or India ink staining
- Oligoclonal bands and IgG index
- VDRL for syphilis
Serum
- Routine blood cultures
- HIV serology (consider RNA)
- Treponemal testing (rapid plasma reagin, specific treponemal test)
Imaging
- Neuroimaging (MRI preferred to CT, if available)
- Chest imaging (chest x-ray or CT)
Neurophysiology
- EEG
Other tissues/fluids
- When clinical features of extra-CNS involvement are present, this may be appropriate (e.g., biopsy of skin lesions; bronchoalveolar lavage or endobronchial biopsy)
Conditional studies
- Immunocompromised host:
- CMV PCR, HHV6/7 PCR, Toxoplasma gondii; MTB, fungal infections, West Nile Virus PCR
- Geographic factors
- Africa—malaria, trypanosomiasias, dengue
- Asia—Japanese encephalitis virus, dengue, malaria, Nipah virus
- Australia—Murray Valley encephalitis, Kunjin virus, Australian bat lyssavirus
- Europe—tick-borne encephalitis virus; if Southern Europe, consider WNV testing, Toscana virus testing
- Central and South America—dengue, malaria, WNV, Venezuelan equine encephalitis
- North America—geographically appropriate arboviruses (e.g., WNV, Powassan, LaCrosse, Eastern equine encephalitis virus, St. Louis encephalitis, dengue, Lyme)
- Season and exposure
- Summer/autumn: WNV and other arboviruses, tick-borne disease
- Cat (particularly if with seizures, paucicellular CSF)—Bartonella
- Tick exposure—tick-borne disease
- Animal bite/bat exposure—rabies
- Swimming or diving in warm freshwater or nasal/sinus irrigation—Naegleria fowleri
Specific management is defined by the specific aetiology, which is difficult if the list of differentials is so broad. However, a few different specific management strategies should be mentioned:
- Supportive management
- A, B, C: Intubate the patientto facilitate investigations (LP and MRI are challenging if they are having seizures or in the grip of a violent psychosis)
- Manage cerebral oedema with head positioning, hypetonic saline or mannitol
- Protect them from seizures with sedation and benzodiazepines or antiepileptics
- Specific management
- HSV: aciclovir 10mg/kg IV q8h
- CMV: ganciclovir, cidofovir, foscarnet
- HHV6: ganciclovir 5mg/kg IV q12h
- HIV: antiretroviral drugs
- Rabies: rabies immune globulin
- Bacterial aetiologies:
- TB: isoniazid, rifampicin, pyrazinamide and streptomycin
- Typical bacteria: ceftriaxone and vancomycin
- Autoimmune causes
- Methylprednisolone
- Dexamethasone
- Rituximab
- Cyclophosphamide
- Plasmapheresis
References
Venkatesan, Arun. "CLINICAL APPROACH TO ACUTE ENCEPHALITIS." (2017).
Singh, Tarun D., Jennifer E. Fugate, and Alejandro A. Rabinstein. "The spectrum of acute encephalitis: causes, management, and predictors of outcome." Neurology 84.4 (2015): 359-366.
Granerod, J., et al. "Challenge of the unknown: a systematic review of acute encephalitis in non-outbreak situations." Neurology 75.10 (2010): 924-932.
Granerod, J., et al. "Causality in acute encephalitis: defining aetiologies." Epidemiology & Infection 138.6 (2010): 783-800.
Venkatesan, Arun, and Romergryko G. Geocadin. "Diagnosis and management of acute encephalitis: A practical approach." Neurology: Clinical Practice 4.3 (2014): 206-215.
Virchow, Rud. "über interstitielle Encephalitis." Virchows Archiv 44.4 (1868): 472-476.
Venkatesan, Arun, et al. "Case definitions, diagnostic algorithms, and priorities in encephalitis: consensus statement of the international encephalitis consortium." Clinical Infectious Diseases 57.8 (2013): 1114-1128.
Johnson, Richard T. "Acute encephalitis." Clinical Infectious Diseases (1996): 219-224.
Arbelaez, Andres, et al. "Congenital Brain Infections." Topics in Magnetic Resonance Imaging 23.3 (2014): 165-172.
Ducros, Anne. "Reversible cerebral vasoconstriction syndrome." The Lancet Neurology 11.10 (2012): 906-917.
Dalmau, Josep, and Myrna R. Rosenfeld. "Autoimmune encephalitis update." Neuro-oncology 16.6 (2014): 771-778.
Question 4 - 2020, Paper 1
Briefly describe the indications, post-procedure management and procedural complications of endovascular clot retrieval (ECR) for acute stroke.
College answer
Indications: 2 Marks
- Ischaemic stroke with proven large-vessel occlusion on CT Angiogram (naming vessels not necessary) (1 mark)
- Onset of symptoms up to 24 hours if CT imaging is supportive. (0.5 marks)
- Functionally independent prior to stroke (0.5 marks)
Post-procedure management: 4 Marks
- Admission to monitored environment (e.g. stroke unit / HDU), usually intubated for procedure, so may describe extubation plan
- Observe vascular access site for complications
- Neurological monitoring for haemorrhagic transformation or further ischaemic complications
- Blood Pressure Target: control as per agreed targets
- Aspirin, 24-hours after thrombolysis and exclusion of haemorrhagic complications
- Other neuroprotective measures (BSL, Na, position, temperature, CO2 etc.)
- Oral intake after speech pathology assessment in patients with clinical neurological deficit
- Mechanical DVT prophylaxis/stress ulcer prophylaxis.
- Longer term management dependent on extent of deficit
Complications: 4 Marks
-
- Direct device-related vascular injury:
- vessel perforation
- symptomatic intracranial haemorrhage
- subarachnoid haemorrhage
- Direct device-related vascular injury:
-
-
- arterial dissection
- emboli to new territories
- vasospasm
- Vascular access site complications:
- dissection
- pseudoaneurysm
- retro-peritoneal Haematoma
- infection
- Contrast-related:
- Allergy
- Renal Injury
- Any complications related to anaesthesia
-
Examiners Comments:
Many candidates provided only generic responses without specific detail.
Discussion
Briefly, they said. The current AHA/ASA guideline source for these indications and post-procedure considerations is Prabhakaran et al (2026).
- Indications:
- Ischaemic stroke with large vessel occlusion
- Substantial neurological deficit, NIHSS ≥ 5
- Timeframe criteria:
- Less than six hours: "broad clinical and imaging criteria"
- 6-24 hour window: "significant volume of salvageable tissue"
- Good level of premorbid independence
- Complications:
- Bleeding (though the risk of symptomatic ICH is no higher)
- Cerebral oedema
- Vascular access site complications
- Evidence:
- DAWN trial: 206 patients, 49% had good functional outcome vs 13%
- DEFUSE-3 trial: 186 patients, 47% had good functional outcome vs 17%
- Other trials: EXTEND1A, ESCAPE, SWIFT-PRIME, REVASCAT
- Post-procedure management:
- Extubate early, if able.
- Mechanical ventilation focuses on maintenance of normoxia and normocapnia
- Blood pressure control:
- Aim for SBP <140-160 for fully revascularised patients
- Aim for MAP 10-20% over normal baseline and SBP <185 for partially revascularised patients
- Minimise sedation and maximise the opportunity for regular reassessment
Also, scan their head after the first 24 hrs. - Control of electrolytes to prevent AF
- Maintenance of neutral fluid balance
- Glucose control: hyperglycaemia is harmful
- Antiplatelets after 24 hrs (earlier if they had an endovascular stent)
- Fever is harmful: paracetamol is recommended
References
Nogueira, R. G., et al. "Endovascular approaches to acute stroke, part 2: a comprehensive review of studies and trials." American Journal of Neuroradiology30.5 (2009): 859-875.
Silva, Gisele S., and Raul G. Nogueira. "Endovascular Treatment of Acute Ischemic Stroke." CONTINUUM: Lifelong Learning in Neurology 26.2 (2020): 310-331.
Brinjikji, Waleed, et al. "Patient outcomes with endovascular embolectomy therapy for acute ischemic stroke a study of the national inpatient sample: 2006 to 2008." Stroke 42.6 (2011): 1648-1652.
Kidwell, Chelsea S., et al. "Design and rationale of the mechanical retrieval and recanalization of stroke clots using embolectomy (mr rescue) trial."International Journal of Stroke 9.1 (2014): 110-116.
Jansen, Olav, et al. "Neurothrombectomy for the treatment of acute ischemic stroke: results from the TREVO study." Cerebrovascular Diseases 36.3 (2013): 218-225.
Furlan, Anthony, et al. "Intra-arterial prourokinase for acute ischemic stroke: the PROACT II study: a randomized controlled trial." Jama 282.21 (1999): 2003-2011.
Ma, Alice, Gerard Moynihan, and Lachlan H. Donaldson. "Intensive Care Management Following Endovascular Clot Retrieval for Acute Stroke: A Systematic Review of the Literature." Journal of Clinical Interventional Radiology ISVIR (2019).
Rodrigues, Filipe Brogueira, et al. "Endovascular treatment versus medical care alone for ischaemic stroke: systematic review and meta-analysis." bmj 353 (2016): i1754.
Hao, Yonggang, et al. "Risk of intracranial hemorrhage after endovascular treatment for acute ischemic stroke: systematic review and meta-analysis." Interventional neurology 6.1-2 (2017): 57-64.
Nogueira, Raul G., et al. "Thrombectomy 6 to 24 hours after stroke with a mismatch between deficit and infarct." New England Journal of Medicine 378.1 (2018): 11-21.
Albers, Gregory W., et al. "Thrombectomy for stroke at 6 to 16 hours with selection by perfusion imaging." New England Journal of Medicine 378.8 (2018): 708-718.
Prabhakaran, Shyam, et al. "2026 Guideline for the Early Management of Patients With Acute Ischemic Stroke: A Guideline From the American Heart Association/American Stroke Association." Stroke (2026).
Leslie-Mazwi, Thabele, et al. "Post-thrombectomy management of the ELVO patient: Guidelines from the Society of NeuroInterventional Surgery." Journal of neurointerventional surgery 9.12 (2017): 1258-1266.
van de Graaf, Rob A., et al. "Periprocedural antithrombotic treatment during acute mechanical thrombectomy for ischemic stroke: a systematic review." Frontiers in neurology 9 (2018): 238.
Torbey, Michel T., et al. "Evidence-based guidelines for the management of large hemispheric infarction." Neurocritical care 22.1 (2015): 146-164.
Ananthasubramaniam, Karthik, et al. "How safely and for how long can warfarin therapy be withheld in prosthetic heart valve patients hospitalized with a major hemorrhage?." Chest 119.2 (2001): 478-484.
Question 6 - 2020, Paper 1
Compare and contrast the clinical manifestations, aetiology, treatment and complications of posterior reversible encephalopathy syndrome (PRES) with herpes simplex virus (HSV) encephalitis
College answer
|
PRES |
HSV encephalitis |
||
|
Clinical manifestations (4 marks) |
The symptoms of PRES evolve rapidly over hours to days Hypertension is frequent but not invariable. The hypertensive crisis may precede the neurologic syndrome by 24 hours or longer. The clinical syndrome of PRES is characterized by
Rarely patients can have symptoms referable to the upper cervical spinal cord (limb weakness, bladder dysfunction), along with one or more of the symptoms above. |
Focal neurologic findings are usually acute - <1 week in duration - and include
The majority of patients will have one of the above symptoms plus fever |
|
|
Aetiology (1 mark) |
|
HSV |
|
|
Management (3 marks) |
|
IV acyclovir |
|
|
Complications (2 marks) |
|
-Behavioural abnormalities |
|
|
-death |
|||
|
- cognitive impairment |
|||
|
-seizures |
|||
Discussion
Though the college must be commended for their lucid tabulated answer, the inclusion of "death" in the complications deserves a raised eyebrow (because surely that can't have attracted a grade if the trainees wrote it). Also, just putting "HSV" under the "aetiology" heading would have probably attracted comments like "insufficient knowledge and detail"
Anyway, the specific information regarding HSV encephalitis is derived from by Bradshaw & Ventakesan (2016) for HSV, and Walter Bartynski (Part 1 or Part 2, 2008) for PRES.
| HSV encephalitis | PRES |
| Pathophysiology / aetiology | |
|
|
| Clinical manifestations | |
|
Historical features and symptoms
Features on examination
CSF biochemistry
Radiology/neurophysiology
|
Historical features and symptoms
Features on examination
CSF biochemistry (Ellis, 2019)
Radiology/neurophysiology
|
| Treatment | |
|
|
| Complications | |
|
Hypertensive complications (Fischer et al, 2017)
Persistent neurological sequelae are rare Persisting epilepsy may occur |
References
Staykov, Dimitre, and Stefan Schwab. "Posterior reversible encephalopathy syndrome." Journal of Intensive Care Medicine 27.1 (2012): 11-24.
Bartynski, W. S. "Posterior reversible encephalopathy syndrome, part 1: fundamental imaging and clinical features." American Journal of Neuroradiology 29.6 (2008): 1036-1042.
Bartynski, W. S. "Posterior reversible encephalopathy syndrome, part 2: controversies surrounding pathophysiology of vasogenic edema." American Journal of Neuroradiology 29.6 (2008): 1043-1049.
Bradshaw, Michael J., and Arun Venkatesan. "Herpes simplex virus-1 encephalitis in adults: pathophysiology, diagnosis, and management." Neurotherapeutics 13.3 (2016): 493-508.
Sili, Uluhan, et al. "Herpes simplex virus encephalitis: clinical manifestations, diagnosis and outcome in 106 adult patients." Journal of Clinical Virology 60.2 (2014): 112-118.
Ellis, Colin A., et al. "Cerebrospinal fluid in posterior reversible encephalopathy syndrome: implications of elevated protein and pleocytosis." The Neurohospitalist 9.2 (2019): 58-64.
Question 22 - 2020, Paper 1
A 48-year-old patient with Guillain Barre Syndrome who has been hospitalised for 30 days was recently re-admitted to your ICU with septic shock. He required mechanical ventilation via his tracheostomy, vasopressor treatment, and is now recovering.
a) What factors in this patient contribute to an increased risk for nosocomial infections?
(30% marks)
b) How would you reduce the risk of him acquiring another nosocomial infection while in the ICU?
(70% marks)
College answer
This question had several aspects to it that required structure to cover those elements. Candidates were expected to cover elements related to the specific patient care of the individual patient but also to cover general ICU aspects in regard to infection prevention management. Detailed descriptions were not required, as long as the general elements were covered with some relevant examples. Especially important points are underlined.
A)
Recognition that long stay patient in hospital who has a tracheostomy is a high risk patient for exposure to and/or colonisation with potential resistant flora and is therefore at risk for development of nosocomial infections (3 marks)
-
-
-
- Increased risk if higher severity of illness, significant comorbidities ,diabetes, malnutrition or immunosuppressed (all critically unwell patients at risk)
- Previous or ongoing antibiotic treatment, specifically when complex regimens and/or prolonged duration
- Open wounds, pressure sores
- Invasive devices – consider timely removal if not required or change when concern of colonisation
-
-
B)
- Prevention of specific infections in the intensive care unit (3 marks)
- Ventilator association pneumonia care bundle
-
-
- Prevention colonisation oral cavity (oral hygiene,
- Prevention aspiration (Nursing 30-45 degrees, subglottic aspiration, cuff pressure maintenance)
- Minimize duration of ventilation (minimise sedation, early mobilisation)
- Endotracheal and circuit care (HME, avoid routine ventilator circuit change, suction when required for secretions).
- CLABSI (central line associated blood stream infection) prevention bundle
- Insertion: Equipment (including PPE and catheter selection, dressing), preparation (including site selection) and sterile technique;
- Care: daily check insertion sites for signs of inflammation, daily review need (and remove when not required), check for lumen patency, hand hygiene and swab hub when handling. Consider timely removal if not required or change when concern of colonisation/infection/inflammation
- Documentation
- Education (staff experience)
- Infective diarrhea
- Vigilance/high index of suspicion for symptoms consistent with infective diarrhea, specifically for Clostridioides difficile
- Contact precautions/isolation (including hand washing) when C difficile suspected/confirmed
- Urinary tract infection
- consider timely removal of catheter if not required or change when concern of colonisation
-
NG tube/sinusitis- consider PEG.
- Environmental and personal aspects (2 marks)
- Hand hygiene
- Aseptic or sterile technique for procedures
- Personal protective equipment as per unit/hospital protocol, specifically in case of multi resistant organisms (ESBL, VRE, MRSA)
- Environmental hygiene (bench top cleaning, disposable versus non disposable curtains)
- Visitor education in regard to hand hygiene
- Antimicrobial stewardship – (some mention of appropriate antibiotic choice and de- escalation) multidisciplinary approach to provide correct treatment to patients with infections, improve outcome and to reduce risk of resistance development (2 marks)
- Regular screening for colonisation with
- Surveillance cultures (tracheal aspirate, urine if catheterised)
- Nasal/rectal swabs if concern for multi resistant organisms (VRE, MRSA)
- Knowledge of local microbiological data and resistance patterns
- Therapeutic guidelines on empiric antibiotic treatment
- De-escalation, change from parenteral to enteral antibiotics, avoid long duration when possible
- Regular screening for colonisation with
Discussion
Increased risk in GBS patients is hard to discuss, not because the topic is entirely unfamiliar to senior ICU trainees, but rather because the answer requires a structured approach, and with so much to discuss, it is difficult to know how best to structure such a vast amount of information. A certain discipline is also going to be required. A well-informed exam candidate will squander many minutes writing everything they know about this.
Let us consider this in terms of predisposing factors and the possible infection they cause. One way is to organise the factors is according to the infections they promote, and the process which has caused them. The ideas used to populate this table came from this article by Henderson et al (2003).
| Infectious consequences | Contributing factors |
| VAP |
|
| Sinusitis |
|
| Hospital-acquired pneumonia |
|
| Pressure area infections |
|
| Line-related sepsis |
|
| Urinary tract infection |
|
| Increased predisposition to infection |
|
| Resistant organisms |
|
With this exercise behind us, we can easily recombine the contributing factors into a structured list of interventions designed to address them:
| Factor | Intervention |
| Prolonged intubation |
|
| Gram-negative colonisation of the lower airway |
|
| Poor oral hygiene |
|
| Weak cough |
|
| Prolonged NGT dwell-time |
|
| Impaired airway defence reflexes |
|
| Prostration and basal atelectasis |
|
| Prolonged immobility |
|
| Prolonged need for parenteral medications |
|
| Long term IDC |
|
| Immunosuppressant therapies |
|
| Malnutrition |
|
| Resistant organisms |
|
| Cross-contamination with MROs |
|
References
Henderson, R. D., et al. "The morbidity of Guillain-Barré syndrome admitted to the intensive care unit." Neurology 60.1 (2003): 17-21.
Question 30 - 2020, Paper 1
a) List four causes and four clinical features of pseudo-bulbar palsy. (60% marks)
b) With regard to injury of the cervical spine, what are the key clinical findings that would differentiate a complete C3/4 injury from a complete C6/7 injury? (40% marks)
College answer
a)
Causes: (any four) (2 Marks)
-
- Bilateral strokes (Internal Capsule Infarcts)
- Multiple sclerosis
-
- Progressive Supranuclear Palsy
- Parkinsons Disease
- Multisystem Atrophy
- Amyotrophic Lateral Sclerosis (motor neuron disease)
- High brainstem tumours
- Head Trauma
Clinical Features: (any four) (4 Marks)
-
- Facial expressions: absent (expressionless face)
- Speech: spastic dysarthria (husky, nasal voice)
- Difficulty in chewing
- Dysphagia, drooling, and nasal regurgitation
- Tongue : Spastic, pointed; Difficulty in tongue protrusion due to spasticity (No wasting/ fasciculations)
- Palatal movement: absent
- Gag reflex: brisk (exaggerated)
- Jaw jerk: exaggerated; clonic
- Emotional lability (pseudobulbar affect)
b)
What are the key clinical findings that would differentiate a complete C3/4 injury from a complete C6/7 injury? (4 marks)
|
C3/4 |
C6/7 |
|
|
Motor function |
|
|
|
Reflexes |
o Absence of all reflexes in upper and lower limbs |
|
|
Sensation |
|
and medial aspect of forearm |
|
Respiratory |
o Phrenic nerve affected with weak diaphragm and reduced vital capacity |
o Phrenic nerve preserved, maybe mild or no reduction in VC depending on effect on other respiratory mechanics |
Examiners Comments:
Answers generally lacked enough detail and were poorly structured.
Discussion
It was something of a surprise to the author, when he discovered that the words "spastic", "spasticity" and "jaw" were hyperlinked to amboss.com in the college answer. This easter egg is of course unintentional, because the content of the answer was a lazy cut-and-paste from this article, and Word preserves hyperlinks.
a) The best article to cover this briefly turned out to be the pseudobulbar palsy chapter from StatPearls (NIH)
Causes:
- Vascular problems:
- Stroke (bilateral thalamic infarct)
- Infection:
- Classically, neurosyphilis
- Cerebral malaria
- Neoplasm
- Large petroclival meningioma
- Drug-induced:
- Methorexate-induced neurotoxicity
- Primary neurological problems
- Myotrophic lateral sclerosis
- Multiple sclerosis
- Parkinson disease
- Progressive supranuclear palsy
- Progressive multifocal leukoencephalopathy
- Congenital causes:
- Congenital malformations of the opercular or insular cortex
- Autoimmune cauises:
- Autoimmune encephalitis
- Hashimoto encephalopathy
- Trauma
- Traumatic brain injury
- Electrolyte abnormalities:
- Central pontine myelinolysis
Clinical features:
- Dysarthria
- Dysphagia
- Dysphonia
- Hypernasal voice, slurred speech
- Paralysis of the tongue
- Weakness of the mastication muscles
- Paralysis of facial muscles
- Emotional lability (pseudobulbar affect); classically, pathological laughter
- Trismus
- Exaggerated facial cranial nerve reflexes (suggesting an upper motor neuron cause)
- Brisk jaw jerk
- Retained or increased palatal reflexes.
- No atrophy or fasciculations of the affected muscles
b)
C3/C4:
- Motor:
- Motor power is lost except for shoulder shrug (spinal accessory nerve); and contrary to the college answer, it is widely believed that the trapezius muscle, and not the deltoid, is responsible for the shoulder shrug. Unless of course your shrug routinely involves some sort of weird arm abduction movements, in which case you are doing it wrong.
- Phrenic nucleus is affected: motor power is lost to diaphragm, i.e. spontaneous breathing is impossible
- Sensory:
- Sensation below the clavicles is absent
C67/C7:
- Motor:
- Elbow flexion and wrist extension is preserved
- Motor supply to the diaphragm is preserved
- Sensory:
- Sensation is present at the C6/7 level, which could include most of the lateral arms, thumb, index and middle finger
References
Saleem, Fatima, and Sunil Munakomi. "Pseudobulbar Palsy." (2020).
Question 9 - 2020, Paper 2
You have been asked to see a 52-year-old female in the Emergency Department who presented with a fever of 39.5ºC and generalised tonic-clonic seizures. Apart from a persistent reduced level of consciousness, her vital signs are currently stable.
a) List three central nervous system (CNS) and three non-CNS aetiological classifications for her presentation, with an example of each. (30% marks)
b) List six findings on physical examination that would be important in differentiating between potential diagnoses. (30% marks)
c) Describe the specific laboratory tests/investigations you would perform or request in this patient with justification for your inclusions. (40% marks)
College answer
Not available.
Discussion
This patient with seizures and a persistently decreased level of consciousness has status epilepticus by the standard definition (where you fail to recover your level of consciousness within a reasonable timeframe).
a) Three CNS "aetiological classifications" (or could we just call them "causes"):
- Infectious causes (Meningitis/encephalitis. brain abscess)
- Autoimmune causes (eg. CNS vasculitis)
- Subarachnoid haemorrhage
Three extracranial reasons for fever and decreased level of consciousness:
- Infectious causes (eg. septic encephalopathy)
- Autoimmune causes (eg. TTP/HUS)
- Drugs (serotonin syndrome, drug withdrawal, NMS)
b) Six findings on physical examination:
- Petechii (TTP, meningococcal meningitis, DIC of sepsis)
- Meningism (meningitis, SAH)
- Focal neurological signs (brain abscess)
- Dilated pupils (serotonin syndrome, drug withdrawal)
- Anuria (TTP/HUS)
- Evidence of IV drug use (brain abscess, drug withdrawal, serotonin syndrome)
c) Investigations:
- LP (meningitis, encephalitis)
- EUC (TTP/HUS)
- ADAMTS-13 (TTP/HUS)
- CK (?rhabdomyolysis)
- Urine drug screen
- Blood cultures and inflammatory markers (sepsis, DIC)
One could also include:
- MRI/MRA (limbic encephalitis, cerebral vasculitis)
- CT brain (brain abscess, SAG)
- EEG (ongoing seizures?)
But- as one of the readers has pointed out - a typical examiner's response may be that "some candidates either listed investigations without a description, or included investigations that aren't sent to a laboratory, and scored zero marks."
References
Chapter 49 (pp. 549) Disorders of consciousness by Balasubramanian Venkatesh
Chapter 50 (pp. 560) Status epilepticus by Helen I Opdam
Tan, R. Y. L., A. Neligan, and S. D. Shorvon. "The uncommon causes of status epilepticus: a systematic review." Epilepsy research 91.2 (2010): 111-122.
Johnson, Nicholas, et al. "Anti-NMDA receptor encephalitis causing prolonged nonconvulsive status epilepticus." Neurology 75.16 (2010): 1480-1482.
Chen, James WY, and Claude G. Wasterlain. "Status epilepticus: pathophysiology and management in adults." The Lancet Neurology 5.3 (2006): 246-256.
Question 24 - 2020, Paper 2
a) Define delirium. (20% marks)
b) Outline your approach to the prevention of delirium in patients in your ICU. (80% marks)
College answer
Not available.
Discussion
This question is the repeat of a repeat of a repeat, and is an absolute gift. The weary exam candidate should be able to relax, letting their pen produce a muscle-memory automatic answer while their mind wanders away to a less depressing place.
a) Definition of delirium (the DSM V definition)
- Disturbance in attention (ie, reduced ability to direct, focus, sustain, and shift attention) and awareness.
- Change in cognition (eg, memory deficit, disorientation, language disturbance, perceptual disturbance) that is not better accounted for by a preexisting, established, or evolving dementia.
- The disturbance develops over a short period (usually hours to days) and tends to fluctuate during the course of the day.
- There is evidence from the history, physical examination, or laboratory findings that the disturbance is caused by a direct physiologic consequence of a general medical condition, an intoxicating substance, medication use, or more than one cause.
b) Prevention of delirium:
- Identification of at-risk patients
- Pre-existing dementia
- Hypertension
- Alcoholism
- High severity of illness at admission
- Control preventable risk factors:
- Minimise the use/duration of urinary catheters
- Minimise the use of restraints
- Decrease the use of opiates (especially morphine)
- Minimise the use of benzodiazepines (restrict to those who are withdrawing from drugs/alcohol)
- Rationalise polypharmacy
- Where possible, cease or reduce the dose of anticholinergic drugs
- Decrease deliriogenic stimuli of critical care environment:
- Is deliriogenic even a word?
- Encourage mobility: early mobilisation is the most evidence-supported intervention to prevent delirium (
- Minimise intrusive care during sleep, reducing sleep deprivation
- Encourage normal sleep-wake diurnal cycle, sun exposure, make use of rooms with outward-facing windows for delirium-prone patients
- Involve the relatives to calm the patient
- Keep noise to a minimum (eg. silence internal room alarms, turn off loud devices such as the suction catheter)
- Manage pain aggressively
- Prevent constipation proactively
- Watch electrolytes carefully (hypo/hypernatremia, hypo/hypercalcemia, uraemia, etc)
- Give them back their hearing aids and spectacles as soon as practical
- I they are intubated, minimise their sedation doses
- Treat underlying condition:
- Hypoxia, hypercapnia, hypotension - obviously the reason for the ICU admission
References
Cavallazzi, Rodrigo, Mohamed Saad, and Paul E. Marik. "Delirium in the ICU: an overview." Ann Intensive Care 2.1 (2012): 49.
Van Rompaey, Bart, et al. "Risk factors for intensive care delirium: a systematic review." Intensive and Critical Care Nursing 24.2 (2008): 98-107.
Schweickert, William D., et al. "Early physical and occupational therapy in mechanically ventilated, critically ill patients: a randomised controlled trial."Lancet (London, England) 373.9678 (2009): 1874-1882.
Stevens, Robert D., Karin J. Neufeld, and Tarek Sharshar. "Delirium in the ICU: time to probe the hard questions." Crit Care 15.1 (2011): 118.
Question 25 - 2021, Paper 1
a) Describe the various types of brain herniation with clinical features and radiological features.
(70% marks)
b) Describe the role of decompressive craniotomy in Traumatic Brain Injury. (30% marks)
College answer
Not available.
Discussion
a) Different types of brain herniation:
| Herniation | Radiological features | Clinical features |
| Subfalcine, or "midline shift" |
|
|
| Uncal |
|
|
| Central (descending transtentorial) |
|
|
| Tonsillar |
|
|
| Upward (ascending transtentorial) |
|
|
| Transcalvarial |
|
|
b) Note that the college asked to "discuss" the practice of decompressive craniectomy in TBI, not "critically evaluate" it. Still:
Rationale for decompressive craniectomy:
- Raised intracranial pressure contributes to secondary brain injury and morbidity/mortality from TBI
- Intracranial pressure is governed by the Monro-Kellie Doctrine, where intracranial content is confined within a finite space and any expansion of one component produces increased pressure on other components
- Decompressive craniectomy increases the volume available to the intracranial contents
- The consequence should be decreased ICP and decreased secondary brain injury.
Advantages:
- Maybe some sort of mortality benefit (cohort studies such as Sonuca et al, 2010; as well as RESCUIicp)
- Shorter ICU stay
- Less ICP-targeting interventions
- Lower ICP
Complications of decompressive craniectomy:
- Herniation though the defect
- Delayed paradoxical herniation
- Subdural hygroma
- Infection
- Bleeding
- Post-traumatic hydrocephalus
- "Sinking Flap Syndrome"
- Bone resorption
Evidence for decompressive craniectomy in TBI:
- DECRA: Unchanged mortality; worse disability outcome
- RESCUEicp: Improved mortality; worse disability outcome
References
Hahn, F. J., and J. Gurney. "CT signs of central descending transtentorial herniation." American Journal of Neuroradiology 6.5 (1985): 844-845.
Brazis, P., J. Masdeu, and Jose Biller. "Localization in Clinical Neurology." 2007 Lippincott Williams & Wilkins
Cuneo, Richard A., et al. "Upward transtentorial herniation: seven cases and a literature review." Archives of neurology 36.10 (1979): 618-623.
Cooper, D. James, et al. "Decompressive craniectomy in diffuse traumatic brain injury." New England Journal of Medicine 364.16 (2011): 1493-1502.
Hutchinson, Peter J., et al. "Trial of decompressive craniectomy for traumatic intracranial hypertension." New England Journal of Medicine 375.12 (2016): 1119-1130.
Torres, Roland. "DECRA… Where do we go from here?." Surgical neurology international 3 (2012).
Muñoz, Javier, et al. "Primary decompressive craniectomy in neurocritical patients. a meta-analysis of randomized controlled trials, cohort and case-control studies." Journal of Emergency and Critical Care Medicine 2.9 (2018).
Riveros Gilardi, Berta, et al. "Types of cerebral herniation and their imaging features." Radiographics 39.6 (2019): 1598-1610.
Question 29.2 - 2021, Paper 1
A 64-year-old male has been an in-patient in your ICU for one week following a subarachnoid haemorrhage. The following data were obtained from a CSF sample taken from the external ventricular drain:
|
Parameter |
Patient Value |
Adult Normal Range |
|
Glucose |
3.8 mmol/L |
2.2 – 3.9 |
|
Protein |
0.46 G/L |
0.15 – 0.50 |
|
White Cell Count |
20 x 106/L* |
< 5 |
|
Red Cell Count |
10,000 x 106/L* |
< 5 |
a) Interpret these results in the context of the brief history given. (20% marks)
College answer
Not available.
Discussion
This question is identical to Question 3.2 from the second paper of 2013.
This is a fairly straightforward data interpretation question. 10,000 / 20 = 500; which is the perfect ratio. This CSF is not infected, it just has blood in it.
Of course, in order to make a more accurate analysis, it would be good to also know the serum WCC, so that one may calculate the proper ratio.
A more detailed discussion of CSF analysis is available elsewhere.
References
Question 27 - 2021, Paper 2
A patient with newly diagnosed Guillain-Barré Syndrome (confirmed with LP and nerve conduction studies) has been referred to the ICU team for monitoring. They have requested admission to ICU for monitoring in case of deterioration.
a) Outline the factors you would consider in the decision on whether to admit this patient to the ICU.
(70% marks)
b) List the non-respiratory complications of severe Guillain-Barré Syndrome. (30% marks)
College answer
Not available.
Discussion
a)
Decision to admit a patient like this for monitoring is made on the basis of the interplay of numerous factors, as follows:
- Patient factors:
- Frailty, i.e. physiological reserve, age, baseline function, and whether ICU admission and aggressive treatment are appropriate
- History of chronic respiratory illness and other comorbidities
- New acute respiratory complications, eg. hospital-acquired pneumonia
- Clinical features suggesting worsening respiratory function, such as:
- Deteriorating peak flow (eg. a PEF rate less than 250 L/min)
- Falling FVC (say, below 20ml/kg, or a decrease of 50% from FVC predicted by age/height/gender)
- Falling MIP (say, under 30 cmH2O)
- Falling MEP (say, under 40 cmH2O)
- Poor cough
- Increasing PaCO2
- Disease factors:
- Time course of progression: i.e. rapid deterioration over recent days or stable plateau
- Type of disease, eg. "vanilla" GBS vs Miller-Fisher
- Involvement of the autonomic nervous system (it can produce the sort of haemodynamic instability that could make the ward staff very nervous)
- Whether appropriate treatment has been started, and how long ago
- Environmental factors:
- Evidence that the patient is not being monitored with sufficiently attentive diligence, eg. missing FVC data from previous days
- Level of skill of ward staff where the patient remains
- Monitoring capacity of the environment where the patient remains, eg. availability of continuous cardiac monitoring or oximetry
- Capacity of the ICU or hospital to care for the patient with GBS (eg. availability of immunoglobulin or plasmapheresis in a small regional hospital)
b)
Nonrespiratory complications of GBS include those directly related to GBS and those which are associated with the overall picture of prolonged immobility and long-term ICU stay:
- Airway complications
- Poor cough and dysphonia (cranial nerve involvement)
- Complications related to prolonged intubation or tracheostomy
- Circulatory complications:
- Haemodynamic instability and dysautonomia due to autonomic involvement
- Neurological:
- Paraesthesia
- Pain from motionlessness
- Psychological consequences of prolonged hospital stay
- Gastrointestinal:
- Ileus and constipation
- Malnutrition due to swallowing dysfunction
- Haematological:
- Increased risk of DVT and VTE
- Infectious complications:
- Increased predisposition to infection due to multiple indewlling devices, immunosuppressant therapy and prolonged hospital stay
- Hospital-acquired pneumonia
- Sinusitis due to long term NGT requirement
- UTI due to long term IDC requirement
- Cross-contamination with MROs
References
Ancona, Paolo, Michael Bailey, and Rinaldo Bellomo. "Characteristics, incidence and outcome of patients admitted to intensive care unit with Guillain-Barre syndrome in Australia and New Zealand." Journal of critical care 45 (2018): 58-64.
van Leeuwen, Nikki, et al. "Hospital admissions, transfers and costs of Guillain-Barré syndrome." PloS one 11.2 (2016): e0143837.
Lawn, Nicholas D., et al. "Anticipating mechanical ventilation in Guillain-Barré syndrome." Archives of neurology 58.6 (2001): 893-898.
Barnes, Stephanie L., and Geoffrey K. Herkes. "Guillain–Barré syndrome: clinical features, treatment choices and outcomes in an Australian cohort." Internal medicine journal 50.12 (2020): 1500-1504.
Shahrizaila, Nortina, Helmar C. Lehmann, and Satoshi Kuwabara. "Guillain-Barré syndrome." The Lancet (2021).
van den Berg, Bianca, et al. "Guillain-Barre syndrome: pathogenesis, diagnosis, treatment and prognosis." Nature Reviews Neurology 10.8 (2014): 469-482.
Yuki, Nobuhiro, and Hans-Peter Hartung. "Guillain–Barré syndrome." New England Journal of Medicine 366.24 (2012): 2294-2304.
Question 29 - 2021, Paper 2
You are called to review a 55-year-old female following difficult prolonged surgery for emergency clipping of a ruptured left middle cerebral artery (MCA) aneurysm. She had returned to the ICU three hours earlier, intubated, ventilated and with an external ventricular drain (EVD) in situ.
She has developed frank blood in the EVD, and her ICP has increased to 57 cmH2O. Outline your approach to her initial management.
College answer
Not available.
Discussion
This question is almost identical to Question 6 from the second paper of 2015, except this time some of the punctuation has been revised and some of the words rearranged. Also, this time, the patient is not hypertensive. The last time this question appeared, the college examiners had commented that "some candidates failed to recognise this as an emergency situation". Thus:
Introductory statement
- This is a super-urgent emergency critical situation of some importance.
Logistics
- Organise CT
- Inform theatres
- Inform neurosurgery
- Start organising equipment for urgent patient transport to OT via CT
Specific management
- Urgent CT angiogram
- Definitive surgical control
Endpoints of therapy
- SBP 150-170
- ICP <20
- SpO2 > 95%
- CO2 35 mmHg
ICP management:
- Position the head (45 °head up, facing straight)
- Loosen the ETT ties
- Remove the C-spine collar
- Decrease PEEP as much as possible
- Increase sedation
- Propofol sedation to decrease distress and thus decrease ICP
- Benzodiazepines may be of use (but they do not decrease the CMRO2 as much as propofol)
- Drain some CSF from the EVD
- Paralysis with neuromuscular junction blocker
- Osmotherapy
- Mannitol 20%
- Hypertonic saline
- Controversial measures
- Barbiturate coma if other methods of lowering ICP have failed
- Decompressive craniectomy
References
Question 12 - 2022, Paper 1
In a suspected case of autoimmune encephalitis:
a) List the investigations needed, and explain why they are required. (50% marks)
b) Outline a specific management plan for proven autoimmune encephalitis and its common complications. Do not include resuscitation in your answer. (50% marks)
College answer
Not available.
Discussion
a) Investigations listed here are partly to to confirm the diagnosis of autoimmune encephalitis, and partly to exclude other competing differentials.
CT brain
- To exclude structural brain lesions (stroke, haemorrhage, abscess)
- To exclude the possibility of raised intracranial pressure for the LP that follows
LP and CSF analysis
- Opening pressure, cell count with differential, protein, glucose (this helps exclude infections causes, and can reveal characteristic patterns)
- Gram stain and bacterial culture (to exclude meningitis)
- Specific infectious PCR on CSF
- HSV-1/2 PCR (if test available, consider HSV CSF IgG and IgM in addition)
- VZV PCR
- Enterovirus PCR
- Cryptococcal antigen or India ink staining
- VDRL for syphilis
- Mycobacteria PCR
- Specific autoimmune biomarkers in the CSF
- Oligoclonal bands and IgG index
- Numerous antibodies (see above) which are diagnostic for autoimmune encephalitis
Peripheral blood tests
- Blood cultures (to exclude systemic sepsis and septic encephalopathy)
- HIV serology (consider RNA)
- Treponemal testing (rapid plasma reagin, specific treponemal test)
- Autoimmune vasculitis screen (to exclude cerebral vasculitis)
Imaging
- MRI - because autoimmune encephalitis may have a characteristic pattern
- CT imaging of the whole body, looking for:
- Occult malignancy (associated with many types of autoimmune encephalitis)
- Lymphadenopathy, granulomatous disease, etc (suspicion of TB)
Neurophysiology
- EEG
Other tissues/fluids
- When clinical features of extra-CNS involvement are present, this may be appropriate (e.g., biopsy of skin lesions; bronchoalveolar lavage or endobronchial biopsy)
b)
Management options for autoimmune encephalitis, and their complications:
- High dose ("pulse") methylprednisolone or dexamethasone
- Hyperglycaemia
- Insomina, agitation, psychosis
- Fluid retention
- Muscle wasting, delayed weaning from ventilation
- Impaired wound healing
- Increased propensity to infection (eg. PJP)
- Rituximab
- Long term loss of humoral immunity
- Infusion reaction
- Lymphopenia
- Cyclophosphamide
- Bone marrow suppression
- Renal tubular necrosis
- Pulmonary fibrosis
- Haemorrhagic cystitis
- IV immunoglobulin
- Risk of anaphylaxis
- Large hyperoncotic fluid load (circulatory overload)
- Plasmapheresis
- Bleeding complications of anticoagulation and vascular access
- Haemolysis and thrombocytopenia
- Hypothermia and complement activation
- Febrile reaction to replaced blood products
- Unavoidable removal of useful blood components (eg. useful drugs)
- Hypotension due to volume loss
References
Abboud, Hesham, et al. "Autoimmune encephalitis: proposed best practice recommendations for diagnosis and acute management." Journal of Neurology, Neurosurgery & Psychiatry 92.7 (2021): 757-768.
Dalmau, Josep, and Myrna R. Rosenfeld. "Autoimmune encephalitis update." Neuro-oncology 16.6 (2014): 771-778.
Venkatesan, Arun, and Romergryko G. Geocadin. "Diagnosis and management of acute encephalitis: A practical approach." Neurology: Clinical Practice 4.3 (2014): 206-215.
Granerod, J., et al. "Causality in acute encephalitis: defining aetiologies." Epidemiology & Infection 138.6 (2010): 783-800.
Venkatesan, Arun. "CLINICAL APPROACH TO ACUTE ENCEPHALITIS." (2017).
Singh, Tarun D., Jennifer E. Fugate, and Alejandro A. Rabinstein. "The spectrum of acute encephalitis: causes, management, and predictors of outcome." Neurology 84.4 (2015): 359-366.
Question 17 - 2022, Paper 1
Compare and contrast phenytoin, sodium valproate and levetiracetam under the following headings.
a) Mechanism of action (20% marks)
b) Pharmacokinetics (20% marks)
c) Adverse effects (30% marks)
d) Therapeutic monitoring (30% marks)
College answer
Not available.
Discussion
This question feels like some kind of refugee from the First Part syllabus. Certainly, anticonvulsants are well-explored in the primary papers, where numerous SAQs ask trainees to compare the properties of these substances.
| Phenytoin | Sodium valproate | Levetiracetam |
| Mechanisms of action | ||
|
|
|
| Pharmacokinetics | ||
|
|
|
| Adverse effects | ||
|
|
Side effects are neurocognitive and behavioural. These may include:
|
| Therapeutic monitoring | ||
|
|
|
References
Jones, Gary L., Gary H. Wimbish, and William E. McIntosh. "Phenytoin: basic and clinical pharmacology." Medicinal research reviews 3.4 (1983): 383-434.
Isbister, Geoffrey K., et al. "Valproate overdose: a comparative cohort study of self poisonings." British Journal of clinical pharmacology 55.4 (2003): 398-404.
Stockis, Armel, et al. "Clinical pharmacology of levetiracetam for the treatment of epilepsy." Expert review of clinical pharmacology 2.4 (2009): 339-350.
Question 28.4 - 2022, Paper 1
A 27-year-old patient with a prolonged ICU stay following a subarachnoid haemorrhage has developed fever with an altered consciousness level.
The CSF specimen result below was taken from the external ventricular drain.
|
Parameter |
Patient Value |
Adult Normal Range |
|
Red Blood Cells |
1946 x 106/L* |
0 – 5 |
|
Neutrophils |
198 x 106/L* |
0 – 5 |
|
Mononuclear cells |
74 x 106/L |
a) List your treatment decisions to be made based on the CSF. (10% marks)
b) Explain your rationale for the above. (10% marks)
College answer
Not available.
Discussion
The question that needs to be answered about the CSF is:
- is this just the decomposition of the clot in the ventricles causing aseptic ventriculitis, or
- is everything just inflamed from the irritant effects of the EVD being in situ for so long, or
- is this bacterial ventriculitis, and the EVD is infected?
For CSF following SAH, analysis is challenging because there is usually enough blood in the CSF to confuse everything, and the process of clot dissolution brings out the neutrophils and macrophages, producing leukocytosis. Annoyingly, the patient can also be febrile purely from the blood in the CSF, leaking inflammatory chemicals into the delicate sensory filaments of the hypothalamic thermostat.
So, what to do with this result? Pfausler et al (2004), reviewing the literature and their own retrospective case series, concluded that there were "no specific CSF features that distinguish in the early diagnosis of ventriculitis after SAH" and suggested that everyone should just give antibiotics anyway, because nosocomial bacterial ventriculitis has a very high morbidity and mortality. These can then be ceased two or three days later, when the CSF culture comes back negative.
Thus, one possible approach is:
a)
- Keep the EVD in situ
- Culture the CSF
- Commence IV antibiotics for the empirical treatment of ventriculitis
- Cease IV antibiotics if nothing grows from the CSF over 72 hrs
- If something grows, remove the EVD
b)
- The rationale for this aggressive approach is that a small fraction of patients with SAH will go on to develop nosocomial bacterial ventriculitis, and for these patients the outcomes are much worse (16% mortality, 20% persistent vegetative state, as per Panic et al, 2022)
- Perhaps 25% of patients with SAH and EVDs will develop fevers, and they will all have similar infected-looking CSF microscopy, but the majority will not have a genuine infection
References
Hoogmoed, J., et al. "Clinical and laboratory characteristics for the diagnosis of bacterial ventriculitis after aneurysmal subarachnoid hemorrhage." Neurocritical care 26.3 (2017): 362-370.
Pfausler, B., et al. "Cell index–a new parameter for the early diagnosis of ventriculostomy (external ventricular drainage)-related ventriculitis in patients with intraventricular hemorrhage?." Acta neurochirurgica 146.5 (2004): 477-481.
Beer, Ronny, Bettina Pfausler, and Erich Schmutzhard. "Management of nosocomial external ventricular drain-related ventriculomeningitis." Neurocritical care 10.3 (2009): 363-367.
Beer, R., et al. "Nosocomial ventriculitis and meningitis in neurocritical care patients." Journal of neurology 255.11 (2008): 1617-1624.
Panic, Hana, et al. "Etiology and Outcomes of Healthcare-Associated Meningitis and Ventriculitis—A Single Center Cohort Study." Infectious Disease Reports 14.3 (2022): 420-427.
Question 29 - 2022, Paper 1
A 22-year-old patient is admitted with an acute traumatic brain injury with raised intracranial pressure. They also have a severe acute kidney injury requiring renal replacement therapy (RRT). Outline the potential issues of providing RRT, including your management of the issues
College answer
Not available.
Discussion
This question is a reworded version of Question 21 from the first paper of 2018, which means readers can go there to see what the official college answer would likely have been.
| Domain | Recommendations | Rationale |
| Access | Avoid internal jugular lines | Promote venous drainage from the brain |
| Modality | Prefer CRRT | Produces a more gradual solute clearance; less likely to produce cerebral oedema |
| Low efficiency IHD/SLED | ||
| Frequency | Daily, if not continuous | Daily treatments decrease the fluctuations of urea |
| Blood flow | Start low, increase slowly | Minimise haemodynamic effects |
| Dialysate flow | Start low, increase slowly | Minimise solute clearance |
| Dose | Under-dialyse (by half) | Minimise solute clearance per unit time |
| Solute clearance | Pre-dilution haemofiltration | Minimise urea clearance: decrease the resulting urea gradient between brain parenchyma and blood, minimising cerebral oedema |
| Filtration | Low volume fluid removal | Minimise dialysis-associated hypotension to prevent cerebral hypoperfusion |
| Anticoagulation | Regional, or none | Prevent cerebral haemorrhage extension due to anticoagulation. Minimal anticoagulation is recommended for 2 weeks following TBI. |
| Dialysate | Add sodium | Minimise the hyponatremia which develops due to exposure to hyponatremic dialysate (to keep sodium around 145-150 mmol/L) |
| Add urea | Minimise urea clearance | |
| Minimise bicarbonate | Prevent intracellular acidosis (may be hypthetical) | |
| Fluid warmer | Temperature matching | Maintain therapeutic hypothermia if this is being used for ICP control |
References
Davenport, Andrew. "Renal replacement therapy in the patient with acute brain injury." American journal of kidney diseases37.3 (2001): 457-466.
Davenport, Andrew. "Renal replacement therapy for the patient with acute traumatic brain injury and severe acute kidney injury." Acute Kidney Injury. Vol. 156. Karger Publishers, 2007. 333-339.
Davenport, Andrew. "Practical guidance for dialyzing a hemodialysis patient following acute brain injury." Hemodialysis International 12.3 (2008): 307-312.
Yeh, Shih-Hao, Chen-Yu Wang, and Chien-Min Lin. "Preventing intracranial pressure fluctuation in severe traumatic brain injury during hemodialysis." Journal of Medical Sciences 36.4 (2016): 152.
Question 5 - 2022, Paper 2
a) List the disease specific interventions for a severe myasthenic crisis in a patient who is invasively ventilated. (50% marks)
b) List four classes of drugs with the potential to exacerbate a myasthenic crisis. (20% marks)
c) Discuss the challenges for a successful extubation in a patient specifically after a myasthenic crisis. Your answer should include methods to address the challenges. (30% marks)
College answer
Most candidates had a superficial understanding of myaesthenia gravis and myaesthenic crisis. Candidates who scored well were familiar with the pathogenesis of the disease and the triggers and treatments. However, even those candidates who referred to specific challenges such as fatiguability, bulbar dysfunction and secretion burden in the management section, often did not give a detailed discussion of how to manage these. Most candidates mentioned pyridostigmine and/or neostigmine, IVIG, plasma exchange, steroids and/or other immunosuppressants, and therefore scored well for part (a) (which was worth 50%).
Discussion
They said "list" the interventions, a syllabus keyword which conventionally does not invite very much discussion; and for 30% of the marks you'd really only be expected to produce a short point-form list:
- Specific interventions include:
- First line:
- Plasmapheresis, or IV immunoglobulin
- High dose steroids (prednisolone 1.0-1.5mg/kg/day)
- Second line
- Pulse steroids (1g methylprednisolone)
- Steroid-sparing agents (azathioprine, mycophenolate)
- Immune suppression (rituximab, cyclophosphamide)
- Complement deactivation (eculizumab)
- Acetylcholinesterase inhibitors (pyridostigmine)
- Thymectomy
- First line:
The list of drug classes that exacerbate myasthenia gravis include multiple different antibiotic classes, which - presumably- would have all counted individually
- Antibiotics:
- Aminoglycosides
- Macrolides
- Fluoroquinolones
- Beta-blockers
- Immune checkpoint inhibitors (ipilimumab, pembrolizumab, atezolizumab, and nivolumab)
- Statins
There is also a list of miscellaneous classless drugs that can trigger myasthenia exacerbations, and it is not clear what would have happened if the trainees had mentioned these:
- Iodinated contrast media
- Live attenuated vaccines
- Procainamide
- Hydroxychloroquine
- D-Penicillamine
- Desferrioxamine
- Challenges to the extubation of a myasthenia gravis patient (and methods to address them):
- Weakness (pyridostigmine)
- Cholinergic side effects, increased secretions (propantheline)
- Critical illness and steroid myopathy (dietary protein supplementation, physiotherapy, early mobility, use of steroid-sparing agents such as mycophenolate)
- Poor swallow or cough (tracheostomy as a bridge to future normal bulbar function)
- Slow weaning (so, extubate on to NIV)
- Marginal respiratory reserve (so, optimise VAP and CCF therapies before contemplating extubation)
An excellent paper on weaning the patient with neuromuscular disease was published by Torres-Castro et al in 2021, and likely served as the origin for this SAQ. Even though they did not find any papers that fit their inclusion criteria, they discuss the options in some detail, and the ideas in that paper were amalgamated into the table above.
References
Wendell, Linda C., and Joshua M. Levine. "Myasthenic crisis." The Neurohospitalist 1.1 (2011): 16-22.
Damian, Maxwell S. "Myasthenia Gravis in the ICU." Textbook of Neuroanesthesia and Neurocritical Care: Volume II-Neurocritical Care (2019): 41-50.
Schroeter, Michael, Günther Thayssen, and Julia Kaiser. "Myasthenia gravis–exacerbation and crisis." Neurology International Open 2.01 (2018): E10-E15.
De Baets, M., and M. H. W. Stassen. "The role of antibodies in myasthenia gravis." Journal of the neurological sciences 202.1-2 (2002): 5-11.
Hehir, Michael K., and Nicholas J. Silvestri. "Generalized myasthenia gravis: classification, clinical presentation, natural history, and epidemiology." Neurologic Clinics 36.2 (2018): 253-260.
Bedlack, Richard S., and Donald B. Sanders. "On the concept of myasthenic crisis." Journal of clinical neuromuscular disease 4.1 (2002): 40-42.
Narayanaswami, Pushpa, et al. "International consensus guidance for management of myasthenia gravis: 2020 update." Neurology 96.3 (2021): 114-122.
Zink, Joe, and Deepak Bose. "Cold potentiation of neuromuscular transmission in the avian biventer cervicis muscle." European journal of pharmacology 28.1 (1974): 149-156.
Sanders, Donald B., and Janice M. Massey. "Clinical features of myasthenia gravis." Handbook of Clinical Neurology 91 (2008): 229-252.
Lotan, Itay, et al. "Exacerbation of myasthenia gravis following corticosteroid treatment: what is the evidence? A systematic review." Journal of Neurology (2020): 1-14.
Dhawan, Priya S., et al. "IVIG versus PLEX in the treatment of worsening myasthenia gravis: what is the evidence?: a critically appraised topic." The neurologist 19.5 (2015): 145-148.
Farrugia, Maria Elena, and John A. Goodfellow. "A practical approach to managing patients with Myasthenia Gravis—Opinions and a review of the literature." Frontiers in Neurology 11 (2020): 604.
Torres-Castro, Rodrigo, et al. "Weaning from mechanical ventilation in people with neuromuscular disease: a systematic review." BMJ open 11.9 (2021): e047449.
Kim, Sun Mi, et al. "Successful extubation after weaning failure by noninvasive ventilation in patients with neuromuscular disease: case series." Annals of Rehabilitation Medicine 41.3 (2017): 450-455.
Question 5 - 2023, Paper 1
Describe a tiered strategy for the management of raised intracranial pressure in traumatic brain injury, including when each treatment should be considered. (100% marks)
College answer
Aim: To outline the process of management of raised ICP.
Key sources include: Paper 2015.1 q12, BTF guidelines. CanMEDS Medical Expert. Discussion: This is a repeat SAQ with an extension asking the candidate to nominate a tiered strategy and give an opinion on timing and implementation of each strategy for control of ICP. Most candidates had the basics of knowledge. Those candidates who did well were well organised, familiar with the guidelines for a tiered approach and provided specifics around timing and ICP levels for intervention and progression of interventions. Details for therapies such as osmotherapy targets and temperature targets were also a component of the better answers. The vast majority did well, and these candidates should be commended
Discussion
Question 12 from the first paper of 2015 is in fact a question about a patient with community-acquired pneumonia who has suddenly become impossible to ventilate. SAQs which actually involved the management of raised ICP have included:
- Question 29 from the second paper of 2021 (aneurysm clip fell off)
- Question 6 from the second paper of 2015 (aneurysm clip fell off again)
- Question 28 from the second paper of 2011 (sedation not working on ICP, halp)
- Question 12 from the first paper of 2004 (generic principles of ICP control)
- Question 5 from the second paper of 2002 (generic principles of ICP control)
This "tiered" approach SAQ likely refers to the 2019 SIBICC algorithm, and appears to be a test of the candidates' ability to reproduce these guidelines and apply them safely.
Thus:
- Tier Zero: basic neuroprotective strategies
- Elevated head of bed
- Fever prevention
- Removal of tight tube ties
- Removal of C-spine collar
- Tier One:
- Increase analgesia
- Increase sedation
- Maintain low-normal PaCO2 (35-38 mmHg)
- Mannitol or hypertonic saline bolus (up to an osmolality of 320 mOsm/kg, or a sodium of 155 mmol/L)
- CSF drainage by EVD
- Tier Two:
- Hyperventilate to 32-35 mmHg
- Use neuromuscular paralysis
- perform MAP challenge (increase MAP by 10mmHg to asssess autoregulation; if the ICP does not rise, autoregulation is intact) - if autoregulation is intact, use fluids/vasopressors/inotropes to increase CPP to 60-70
- Tier Three:
- Thiopentone coma
- Decompressive craniectomy
- Therapeutic hypothermia (35-36 C)
- Use of the tiered approach:
- When possible, use the lowest tier
- Move to the next tier if the ICP remains raised (CPP below 60-70)
- It is not necessary to use all the modalities within a tier before moving to the next tier
- Tiers can be skipped if this is considered advantageous
References
Brain Trauma Organisation Guidelines for Management Traumatic Brain Injury.
Hawryluk, Gregory WJ, et al. "A management algorithm for patients with intracranial pressure monitoring: the Seattle International Severe Traumatic Brain Injury Consensus Conference (SIBICC)." Intensive care medicine 45 (2019): 1783-1794.
Question 27 - 2023, Paper 1
Outline the role, advantages, and disadvantages of the following neuro-monitoring modalities, used in an intubated ICU patient with severe traumatic brain injury.
a) Clinical assessment. (20% marks)
b) ICP monitoring. (30% marks)
c) Cerebral blood flow monitoring. (30% marks)
d) Cerebral function and metabolism. (20% marks)
College answer
Aim: To explore the options available for neuromonitoring in TBI.
Key sources include: Paper 2010.1 Q8 compare and contrast EVD and fibre optic. 2009.2 Q25.1 - clinical assessment. CanMEDS Medical Expert.
Discussion: Parts a, b and c are repeat explorations of this topic. Many candidates did not gain marks by not attempting parts of the question. Marks were gained by answering questions discussing first principles. Whilst some techniques described in the question are not available in all centres, the principles underpinning their use are simple and well described in textbooks. Candidates are reminded that there is no negative marking, and it is recommended to attempt all parts of the question. First principle examples would include details on availability, cost, invasiveness, reproducibility, type, and volume of information gathered and complications.
Discussion
The examiners referenced Question 8 from the first paper of 2010, which asked for a comparison between an EVD and a fiberoptic pressure transducer, and Question 25.1 from the second paper of 2009, which actually asked for the sort of clinical features that would suggest raised intracranial pressure and imply that a head CT would be needed prior to a lumbar puncture. The added twist this time was "role", which would have made some of the candidates think carefully and choose their words. For example, considering c) and d) are not well-accepted or widespread, one could legitimately argue that they have no well-established role. One way of addressing this SAQ could have been to list the possible methods of each assessment and then discuss their advantages and disadvantages (eg. comparing EVD and fibreoptic catheters) but this would have missed an opportunity to showcase some higher-order analysis. What follows is an attempt to answer this question in a way that takes advantage of the stem to discuss the advantages and disadvantages of the whole concept, rather than specific applications of it.
a) Clinical assessment:
- Role: part of the ongoing tertiary survey of ICU patients with TBI
- Advantages:
- Gold standard of assessment
- Easily repeatable
- Cheap (i.e. minimal equipment cost)
- Thorough (can identify subtle deficits, eg. cranial nerve palsies)
- Reliable (especially when using validates scales, eg. the GCS)
- Disadvantages:
- Interpreter-dependent
- A full examination may take longer than other methods of assessment
- Confounded by sedation
- Often limited to the GCS, which may miss subtle changes
b) ICP monitoring:
- Role: titration of neuroprotective therapies to prevent secondary brain injury
- Advantages:
- Well accepted preventative methods, eg. supported by BTF guidelines
- An established range of therapies (eg. osmotherapy) are guided by ICP monitoring
- Well-practiced, and generally safe
- Disadvantages:
- Invasive, particularly EVDs
- Gradually less and less accurate (fibreoptic monitors)
- May not allow recalibration (fibreoptic monitors)
- Susceptible to infection (eg. ventriculitis)
c) Cerebral blood flow monitoring:
- Role: titration of neuroprotective therapies to prevent secondary brain injury
- Advantages:
- Non-invasive (in the case of transcranial doppler) or minimally invasive (in case of jugular oximetry)
- Supported by solid physiological principles, i.e plausible
- Specifically target a critically important endpoint (whereas ICP and CPP are surrogates for CBF, which is what we are really interested in)
- Can be used to assess the safety of hyperventilation
- Allows assessment of cerebral blood flow autoregulation
- Is prognostically important (as an extreme example, the absence of CBF can identify brain death)
- Disadvantages:
- Limited support from guidelines
- Expensive to implement (requires specific devices or consumables)
- Requires some training for use, and can be operator-dependent (transcranial Doppler), including being dependent on the availability of the operrator
- Therapies designed to prevent secondary brain injury are mostly described in the setting of ICP monitoring; to substitute CBF monitoring would mean to extrapolate from ICP-based treatment recommendations
- CBF monitoring quantifies the flow, but does not assess whether this quantity is adequate
d) Cerebral function and metabolism:
- Role: assessment of the adequacy of cerebral blood flow and extent of cerebral dysfunction
- Advantages:
- Can identify otherwise undetectable pathology (eg. EEG can detect non-convulsive status epilepticus)
- Can be used to target neuroprotective therapies (eg. where EEG is monitored to confirm the depth of thiopentone coma)
- Regional assessment of cerebral pathology becomes possible (eg. cerebral microdialysis can target specific at-risk areas)
- Functional impairment can be more easily detected or prognosticated (eg. with somatosensory evoked potentials)
- Not confounded by muscle relaxants
- Disadvantages:
- Limited to centres with experience, and mostly used for research purposes
- Expensive equipment
- Requires expertise and availability of specialist services
- Little support from guidelines and professional bodies
An extension of this SAQ into e) neuroimaging is also a plausible future avenue.
References
Kirkness, Catherine J. "Cerebral blood flow monitoring in clinical practice." AACN Advanced Critical Care 16.4 (2005): 476-487.
Casault, Colin, et al. "Multimodal brain monitoring following traumatic brain injury: A primer for intensive care practitioners." Journal of the Intensive Care Society 23.2 (2022): 191-202.
Feyen, B. F., et al. "Neuromonitoring in traumatic brain injury." Minerva anestesiologica 78.8 (2012): 949-958.
Lazaridis, Christos, and Brandon Foreman. "Management Strategies Based on Multi-Modality Neuromonitoring in Severe Traumatic Brain Injury." Neurotherapeutics (2023): 1-15.
Ropper, Alexander E., and John H. Chi. "Treatment of traumatic brain injury without direct intracranial pressure monitoring." Neurosurgery 72.4 (2013): N19-N20.
Question 1 - 2023, Paper 2
a) Discuss the assessment and challenges of diagnosing ventriculitis in a febrile patient with a subarachnoid haemorrhage (SAH) and an external ventricular drain (EVD) in situ. (6 marks)
b) Outline the principles of management if a diagnosis of EVD-related ventriculitis is strongly suspected or confirmed. (4 marks)
College answer
Syllabus topic/section:
2.1.3 Sepsis and Infections – L1.
2.1.8 Neurological Intensive Care – L1.
Aim:
1. To ask the candidate to demonstrate knowledge of assessment of the diagnosis of EVD related ventriculitis.
2. To test application of this knowledge to the clinical context and discuss the challenges of using the diagnostic criteria in a critically unwell patient.
3. To test knowledge of broad principles of management of EVD related ventriculitis.
Discussion:
To demonstrate competency of the subject, the answer needed to address every element requested in the stem. For part A candidate answers that addressed the assessment AND challenges as requested gained higher marks.
Examples of challenges include the difficulty of an accepted definition of ventriculitis, inflammatory changes due to brain injury with the presence of the EVD and features associated with SAH which will mask the features of infection amongst others. Candidates using the glossary of terms who structed their answer in terms of history (including risk factors for ventriculitis, e.g. patient related, and catheter related factors) examination findings and targeted investigations with rationale gained higher marks.
In Part B the expected transitional fellow level standard contained details of antibiotic choice and rationale, as well as a discussion on the management of the EVD and patient related factors. Ventriculitis is a pathology that has a specific therapy of antimicrobials and little requirement for ongoing source control, unlike, for example, pancreatitis. It is therefore necessary to go into detail about choice, rationale, timing, duration, and route in the explanation of antibiotics in this setting This is particularly important in severe ventriculitis where the intraventricular route is required for treatment resistant cases.
Marking rubric:
|
Part A Assessment and challenges 6 marks |
Inadequate detail Doesn’t appreciate the challenges of diagnosis. 0-2 marks |
Has knowledge of how to diagnose ventriculitis but has not demonstrated the challenges in the critically unwell patient. 2-3 marks |
Good detail present. Able to appreciate some of the challenges of making diagnosis of ventriculitis in poor detail. 3-4 marks |
Contained applied clinical perspective. Detailed and nuanced answer, Able to appreciate the challenges of making the diagnosis of ventriculitis. 5-6 marks |
|
Part B Principles of management 4 marks |
Superficial answer, minimal details about antibiotic choice. Minimal or no discussion about EVD. <2 marks |
Addresses antibiotics, EVD in limited detail. 1-2 marks |
Improved structured answer with more detail. Some organisation attempt of details. 2-3 marks |
Detailed and nuanced answer Included antibiotic choice, dose and rationale, management of EVD and considerations relating to change. 4 marks |
Discussion
This was the first time the exam was reported upon with so much luxurious detail, with marking rubrics and blueprinting links to the Syllabus for the Second Part Examination. The greatest challenge going forward for this sort of armchair commentary will no longer be the need to guess what was in the minds of the examiners when they wrote the paper, but how to craft an answer fit to get the maximum marks.
An additional point of interest is the removal of the "pass rate" metric, and its replacement with the Angoff score, as a better measure of question difficulty. This should be of immediate interest to everybody. The SAQs which had a pass rate of (for example) 0% in previous years (you know the ones I mean) were not the most difficult per se, they were just met with a group of trainees who were especially unprepared for this specific SAQ (it having never been seen before, and past papers being the favoured method or preparation). The question itself (eg. "list the key clinical signs of traumatic asphyxia") was not itself remarkable by the degree of knowledge or analysis it expected, but nobody knew the answer anyway. Theoretically, a group of trainees who all somehow expected a traumatic asphyxia question would have fallen into a normal distribution with the fat part somewhere around 5. The Angoff score is therefore a better metric, as it does not rely on the exam candidates level of preparation.
Anyway: a "discuss" answer will require some detail, for six marks:
1)
Assessment of suspected ventriculitis:
-
Risk factors:
-
Patient characteristics:
-
Intraventrciular blood
-
Systemic infection
-
Duration of catheterization (11 days seems to be the cutoff for increasing risk of infection)
-
Immune compromise
-
-
Features of surgery:
-
Craniotomy (vs burrhole)
-
Superficial surgical site infections
-
CSF leakage
-
-
Catheter management
-
EVD, rather than a parenchymal pressure transducer
-
Frequent sampling
-
EVD irrigation
-
Non-tunnelled vs. tunnelled EVD
-
-
-
Symptoms
-
Headache
-
Photophobia
-
Neck pain
-
-
Physical signs
- Unexplained decrease in the level of consciousness
- Fever
- Neck stiffness
- New cranial nerve signs
- Seizures
- Features of meningism (eg. Kernig and Brudzinski signs)
- Tenderness over the site of EVD insertion
-
Investigations
- Peripheral blood
- Increasing inflammatory markers
- Positive blood cultures
- CSF analysis
- Culture, Gram stain
- Cell count (WCC/RBC ratio of 1:106 or a rising trend)
- Nucleic acid amplification tests for specific pathogens
- β–D-glucan and galactomannan for fungal ventriculitis
- Imaging
- MRI with gadolinium could be helpful, or at least more helpful than CT
- Peripheral blood
Challenges of diagnosing ventriculitis:
- Definition of ventriculitis and diagnostic criteria are vague and not universally accepted
- Inflammatory change in CSF promotes sterile pleocytosis
- CSF cell count threshold is not agreed upon
- CSF cell count fluctuates dramatically even with sequential sampling
- Not all organisms will show up on a Gram stain
- History and examination are difficult in the unconscious patient
- Other causes of fever are common (eg. VAP, "central" fever)
Management of ventriculitis
- Source control:
- Remove the EVD if at all possible to survive without ICP monitoring and CSF drainage
- Replace the EVD with a sterile parenchymal monitor, if is still necessary to monitor the ICP but where CSF drainage is not essential
- If you absolutely need CSF drainage, perhaps remove the EVD and reinsert a new one after at least 48 hours of effective antibiotic therapy
- If you absolutely cannot remove the EVD, at least open it continuously, to let the infected CSF drain out.
- Systemic antibiotics
- Empiric treatment is with vancomycin and an anti-pseudomonal beta-lactam (such as cefepime, ceftazidime, or meropenem) - these are the IDSA-recommended agents
- Doses of these agents have to be adjusted to permit penetration into the CSF
- Intrathecal antibiotics for patients with treatment failure
References
Chavali, Siddharth, et al. "Fever in the neurointensive care unit." Journal of Neuroanaesthesiology and Critical Care 6.03 (2019): 275-283.
Laws, Craig, and Jack Jallo. "Fever and infection in the neurosurgical intensive care unit." JHN Journal 5.2 (2010): 5.
Goyal, Keshav, Neha Garg, and Parmod Bithal. "Central fever: a challenging clinical entity in neurocritical care." Journal of Neurocritical Care 13.1 (2020): 19-31.0
Ball, Perry A. "Fever in the Neurocritically Ill Patient." Acute Care Neurosurgery by Case Management: Pearls and Pitfalls. Cham: Springer International Publishing, 2022. 293-302.
Rabinstein, Alejandro A., and Kirsten Sandhu. "Non‐infectious fever in the neurological intensive care unit: incidence, causes and predictors." Journal of neurology, neurosurgery, and psychiatry 78.11 (2007): 1278.0
Commichau, Christopher, Nikolaos Scarmeas, and Stephan A. Mayer. "Risk factors for fever in the neurologic intensive care unit." Neurology 60.5 (2003): 837-841.
Wang, Zhuo, et al. "Clinical factors and incidence of prolonged fever in neurosurgical patients." Journal of Clinical Nursing 26.3-4 (2017): 411-417.
Migliorino, Ernesto, et al. "Neurogenic fever after subarachnoid hemorrhage in animal models: a systematic review." International journal of molecular sciences 24.14 (2023): 11514.
Lenski, Markus, et al. "Significance of cerebrospinal fluid inflammatory markers for diagnosing external ventricular drain–associated ventriculitis in patients with severe traumatic brain injury." Neurosurgical Focus 47.5 (2019): E150
Ramanan, Mahesh, Andrew Shorr, and Jeffrey Lipman. "Ventriculitis: infection or inflammation." Antibiotics 10.10 (2021): 1246.
Bådholm, Marcus, et al. "Cerebrospinal fluid cell count variability is a major confounding factor in external ventricular drain-associated infection surveillance diagnostics: a prospective observational study." Critical Care 25.1 (2021): 1-14.
Willer‐Hansen, Rasmus Stanley, et al. "Diagnostic criteria of CNS infection in patients with external ventricular drainage after traumatic brain injury: a pilot study." Acta Anaesthesiologica Scandinavica 66.4 (2022): 507-515.
Mayhall et al. "Ventriculostomy-related infections." New England Journal of Medicine 310.9 (1984): 553-559.
Brooks, Michael, et al. "Cerebrospinal fluid white cell count to red cell count ratio as a predictor of ventriculitis in patients with external ventricular drains." ANZ Journal of Surgery 92.12 (2022): 3278-3282.
Mehndiratta, Manmohan, et al. "Appraisal of Kernig's and Brudzinski's sign in meningitis." Annals of Indian Academy of Neurology 15.4 (2012): 287.
Savin, Ivan, et al. "Healthcare-associated ventriculitis and meningitis in a neuro-ICU: incidence and risk factors selected by machine learning approach." Journal of critical care 45 (2018): 95-104.
Kim, Joon-Hyung, et al. "Factors contributing to ventriculostomy infection." World neurosurgery 77.1 (2012): 135-140.
Dorresteijn, Kirsten RIS, et al. "Factors and measures predicting external CSF drain-associated ventriculitis: a review and meta-analysis." Neurology 93.22 (2019): 964-972.
Beer, R., et al. "Nosocomial ventriculitis and meningitis in neurocritical care patients." Journal of neurology 255 (2008): 1617-1624.
Tunkel, Allan R., et al. "2017 Infectious Diseases Society of America’s clinical practice guidelines for healthcare-associated ventriculitis and meningitis." Clinical Infectious Diseases 64.6 (2017): e34-e65.
Wen, Dennis Y., et al. "The Intraventricular Use of Antibiotic." Neurosurgery Clinics of North America 3.2 (1992): 343-354.
Llave, Nathaniel, et al. "Efficacy and Safety of Intraventricular Antibiotic Administration: A Review of the Literature." Infectious Diseases in Clinical Practice 29.6 (2021): e340-e346.
Naidech, Andrew M., et al. "Fever burden and functional recovery after subarachnoid hemorrhage." Neurosurgery 63.2 (2008): 212-218.
Mendieta Zerón, Hugo, and JULIO CESAR ARRIAGA GARCIA RENDON. "Remission of central fever with morphine post traumatic brain injury." (2014).
Korepu, Priyanka, Kamath Sriganesh, and Byrappa Vinay. "Hyperpyrexia following hemispherotomy and role of unconventional therapy." Journal of Neuroanaesthesiology and Critical Care 1.03 (2014): 210-211.
Lavinio, Andrea, et al. "Targeted temperature management in patients with intracerebral haemorrhage, subarachnoid haemorrhage, or acute ischaemic stroke: updated consensus guideline recommendations by the Neuroprotective Therapy Consensus Review (NTCR) group." British Journal of Anaesthesia (2023).
Question 4 - 2024, Paper 1
With respect to non-convulsive status epilepticus (NCSE):
a) Outline the challenges in the diagnosis of NCSE. (2.5 marks)
b) List five risk factors for NCSE. (2.5 marks)
c) Outline the principles of management for patients with suspected NCSE. (5 marks)
College answer
Syllabus topic/section: 2.1.8 Neurological Intensive Care / Seizure disorders including status epilepticus: L1
Discussion: NCSE is a distinct clinical entity from status epilepticus. Candidates who acknowledged those nuances and addressed this in their answer were able to demonstrate the standard required. Candidates can ensure they cover breadth by considering the types of information used clinically when securing a diagnosis as history, examination and investigations all contribute to diagnostic reasoning. Answers with structure, (for example, in part a) using headings which could include practical, logistical and clinical challenges among others) were rewarded.
Better answers to part C addressed control of seizures, prevention of secondary injury, finding and treating precipitants and involved a strategy for de-escalation. Outline is a glossary term that is defined as ‘provide a summary of the important points’ which is more than a simple list. For parts A and B, the question asked for an outline and accordingly higher marks were awarded for structured, details answers. As an illustration, general comments about the importance of maintenance of MAP/normoxia/normoglycaemia did not gain marks unless they were contextualised as neuroprotective cares for the patient with NCSE.
It is expected that just listing anti-epileptics is not enough to demonstrate the standard of competence required at the level of a transitional fellow who will be entrusted with independent practice of the critically ill. More detail in terms of dosing considerations, an approach to drug interactions and ways to mitigate unintended consequences is needed.
Discussion
Challenges:
- Distinguishable from convulsive SE by not involving motor cortex neurons, but also may be distinct in other ways, eg. potentially not a distinct disease process but rather a marker of severity of CNS dysfunction
- No clinical findings
- No agreement on the diagnostic criteria by which to identify this condition.
- What criteria we have are based on EEG, but EEG may not capture the epileptiform discharges if it is only performed during an interictal period
- Even when EEG is available, EEG findings are frequently non-specific which should also be interpreted as features of encephalopathy
Risk factors:
- Known epileptic with an acute infection
- Recent convulsive seizures
- Remote risk factors for seizures:
- previous stroke
- tumour
- neurosurgery
- dementia
- multiple sclerosis
- encephalitis or meningitis
Principles of management
- Treatment of the underlying precipitant is essential
- Controversy exists as to whether one should offer any treatment at all to the NSCE itself
- It is unclear whether it causes neurological damage (animal data, mostly)
- Guidelines are mostly extrapolated from convulsive SE, which means they may be too aggressive
- Management should be reserved for patients in whom the added benefit of management has clear advantages (eg. decreased CNS oxyegnc consumption in TBI)
- Prognosis is mostly determined by the prognosis of the underlying disease; management of patients with lower severity of underlying disease should therefore be more conservative
- For pharmacotherapy, benzodiazepines are first line
- Valproate, levitiracteam and lacosamide are second line
- Seek to reduce threshold-lowering stimuli (eg. hyponatremia)
- Antiepileptic therapy must be guided by serial or continuous EEG, as clinical features are subtle and difficult to track
References
Oh's Intensive Care manual: Chapter 42 (pp. 487) Acute gastrointestinal bleeding by Joseph JY Sung
Gibson, Joanna A., and Robert D. Odze. "Pathology of diseases that cause upper gastrointestinal tract bleeding." Gastrointestinal Endoscopy Clinics 21.4 (2011): 583-596.
Baxter, M., and E. H. Aly. "Dieulafoy's lesion: current trends in diagnosis and management." The Annals of The Royal College of Surgeons of England 92.7 (2010): 548-554.
arcia-Tsao, Guadalupe, and Jaime Bosch. "Management of varices and variceal hemorrhage in cirrhosis." New England Journal of Medicine 362.9 (2010): 823-832.
Laursen, Stig Borbjerg, Jane Møller Hansen, and Ove B. Schaffalitzky De Muckadell. "The Glasgow Blatchford score is the most accurate assessment of patients with upper gastrointestinal hemorrhage." Clinical Gastroenterology and Hepatology 10.10 (2012): 1130-1135.
Hyett, Brian H., et al. "The AIMS65 score compared with the Glasgow-Blatchford score in predicting outcomes in upper GI bleeding." Gastrointestinal endoscopy 77.4 (2013): 551-557.
García-Pagán, Juan Carlos, et al. "Early use of TIPS in patients with cirrhosis and variceal bleeding." New England Journal of Medicine 362.25 (2010): 2370-2379.
Vlavianos, P., et al. "Balloon tamponade in variceal bleeding: use and misuse."BMJ: British Medical Journal 298.6681 (1989): 1158.
Reverter, Enric, and Juan Carlos García‐Pagán. "Management of an acute variceal bleeding episode." Clinical Liver Disease 1.5 (2012): 151-154.
Ioannou, G. N., J. Doust, and D. C. Rockey. "Terlipressin in acute oesophageal variceal haemorrhage." Alimentary pharmacology & therapeutics 17.1 (2003): 53-64.
Corley, Douglas A., et al. "Octreotide for acute esophageal variceal bleeding: a meta-analysis." Gastroenterology 120.4 (2001): 946-954.
Reiberger, Thomas, et al. "Carvedilol for primary prophylaxis of variceal bleeding in cirrhotic patients with haemodynamic non-response to propranolol." Gut62.11 (2013): 1634-1641.
Hou, Ming‐Chih, et al. "Antibiotic prophylaxis after endoscopic therapy prevents rebleeding in acute variceal hemorrhage: a randomized trial." Hepatology 39.3 (2004): 746-753.
Augustin, Salvador, Antonio González, and Joan Genescà. "Acute esophageal variceal bleeding: Current strategies and new perspectives." World J Hepatol 2.7 (2010): 261-274.
Chen, Ping-Hsien, et al. "Delayed endoscopy increases re-bleeding and mortality in patients with hematemesis and active esophageal variceal bleeding: a cohort study." Journal of hepatology 57.6 (2012): 1207-1213.
Kleber, Gerhard, et al. "Prediction of variceal hemorrhage in cirrhosis: a prospective follow-up study." Gastroenterology 100.5 (1991): 1332-1337.
Xu, Liang, et al. "Risk factors for predicting early variceal rebleeding after endoscopic variceal ligation." World journal of gastroenterology: WJG 17.28 (2011): 3347.
Tavakoli, Nader, et al. "Comparison of the efficacy of intravenous tranexamic acid with and without topical administration versus placebo in urgent endoscopy rate for acute gastrointestinal bleeding: A double-blind randomized controlled trial." United European Gastroenterology Journal (2017): 2050640617714940.
Barer, David, et al. "Cimetidine and tranexamic acid in the treatment of acute upper-gastrointestinal-tract bleeding." New England Journal of Medicine308.26 (1983): 1571-1575.
Brooks, W. Scott. "Use of Sucralfate in Variceal Sclerotherapy-Induced Ulcerations." Sucralfate (1995): 323-331.
Haruta, Ikuko, et al. "Balloon-occluded retrograde transvenous obliteration (BRTO), a promising nonsurgical therapy for ectopic varices: a case report of successful treatment of duodenal varices by BRTO." American Journal of Gastroenterology 91.12 (1996).
Park, Jonathan K., et al. "Balloon-occluded retrograde transvenous obliteration (BRTO) for treatment of gastric varices: review and meta-analysis." Digestive diseases and sciences 60.6 (2015): 1543.
Bosch, Jaime, et al. "Recombinant factor VIIa for variceal bleeding in patients with advanced cirrhosis: a randomized, controlled trial." Hepatology 47.5 (2008): 1604-1614.
Koch, Erica, et al. "Shock index in the emergency department: utility and limitations." Open Access Emergency Medicine (2019): 179-199.
Haffey, S., A. McKernan, and K. Pang. "Non-convulsive status epilepticus: a profile of patients diagnosed within a tertiary referral centre." Journal of Neurology, Neurosurgery & Psychiatry 75.7 (2004): 1043-1044.
Jirsch, J., and L. J. Hirsch. "Nonconvulsive seizures: developing a rational approach to the diagnosis and management in the critically ill population."Clinical neurophysiology 118.8 (2007): 1660-1670.
Rupprecht, Sven, et al. "Levetiracetam as a treatment option in non-convulsive status epilepticus." Epilepsy research 73.3 (2007): 238-244.
Misirocchi, Francesco, et al. "Prognostic value of Salzburg nonconvulsive status epilepticus criteria: The SACE score." Epilepsia 65.1 (2024): 138-147.
Shin, Jung-Won. "Management strategies for refractory status epilepticus." Journal of Neurocritical Care 16.2 (2023): 59-68.
Question 28 - 2024, Paper 1
Discuss your approach to prognostication of neurological outcome in adult ICU patients after successful cardiovascular resuscitation following out of hospital cardiac arrest. Your answer should include the following headings:
a) Guidelines. (2 marks)
b) General approach and clinical factors. (3 marks)
c) Investigations, and their role in prognostication. (5 marks)
College answer
Syllabus topic/section:
2.1.8 Neurological Intensive Care / Hypoxic Ischaemic Encephalopathy: L1
Discussion:
Candidates demonstrated the standard required if they addressed their answer as per the 3 parts of the question, showed a clearly thought-out process of neuroprognostication and acknowledged a multi-modal approach with repeated examination and appropriate timing.
Candidates who were not familiar with any guidelines or able to reference them and/or were unclear regarding clinical features, relevant investigations and timing of neuroprognostication indicators did not demonstrate the standard required and marks were allocated accordingly.
|
Below standard |
At standard |
Above standard |
|
|
Guidelines |
Specific mention of >=1 relevant guideline (NCCS, ILCOR or ESICM), but not linked to rest of the answer |
Specific reference to >=1 relevant guideline, including how it informs the answer |
As per standard AND some critical discussion |
|
(2 marks) |
0-0.5 marks |
1.0 mark |
1.5-2.0 marks |
|
General approach and clinical factors |
Poorly structured with minimal discussion about general approach; omits timing of assessment; or does not acknowledge prognostic uncertainty |
Appropriate structure. Includes timing, AND integration of multiple parameters OR Favourable + Poor indicators |
Includes Timing AND Integration of multiple parameters AND favourable + poor indicators AND Prognostic uncertainty / Values-based care |
|
(3 marks) |
0-1.0 marks |
1.5-2.0 marks |
2.5-3.0 marks |
|
Investigations and role in prognostication |
Incomplete list of basic investigations (CT, MRI, electrophysiology [EEG and/or N20], and laboratory investigations) or minimal description of basic interpretation of chosen investigations |
Complete list as per below standard and description of key prognostic features of each investigation |
As per standard with detailed description including timing, reliability and controversies |
|
(5 marks) |
0-2.0 marks |
2.5-3.5 marks |
4.0-5.0 marks |
Discussion
a) Guidelines:
- The main guidelines are the 2023 NCS guidelines and the 2021 ESICM/ERC guidelines.
- Both guidelines agree on a multimodal approach to prognostication
- ESICM: poor prognosis if < M3 motor score at >72hrs post ROSC, plus any two or more of the factors they list.
- NCCS: offer a list of reliable and unreliable markers
b)
General approach:
- Multimodal assessment: use several techniques concurrently to help form an opinion
- Timing: not before 24 hours; ideally at 72-120 hours
- Clinical features are especially susceptible to time context, i.e. need to exclude the effects of sedation and hypothermia
Clinical features associated with a poor outcome:
- History:
- Initial rhythm (PEA or asystole)
- unwitnessed
- delayed CPR
- CPR for longer than 20 minutes
- Examination:
- Unreactive pupils
- Absent corneal reflex
- Status myoclonus
- GCS motor score < 3
- High false positive rate with clinical examination alone
- Confounded by sedation and cooling
c)
- Imaging findings associated with a poor outcome:
- CT: loss of grey-white differentiation (inversed gray/white matter ratio in Hounsfield units)
- Early (<24hr) CT may fail to demonstrate these findings; poor negative predictive value (i.e. a normal CT does not rule out a bad outcome)
- MRI: early increased signal intensity on DWI and diffusion restriction on ADC
- Good positive and negative predictive value at days 2-7
- CT: loss of grey-white differentiation (inversed gray/white matter ratio in Hounsfield units)
- Neurophysiological studies associated with a poor outcome:
- EEG: Absence of reactivity, burst suppression, suppressed background, or status epilepticus within the first 72 hrs
- False positive rate 0-7%
- SSEP: absence of the N20 component with median nerve stimulation
- Very low false positive rate (close to 0%) even in cooled patients
- EEG: Absence of reactivity, burst suppression, suppressed background, or status epilepticus within the first 72 hrs
- Biomarkers associated with a poor outcome:
- NSE over 33μg/L at 1-3 days post CPR
- No uniformly accepted threshold
- S100 calcium-binding protein B
- Remains largely experimental
- NSE over 33μg/L at 1-3 days post CPR
References
Engdahl, Johan, et al. "Can we define patients with no and those with some chance of survival when found in asystole out of hospital?." The American journal of cardiology 86.6 (2000): 610-614.
Bunch, T. Jared, et al. "Outcomes and in-hospital treatment of out-of-hospital cardiac arrest patients resuscitated from ventricular fibrillation by early defibrillation." Mayo Clinic Proceedings. Vol. 79. No. 5. Elsevier, 2004.
Levine, Robert L., Marvin A. Wayne, and Charles C. Miller. "End-tidal carbon dioxide and outcome of out-of-hospital cardiac arrest." New England Journal of Medicine 337.5 (1997): 301-306.
Rea, Thomas D., et al. "Temporal Trends in Sudden Cardiac Arrest A 25-Year Emergency Medical Services Perspective." Circulation 107.22 (2003): 2780-2785.
Carew, Heather T., Weiya Zhang, and Thomas D. Rea. "Chronic health conditions and survival after out-of-hospital ventricular fibrillation cardiac arrest." Heart 93.6 (2007): 728-731.
Goldberger, Zachary D., et al. "Duration of resuscitation efforts and survival after in-hospital cardiac arrest: an observational study." The Lancet (2012).
Wijdicks, E. F. M., et al. "Practice Parameter: Prediction of outcome in comatose survivors after cardiopulmonary resuscitation (an evidence-based review) Report of the Quality Standards Subcommittee of the American Academy of Neurology."Neurology 67.2 (2006): 203-210.
Rogove, Herbert J., et al. "Old age does not negate good cerebral outcome after cardiopulmonary resuscitation: analyses from the brain resuscitation clinical trials."Critical care medicine 23.1 (1995): 18-25.
LEVY, DE, et al. "Predicting Outcome from Hypoxic-Ischemic Coma." Survey of Anesthesiology 30.2 (1986): 93.
Sandroni, Claudio, et al. "Prognostication in comatose survivors of cardiac arrest: an advisory statement from the European Resuscitation Council and the European Society of Intensive Care Medicine." Resuscitation 85.12 (2014): 1779-1789.
Greer, David M., et al. "Clinical examination for prognostication in comatose cardiac arrest patients." Resuscitation 84.11 (2013): 1546-1551.
Lee, Ha Lim, and Ju Kang Lee. "Lance-adams syndrome." Annals of rehabilitation medicine 35.6 (2011): 939-943.
Bouwes, Aline, et al. "Acute posthypoxic myoclonus after cardiopulmonary resuscitation." BMC neurology 12.1 (2012): 63.
Stammet, Pascal, et al. "Neuron-specific enolase as a predictor of death or poor neurological outcome after out-of-hospital cardiac arrest and targeted temperature management at 33 C and 36 C." Journal of the American College of Cardiology 65.19 (2015): 2104-2114.
Golan, Eyal, et al. "Predicting Neurologic Outcome After Targeted Temperature Management for Cardiac Arrest: Systematic Review and Meta-Analysis*." Critical care medicine 42.8 (2014): 1919-1930.
Howes, Daniel, et al. "Canadian Guidelines for the use of targeted temperature management (therapeutic hypothermia) after cardiac arrest: A joint statement from The Canadian Critical Care Society (CCCS), Canadian Neurocritical Care Society (CNCCS), and the Canadian Critical Care Trials Group (CCCTG)." Resuscitation 98 (2016): 48-63.
Sandroni, Claudio, Sonia D’Arrigo, and Jerry P. Nolan. "Prognostication after cardiac arrest." Critical care 22.1 (2018): 1-9.
Nolan, Jerry P., et al. "European resuscitation council and european society of intensive care medicine guidelines 2021: post-resuscitation care." Resuscitation 161 (2021): 220-269.
Cronberg, Tobias, et al. "Brain injury after cardiac arrest: from prognostication of comatose patients to rehabilitation." The Lancet Neurology 19.7 (2020): 611-622.
Kim, Youn-Jung, et al. "Long-term neurological outcomes in patients after out-of-hospital cardiac arrest." Resuscitation 101 (2016): 1-5.
Scarpino, Maenia, et al. "Neurophysiology and neuroimaging accurately predict poor neurological outcome within 24 hours after cardiac arrest: the ProNeCA prospective multicentre prognostication study." Resuscitation 143 (2019): 115-123.
Dyson, Kylie, et al. "International variation in survival after out-of-hospital cardiac arrest: a validation study of the Utstein template." Resuscitation 138 (2019): 168-181.
Dragancea, Irina, et al. "The influence of induced hypothermia and delayed prognostication on the mode of death after cardiac arrest." Resuscitation 84.3 (2013): 337-342.
Hofmeijer, Jeannette, et al. "Unstandardized treatment of electroencephalographic status epilepticus does not improve outcome of comatose patients after cardiac arrest." Frontiers in neurology 5 (2014): 39.
Bertoni, M., et al. "Neuroimaging assessment of hypoxic ischemic brain injury of the adult with perfusion computed tomography." Journal of the Neurological Sciences 381 (2017): 71-72.
Huang, Benjamin Y., and Mauricio Castillo. "Hypoxic-ischemic brain injury: imaging findings from birth to adulthood." Radiographics 28.2 (2008): 417-439.
Gutierrez, Leonardo Guilhermino, et al. "CT and MR in non-neonatal hypoxic–ischemic encephalopathy: radiological findings with pathophysiological correlations." Neuroradiology 52 (2010): 949-976.
Parada-Duarte, Óscar Andrés, et al. "Cortical Laminar Necrosis in Computed Tomography Scan: A Case Report." Rev. Colomb. Radiol. 2019; 30(4): 5239-41
Muttikkal, Thomas J. Eluvathingal, and Max Wintermark. "MRI patterns of global hypoxic-ischemic injury in adults." Journal of Neuroradiology 40.3 (2013): 164-171.
Han, B. Kim, et al. "Reversal sign on CT: effect of anoxic/ischemic cerebral injury in children." AJR. American journal of roentgenology 154.2 (1990): 361-368.
Krishnan, Prasad, and Siddhartha Roy Chowdhury. "“White cerebellum” sign-A dark prognosticator." Journal of Neurosciences in Rural Practice 5.04 (2014): 433-433.
Chakraborty, Santanu, et al. "Diffuse ischemia in noncontrast computed tomography predicts outcome in patients in intensive care unit." Canadian Association of Radiologists Journal 63.2 (2012): 129-134.
Torbey, Michel T., et al. "Quantitative analysis of the loss of distinction between gray and white matter in comatose patients after cardiac arrest." Stroke 31.9 (2000): 2163-2167.
Scheel, Michael, et al. "The prognostic value of gray-white-matter ratio in cardiac arrest patients treated with hypothermia." Scandinavian journal of trauma, resuscitation and emergency medicine 21 (2013): 1-7.
Lang, Margareta, et al. "A Pilot Study of Methods for Assessment of Hypoxic-Ischaemic Encephalopathy on Head Computed Tomography after Cardiac Arrest."
Yuzawa, Hironao, et al. "Pseudo-subarachnoid hemorrhage found in patients with postresuscitation encephalopathy: characteristics of CT findings and clinical importance." American journal of neuroradiology 29.8 (2008): 1544-1549.
Maurya, V. K., et al. "Hypoxic–ischemic brain injury in an adult: magnetic resonance imaging findings." Medical Journal, Armed Forces India 72.1 (2016): 75.
Question 5 - 2024, Paper 2
A 34-year-old patient presents to the emergency department with a suspected recreational drug overdose and is intubated for a low Glasgow Coma Scale (GCS). There is no past medical history of note. On day 3, the patient is de-sedated, extubated, and subsequently assaults the bedside nurse.
The patient is re-sedated and re-intubated.
Discuss your management plan for de-sedating and extubating this patient.
College answer
Syllabus topic/section:
2.1.8 Neurological Intensive Care: Acute behavioural disturbances: L1
2.1.19 Intensive care Procedures: Intubation
Discussion:
This was a very practical question asking for an approach to a relatively common ICU problem. Candidates that did not provide a structure to their answer frequently missed important elements that would normally be considered when extubating a patient with a history of aggression and safety risks to self and staff. Candidates that did well in this question considered the potential reasons for his post-extubation aggressive behaviour, including organic, psychiatric and toxidrome factors, addressed the logistical issues when considering a second extubation, understood the importance of staff and patient safety and had a back-up plan in case it failed.
Both pharmacological and non-pharmacological strategies when extubating the patient should be considered. For an above standard answer, it was important to include some details about the different pharmacological options that might be used. Please see the below rubric for examples of the elements required. Please note that this is not the only structure/ headings possible. Many differently structed answers with equal content gained the same marks.
The marking rubric is included to aid the candidate’s future study.
|
Below standard |
At standard |
Above standard |
|
|
Considers underlying reasons for aggression in previous extubation (2 marks) |
Fails to consider reasons for failed extubation Doesn’t consider staff or patient safety Lack of a back-up plan if fails extubation 0-0.5 marks |
Considers some potential underlying reasons for behaviour 1-1.5 marks |
At standard plus Considers a broad range of underlying reasons including medical/ psychiatric & toxidrome 2 marks |
|
Staff Safety (3 marks) |
None or inaccurate consideration. 0-1 marks |
Partial consideration to items listed in the column on above standard 1.5-2marks |
Considers the points listed below Considers logistics
2.5-3.0 marks |
|
Patient safety and plan for smooth emergence (3 marks) |
None or inaccurate Considerations 0-1 marks |
Consideration of some pharmacological and non- pharmacological techniques 1.5-2marks |
Considers non- pharmacological and pharmacological techniques for smooth emergence Considers contacting specialty services for advice where applicable. 2.5-3.0 marks |
|
Team Plan (2 marks) |
None or inaccurate considerations 0-1 marks |
Mention made of a backup plan but no mention of team preparedness. 1 mark |
Team communication of detailed backup plan for aggressive emergence 1.5-2 marks |
Discussion
The rubric is enlightening because the structure is generic for the management of basically any situation where the patient and the staff have interacted in some way that led to the detriment of both (i.e. these can be generalised to questions about needle stick injury, open disclosure, complaint resolution, and so on). The last time this happened, it was in Question 27 from the first paper of 2018, where the college focused on managing the misbehaviour, with a strong focus on pharmacological options. This time prevention seems to be the focus. An effective strategy for candidates to adopt appears to be a structure that resembles the management of delirium:
- Debrief
- Assess the events of the last extubation, specifically how the sedation wean was managed
- Assess the specific proximal cause for the escalation
- Assess the risk of future escalation on the basis of the patients background and risk profile
- Re-consult toxicology and review the medical history to exclude untreated toxicity or drug withdrawal
- Councel staff, ensure appropriate leave, encourage the submission of an incident report
- Prepare the patient
- Sedation while weaning anaesthetic agents:
- Dexmedetomidine (data extrapolated from delirium literature)
- Antipsychotics (choice is determined by side effect profile)
- Benzodiazepines (favoured in drug and alcohol withdrawal states)
- Opioids (where opioid dependence or untreated pain may be contributing)
- Consider the need for physical restraints
- Sedation while weaning anaesthetic agents:
- Prepare the environment
- Unbstructed exits
- Loose items or dangerous equipment (needles, scissors) are tidied away
- Quiet (silence monitors, ventilator) - patients with sensory sensitivity may be
- Prepare the staffing
- Wait for daytime, ideally some period of handover or shift overlap where there are a large number of staff available
- Add staff: security officers +/- mental health nursing staff +/- multiple ICU nurses
- Organise the presence of a family member who is known to have a claiming influence
- Prepare any medications to be used in case of a re-escalation of behaviour
- Extubate in a controlled fashion
- Commence dexmedetomidine
- Add an antipsychotic agent with antihistamine activity (eg. olanzapine) or a benzodiazepine/opioid if there is concern regarding withrawal
- Cease other sedation and extubate the patient with dexmedetomidine as a solo anaesthetic agent - supported by the DahLIA study (Reade et al, 2016)
- Wean the dexmedetomidine gradually to allow awakening without tube-associated agitation
References
Drury, Thomas. "Recognizing the potential for violence in the ICU." Dimensions of Critical Care Nursing 16.6 (1997): 314-327.
Kynoch, Kate, Chiung‐Jung Wu, and Anne M. Chang. "Interventions for preventing and managing aggressive patients admitted to an acute hospital setting: a systematic review." Worldviews on Evidence‐Based Nursing 8.2 (2011): 76-86.
Reade, Michael C., et al. "Effect of dexmedetomidine added to standard care on ventilator-free time in patients with agitated delirium: a randomized clinical trial." Jama 315.14 (2016): 1460-1468.
Question 6.1 - 2024, Paper 2
A 69-year-old patient was intubated and ventilated for a reduced level of consciousness, with a 4-day
history of neurological deterioration. Lumbar puncture was performed.
Cerebrospinal fluid (CSF) analysis revealed
|
Parameter |
Patient |
Reference |
|
Polymorphonuclear cells |
0 x 106/L |
Range: 0 cells |
|
Mononuclear cells |
3 x 10⁶/L |
Range: 0-5 cells |
|
Red blood cells |
1640 x 106/L* |
10-20 |
|
No bacteria seen. Blood stained. |
||
|
Protein Level CSF |
7.35 g/L* |
0.15-0.45 |
i) List TWO causes for the raised CSF red blood cells in this patient. (2 marks)
ii) List FOUR likely causes for the raised CSF protein level in this patient. (2 marks)
College answer
Syllabus topic/section:
2.1.8 Neurological Intensive Care: Interpretation of cerebrospinal fluid: L1
Discussion:
Part a) was a straightforward question with most candidates successfully listing the causes of high protein and red blood cells within CSF
Discussion
The extremely high Angoff mark suggests that "the borderline candidate" should be know this very well, and the author (having an extensive history of being a borderline candidate) confirms that this would indeed have been the case during his written attempts, as the CSF questions are frequent in the past papers and everyone is expected to have done those to the point of sullen tedium.
Causes of proteorrhachia include:
- Raised protein because contaminated with blood (blood LP or EVD in ICH)
- Ischaemic stroke
- Infection: menigitis/encephalitis, which for this patient would have to be viral (as the CSF is minimally cellular)
- Neoplasm (eg. Froins syndrome, except the protein is probably not high enough, as Froin syndrome can make is supra-systemic)
- Alcoholism
- Congenital hydrocephalus
- Idiopathic causes, eg. diabetic neuropathy, seizures,
- Autoimmune encephalitis, CNS vasculitis, demyelinating infllamatiry disease (eg. GBS, MS, ALS)
- Head injury
- Myxoedema
References
Venkatesh, B., P. Scott, and M. Ziegenfuss. "Cerebrospinal fluid in critical illness." Critical care and resuscitation 2 (2000): 42-54.
SCHAIN, RICHARD J. "Cerebrospinal fluid and serum cation levels." Archives of Neurology 11.3 (1964): 330.
POSNER, JEROME B., AUGUST G. SWANSON, and FRED PLUM. "Acid-base balance in cerebrospinal fluid." Archives of neurology 12.5 (1965): 479.
Brown, P. D., et al. "Molecular mechanisms of cerebrospinal fluid production."Neuroscience 129.4 (2004): 955-968.
Steele, Russell W., et al. "Leukocyte survival in cerebrospinal fluid." Journal of clinical microbiology 23.5 (1986): 965-966.
Beer, R., P. Lackner, and B. Pfausler. "Nosocomial ventriculitis and meningitis in neurocritical care patients." Journal of neurology 255.11 (2008): 1617-1624.
Zaret, Deborah L., et al. "Immunofixation to quantify beta 2-transferrin in cerebrospinal fluid to detect leakage of cerebrospinal fluid from skull injury."Clinical chemistry 38.9 (1992): 1908-1912.
Swedenborg, E. "The Brain." Considered Anatomically, Physiologically and Phylosopically.(translated and edited by RL Tafel), London (1887).
Hajdu, Steven I. "Discovery of the cerebrospinal fluid." Annals of Clinical & Laboratory Science 33.3 (2003): 334-336.
Question 24 - 2024, Paper 2
A 53-year-old patient is admitted to the intensive care unit following an uneventful emergency clipping of a right middle cerebral artery aneurysm. They are extubated the following morning with normal neurology. Six hours after extubation the urine output suddenly increases to over 400ml per hour.
a) List FOUR likely diagnoses. (2 marks)
b) Outline your immediate assessment. (4 marks)
c) Outline the management plan for the patient's polyuria. (4 marks)
College answer
Syllabus topic/section:
2.1.8 Neurological intensive care: Subarachnoid haemorrhage: L1
Discussion:
Candidates who attended to all components of this question performed well. Addressing immediate assessment requires history, examination and investigations to be addressed. As assessment intends to define the diagnosis, better answers were informed by the list of likely diagnoses in part A. A comprehensive answer to a management question addresses resuscitation, definitive as well as supportive therapy and monitoring. Better answers addressed each of these.
Discussion
a)
The potential causes of polyuria post SAH include:
- Normal response to fluid loading (perhaps somebody still does HHH therapy?)
- Hypertensive diuresis (quite likely, as the now-awake patient probably has strict blood pressure targets defined by an arterial transducer zeroed at the Circle of Willis)
- Central diabetes insipidus
- Cerebral salt wasting
- Mannitol diuresis (though it is quite late for that, considering it is usually immediate following administration)
b)
History:
- Procedural records of fluid and osmotherapy administration
- Blood pressure control recently in ICU
- Drug history (eg. lithium?)
Examination:
- Volume status
- New neuro findings (eg. bitemporal hemianopia)
Investigations:
- Urinary sodium and osmolality (CSW vs DI)
- CTB (extent of SAH), MRI (pituitary infarction or oedema)
c) Management
Options include:
- Conservative management
- Observe urine output for several hours
- Observe volume status and serum sodium
- React to changes in levels if they cross thresholds (eg. sodium over 150 mmol/L)
- Control for possible causes
- Address hypertension, fluid excess, etc
- Renegotiate BP targets with neurosurgeons
- Restore volume
- If hypovolemia develops, replace lost volume
- Avoid replacing it prospectively (as this begets firther diuresis)
- If a diagnosis of DI is made on biochemistry and history,
- DDAVP 0.5 mcg regularly
- Continue measuring sodium regularly (eg. q4h)
- Watch for hyponatremia (also a common consequence of SAH)
References
Tisdall, Martin, et al. "Disturbances of sodium in critically ill adult neurologic patients: a clinical review." Journal of neurosurgical anesthesiology 18.1 (2006): 57.
John, Cynthia Cindi A., and Michael W. Day. "Central neurogenic diabetes insipidus, syndrome of inappropriate secretion of antidiuretic hormone, and cerebral salt-wasting syndrome in traumatic brain injury." Critical care nurse32.2 (2012): e1-e7.
Roman, R. J. "Pressure diuresis mechanism in the control of renal function and arterial pressure."
Federation proceedings. Vol. 45. No. 13. 1986.
Granger, J. P. "Pressure natriuresis. Role of renal interstitial hydrostatic pressure." Hypertension 19.1 Suppl (1992): I9.
Kunau, R. T., and NORBERT H. Lameire. "The effect of an acute increase in renal perfusion pressure on sodium transport in the rat kidney." Circulation research 39.5 (1976): 689-695.
Fenske, Wiebke, and Bruno Allolio. "Current state and future perspectives in the diagnosis of diabetes insipidus: a clinical review." The Journal of Clinical Endocrinology & Metabolism 97.10 (2012): 3426-3437.
Guerrero, R., et al. "Early hyponatraemia after pituitary surgery: cerebral salt-wasting syndrome." European journal of endocrinology 156.6 (2007): 611-616.
Hensen, Johannes, et al. "Prevalence, predictors and patterns of postoperative polyuria and hyponatraemia in the immediate course after transsphenoidal surgery for pituitary adenomas." Clinical endocrinology 50.4 (1999): 431-439.
Question 7 - 2025, Paper 1
Briefly outline the clinical examination features of the following:
a) Basal ganglia infarct (3 marks)
b) High (C5) spinal cord injury (4 marks)
c) Critical illness myopathy (3 marks)
College comments
Syllabus topic/section: 2.1.8 Neurological Intensive Care
Discussion:
Candidates who performed well in this section demonstrated a clear and structured answer, with knowledge of the neurological examination and specific deficits that were related back to the anatomical location of the lesion.
Answers that scored less well were vague and lacked structure. The marking Examiners commented that having a clearer structure and including all elements of the neurological exam in a logical sequence (eg motor: tone/power/reflexes, the various sensory examination components, autonomic features) would have led to more comprehensive and better scoring answers.
Interpretation
The comments sound like the examiners wanted the findings presented in a certain way; or rather, that candidates who presented their answer laid out in logical manner scored higher. This may be partly die to the fact that it is easier to mark a logically presented answer, and partly because a logical structure prevents you from forgetting various details. In this scenario, the question is asking about neurological findings, so the usual power/tone/reflexes/sensation structure is probably the most effective:
Basal ganglia stroke
- Power: contralateral weakness (including face)
- Tone: Contralateral upper motor neuron signs, increased tone and clonus
(initially, flaccid) - Reflexes: contralateral hyperreflexia
- Sensation: contralateral loss of sensation (including face)
- Autonomic function: usually preserved
-
Subtypes exist:
- A pure motor variant (internal capsule and pons only)
- A pure sensory variant (thalamus and corona radiata)
- Ataxic hemiparesis (thalamus and internal capsule)
C5 spinal cord injury:
- Power: quadriparesis; shoulder shrug and elbow flexion is preserved
- Tone: Flaccid initially (spinal shock), later spasticity and contractures
- Reflexes: areflexic initiallyu, later hyperreflexic
- Sensation: bilateral loss of sensation below the root of the neck
- Autonomic function: autonomic dysreflexia, neurogenic bladder and bowel
Critical illness myopathy
- Power: proximal muscle weakness
- Tone: decreased, flaccid
- Reflexes: would be normal if the muscles were not so weak
- Sensation: preserved
- Autonomic function: preserved
References
Eliacik, Sinan. "LACUNAR STROKE AND AUTONOMIC DYSFUNCTION." ASEAN Journal of Psychiatry 25.5 (2024).
KO, Myoung-Hwan, Yun-Hee KIM, and Jeong-Hwan SEO. "Clinical and neuropsychological characteristics of patients with stroke of the basal ganglia." Journal of the Korean Academy of Rehabilitation Medicine (1997): 652-657.
Wagner, Robert, and Andy Jagoda. "Spinal cord syndromes." Emergency medicine clinics of North America 15.3 (1997): 699-711.
Hermans, Greet, and Greet Van den Berghe. "Clinical review: intensive care unit acquired weakness." Critical care 19.1 (2015): 274.
Stevens, Robert D., et al. "A framework for diagnosing and classifying intensive care unit-acquired weakness." Critical care medicine 37.10 (2009): S299-S308.
Question 16 - 2025, Paper 1
With respect to posterior reversible encephalopathy syndrome (PRES):
a) List four risk factors (2 marks)
b) Outline the clinical features and radiological findings on presentation (4 marks)
c) Outline the management principles of PRES (4 marks)
College comments
Syllabus topic/section: 2.1.8 Neurological Intensive Care: Posterior reversible encephalopathy syndrome
Discussion:
Part a) required a recall of facts with good candidates able to provide 4 differentials from a broad range of conditions to ensure they scored the full 2 marks. Candidates that gave 2 answers from similar categories (eg SLE and scleroderma or preeclampsia and eclampsia) scored less marks as these counted as 1 risk factor due to their overlapping nature.
Part b) required both the clinical features and radiological findings of PRES. Most candidates were able to provide the clinical features in reasonable detail but many struggled to discuss the specific radiological findings. Candidates that did well understood the limitations of CT and were able to discuss the typical patterns of PRES on imaging and the more specific nature of MRI in this condition.
Part c) asked for the management principles of PRES. A number of candidates wasted time on general resuscitation measures and generic management with a FASTHUG approach that didn’t score marks as the question asked for management principles. Candidates that scored well included management of the underlying cause, addressed control of the hypertension with safe endpoints and appropriate agents and mentioned management of potential complications (eg seizures/raised ICP).
Interpretation
This question is almost identical in content, if not in style, to Question 10 from the second paper of 2018. Depressingly, the pass rate was 79.1% in 2018, but only 42.9% in 2025.
a) Four risk factors
- Organ transplant (solid or bone marrow)
- Immunosuppressant therapy, especially cyclosporine and tacrolimus
- Pregnancy (particularly, pre-eclampsia)
- Autoimmune disease, particularly scleroderma, SLE, polyarteritis nodosa and Wegener's granulomatosis
- Sepsis and septic shock, specially when associated with MOSF
- Chronic kidney diseases
- Porphyria
- Tumour lysis syndrome
- Sympathomimetic overdose
b)
Clinical features:
- Altered level of consciousness, ranging from confusion to coma
- Headache
- Seizures
- Visual symptoms (usually, blindness or hemianopia)
- Neuroradiology findings
- Exclusion of other pathology (eg. encephalitis or stroke)
- Acute onset, and reversibility over days or weeks
- Hypertension
Radiological findings:
- On CT:
- Oedema is symmetric (bilateral)
- Posterior occipital or parietal distribution (but this is not essential): in fact three major anatomical patterns of distribution exist:
- holohemispheric
- superior frontal sulcal
- primary parietal-occipital
- On MRI:
- T1: hypointense in affected regions
- T1 C+ (Gd): patchy variable enhancement. It can be seen in ~35% of patients, whether leptomeningeal or cortical pattern.
- T2: hyperintense in affected regions
- DWI: usually normal
- ADC: signal increased in affected regions due to increased diffusion
- GRE: may show hypointense signal in cases of haemorrhage
- SWI: may show microhemorrhages in up to 50%
c) Management principles of PRES:
- Treat the cause
- Stop the causative drug.
- Deliver the baby (in eclampsia).
- Aggressively control the blood pressure.
- No specific guidelines or targets in the lierature
- Extrapolations from generic arterial hypertension guidelines:
- European guidelines (Williams et al, 2018): reduce MAP by 20–25% immediately
- American guidelines (Jones et al, 2025):
- Drop SBP by 25% from peak within the first hour
- Then to under SBP 160 / DBP 100 in the next 2-6 hrs
- Then to under SBP 130-140 over the next 24-48 hrs
- Choice of agent: labetalol + clevidipine (or nitroprusside)
- Prevent complications
- Give antiepileptics if seizures were a presenting problem.
- Intubate the patient to protect their airway and facilitate safe investigations.
- "Neuroprotective" ventilator targets, aiming to keep PEEP low, maintaning the CO2 in a 35-45 range.
- Treatment is mainly supportive
- Corticosteroids have been proposed as a potential specific management strategy but there is no compelling evidence
References
Srichawla, Bahadar S., Taranjit Kaur, and Harsimran Singh. "Corticosteroids in posterior reversible encephalopathy syndrome: Friend or foe? A systematic review." World Journal of Clinical Cases 13.12 (2025): 98768.
Triplett, James D., et al. "Posterior reversible encephalopathy syndrome (PRES): diagnosis and management." Practical neurology 22.3 (2022): 183-189.
Williams, Bryan, et al. "2018 ESC/ESH Guidelines for the management of arterial hypertension: The Task Force for the management of arterial hypertension of the European Society of Cardiology (ESC) and the European Society of Hypertension (ESH)." European heart journal 39.33 (2018): 3021-3104.
Writing Committee Members*, et al. "2025 AHA/ACC/AANP/AAPA/ABC/ACCP/ACPM/AGS/AMA/ASPC/NMA/PCNA/SGIM guideline for the prevention, detection, evaluation and management of high blood pressure in adults: a report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines." Circulation 152.11 (2025): e114-e218.
Question 24 - 2025, Paper 1
Discuss the role of decompressive hemicraniectomy following a middle cerebral artery infarction. In your answer, include the evidence for this practice.
(10 marks)
College comments
Syllabus topic/section: 2.1.8 Neurological Intensive Care L1 condition: acute cerebrovascular injury
Discussion:
This question invited candidates to discuss decompressive hemicraniectomy following middle cerebral artery infarction. A standard response was expected to cover the key principles, explore relevant controversies with advantages and disadvantages, and summarise current evidence.
Candidates who addressed the major domains outlined in the glossary of terms for a “discuss” question generally performed well. Those who incorporated evidence from individual trials and pooled analyses demonstrated a deeper understanding and scored higher than those who simply listed trial names. Responses that referenced evidence from decompressive craniectomy for traumatic brain injury or mechanical thrombectomy in stroke were not credited, as these were outside the scope of the question.
Answers that included vague statements - such as “decompressive craniectomy would be provided on a case- by-case basis”- without elaborating on the clinical factors guiding such decisions did not score as highly as candidates who gave a rationale for decision making.
Candidates must be careful with language/symbols that can be confused in the heat of the exam; for instance, symbols like “<” and “>” were incorrectly used by some candidates. Similarly, the terms morbidity and mortality were used interchangeably while summarising evidence.
Interpretation
A "Discuss" question with evidence might seem virtually indistinguishable from a "critically evaluate" question, and candidates may spent long hours considering the hidden meaning behind the decision to start this SAQ with this specific exam vocabulary term instead of the other.
Key principles:
- MCA infarction has high mortality (70%) and morbidity.
- Much of it is due to raised ICP and midline shift
- This could be relieved by decompressive craniectomy
Advantages and disadvantages:
- A mortality improvement is consistently seen in the literature
- For younger patients, an improved functional outcome is also possible
- The association between raised ICP and mortality seems to be genuine
- The procedure appears to be safe even following thrombolysis and while on antiplatelet agents
- The idea has a strong theoretical foundation
However:
- Highly invasive
- Potentially lifesaving but produces severely disabled survivors
- Complications of the procedure (seizures, hygroma, local wound and CNS infections and bone graft resorption).
- Slow recovery and long hospital stay
Relevant controversies:
- Unclear diagnostic and therapeutic criteria to identify those who would benefit (eg. on the basis of age or premorbid function)
- Unknown benefits in lower-resourced environments
- The effect of age on outcome is not fully understood
- The timing of the procedure remains debated (within 48 hrs vs later)
A summary of the current evidence:
- Four major studies from ~10-20 yrs ago: DESTINY trial (2007), DECIMAL trial (2007), HAMLET trial (2009), DESTINY II Trial (2014)
- These were very small (pooled analysis of the first three only totalled 93 patients)
- NNT = 2 for mortality, 4 for major disability and mortality combined
- DESTINY-II specifically looked at the older cohort (>60s) and found 38% of the survivors had a MRS outcome score of >3, i.e. over 60% of the survivors were severely disabled, even though the mortality improved from 70% to 33%
References
Wartenberg, Katja E. "Malignant middle cerebral artery infarction." Current opinion in critical care 18.2 (2012): 152-163.
Yang, Ming-Hao, et al. "Decompressive hemicraniectomy in patients with malignant middle cerebral artery infarction: A systematic review and meta-analysis." The Surgeon (2015).
Jüttler, Eric, et al. "Decompressive surgery for the treatment of malignant infarction of the middle cerebral artery (DESTINY) a randomized, controlled trial." Stroke 38.9 (2007): 2518-2525.
Jüttler, Eric, et al. "DESTINY II: DEcompressive Surgery for the Treatment of malignant INfarction of the middle cerebral arterY II." International Journal of Stroke 6.1 (2011): 79-86.
Vahedi, Katayoun, et al. "Sequential-design, multicenter, randomized, controlled trial of early decompressive craniectomy in malignant middle cerebral artery infarction (DECIMAL Trial)." Stroke 38.9 (2007): 2506-2517.
Hofmeijer, Jeannette, et al. "Surgical decompression for space-occupying cerebral infarction (the Hemicraniectomy After Middle Cerebral Artery infarction with Life-threatening Edema Trial [HAMLET]): a multicentre, open, randomised trial." The Lancet Neurology 8.4 (2009): 326-333.
Vahedi, Katayoun, et al. "Early decompressive surgery in malignant infarction of the middle cerebral artery: a pooled analysis of three randomised controlled trials." The Lancet Neurology 6.3 (2007): 215-222.
Slotty, Philipp Jörg, et al. "The influence of decompressive craniectomy for major stroke on early cerebral perfusion." Journal of neurosurgery (2015): 1-6.
Question 1 - 2025, Paper 2
A 60-year-old patient remains intubated with a reduced consciousness level 6 hours following endovascular clot retrieval (ECR) for an acute middle cerebral artery (MCA) stroke. Sedation was stopped immediately post procedure.
a. List six likely causes of the reduced conscious state (3 marks) b. Outline your assessment of this patient’s reduced conscious level (7 marks)
Discussion
Syllabus topic/section: 2.1.8 Neurological Intensive Care
This question was answered well by most candidates and was assessed to be an easy question to pass. Better marks were scored by candidates who described an assessment that was tailored to the clinical scenario, rather than a more generic description of how to assess someone with a decreased conscious state.
For instance, the above standard answer would include both stroke AND procedure related history with relevant details for investigations and examination.
Interpretation
a)
- Haemorrhagic transformation of the ifarct
- Cerebral oedema, malignant MCA, midline shift, herniation
- Reocclusion or initial incomplete revascularisation (eg. mTICI 1 or 2a)
- Cerebral artery dissection
- Seizures
- Vascular access site complications
b)
- History
- Duration from stroke onset to reperfusion
- Initial NIHSS score and GCS at presentation
- Aphasia pre-procedure
- Volume of the stroke on pre-procedure imaging (predictive of malignant MCA syndrome)
- History of sedation, anticoagulation, antiplatelet drugs, prehospital thrombolysis
- Procedural complexity
- Examination
- Reassessment of the GCSm serially
- Cranial nerve exam looking for features of herniation
- Motor examination looking for worsening of the pre-stroke power and tone
- Features of nonconvulsive seizures (dilated pupils, increased tone globally, clonus, hippus)
- Carotid auscultation (bruitt of dissection?)
- Investigations
- Neuroimaging: CT brain noncontrast, followed by a perfusion study, and then MRI if these do not reveal the cause
- Laboratory tests for distat possibilities such as coagulopathy, hyponatremia or hypernatremia, hypoglycaemia, and other metabolic causes of coma
- ECG to appreciate whether the patient remains in AF and could be at further risk of emboli
- TOE to determine whether intracardiac emboli are to be expected going forward
References
Leslie-Mazwi, Thabele, et al. "Post-thrombectomy management of the ELVO patient: Guidelines from the Society of NeuroInterventional Surgery." Journal of neurointerventional surgery 9.12 (2017): 1258-1266.
van de Graaf, Rob A., et al. "Periprocedural antithrombotic treatment during acute mechanical thrombectomy for ischemic stroke: a systematic review." Frontiers in neurology 9 (2018): 238.
Torbey, Michel T., et al. "Evidence-based guidelines for the management of large hemispheric infarction." Neurocritical care 22.1 (2015): 146-164.
Jung, Simon, et al. "Adverse Effect of Early Epileptic Seizures in Patients Receiving Endovascular Therapy for Acute Stroke." Stroke 43.6 (2012): 1584-1590.
Prabhakaran, Shyam, et al. "2026 Guideline for the Early Management of Patients With Acute Ischemic Stroke: A Guideline From the American Heart Association/American Stroke Association." Stroke 57 (2026).
Li, Xiangyu, et al. "The predictors and prognosis for unexpected reocclusion after mechanical thrombectomy: a meta-analysis." Annals of Translational Medicine 8.23 (2020): 1566.
Caldwell, Stephanie, et al. "Bridging the Distance for Ischaemic Stroke Treatment in Regional Australia: A Retrospective Cohort Study." Australian Journal of Rural Health 34.2 (2026): e70177.
Zaidat, Osama O., et al. "Recommendations on angiographic revascularization grading standards for acute ischemic stroke: a consensus statement." Stroke 44.9 (2013): 2650-2663.
Gurbani, Saumya S., et al. "Post-Stroke Thrombectomy Evaluation: Expected Findings and Unexpected Complications." RadioGraphics 46.1 (2025): e250045.
Shahid, Adnan H., et al. "Risk Factors of Futile Recanalization Following Endovascular Treatment in Patients With Large-Vessel Occlusion: Systematic Review and Meta-Analysis." Stroke: Vascular and Interventional Neurology 2.6 (2022): e000257.
Wang, Jeffrey Z., et al. "Incidence and management of seizures after ischemic stroke: systematic review and meta-analysis." Neurology 89.12 (2017): 1220-1228.
Shapiro, S. Z., et al. "Access-site complications in mechanical thrombectomy for acute ischemic stroke: a review of prospective trials." American Journal of Neuroradiology 41.3 (2020): 477-481.
Prabhakaran, Shyam, et al. "2026 Guideline for the early management of patients with acute ischemic stroke: a guideline from the American Heart Association/American Stroke Association." Stroke (2026).